ANAPC1 / Anaphase-promoting complex subunit 1 · IHC design guide

Design Immunohistochemistry for ANAPC1

Plan chromogenic ANAPC1 IHC in paraffin sections using the reported cytoplasmic staining in gastrointestinal tissues as a reference (HPA tissue IHC). Include controls and interpret intensity cautiously because antibody staining has low consistency with RNA data and awaits external verification (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ANAPC1 (IHC for ANAPC1): expected localisation Cytoplasmic staining in several tissues (HPA tissue IHC), antibody A03471-2, validated IHC image, and IHC protocol steps
Printable ANAPC1 IHC protocol sheet — expected localisation Cytoplasmic staining in several tissues (HPA tissue IHC), antibody A03471-2, controls and protocol steps. Open the full ANAPC1 IHC guide →

ANAPC1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in several tissues (HPA tissue IHC)
Staining pattern Cytoplasmic staining, most abundant in the GI tract (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A03471-2)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining has low consistency with RNA data (HPA tissue IHC)
Regulation No expression regulator annotated (UniProt)
Isoform / epitope No isoforms or cleavage annotated; epitope map unresolved (UniProt)
Section 1

Recommended ANAPC1 IHC & IF Protocols

The catalog antibody IHC-P protocol (datasheet A03471-2) is accompanied by published lung squamous cell carcinoma (PMC11951694) and hepatocellular carcinoma (PMC12142242) tissue protocols.

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human placenta tissue; fixative not specified (datasheet A03471-2)
FixationImage fixative and duration unreported (datasheet A03471-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A03471-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03471-2)
Primary antibodyRabbit anti-ANAPC1, 2-5 μg/ml (datasheet A03471-2)
Primary incubationOvernight at 4 °C (datasheet A03471-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A03471-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultANAPC1-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissue types, most abundant in gastrointestinal tract. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet A03471-2); the lung study also used EDTA but did not report its pH (PMC11951694).
Section 2

What Is the Expected ANAPC1 Staining Pattern?

In paraffin-section IHC, expect predominantly cytoplasmic ANAPC1 staining in several tissues, especially gastrointestinal glandular cells (HPA: tissue IHC profile). ANAPC1 has no annotated transmembrane segment, but UniProt does not assign a subcellular location (UniProt Q9H1A4 topology and subcellular record). Treat this pattern as a guide rather than definitive proof of specificity: HPA rates its tissue IHC “Approved” while reporting low consistency with RNA expression and pending external verification (HPA: tissue IHC reliability).

What am I looking at on my slide?
Strong cytoplasmic stain in appendix, colon, duodenum or rectum glandular cells (HPA: High).This matches the reported gastrointestinal pattern (HPA: tissue IHC). Compare signal with neighboring cells, morphology and controls before calling it specific; HPA's “Approved” rating still carries a low RNA-concordance caveat (HPA: reliability).
Cytoplasmic stain in esophageal squamous cells, gallbladder glandular cells, kidney tubule cells or pancreatic exocrine glandular cells (HPA: High).These are additional reported high-staining cell populations, so a positive result need not be confined to intestinal glands (HPA: tissue IHC). Judge the named cells rather than treating every cell in the section as an expected positive.
Predominantly nuclear or crisp plasma-membrane staining with little cytoplasmic signal.That distribution conflicts with the reported cytoplasmic tissue pattern (HPA: tissue IHC). A membrane-only interpretation also lacks support from ANAPC1's topology (UniProt Q9H1A4: no transmembrane segment). Check morphology and controls for artefact; the compartment mismatch alone does not identify its cause.
Strong stain in adipocytes or lung alveolar cells (HPA: Not detected).These populations are useful discordance checks because HPA reports no detectable tissue IHC staining in them (HPA: tissue IHC). Investigate nonspecific binding or endogenous chromogenic activity with controls; a discordant stain is a warning, not proof of cross-reactivity.
Haze across tissue and empty spaces, or no stain in a high-staining reference cell population.Diffuse haze impairs cell and compartment assignment (standard IHC interpretation). An absent signal in a listed high population conflicts with the HPA reference pattern (HPA: tissue IHC); review tissue preservation, retrieval, reagent performance and detection controls as general IHC checks.
💡Expected ANAPC1 appearanceCall a section concordant when cytoplasmic chromogen is clear in the listed high-staining epithelial or tubule cells (HPA: tissue IHC), with appropriately limited background; dominant nuclear or membrane-only staining, or strong adipocyte or alveolar staining, warrants review (HPA: cytoplasmic profile; Not detected populations).
How each factor affects the staining
Tissue and cell identityHPA reports high staining in eight named cell populations, including gastrointestinal glands, pancreatic exocrine glands and kidney tubules; adipocytes and alveolar cells are not detected (HPA: tissue IHC). Compare the same cell types across sections.
Evidence strengthThe tissue IHC profile is “Approved,” yet antibody staining has low consistency with RNA expression and awaits external verification (HPA: reliability). HPA lists three IHC-Approved antibodies—HPA036329, HPA036330 and HPA042998—but that status does not resolve a discordant slide.
Topology and processingUniProt lists no transmembrane segment, signal peptide, propeptide or cleaved chain (UniProt Q9H1A4). These facts give no basis to predict a surface-only or shed-product IHC pattern; they do not establish how a particular epitope survives tissue preparation.
Fixation and retrievalNo target-specific fixation sensitivity or retrieval condition is established by the supplied UniProt and HPA records. Assess retrieval with an appropriate positive tissue and controls as general IHC practice; do not infer a condition from staining intensity alone.
IF/ICC Q: Should vesicular fluorescence match tissue IHC exactly?A: HPA reports an approved vesicular ICC-IF location, while its tissue IHC profile is cytoplasmic (HPA: subcellular and tissue IHC). Interpret each observation in its own assay and specimen context; UniProt gives no independent subcellular annotation (UniProt Q9H1A4).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected glandular cells stain weakly or not at all (HPA: High).An ineffective IHC run, tissue quality issue or unsuitable retrieval may reduce visible signal (standard IHC practice); HPA does not identify ANAPC1-specific fixation sensitivity.Confirm morphology and a positive reference section, then review retrieval, antibody application and detection controls one variable at a time (standard IHC practice).
Only nuclei or cell borders stain strongly.The distribution conflicts with cytoplasmic tissue IHC (HPA: profile); UniProt has no transmembrane annotation (UniProt Q9H1A4). The image alone cannot distinguish artefact from antibody cross-reactivity.Recheck compartment boundaries with the counterstain and compare a listed high-staining population and assay controls (HPA: tissue IHC; standard IHC practice).
Adipocytes or alveolar cells show strong chromogen (HPA: Not detected).The result is discordant with HPA's reported cell-level negatives (HPA: tissue IHC); nonspecific antibody binding or endogenous detection activity are general IHC possibilities.Inspect a no-primary control and the distribution of chromogen, then review blocking and detection steps as general IHC checks. Do not score the discordant cells as validated ANAPC1 signal.
Broad, diffuse color obscures individual cells.Background may reflect excess antibody or insufficient blocking or washing (standard IHC practice); HPA's cytoplasmic profile cannot be assessed while boundaries are obscured (HPA: tissue IHC).Compare the no-primary control, optimize blocking and washing, and adjust antibody concentration using the catalog antibody's IHC-P guidance (standard IHC practice).
A weakly stained tissue is read as a failed positive.HPA reports only low staining in seminal-vesicle glands, ovarian stroma, endometrial glands, decidual cells, breast glands and tonsil germinal centers (HPA: tissue IHC).Use a listed high-staining cell population to judge run performance, and score the weak tissue against its own reported level and morphology (HPA: tissue IHC).
A convincing stain still disagrees with the expected distribution.HPA's “Approved” tissue profile has low consistency with RNA expression and is pending external verification (HPA: reliability). Visual intensity by itself cannot settle specificity.Document the cell type and compartment, compare suitable controls, and seek an independent antibody or orthogonal check before making a strong specificity claim (standard IHC validation practice).

Sample controls for ANAPC1 IHC & IF

🧪Run colon first and score glandular cells, which HPA rates High for ANAPC1 (HPA: Colon, glandular cells High). Use adipose tissue as the negative tissue and score adipocytes, which HPA lists as Not detected; on the colon slide, use nearby nonglandular areas to judge background without assuming those cells are ANAPC1-negative (HPA: Adipose tissue, adipocytes Not detected; HPA: Colon, glandular cells High).
Positive control tissue: Appendix (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ANAPC1 in A-431, U2OS, NIH 3T3, with annotated localisation: Vesicles (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and concentration-matched nonimmune rabbit IgG isotype controls, plus ANAPC1 knockout material or immunogen-peptide competition where available (selected-SKU caption: rabbit primary antibody; standard IHC controls). For chromogenic colon IHC, quench endogenous peroxidase and check that luminal material does not acquire nonspecific DAB signal (selected-SKU caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the selected-SKU paraffin-section caption does not state the fixative (selected-SKU caption: fixative unreported). That caption uses heat-mediated EDTA retrieval at pH 8.0, but it does not establish that retrieval is required for every specimen (selected-SKU caption: EDTA pH 8.0). The supplied evidence does not establish whether frozen sections or IF are easier than paraffin IHC; HPA reports vesicular ICC-IF localization in A-431, U2OS and NIH 3T3 cells, while colon IHC requires attention to nonspecific luminal DAB signal (HPA: subcellular ICC-IF; standard IHC practice).

HPA tissue IHC evidence for ANAPC1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Esophagus Squamous epithelial cells High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Lung Alveolar cells Not detected Protein (IHC) HPA →
Section 3

Advanced ANAPC1 IHC Tips

Troubleshoot ANAPC1 staining in paraffin sections using the catalog antibody’s tissue image, HPA observations, and appropriate IHC controls.

How should I adjust retrieval when ANAPC1 staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A03471-2). The selected tissue image used this retrieval before overnight incubation at 4°C with 2 μg/ml primary antibody (datasheet A03471-2). If staining remains weak, vary heating duration on adjacent sections while keeping detection and exposure comparable; assess tissue preservation alongside signal (standard IHC practice). Include a known staining tissue, such as colon glandular epithelium, to distinguish failed retrieval from low expression in the specimen (HPA: High in colon glandular cells; standard IHC practice). Record retrieval conditions for every slide so that apparent differences between specimens are interpretable (standard IHC practice).
Could fixation account for inconsistent ANAPC1 staining?
Target-specific sensitivity of ANAPC1 to fixation is unknown from the supplied evidence; the selected paraffin-section caption does not state its fixative (datasheet A03471-2). Record the fixative, fixation duration, and processing history for each specimen before comparing staining across blocks (standard IHC practice). When variability tracks processing, stain adjacent sections with the same EDTA pH 8.0 retrieval and 2 μg/ml primary antibody conditions used in the caption (datasheet A03471-2; standard IHC practice). Compare signal with tissue morphology and a consistent control section, because damaged morphology can make cellular scoring unreliable (standard IHC practice). Do not infer fixation sensitivity from tissue staining patterns or ANAPC1 sequence features (HPA tissue IHC; UniProt Q9H1A4).
What cellular pattern should I expect in ANAPC1 IHC?
Assess cytoplasmic staining within identifiable cells: HPA reports cytoplasmic expression across several tissues, particularly the gastrointestinal tract (HPA tissue IHC). HPA also reports vesicular localisation from ICC/IF images, but that observation does not establish a mandatory punctate pattern in chromogenic sections (HPA subcellular; standard IHC practice). UniProt supplies no subcellular annotation for ANAPC1 and lists no transmembrane segment, so avoid assigning a membrane compartment from sequence alone (UniProt Q9H1A4). Compare the cellular pattern with a matched positive section, such as colon glandular cells, and with primary-omission controls (HPA: High in colon glandular cells; standard IHC practice). Document diffuse and punctate components separately when morphology permits (standard IHC practice).
Could isoforms or epitope accessibility explain discordant staining?
The supplied UniProt record lists 0 isoforms, and the antibody caption does not identify its epitope (UniProt Q9H1A4; datasheet A03471-2). Therefore, do not attribute a difference between sections to a particular splice variant or epitope without independent evidence (UniProt Q9H1A4; standard IHC practice). ANAPC1 has annotated phosphosites, including serines 51 and 60, but their effect on this antibody’s tissue staining is unknown (UniProt Q9H1A4). If staining differs across preparations, first compare retrieval, primary incubation, and section quality using the same control tissue (datasheet A03471-2; standard IHC practice). Keep any proposed modification-dependent interpretation provisional until an epitope-specific validation supports it (standard IHC practice).
How can IF help investigate an ambiguous chromogenic ANAPC1 pattern?
Use IF as a complementary localisation check when the IHC cellular pattern is unclear, since HPA reports vesicular ICC/IF localisation (HPA subcellular; standard IHC practice). Multiplex ANAPC1 with a validated marker of the cell population being scored, such as glandular cells in colon, and include single-label controls (HPA: High in colon glandular cells; standard IF practice). Choose fluorophores in channels with low measured tissue autofluorescence, using unstained sections to establish that background (standard IF practice). ANAPC1 has no annotated transmembrane segment, so permeabilise cells to access an intracellular epitope while recognising that the antibody’s exact epitope is unspecified (UniProt Q9H1A4; datasheet A03471-2; standard IF practice). Do not directly equate IF puncta with DAB deposits without matched morphology (standard IHC/IF practice).
How do I troubleshoot diffuse brown signal in ANAPC1 sections?
Separate primary-dependent staining from detection background with a primary-omission section processed through the same secondary and DAB steps (standard IHC practice). The selected caption used 10% goat serum blocking, a peroxidase-conjugated secondary, and DAB chromogen, providing a starting point for this antibody (datasheet A03471-2). Quench endogenous peroxidase, check secondary-only staining, and shorten chromogen development if background obscures cellular boundaries (standard IHC practice). Keep the primary at the caption’s 2 μg/ml during initial troubleshooting, then titrate only after detection background is controlled (datasheet A03471-2; standard IHC practice). Treat staining concentrated at folds or damaged edges cautiously, since those areas can accumulate nonspecific signal (standard IHC practice).
What is a defensible way to quantify ANAPC1 IHC? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because HPA reports cytoplasmic tissue staining and differing levels among cell types (HPA tissue IHC; standard IHC practice). For glandular epithelium, report the percentage of positive glandular cells and an H-score from intensity categories applied consistently across slides (HPA: High in colon glandular cells; standard IHC practice). If counting discrete positive cells, report density per mm² of viable tissue and specify the counted compartment (standard IHC practice). Normalise comparisons to the number or area of evaluable target cells, rather than total section area when cellular composition differs (standard IHC practice). Use identical retrieval, development, and scoring thresholds across batches, with a shared control section (standard IHC practice).
When should I doubt an apparent ANAPC1-positive result?
Prioritise staining within intact cells and compare its distribution with HPA’s cytoplasmic tissue profile, while recognising that HPA calls its tissue evidence Approved with low staining-to-RNA consistency (HPA tissue IHC). High signal in colon glandular cells is plausible, whereas isolated strong signal in alveolar cells needs additional validation because HPA reports ANAPC1 as not detected there (HPA: High in colon glandular cells; HPA: Not detected in lung alveolar cells). Check primary-omission and peroxidase-block controls before interpreting brown deposits as antigen (standard IHC practice). Exclude section edges, folds, and necrotic areas from scoring when their morphology or background compromises interpretation (standard IHC practice). A mismatch with ICC/IF vesicular localisation alone does not prove an IHC artefact (HPA subcellular; standard IHC/IF practice).
Boster reagents

Best ANAPC1 / Anaphase-promoting complex subunit 1 IHC Antibodies

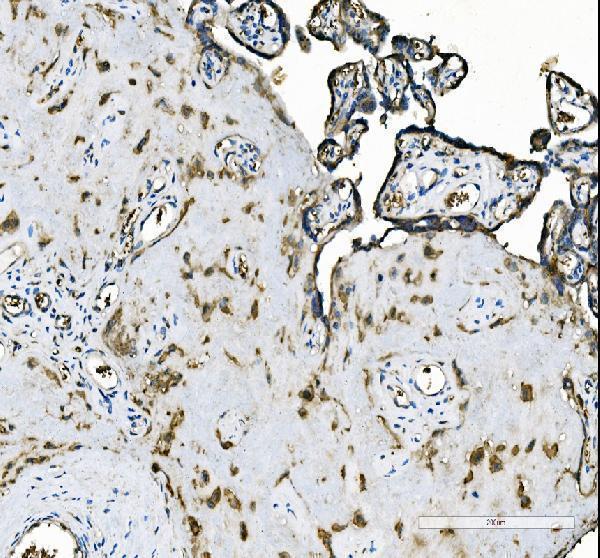
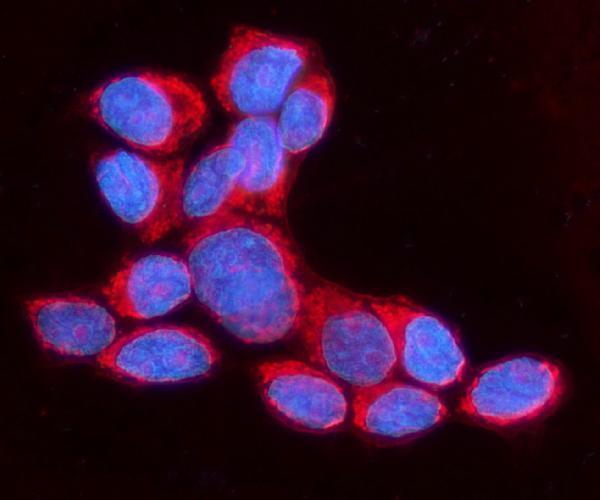
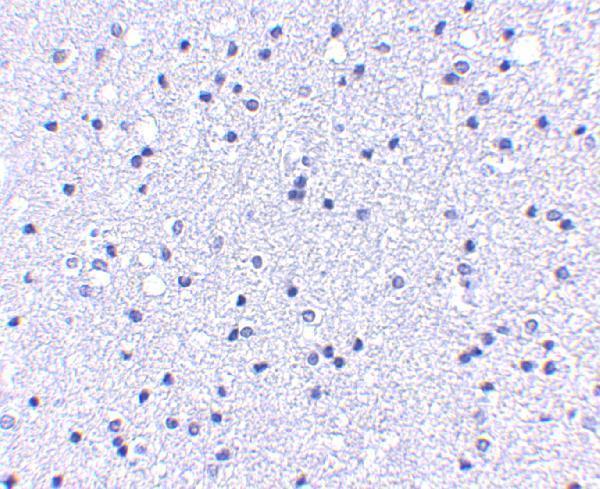
Two anti-ANAPC1 antibodies have human tissue IHC images: brain and paraffin-section placenta (catalog IHC captions: A03471, A03471-2). A03471-2 also has human MCF-7 IF data (catalog IF caption).

Real IHC data IHC analysis of APC1/ANAPC1 using anti-APC1/ANAPC1 antibody (A03471-2). APC1/ANAPC1 was detected in a paraffin-embedded section of human placenta tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-APC1/ANAPC1 Antibody (A03471-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-APC1/ANAPC1 Antibody ®
Cat # A03471-2
Real IHC data Immunohistochemistry of APC1 in human brain tissue with APC1 antibody at 5 μg/mL.
Anti-APC1 ANAPC1 Antibody
Cat # A03471

A03471 will render with human brain IHC data at 5 μg/mL (catalog IHC caption: A03471). A03471-2 will render with human placenta paraffin-section IHC data at 2 μg/ml; its separate IF image uses MCF-7 cells (catalog IHC and IF captions: A03471-2).

Which to pick: For tissue IHC, choose A03471-2 when a documented paraffin-section workflow matters (catalog IHC caption: A03471-2); A03471 has a human brain IHC image, but its section processing is unreported (catalog IHC caption: A03471). Choose A03471-2 for IF/ICC because those applications are listed and an MCF-7 IF image is provided (catalog applications and IF caption: A03471-2). For mouse samples, A03471 lists mouse reactivity, though its pictured IHC validation is human; both antibodies are rabbit-hosted, clonality is unreported, and the IHC captions do not report a fixative (catalog reactivity, host and clone fields; catalog IHC captions: A03471, A03471-2).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9H1A4 (APC1_HUMAN, Anaphase-promoting complex subunit 1).
  2. Human Protein Atlas. ANAPC1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. ANAPC1 subcellular location (ICC-IF): Localized to vesicles..
  4. Human Protein Atlas. ANAPC1 antibody validation summary (3 antibodies).
  5. The Potential Biological Roles and Clinical Significance of Anaphase-Promoting Complex Subunit 1 in Colorectal Cancer. Cancer control : journal of the Moffitt Cancer Center 2025 — PMC12033653.
  6. Elevated expression of ANAPC1 in lung squamous cell carcinoma: clinical implications and mechanisms. Future science OA 2025 — PMC11951694.
  7. Exploring the potential function of high expression of ANAPC1 in regulating ubiquitination in hepatocellular carcinoma. World journal of gastrointestinal oncology 2025 — PMC12142242.
  8. PubMed PMID:11179667 — UniProt-cited evidence.
  9. PubMed PMID:15489334 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.