ATG12 / Ubiquitin-like protein ATG12 · IHC design guide

Design Immunohistochemistry for ATG12

Plan chromogenic ATG12 IHC in paraffin sections using 2.5 μg/mL as the starting concentration for A00820 (datasheet: IHC). Kidney tubules and lung macrophages show high staining, but the tissue profile has uncertain reliability (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ATG12 (IHC for ATG12): expected localisation Cytoplasmic and nuclear tissue staining (HPA tissue IHC), antibody A00820, validated IHC image, and IHC protocol steps
Printable ATG12 IHC protocol sheet — expected localisation Cytoplasmic and nuclear tissue staining (HPA tissue IHC), antibody A00820, controls and protocol steps. Open the full ATG12 IHC guide →

ATG12 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and nuclear tissue staining (HPA tissue IHC)
Staining pattern Glandular cells and macrophages; cytoplasmic/nuclear signal (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Oral mucosa+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Tissue staining awaits external verification (HPA tissue IHC)
Regulation Induction not reported (UniProt)
Isoform / epitope 2 isoforms; epitope coverage needs assessment (UniProt)
Section 1

Recommended ATG12 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is paired with one published chromogenic IHC protocol for ATG12 in OSCC tissues and MNTs (PMC8093968).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A00820); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-ATG12, 2.5 μg/mL (datasheet A00820)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultATG12-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic and nuclear expression in several tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page antigen retrieval); the published protocol uses pressure-cooker retrieval for 13 min (PMC8093968).
Section 2

What Is the Expected ATG12 Staining Pattern?

ATG12 is cytoplasmic and associates with preautophagosomal structure membranes (UniProt O94817). In paraffin sections, expect staining in glandular cells, kidney tubule cells, lung macrophages, and skeletal myocytes reported as High by HPA (HPA: tissue IHC). ATG12 has no transmembrane segment (UniProt O94817 topology). Interpret the pattern cautiously: HPA rates its tissue IHC reliability Uncertain, with medium agreement between staining and RNA data pending external verification (HPA: tissue IHC reliability).

What am I looking at on my slide?
Cytoplasmic staining in colon or duodenal glandular cells, kidney tubule cells, or lung macrophages.This fits reported High staining in those cells (HPA: tissue IHC). A vesicular component is biologically plausible given ATG12's preautophagosomal association (UniProt O94817), but tissue IHC alone does not identify individual vesicles.
Predominantly nuclear staining, or a sharp cell-surface rim without convincing cytoplasmic signal.Treat this as inconclusive rather than an expected dominant pattern: UniProt places ATG12 in the cytoplasm and on preautophagosomal structure membranes (UniProt O94817). HPA also reports nuclear tissue staining and an uncertain nucleoplasmic IF location, so nuclear signal alone does not prove an artefact (HPA: tissue IHC; HPA: subcellular).
Strong signal in skin keratinocytes or oral squamous epithelial cells.These cells were Not detected in HPA tissue IHC (HPA: skin and oral mucosa). Check cross-reactivity and endogenous chromogen-producing activity with appropriate controls (general IHC practice); a discrepancy is not definitive because HPA rates the tissue profile Uncertain (HPA: tissue IHC reliability).
Diffuse color across cells and surrounding section, obscuring cell boundaries.This limits compartment and cell-type interpretation (general IHC practice). Compare a primary-antibody omission control and review blocking, washes, and detection conditions for nonspecific or endogenous signal (general IHC practice).
No staining in colon glandular cells or kidney tubule cells.Both are reported High by HPA (HPA: colon and kidney). Check an on-slide positive control, antibody dilution, antigen retrieval, and detection workflow (general IHC practice). HPA's Uncertain reliability limits how strongly one negative specimen can be judged (HPA: tissue IHC reliability).
💡Expected ATG12 appearanceA convincing positive is mainly cytoplasmic staining in a reported High cell population, such as kidney tubule cells or lung macrophages (HPA: tissue IHC; UniProt O94817); diffuse section-wide color or equally strong staining in HPA Not detected keratinocytes warrants control-based review (HPA: skin; general IHC practice).
How each factor affects the staining
Compartment and molecular formATG12 is cytoplasmic, associates with preautophagosomal structure membranes, and forms an ATG12–ATG5 conjugate (UniProt O94817). A chromogenic section cannot establish whether a stained structure contains free or conjugated ATG12 (general IHC interpretation).
Tissue contrastHPA reports High staining in several cell populations, Low staining in some neuronal and squamous populations, and Not detected staining in skin keratinocytes and oral squamous cells (HPA: tissue IHC). Its overall tissue reliability is Uncertain (HPA: tissue IHC reliability).
Antibody evidenceCAB013272 has Uncertain IHC validation; HPA068989 has Supported ICC validation and no listed IHC status (HPA: antibody validation). Do not transfer ICC validation to an IHC interpretation (general assay interpretation).
Isoforms and epitope coverageUniProt lists 2 ATG12 isoforms (UniProt O94817). The supplied evidence gives no epitope location, so it cannot establish whether an antibody detects both isoforms or how isoforms affect the slide pattern.
IF/ICC Q&A: should IF show the same pattern?HPA reports vesicles as a supported IF location and nucleoplasm as uncertain, with images from SiHa, U-251MG, and U2OS (HPA: subcellular ICC-IF). Those IF observations can inform interpretation but do not set an IHC nuclear-staining requirement (general assay interpretation).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive tissue appears blank.A workflow failure is possible; HPA reports High staining in colon glandular cells and kidney tubule cells, with Uncertain overall reliability (HPA: tissue IHC).Confirm the positive-control section and detection reagents, then review the antibody dilution and antigen-retrieval conditions (general IHC practice). Do not assign an ATG12-specific retrieval failure without evidence.
Color appears throughout the section, including empty or damaged areas.Background or endogenous detection activity can obscure cell-associated staining (general IHC practice).Compare a primary-antibody omission control; review blocking, washes, and chromogen exposure (general IHC practice). Score only interpretable cellular signal.
Skin keratinocytes stain as strongly as the positive control.HPA reports keratinocytes as Not detected, so nonspecific staining or endogenous activity is possible; the HPA tissue profile remains Uncertain (HPA: skin; HPA: tissue IHC reliability).Inspect controls and compare the staining distribution with a reported High cell population in the same run (HPA: tissue IHC; general IHC practice).
The apparent signal is exclusively nuclear.HPA describes nuclear tissue staining and uncertain nucleoplasmic IF localization, while UniProt places ATG12 in the cytoplasm (HPA: tissue IHC; HPA: subcellular; UniProt O94817).Report nuclear staining separately; check controls and seek corroboration before calling it the expected ATG12 IHC pattern (general IHC interpretation).
Scattered puncta are the only positive features.ATG12 associates with preautophagosomal structure membranes, and HPA supports vesicular IF localization; chromogenic puncta alone cannot identify an organelle (UniProt O94817; HPA: subcellular).Check that puncta occur in a reported positive cell type and exceed control background; avoid assigning a specific vesicle identity from IHC alone (HPA: tissue IHC; general IHC interpretation).
Two tissue samples give different staining intensities.HPA reports High, Low, and Not detected cell populations despite low tissue RNA specificity (HPA: tissue IHC). Its staining profile has Uncertain reliability (HPA: tissue IHC reliability).Compare the same cell types, controls, and scoring criteria across sections before attributing the difference to ATG12 expression (general IHC practice).

Sample controls for ATG12 IHC & IF

🧪Run kidney first: tubular cells should stain (HPA: High in cells in tubules). Use skin keratinocytes as the negative tissue (HPA: Not detected); the supplied kidney data do not identify an internal negative cell population, so cells without specific chromogen but with intact counterstain are only candidate internal negatives (HPA: kidney tubular-cell row).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Oral mucosa (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ATG12 in SiHa, U-251MG, U2OS, with annotated localisation: Nucleoplasm (uncertain), Vesicles (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide, a host- and immunoglobulin-matched isotype control, and an ATG12-knockout biological control (standard IHC practice). Block endogenous peroxidase and, if using biotin-based detection, endogenous biotin in kidney; compare any residual tubular signal with the controls (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A00820 brain IHC caption does not state a fixative (caption: fixative not stated). ATG12-specific retrieval dependence is unreported; the supplied evidence does not establish whether frozen sections or IF are easier (supplied target/application evidence). Renal tubular staining needs careful interpretation because endogenous peroxidase or biotin can contribute signal (standard IHC practice).

HPA tissue IHC evidence for ATG12

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Cerebral cortex Neuropil High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Kidney Cells in tubules High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Oral mucosa Squamous epithelial cells Not detected Protein (IHC) HPA →
Skin Keratinocytes Not detected Protein (IHC) HPA →
Section 3

Advanced ATG12 IHC Tips

Troubleshoot ATG12 staining in chromogenic paraffin IHC by checking retrieval, cellular distribution, controls and scoring against the available evidence.

How should I retrieve ATG12 when staining is weak in paraffin sections?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 min (page retrieval protocol). If signal remains weak, compare a modestly longer heating period on matched sections while holding antibody concentration and detection conditions constant (standard IHC practice). Cool sections consistently after heating, then check whether tissue morphology and positive control staining remain intact (standard IHC practice). ATG12 has no transmembrane segment and is reported in the cytoplasm and at preautophagosomal membranes (UniProt O94817 topology and localisation); those annotations do not establish its retrieval sensitivity. Record the condition used for every scored section.
Could fixation explain inconsistent ATG12 staining between paraffin blocks?
Target-specific fixation sensitivity for ATG12 is unknown from the supplied evidence; do not infer it from tissue staining patterns or protein annotations. Compare blocks with documented fixation and processing histories, using matched sections and the same retrieval, antibody incubation and detection run (standard IHC practice). Inconsistent staining may reflect processing differences, so examine preserved morphology and an on-slide positive control before changing the ATG12 antibody concentration (standard IHC practice). The selected tissue image reports ATG12 staining in human brain at 2.5 µg/mL but does not state its fixative (A00820 tissue-IHC caption). Treat that concentration as an image condition, not a fixation recommendation.
Which cellular pattern should I expect for ATG12 in chromogenic IHC?
Assess cytoplasmic and vesicle-associated staining first: ATG12 is annotated in the cytoplasm and at preautophagosomal membranes (UniProt O94817 localisation). The ATG12–ATG5 conjugate can be recruited to autolysosomal membranes by TECPR1 (UniProt O94817 subunit and localisation), so discrete intracellular staining merits review alongside diffuse signal. Nuclear staining needs caution: tissue IHC reports cytoplasmic and nuclear expression, while nucleoplasmic localisation is marked uncertain in the subcellular data (HPA tissue IHC; HPA subcellular). Compare cellular staining with a no-primary control and inspect nuclei against the counterstain (standard IHC practice). Do not score pigment, precipitate or staining outside identifiable cells as ATG12 (standard IHC practice).
Can the ATG12 epitope or isoform affect paraffin-section staining?
ATG12 has 2 listed isoforms, but the supplied evidence does not map this antibody’s epitope or establish isoform recognition (UniProt O94817 isoforms; A00820 tissue-IHC caption). Ask for an epitope map or validation data before interpreting differences between samples as isoform-specific staining (standard IHC practice). The annotated protein has no transmembrane segment, glycosylation sites or modified residues in the supplied record (UniProt O94817 topology and annotations); these facts do not predict epitope survival during processing. ATG12 also forms a conjugate with ATG5 (UniProt O94817 subunit), which may change antigen accessibility. Evaluate staining with matched retrieval and controls before assigning a molecular cause.
How can I compare ATG12 IHC with a multiplex IF experiment?
Use the IF experiment as a separate validation exercise because the selected antibody evidence describes tissue IHC, not an IF protocol (A00820 tissue-IHC caption). In lung, multiplex ATG12 with a macrophage lineage marker to check the cell population where tissue IHC reports high expression (HPA tissue IHC: lung macrophages). Choose fluorophores after measuring tissue autofluorescence, and include single-stain and no-primary controls to assess spectral overlap and background (standard IF practice). ATG12 has no transmembrane segment and is annotated in the cytoplasm and at preautophagosomal membranes (UniProt O94817 topology and localisation); use controlled permeabilisation to access intracellular epitopes. Optimise IF fixation independently; no directly relevant fixation condition is supplied.
What should I change when ATG12 chromogenic staining is widespread or patchy?
First compare the no-primary control and inspect whether colour follows tissue edges, folds or damaged areas (standard IHC practice). Block endogenous peroxidase before a peroxidase-based chromogenic detection step, then check whether the same deposits persist without primary antibody (standard IHC practice). Optimise primary antibody concentration and blocking on adjacent sections while keeping retrieval and development time fixed (standard IHC practice). Widespread staining alone is inconclusive because ATG12 is annotated as ubiquitous, and tissue IHC reports expression across several tissues (UniProt O94817 tissue specificity; HPA tissue IHC). The catalog image used 2.5 µg/mL in human brain; it does not establish a universal working concentration (A00820 tissue-IHC caption).
How should I quantify ATG12 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cellular compartment and region before scoring, then apply the same segmentation and chromogen threshold to every section (standard IHC practice). For identifiable cells, report the percentage positive and an H-score based on staining intensity; for area-based analysis, report positive-cell density per mm² of viable tissue (standard IHC practice). Normalise counts to the number of eligible cells or measured viable area, and exclude folds, necrosis and tissue loss consistently (standard IHC practice). Report cytoplasmic and nuclear measurements separately because tissue IHC describes both, while nucleoplasmic localisation remains uncertain (HPA tissue IHC; HPA subcellular). Include control performance and acquisition settings with each comparison.
How can I distinguish credible ATG12 signal from staining artefact?
Give greatest weight to reproducible staining in identifiable cells with appropriate morphology and a clean no-primary control (standard IHC practice). Cytoplasmic or vesicle-associated signal fits the protein annotation; nuclear signal requires separate scrutiny because the subcellular nucleoplasm assignment is uncertain (UniProt O94817 localisation; HPA subcellular). Compare cell identity with the reference pattern: tissue IHC reports high staining in lung macrophages and kidney tubule cells, but no detection in skin keratinocytes (HPA tissue IHC). Investigate edge effects, necrotic regions, pigment and residual endogenous peroxidase before calling focal chromogen positive (standard IHC practice). Interpret agreement cautiously because the tissue IHC reliability is rated uncertain (HPA tissue IHC reliability).
Boster reagents

Best ATG12 / Ubiquitin-like protein ATG12 IHC Antibodies

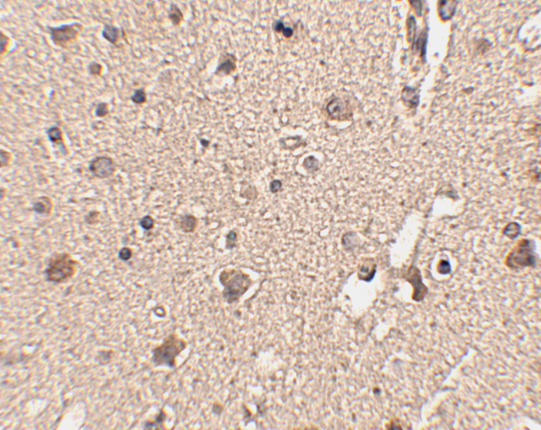
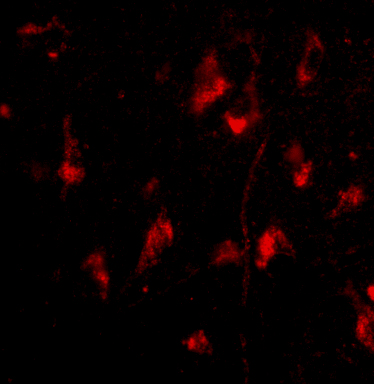
A00820 has IHC data in human brain tissue and IF data in human brain cells (catalog image captions); its listed reactivity covers human, mouse, and rat (catalog reactivity).

Real IHC data Immunohistochemistry of ATG12 in human brain tissue with ATG12 antibody at 2.5 μg/mL.
Anti-Ubiquitin-like protein ATG12 ATG12 Antibody
Cat # A00820

Only A00820 renders: its IHC figure shows human brain tissue at 2.5 μg/mL (catalog IHC caption). Its IF figure shows human brain cells at 20 μg/mL (catalog IF caption).

Which to pick: Choose A00820 for paraffin-section IHC: IHC-P is listed and its own IHC figure shows human brain tissue; the fixative is unreported (catalog applications; catalog IHC caption). For IF, choose A00820 based on its human brain-cell figure; M00820 and M00820-2 list ICC/IF but have no supplied figures (catalog IF caption; catalog applications and image alts). For mouse or rat samples, A00820 is the listed cross-species option, though its supplied figures show human samples (catalog reactivity; catalog image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O94817 (ATG12_HUMAN, Ubiquitin-like protein ATG12).
  2. Human Protein Atlas. ATG12 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. ATG12 subcellular location (ICC-IF): Localized to the nucleoplasm and vesicles..
  4. Human Protein Atlas. ATG12 antibody validation summary (2 antibodies).
  5. Erb-b2 Receptor Tyrosine Kinase 2 (ERBB2) Promotes ATG12-Dependent Autophagy Contributing to Treatment Resistance of Breast Cancer Cells. Cancers 2021 — PMC7958130.
  6. Screening and identification of autophagy-related biomarkers for oral squamous cell carcinoma (OSCC) via integrated bioinformatics analysis. Journal of cellular and molecular medicine 2021 — PMC8093968.
  7. Long noncoding RNA MALAT1 regulates autophagy associated chemoresistance via miR-23b-3p sequestration in gastric cancer. Molecular cancer 2017 — PMC5699172.
  8. The Steroid Hormone 20-Hydroxyecdysone Regulates the Conjugation of Autophagy-Related Proteins 12 and 5 in a Concentration and Time-Dependent Manner to Promote Insect Midgut Programmed Cell Death. Frontiers in endocrinology 2018 — PMC5808327.
  9. PubMed PMID:9852036 — UniProt-cited evidence.
  10. PubMed PMID:15372022 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.