BRD7 / Bromodomain-containing protein 7 · IHC design guide

Design Immunohistochemistry for BRD7

Plan BRD7 chromogenic IHC around the widespread nuclear staining observed in tissues (HPA tissue IHC). Start with the catalog antibody at 0.5–1 μg/ml on paraffin sections (datasheet A01289-1), and assess nuclear signal against a negative control (standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for BRD7 (IHC for BRD7): expected localisation Nuclear staining in tissue (HPA tissue IHC), antibody A01289-1, validated IHC image, and IHC protocol steps
Printable BRD7 IHC protocol sheet — expected localisation Nuclear staining in tissue (HPA tissue IHC), antibody A01289-1, controls and protocol steps. Open the full BRD7 IHC guide →

BRD7 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in tissue (HPA tissue IHC)
Staining pattern Widespread nuclear staining across cell types (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A01289-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Adipocytes may show no detectable staining (HPA tissue IHC)
Regulation Expression regulation unreported (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended BRD7 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is followed by four published BRD7 IHC protocols covering osteosarcoma, hepatocellular carcinoma, paraffin sections, and human cartilage (PMC4102794; PMC4941311; PMC5938698; PMC10292652).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon cancer tissue; fixative not specified (datasheet A01289-1)
FixationImage fixative and duration unreported (datasheet A01289-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A01289-1)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01289-1)
Primary antibodyRabbit anti-BRD7, 0.5-1μg/ml (datasheet A01289-1)
Primary incubationOvernight at 4 °C (datasheet A01289-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A01289-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultBRD7-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat retrieval in citrate at pH 6 for the catalog antibody (datasheet: citrate pH 6); EDTA at pH 8.0 is a published alternative (PMC4941311).
Section 2

What Is the Expected BRD7 Staining Pattern?

BRD7 should appear chiefly in nuclei across many cell types in paraffin sections (HPA: ubiquitous nuclear expression; UniProt Q9NPI1: nucleus, chromosome). Strong examples include colon glandular cells, bronchial respiratory epithelial cells, and bone marrow hematopoietic cells (HPA: High in each). HPA rates the tissue staining evidence Enhanced, with high consistency between antibody staining and RNA expression (HPA: Enhanced). BRD7 has no transmembrane segment (UniProt Q9NPI1: topology).

What am I looking at on my slide?
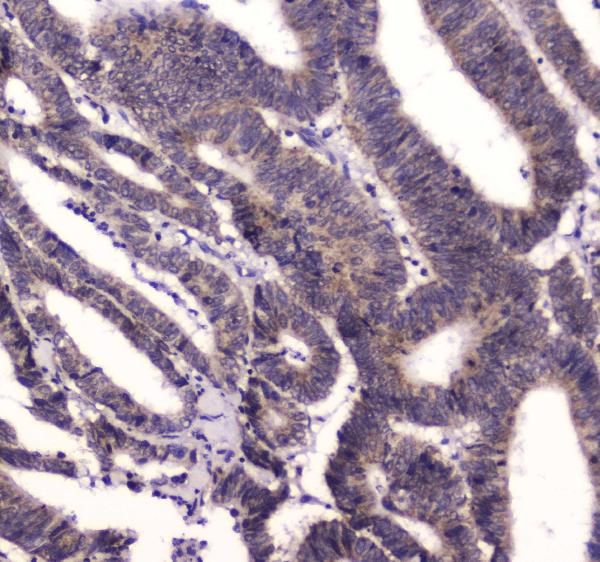
Brown signal is concentrated in nuclei of colon glandular cells, with visible counterstained tissue structure.This fits the expected compartment and a documented strong cell type (UniProt Q9NPI1: nucleus; HPA: High in colon glandular cells). Judge nuclear signal against nearby background, since a dark section alone does not establish specific staining (general IHC practice).
Most signal fills cytoplasm or outlines cell membranes while nuclei remain pale.This conflicts with the principal IHC pattern (HPA: ubiquitous nuclear expression; UniProt Q9NPI1: nucleus, chromosome). Check detection controls and slide preparation before interpreting it as BRD7; HPA reports an uncertain additional cytosolic location in ICC-IF, which does not establish a dominant cytoplasmic pattern in paraffin IHC (HPA: subcellular ICC-IF).
Strong brown staining appears in adipocytes, while expected nuclear staining elsewhere is weak or absent.Adipocytes are listed as not detected in the supplied tissue profile (HPA: adipose tissue, adipocytes). Consider cross-reactivity or endogenous detection activity, and compare a no-primary control before assigning the signal to BRD7 (general IHC practice).
Brown haze covers nuclei, cytoplasm, and spaces between cells without clear cell boundaries.Diffuse staining makes nuclear localisation hard to assess; it can reflect nonspecific binding or detection background (general IHC practice). Compare the no-primary control and the expected nuclear distribution before scoring (HPA: ubiquitous nuclear expression).
A colon section has no convincing nuclear signal in glandular cells.That is unexpected for this documented high-staining cell type (HPA: High in colon glandular cells). First check tissue quality, retrieval, antibody and detection controls; a blank slide by itself cannot distinguish technical failure from a true negative (general IHC practice).
💡Expected BRD7 appearanceCall a result positive when distinct nuclear chromogen is visible in expected cells, such as strongly stained colon glandular cells (HPA: High in colon glandular cells; HPA: ubiquitous nuclear expression); predominant membrane staining or diffuse brown haze is suspect (UniProt Q9NPI1: nucleus, no transmembrane segment; general IHC practice).
How each factor affects the staining
Compartment and chromatin associationNuclear and chromosome annotations support a nucleus-led readout (UniProt Q9NPI1: subcellular location). BRD7 interacts with acetylated histone H3 through its bromodomain (UniProt Q9NPI1: subunit), but the supplied record does not define a distinctive intranuclear staining texture.
Tissue and cell choiceColon glandular cells, bronchial respiratory epithelial cells, and bone marrow hematopoietic cells are documented High examples (HPA: tissue IHC). Adipocytes are not detected and hippocampal glial cells are listed as low; neither is a strong positive benchmark (HPA: tissue IHC).
Antibody evidenceThe tissue profile has Enhanced reliability (HPA: tissue IHC). Among the listed antibodies, CAB046458 has IHC Enhanced status; HPA042389 and HPA060171 have ICC Enhanced status without an IHC status in this payload (HPA: antibody validation). Treat validation as application specific.
Isoforms and processingUniProt lists 2 isoforms and a full-length chain, with no signal peptide or propeptide (UniProt Q9NPI1: isoforms, processing). No antibody epitope is supplied, so the record cannot establish isoform coverage or an epitope-dependent staining difference.
Fixation and retrieval evidenceTarget-specific fixation sensitivity and an antigen-retrieval condition are unreported in the supplied UniProt and HPA records. Any retrieval comparison is a general paraffin-IHC optimisation step; do not infer an effect on BRD7 from its topology, modifications, or HPA tissue intensity.
IF/ICC Q&A: where should BRD7 appear?Mainly in nucleoplasm (HPA: supported ICC-IF location). HPA also lists cytosol as an uncertain additional location; that qualifier should accompany any cytosolic IF interpretation (HPA: subcellular ICC-IF). This observation does not set an IHC protocol condition.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Colon glandular cell nuclei are blank.Possible section, staining, or detection failure; colon glandular cells are normally High in the supplied profile (HPA: tissue IHC; general IHC practice).Review tissue morphology and staining controls, then check the antibody dilution and retrieval settings against the actual IHC-P protocol; no dilution or retrieval setting is supplied here (general IHC practice).
Only membrane edges stain.A membrane-led pattern conflicts with nuclear BRD7 and its lack of a transmembrane segment (UniProt Q9NPI1: location, topology).Compare a no-primary control and another expected-positive section; check for detection background before interpreting the edge signal (general IHC practice; HPA: High in colon glandular cells).
Adipocytes stain strongly.The supplied tissue profile reports adipocytes as not detected; cross-reactivity or endogenous activity is plausible (HPA: adipose tissue; general IHC practice).Inspect the no-primary control and other cell types on the section; do not score adipocyte colour alone as specific BRD7 (general IHC practice; HPA: adipocytes not detected).
Brown haze obscures nuclear boundaries.Nonspecific binding or excess chromogen development can obscure compartment assessment (general IHC practice).Check the no-primary control, blocking and detection conditions, then adjust the assay to recover discrete nuclear contrast (general IHC practice; HPA: ubiquitous nuclear expression).
Nuclear signal varies between tissues.The profile spans High examples, low hippocampal glial cells, and undetected adipocytes (HPA: tissue IHC); tissue-wide uniform intensity is not established.Compare the same named cell types and controls across sections; record nuclear intensity by cell population before calling a run inconsistent (general IHC practice; HPA: tissue IHC).
A proposed IF/ICC image shows cytosol brighter than nuclei.HPA supports nucleoplasm as the main ICC-IF location and marks cytosol uncertain (HPA: subcellular ICC-IF).Recheck channel background and nuclear counterstain, then report the cytosolic observation with the HPA uncertainty qualifier; assess IHC sections against their nuclear tissue pattern (general IF practice; HPA: tissue IHC).

Sample controls for BRD7 IHC & IF

🧪Run adrenal gland first and expect staining in glandular cells (HPA: High in adrenal gland glandular cells). Run adipose tissue as the negative tissue (HPA: Not detected in adipocytes); any unstained cells within the adrenal section should retain counterstain without BRD7 nuclear signal (UniProt Q9NPI1: nucleus).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show BRD7 in CACO-2, Hep-G2, U2OS, HEK293, KOLF2.1J, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include no-primary/secondary-only and rabbit IgG isotype controls matched to the primary antibody’s class and clonality (selected SKU caption: rabbit anti-BRD7), plus a BRD7 knockout sample as a biological negative. For the adrenal slide, block endogenous peroxidase and check for endogenous biotin when using the caption’s biotin-based DAB detection (selected SKU caption: biotinylated secondary, streptavidin-biotin complex and DAB).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported, and the selected SKU caption does not state the fixative (selected SKU caption: fixative not stated). The paraffin-section example uses citrate retrieval at pH 6 for 20 minutes, but whether BRD7 detection depends on that retrieval is unreported (selected SKU caption: citrate retrieval). Frozen sections and IF cannot be judged easier from the supplied evidence; no adrenal-specific artefact is reported (HPA: adrenal gland IHC; HPA: ICC-IF images).

HPA tissue IHC evidence for BRD7

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced BRD7 IHC Tips

Troubleshoot BRD7 staining by checking retrieval, nuclear localization, controls, and scoring against the evidence available for paraffin-section IHC.

What retrieval conditions should I try when BRD7 staining is weak?
Start with heat-mediated retrieval in citrate buffer at pH 6 for 20 minutes (datasheet A01289-1). The catalog antibody produced staining in a paraffin-embedded human colon cancer section after that treatment, followed by 1 μg/ml primary antibody overnight at 4°C (datasheet A01289-1). If nuclear staining remains weak, check heating consistency, section attachment, and whether the primary incubation matches the documented condition before testing another retrieval buffer as a fallback (standard IHC practice). Compare any retrieval changes on adjacent sections with identical detection and counterstaining, assessing nuclear signal against background and tissue morphology (standard IHC practice; HPA: ubiquitous nuclear expression).
Could fixation explain absent or uneven BRD7 staining?
BRD7-specific fixation sensitivity is unknown because the selected paraffin-section caption does not state the fixative (datasheet A01289-1). Record the actual fixative and fixation history for each specimen, then compare similarly processed sections using citrate pH 6 retrieval for 20 minutes and the same detection run (datasheet A01289-1; standard IHC practice). Variable nuclear signal across differently processed samples can reflect preanalytic variation, so inspect tissue preservation and avoid assigning the difference to BRD7 biology without matched controls (standard IHC practice). Neither BRD7 topology nor its modified residues establishes how this antibody responds to fixation (UniProt Q9NPI1: topology and modified residues).
How should I assess strong cytoplasmic BRD7 staining in a paraffin section?
Prioritize nuclear staining when evaluating chromogenic BRD7 IHC: UniProt places BRD7 in the nucleus and on chromosomes, and HPA describes ubiquitous nuclear tissue expression (UniProt Q9NPI1: subcellular location; HPA: tissue IHC). HPA reports nucleoplasmic localization in cell imaging, with additional cytosolic localization marked uncertain, so cytoplasmic DAB alone warrants scrutiny rather than automatic acceptance (HPA: subcellular). Check whether the apparent cytoplasmic signal tracks section folds, damaged regions, or diffuse background, and compare it with a no-primary control (standard IHC practice). Use the nuclear pattern in intact cells and the documented colon cancer section as reference points, without treating either as proof of every specimen’s specificity (HPA: tissue IHC; datasheet A01289-1).
Can a negative BRD7 stain reflect isoform or epitope differences?
BRD7 has 2 annotated isoforms, and its bromodomain spans residues 131–235; the supplied antibody caption does not identify its binding epitope (UniProt Q9NPI1: isoforms and domains; datasheet A01289-1). Consequently, a negative section cannot distinguish absent protein from an inaccessible or missing epitope without further validation (standard IHC practice). Compare adjacent sections under the documented citrate pH 6, 20-minute retrieval condition, with a known staining section in the same run (datasheet A01289-1; standard IHC practice). If an independent antibody with a documented different epitope is available, compare nuclear staining patterns while recording each reagent’s own tissue validation (standard IHC practice; HPA: ubiquitous nuclear expression).
How can I check a BRD7 result by multiplex immunofluorescence?
On the separate IF/ICC guide, pair BRD7 with a marker identifying the expected cell population; for colon sections, HPA reports high BRD7 staining in glandular cells (HPA: colon glandular cells, High). Choose spectrally separated fluorophores and consider a far-red BRD7 channel when tissue autofluorescence compromises shorter wavelengths, using single-stain and unstained controls to assess bleed-through and background (standard IF practice). BRD7 is nuclear and has no transmembrane segment, so access to an intracellular epitope generally requires appropriate permeabilisation after fixation (UniProt Q9NPI1: subcellular location and topology; standard IF practice). The paraffin-section caption supplies chromogenic IHC conditions, including 1 μg/ml primary antibody, and does not establish an IF dilution or fixation method (datasheet A01289-1).
What should I check when DAB obscures nuclear BRD7 staining?
First compare the section with a no-primary control and inspect whether brown signal is diffuse, concentrated at edges, or present in damaged areas (standard IHC practice). The documented assay used 10% goat serum blocking, 1 μg/ml rabbit primary antibody overnight at 4°C, a biotinylated secondary, and DAB development (datasheet A01289-1). Review blocking, washing, primary concentration, secondary exposure, and DAB development one variable at a time; include a peroxidase block as a general chromogenic IHC step (standard IHC practice). Because the documented detection is biotin based, assess endogenous biotin where relevant before attributing diffuse brown signal to BRD7, whose expected tissue pattern is nuclear (datasheet A01289-1; HPA: ubiquitous nuclear expression; standard IHC practice).
How should I quantify BRD7 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Score BRD7 in intact, identifiable nuclei because the reported tissue IHC pattern is ubiquitously nuclear (HPA: tissue IHC). Define the sampled compartment before analysis and report the percentage of positive nuclei plus an intensity-based H-score from 0–300, using the same thresholds and counterstain settings across sections (standard IHC practice). Normalize each percentage or H-score to evaluable nuclei in the same cell population, and exclude necrosis, folds, and poorly preserved edges by a predefined rule (standard IHC practice). Include a common staining control across runs and report nuclear intensity separately from cytoplasmic signal, since the additional cytosolic localization in cell imaging is uncertain (HPA: subcellular; standard IHC practice).
When is apparent BRD7 positivity more likely artefact than true staining?
Give greatest weight to staining within intact nuclei: BRD7 is annotated in the nucleus and on chromosomes, and HPA reports ubiquitous nuclear tissue expression (UniProt Q9NPI1: subcellular location; HPA: tissue IHC). A colon glandular-cell nuclear pattern is consistent with HPA observations, while a specimen’s cell identity still needs confirmation from its histology (HPA: colon glandular cells, High; standard IHC practice). Treat isolated edge staining, necrotic debris, and signal that persists without primary antibody as potential artefact, including residual endogenous peroxidase in a DAB assay (standard IHC practice; datasheet A01289-1: DAB detection). Review morphology and controls before interpreting unexpected cytoplasmic staining, because HPA marks BRD7’s additional cytosolic location uncertain (HPA: subcellular; standard IHC practice).
Boster reagents

Best BRD7 / Bromodomain-containing protein 7 IHC Antibodies

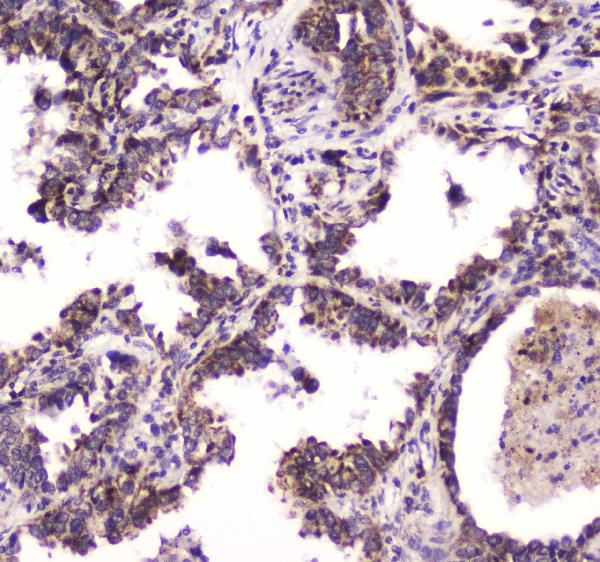
A01289-1 has real IHC images from human colon and lung cancer paraffin sections (catalog IHC captions); its listed reactivity includes human, mouse, and rat (catalog applications/reactivity).

Real IHC data IHC analysis of BRD7 using anti-BRD7 antibody (A01289-1). BRD7 was detected in paraffin-embedded section of human colon cancer tissue. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-BRD7 Antibody (A01289-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-BRD7 Antibody ®
Cat # A01289-1

A01289-1 will render with IHC data from a human colon cancer paraffin section (A01289-1 figure caption). Its catalog also shows a human lung cancer paraffin section and lists IHC plus human, mouse, and rat reactivity (A01289-1 IHC captions; catalog applications/reactivity).

Which to pick: Choose A01289-1 for tissue IHC: it is a rabbit polyclonal antibody listed for IHC, with images from human colon and lung cancer paraffin sections (catalog host/clonality/applications; A01289-1 IHC captions). No IF/ICC option is supported by the supplied catalog because A01289-1 has no IF application or IF image (catalog applications; IF image list). For mouse or rat tissue, A01289-1 lists those species as reactive, but the supplied IHC images are human; the captions report paraffin sections and do not report the fixative (catalog reactivity; A01289-1 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9NPI1 (BRD7_HUMAN, Bromodomain-containing protein 7).
  2. Human Protein Atlas. BRD7 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. BRD7 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the cytosol..
  4. Human Protein Atlas. BRD7 antibody validation summary (3 antibodies).
  5. Targeting the anaphase-promoting complex/cyclosome (APC/C)- bromodomain containing 7 (BRD7) pathway for human osteosarcoma. Oncotarget 2014 — PMC4102794.
  6. Bromodomain-containing protein 7 (BRD7) as a potential tumor suppressor in hepatocellular carcinoma. Oncotarget 2016 — PMC4941311.
  7. BRD7 inhibits the Warburg effect and tumor progression through inactivation of HIF1α/LDHA axis in breast cancer. Cell death & disease 2018 — PMC5938698.
  8. Machine learning identifies ferroptosis-related genes as potential diagnostic biomarkers for osteoarthritis. Frontiers in endocrinology 2023 — PMC10292652.
  9. PubMed PMID:11025449 — UniProt-cited evidence.
  10. PubMed PMID:12489984 — UniProt-cited evidence.
  11. PubMed PMID:15616553 — UniProt-cited evidence.