CA9 / Carbonic anhydrase 9 · IHC design guide

Design Immunohistochemistry for CA9

Plan CA9 staining in paraffin sections using the catalog antibody at 2–5 μg/ml (datasheet A01083-3). Compare membranous staining with the high expression reported in stomach and gallbladder glandular cells (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CA9 (IHC for CA9): expected localisation Membranous staining in gastrointestinal glands (HPA tissue IHC), antibody A01083-3, validated IHC image, and IHC protocol steps
Printable CA9 IHC protocol sheet — expected localisation Membranous staining in gastrointestinal glands (HPA tissue IHC), antibody A01083-3, controls and protocol steps. Open the full CA9 IHC guide →

CA9 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Membranous staining in gastrointestinal glands (HPA tissue IHC)
Staining pattern Selective membranous staining in gastrointestinal and gallbladder glands (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01083-3)
Positive control ⓘ Gallbladder+3 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific)
Caveat Normal stomach and gallbladder glands stain strongly (HPA tissue IHC)
Regulation Expression regulation is unreported (UniProt)
Isoform / epitope No listed isoforms; extracellular versus cytoplasmic epitope matters (UniProt)
Section 1

Recommended CA9 IHC & IF Protocols

The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet A01083-3). Three published CA9 IHC protocols provide tissue-specific alternatives (PMC6047828; PMC3875845; PMC8168507).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colonic adenocarcinoma tissue; fixative not specified (datasheet A01083-3)
FixationImage fixative and duration unreported (datasheet A01083-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01083-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01083-3)
Primary antibodyRabbit anti-CA9, 2-5 μg/ml (datasheet A01083-3)
Primary incubationOvernight at 4 °C (datasheet A01083-3)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A01083-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCA9-positive staining in glandular cells of gallbladder (HPA tissue IHC: High). HPA tissue profile: Highly selective membranous expression in the gastrointestinal mucosa and gall bladder. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 for the catalog antibody (datasheet A01083-3); the published protocols used citrate retrieval or omitted retrieval for loose fetal tissue (PMC6047828; PMC8168507; PMC3875845).
Section 2

What Is the Expected CA9 Staining Pattern?

CA9 is a transmembrane protein with an extracellular region spanning residues 38–414 (UniProt Q16790 topology). In paraffin section IHC, expect chiefly membranous staining in glandular cells of gastric and gallbladder mucosa; HPA reports high staining in both and describes the tissue pattern as highly selective. Its tissue IHC reliability is Enhanced, reflecting high consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Crisp membrane staining in gastric or gallbladder glandular cells, with limited surrounding stain.This matches the high glandular cell staining and selective membranous pattern reported for these tissues (HPA tissue IHC). Compare the membrane signal with an appropriate negative control when judging a slide (general IHC practice).
Medium membrane staining in duodenal or small intestinal glandular cells.A weaker positive result can still fit the reference: HPA records medium staining in these glandular cells, versus high staining in stomach and gallbladder (HPA tissue IHC). Score the observed cells and compartment as well as intensity.
Predominantly nuclear or diffuse cytoplasmic stain, without a convincing glandular membrane pattern.This is discordant with HPA tissue IHC and its supported plasma membrane ICC-IF localisation (HPA tissue IHC; HPA subcellular). UniProt also lists nuclear and nucleolar localisation, so nuclear signal alone cannot prove an artefact (UniProt Q16790 subcellular). Check controls and antibody specificity.
Stain in an unexpected cell population, or similar colour in the negative control.Consider off-target binding or detection background before assigning CA9 expression (general IHC practice). HPA's ‘not detected’ entries apply to the named cell populations—for example, adrenal glandular cells and bronchial respiratory epithelial cells—not every cell in those tissues (HPA tissue IHC).
No membrane signal in gastric or gallbladder glandular cells.This conflicts with HPA's high staining in those named cells (HPA tissue IHC). First confirm that the expected glands are present and assess the run controls; then review the antibody's validated IHC-P conditions and the staining workflow (general IHC practice).
💡Expected CA9 appearanceCall a positive result when glandular cell membranes stain clearly in stomach or gallbladder, where HPA reports high signal; diffuse colour or signal confined to unrelated cells does not establish this reference pattern (HPA tissue IHC; general IHC practice).
How each factor affects the staining
Epitope location and assay accessCA9 spans the membrane at residues 415–435, with residues 38–414 extracellular and 436–459 cytoplasmic (UniProt Q16790 topology). Check the antibody's stated epitope, if available, when interpreting compartment differences; the supplied record gives no antibody epitope.
Reference tissue and cell populationHPA reports high glandular staining in stomach and gallbladder, medium glandular staining in duodenum and small intestine, and no detection in the specifically listed negative cell populations (HPA tissue IHC). Choose controls by the named cell population, not a whole-tissue label.
Strength of localisation evidenceHPA describes tissue IHC as highly selective and membranous, with Enhanced reliability; its ICC-IF summary supports plasma membrane localisation (HPA tissue IHC; HPA subcellular). UniProt additionally records surface microvilli and nuclear, particularly nucleolar, localisation (UniProt Q16790 subcellular). Interpret unexpected nuclear IHC with controls.
IF/ICC Q&A: What pattern is expected?Expect plasma membrane localisation in ICC-IF (HPA subcellular). This is a localisation reference, not an IF/ICC protocol or an IHC-P dilution. The supplied HPA antibody list marks ICC as Supported for CAB005100 and CAB017107; HPA055207 has no ICC status (HPA antibodies).
Fixation and retrieval evidenceTarget-specific fixation sensitivity and a CA9 retrieval condition are unreported in the supplied UniProt and HPA records. If signal fails, review the chosen antibody's validated IHC-P instructions and a positive control before changing retrieval (general IHC practice).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Gastric or gallbladder glands are present, but membrane staining is absent.The result disagrees with high staining reported for those glandular cells (HPA tissue IHC); the supplied sources do not identify which preparation or staining step failed.Check run controls, tissue identity and the catalog antibody's validated IHC-P instructions, including any specified retrieval and dilution (general IHC practice). Do not infer CA9-specific fixation sensitivity.
The entire section has diffuse chromogenic colour.Nonspecific antibody binding or background from the detection system may obscure the selective membrane pattern (general IHC practice; HPA tissue IHC).Inspect a no-primary control, blocking and washes. If using peroxidase detection, check endogenous peroxidase control and blocking according to the detection workflow (general IHC practice).
Only nuclei stain in an otherwise well-preserved section.Nuclear localisation is listed by UniProt, but isolated nuclear staining does not match HPA's predominant membranous tissue IHC pattern (UniProt Q16790 subcellular; HPA tissue IHC).Compare with a positive glandular tissue and a no-primary control; verify the antibody's IHC validation before scoring nuclear signal as CA9 (general IHC practice; HPA antibodies).
Adrenal glandular cells or bronchial respiratory epithelial cells stain strongly.Those specific cell populations are ‘not detected’ in HPA tissue IHC, so strong staining is discordant with that reference; the result alone cannot identify its cause (HPA tissue IHC).Confirm the cell type, compare a no-primary control and repeat with an independently IHC-validated antibody where available (general IHC practice; HPA antibodies).
Stomach stains, but duodenal or small intestinal glands appear weaker.HPA reports high staining in stomach and medium staining in duodenal and small intestinal glandular cells (HPA tissue IHC).Assess membrane localisation and the run controls before treating this intensity difference as assay failure; record the tissue and glandular cell population in the score (general IHC practice).
An ICC-IF image differs from the paraffin section IHC result.HPA supports plasma membrane ICC-IF localisation, while its tissue IHC profile describes selective membranous staining in named mucosal cells; the records cover different sample settings (HPA subcellular; HPA tissue IHC).Interpret each result against its own controls and validation status. Use the antibody's IHC-P instructions for the paraffin section; this section supplies no IF/ICC protocol (general IHC practice; HPA antibodies).

Sample controls for CA9 IHC & IF

🧪Run stomach first: its glandular cells should stain for CA9 (HPA: High in stomach glandular cells). Use adrenal gland as a negative tissue (HPA: Not detected in adrenal gland glandular cells); on the stomach slide, non-glandular cells should show only background staining, which should be checked rather than assumed.
Positive control tissue: Gallbladder (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CA9 in A-431, U2OS, with annotated localisation: Plasma membrane (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a host- and clonality-matched isotype control; use CA9 knockout tissue or a validated peptide block as a biological negative. Block endogenous peroxidase before HRP–DAB detection in the stomach section (selected-SKU IHC caption: HRP–DAB detection).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A01083-3 paraffin-section caption does not state a fixative (selected-SKU IHC caption). Heat-mediated EDTA retrieval at pH 8.0 preceded CA9 detection, but whether retrieval is required is unreported (selected-SKU IHC caption). Relative ease of frozen-section staining or IF is unreported; ICC-IF images support plasma-membrane localization, and no stomach-specific artefact is reported in the supplied evidence (HPA subcellular).

HPA tissue IHC evidence for CA9

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Gallbladder Glandular cells High Protein (IHC) HPA →
Stomach Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells Medium Protein (IHC) HPA →
Small intestine Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced CA9 IHC Tips

Troubleshoot CA9 staining in paraffin sections by checking retrieval, compartment, cell type, and controls before comparing signal intensity.

What retrieval should I use when CA9 staining is weak in paraffin sections?
Start with heat mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A01083-3). The selected CA9 tissue image used that condition before overnight primary antibody incubation at 4°C (datasheet A01083-3). If staining remains weak, compare retrieval duration on adjacent sections while holding antibody concentration and detection conditions constant (standard IHC practice). Use a known positive glandular section to distinguish failed retrieval from genuinely low expression, and inspect morphology for heat damage (HPA tissue IHC; standard IHC practice). Record the heating and cooling conditions because a buffer name alone does not define a reproducible retrieval treatment (standard IHC practice).
How should I assess whether fixation caused weak CA9 staining?
The selected paraffin section caption does not report its fixative, so CA9 sensitivity to a particular fixative or fixation duration is unknown for this antibody (datasheet A01083-3). Record the specimen's fixation history and compare sections with known differences in processing using the same EDTA pH 8.0 retrieval and staining run (datasheet A01083-3; standard IHC practice). Examine preserved morphology alongside CA9 signal, since damaged tissue complicates interpretation of any apparent staining loss (standard IHC practice). Include a positive tissue control in each run to check whether the staining procedure worked (HPA tissue IHC; standard IHC practice). Do not assign a weak result to fixation without a controlled comparison (standard IHC practice).
Should I count nuclear CA9 staining as a positive result?
Score membrane staining separately: highly selective membranous staining is the reported tissue IHC pattern, and the plasma membrane is the supported main subcellular location (HPA tissue IHC; HPA subcellular). UniProt also reports CA9 on microvilli and in the nucleus, particularly the nucleolus, so nuclear signal merits examination rather than automatic inclusion or rejection (UniProt Q16790 localisation). Check whether nuclear staining occurs in the expected glandular cells and accompanies a credible membrane pattern on the same section (HPA tissue IHC; standard IHC practice). Review the negative control and tissue morphology before scoring isolated nuclear staining (standard IHC practice). State which compartment contributes to the reported score (standard IHC practice).
How can epitope position change CA9 staining interpretation?
CA9 has no listed isoforms, but the binding site of this catalog antibody is not specified in the supplied evidence (UniProt Q16790 isoforms; datasheet A01083-3). Its extracellular region spans residues 38–414, its transmembrane segment 415–435, and its cytoplasmic tail 436–459 (UniProt Q16790 topology). Glycosylation is listed at residues 115 and 346, so avoid assuming that every antibody recognizes an unaffected extracellular sequence (UniProt Q16790 glycosylation). If two antibodies yield different compartment patterns, document their mapped epitopes when available and compare them on adjacent sections under controlled staining conditions (standard IHC practice). An unmapped epitope cannot establish which side of the membrane the antibody recognizes (UniProt Q16790 topology; datasheet A01083-3).
How should I investigate a CA9 pattern by multiplex IF?
Pair CA9 with a marker identifying the expected glandular epithelial cells, then assess membrane overlap and cell identity in separate channels (HPA tissue IHC; standard IF practice). Choose fluorophores and filter sets after examining an unstained section for tissue autofluorescence, and use single stain controls to check channel bleed through (standard IF practice). For a confirmed extracellular epitope, compare staining without permeabilisation; an intracellular tail epitope may require permeabilisation, but this catalog antibody's epitope is unspecified (UniProt Q16790 topology; datasheet A01083-3; standard IF practice). HPA reports plasma membrane localisation and ICC/IF images in A-431 and U2OS, which provide a localisation reference rather than an IF protocol for this antibody (HPA subcellular). Keep IF exposure settings consistent across compared specimens (standard IF practice).
What should I check when CA9 DAB staining looks diffuse?
First compare a no primary control with the stained section to identify signal arising from detection reagents or endogenous peroxidase (standard IHC practice). Include a peroxidase block before HRP and DAB development, and evaluate whether the block suppresses staining in the control (standard IHC practice). The selected image used 10% goat serum blocking, 2 µg/mL primary antibody overnight at 4°C, and DAB detection (datasheet A01083-3). If background persists, titrate primary antibody and adjust blocking or washing while retaining a positive tissue control (standard IHC practice). Judge improvement by clearer membrane boundaries in expected cells, rather than a general loss of color (HPA tissue IHC; standard IHC practice).
How should I quantify CA9 in heterogeneous tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored compartment as cell membrane and annotate viable glandular or tumor cells before measuring signal (HPA tissue IHC; standard IHC practice). Report the percentage of positive cells and an H-score calculated as the sum of each intensity grade, 0–3, multiplied by its percentage of cells, giving a 0–300 range (standard IHC practice). Set positivity and intensity thresholds using the same controls and staining run for all compared sections (standard IHC practice). Normalise counts to the number of eligible cells, or normalise stained area to annotated viable tissue area in mm² (standard IHC practice). Record excluded necrotic and damaged regions so sampling differences remain visible (standard IHC practice).
How do I distinguish genuine CA9 staining from artefact?
Look for bounded membrane staining in plausible glandular cells; HPA reports selective membranous expression in gastrointestinal mucosa and gall bladder (HPA tissue IHC). High staining is reported in stomach and gallbladder glandular cells, while adipocytes in adipose tissue are reported as undetected, providing useful tissue context (HPA tissue IHC). Examine unexpected staining in other compartments or cell types against morphology, a no primary control, and the expected membrane pattern (HPA subcellular; standard IHC practice). Discount signal limited to section edges, folds, or necrotic areas when assessing viable cells (standard IHC practice). If diffuse DAB remains in the no primary control, check endogenous peroxidase blocking before attributing that color to CA9 (standard IHC practice).
Boster reagents

Best CA9 / Carbonic anhydrase 9 IHC Antibodies

Three anti-CA9 antibodies have IHC images from human tissue; additional images cover mouse stomach and rat stomach (catalog image captions). IF is listed for M01083-5, with no IF image supplied (catalog applications and images).

Real IHC data IHC analysis of Carbonic Anhydrase 9/CA9 using anti-Carbonic Anhydrase 9/CA9 antibody (A01083-3). Carbonic Anhydrase 9/CA9 was detected in a paraffin-embedded section of human colonic adenocarcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-Carbonic Anhydrase 9/CA9 Antibody (A01083-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Carbonic Anhydrase 9/CA9 Antibody ®
Cat # A01083-3
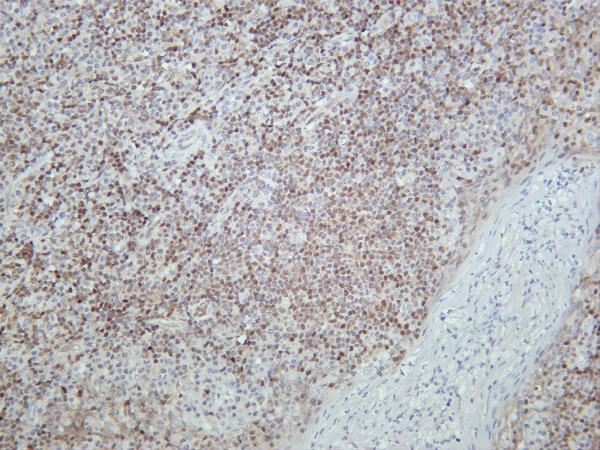
Real IHC data Human tonsil was stained with Anti-Carbonic Anhydrase 9 rabbit antibody
Anti-Carbonic Anhydrase 9 Rabbit Monoclonal Antibody
Cat # M01083-5
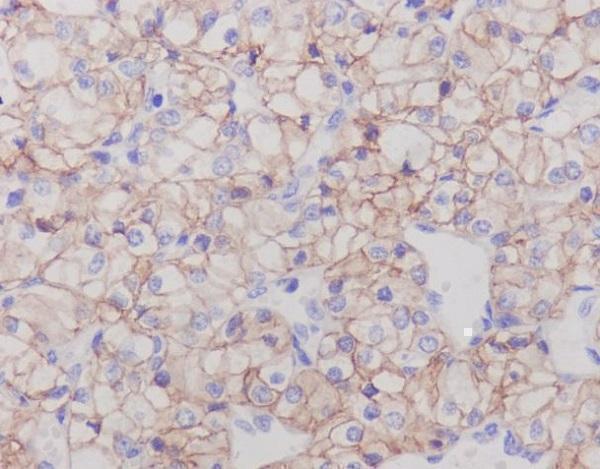
Real IHC data Immunohistochemical analysis of paraffin-embedded human kindey cancer, using CA9 Antibody.
Anti-CA9/Ca Ix Rabbit Monoclonal Antibody
Cat # M01083-1

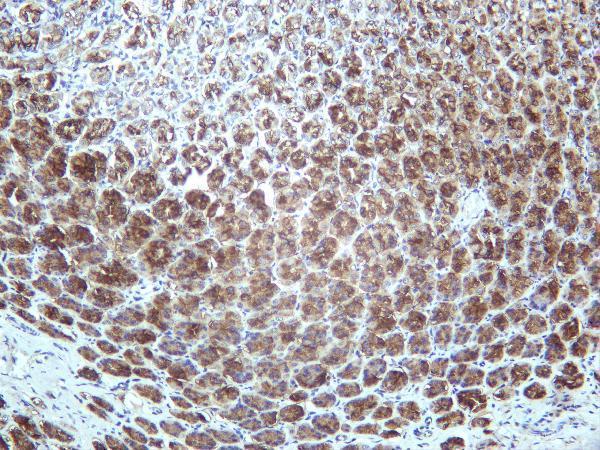
A01083-3 has paraffin-section IHC images from human colonic and renal adenocarcinoma and mouse stomach (A01083-3 image captions); M01083-1 has a paraffin-section IHC image from human kidney cancer (M01083-1 image caption). M01083-5 has IHC images from human tonsil, colon carcinoma and stomach, plus rat stomach; its catalog also lists IF (M01083-5 image captions and applications).

Which to pick: For paraffin-section IHC, choose A01083-3 for its documented human and mouse examples, or M01083-1 for a human kidney cancer example (respective image captions). For IF, choose rabbit monoclonal M01083-5 because IF is listed at 1:200–1:1000; ICC validation and an IF image are unreported (M01083-5 catalog). For IHC across the widest listed species range, M01083-5 covers human, mouse and rat, although its IHC images show only human and rat tissue and do not report section processing or fixative (M01083-5 reactivity and image captions); the paraffin-section captions for A01083-3 and M01083-1 also leave fixative unreported (respective image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q16790 (CAH9_HUMAN, Carbonic anhydrase 9).
  2. Human Protein Atlas. CA9 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CA9 subcellular location (ICC-IF): Localized to the plasma membrane..
  4. Human Protein Atlas. CA9 antibody validation summary (3 antibodies).
  5. Circulating hypoxia marker carbonic anhydrase IX (CA9) in patients with hepatocellular carcinoma and patients with cirrhosis. PloS one 2018 — PMC6047828.
  6. Expression of carbonic anhydrase IX in human fetal joints, ligaments and tendons: a potential marker of mechanical stress in fetal development?. Anatomy & cell biology 2013 — PMC3875845.
  7. Molecular profiling reveals a hypoxia signature in breast implant-associated anaplastic large cell lymphoma. Haematologica 2021 — PMC8168507.
  8. Identification of ferroptosis-related genes as potential biomarkers of tongue squamous cell carcinoma using an integrated bioinformatics approach. FEBS open bio 2022 — PMC8804613.
  9. PubMed PMID:8084592 — UniProt-cited evidence.
  10. PubMed PMID:10709109 — UniProt-cited evidence.
  11. PubMed PMID:15164053 — UniProt-cited evidence.