CALB1 / Calbindin · IHC design guide

Design Immunohistochemistry for CALB1

Plan chromogenic IHC for CALB1 using its selective cytoplasmic staining in Purkinje cells and renal tubules as a guide to interpretation (HPA tissue IHC). Compare distal tubules with other renal tubules and keep fixation consistent across sections (HPA tissue IHC; standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
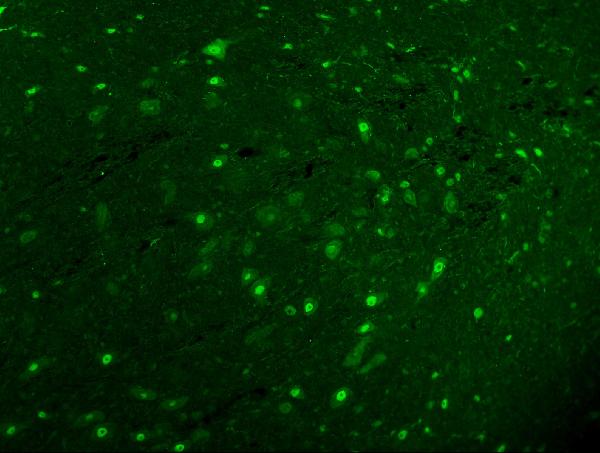
Immunohistochemistry protocol sheet for CALB1 (IHC for CALB1): expected localisation Cytoplasmic staining in Purkinje cells and renal tubules (HPA tissue IHC), antibody PB9045, validated IHC image, and IHC protocol steps
Printable CALB1 IHC protocol sheet — expected localisation Cytoplasmic staining in Purkinje cells and renal tubules (HPA tissue IHC), antibody PB9045, controls and protocol steps. Open the full CALB1 IHC guide →

CALB1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in Purkinje cells and renal tubules (HPA tissue IHC)
Staining pattern Purkinje cytoplasm, granular-layer processes and renal tubules (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PB9045)
Positive control ⓘ Cerebellum+2 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific)
Caveat Score distal tubules separately from other renal tubules (HPA tissue IHC)
Regulation No expression regulator annotated (UniProt)
Isoform / epitope 2 isoforms; epitope differences are not mapped (UniProt)
Section 1

Recommended CALB1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet PB9045) is accompanied by published CALB1 protocols for paraffin-embedded mouse brain (PMC3338865) and frozen brain sections (PMC6738605).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded mouse kidney tissue; fixative not specified (datasheet PB9045)
FixationImage fixative and duration unreported (datasheet PB9045); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PB9045); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB9045)
Primary antibodyRabbit anti-CALB1, 0.5-1μg/ml recommended; image 2 μg/ml (datasheet PB9045)
Primary incubationOvernight at 4 °C (datasheet PB9045)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet PB9045)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCALB1-positive staining in processes in granular layer of cerebellum (HPA tissue IHC: High). HPA tissue profile: Selective cytoplasmic expression in Purkinje cells and renal tubules. No signal in the no-primary control.
💡Decision noteFor the catalog antibody, start with heat-mediated EDTA pH 8.0 retrieval (datasheet PB9045). The published paraffin protocol used Tris/EDTA/Tween 20 at pH 9 (PMC3338865).
Section 2

What Is the Expected CALB1 Staining Pattern?

CALB1 should show selective cytoplasmic staining in cerebellar Purkinje cells and renal tubules; HPA reports high staining in processes of the cerebellar granular layer and kidney distal tubules (HPA tissue IHC). Its tissue IHC profile has Enhanced reliability, reflecting consistency between antibody staining and RNA expression (HPA tissue IHC). CALB1 has no transmembrane segment (UniProt P05937 topology).

What am I looking at on my slide?
Cytoplasmic staining in Purkinje cells and their processes; high signal in granular-layer processes (HPA tissue IHC).This fits the selective cerebellar pattern. Judge the stained cells and processes against tissue anatomy, not overall section darkness (HPA tissue IHC; standard IHC practice).
High staining in kidney distal tubules, with other structures less prominent (HPA tissue IHC).This supports the expected renal pattern. Identify distal tubules before scoring; HPA reports a cell-specific pattern, not uniform kidney staining (HPA tissue IHC).
Predominantly nuclear staining without the expected cytoplasmic pattern (HPA tissue IHC).Treat this as a localisation mismatch requiring validation. HPA tissue IHC describes selective cytoplasmic expression; nuclear staining alone does not confirm CALB1 (HPA tissue IHC).
Strong signal in adipocytes or adrenal glandular cells (HPA tissue IHC).HPA reports CALB1 as not detected in those cells. Consider cross-reactivity or endogenous detection activity, then compare controls (HPA tissue IHC; standard IHC practice).
Diffuse colour across cells and extracellular areas, or no signal in cerebellum and kidney (HPA tissue IHC).Diffuse colour weakens cell-specific interpretation; absent staining in these expected-positive tissues calls for an assay check before a negative call (HPA tissue IHC; standard IHC practice).
💡Expected CALB1 appearanceCall a section positive when staining is predominantly cytoplasmic in Purkinje cells and their processes or kidney distal tubules, with high signal in granular-layer processes and distal tubules; isolated nuclear or widespread unrelated-cell colour is suspect (HPA tissue IHC).
How each factor affects the staining
Tissue and cell selectionHPA reports high staining in cerebellar granular-layer processes and kidney distal tubules, medium in caudate neuronal cells, and low in cerebral-cortex neuronal cells (HPA tissue IHC).
Negative tissue contextHPA reports not detected in adipose-tissue adipocytes and adrenal glandular cells. These are comparison tissues, not proof that every faint mark is nonspecific (HPA tissue IHC; standard IHC practice).
Compartment evidenceTissue IHC describes selective cytoplasmic expression, while ICC-IF reports an approved vesicular location. Interpret each observation within its assay; UniProt supplies no subcellular annotation (HPA tissue IHC; HPA subcellular; UniProt P05937).
Topology and processingCALB1 has no transmembrane segment or signal peptide; the annotated chain spans residues 2–261. These annotations do not establish a target-specific antigen-retrieval requirement (UniProt P05937 topology and processing).
Isoforms and epitope limitsUniProt lists 2 isoforms, but the supplied evidence does not map an IHC antibody epitope to either one. Do not assign a staining difference to an isoform without further evidence (UniProt P05937 isoforms).
Validation scopeTarget-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in expected-positive cerebellum or kidney (HPA tissue IHC).The run may have failed, or the sampled section may lack the relevant cells (standard IHC practice).Verify the tissue anatomy and run controls; check the antibody, retrieval, and detection steps under the assay instructions before calling CALB1 absent (standard IHC practice).
Staining is weak in caudate or cerebral cortex (HPA tissue IHC).HPA reports medium caudate neuronal staining and low cerebral-cortex neuronal staining (HPA tissue IHC).Compare with the stronger cerebellar or distal-tubule pattern and score the relevant cells; avoid expecting equal intensity across regions (HPA tissue IHC; standard IHC practice).
Colour spreads diffusely beyond identifiable cells (standard IHC practice).Nonspecific binding or incomplete washing can raise background (standard IHC practice).Review blocking and wash steps, and compare a negative control with the cell-specific positive pattern (standard IHC practice; HPA tissue IHC).
Adipocytes or adrenal glandular cells stain strongly (HPA tissue IHC).Cross-reactivity or endogenous chromogenic detection activity is possible; HPA reports CALB1 as not detected there (standard IHC practice; HPA tissue IHC).Inspect controls for antibody-independent colour, then reassess antibody specificity before assigning the signal to CALB1 (standard IHC practice).
Staining appears mainly nuclear (standard IHC practice).That conflicts with HPA's selective cytoplasmic tissue-IHC profile; background or misidentified structures are possible (HPA tissue IHC; standard IHC practice).Recheck counterstain and morphology, then compare with cytoplasmic signal in an expected-positive tissue (standard IHC practice; HPA tissue IHC).
Why might an IF image look punctate when tissue IHC looks cytoplasmic?HPA reports vesicles as the approved ICC-IF location and selective cytoplasmic expression in tissue IHC (HPA subcellular; HPA tissue IHC).Interpret IF and tissue IHC within their own assay contexts; the supplied evidence does not establish that every punctum or every diffuse cytoplasmic signal is CALB1 (HPA subcellular; HPA tissue IHC).

Sample controls for CALB1 IHC & IF

🧪Run cerebellum first: processes in its granular layer should stain strongly (HPA: High in processes in granular layer). Use adipose tissue as a negative, focusing on adipocytes (HPA: Not detected in adipocytes); on the cerebellar slide, cells without specific staining provide a background reference, but the supplied HPA row does not identify a particular negative cell type.
Positive control tissue: Cerebellum (Processes in granular layer, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CALB1 in A-431, U-251MG, U2OS, with annotated localisation: Vesicles (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a host-matched rabbit IgG control (PB9045 tissue-IHC caption: rabbit primary antibody); use CALB1 knockout tissue, if available, as a biological specificity control. Quench endogenous peroxidase before HRP/DAB detection and check for residual background on the cerebellar slide (PB9045 tissue-IHC caption: HRP/DAB detection).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected PB9045 tissue-IHC caption does not state the fixative (PB9045 tissue-IHC caption: fixative unreported). The caption uses heat retrieval in EDTA at pH 8.0 for a paraffin-embedded mouse kidney section, but does not establish that retrieval is required for cerebellum (PB9045 tissue-IHC caption: mouse kidney retrieval). The supplied evidence does not establish that frozen sections or IF are easier; cerebellar autofluorescence may complicate IF assessment (standard IF practice).

HPA tissue IHC evidence for CALB1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebellum Processes in granular layer High Protein (IHC) HPA →
Kidney Distal tubules High Protein (IHC) HPA →
Caudate Neuronal cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced CALB1 IHC Tips

Troubleshoot CALB1 staining in paraffin sections by checking retrieval, cell identity, intracellular pattern, controls, and scoring before interpreting chromogenic signal.

What retrieval should I try first when CALB1 staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet PB9045). The selected mouse kidney image used that retrieval before incubation with 2 μg/ml primary antibody overnight at 4°C, so reproduce those documented conditions when comparing your staining (datasheet PB9045). If signal remains weak, check section adhesion, retrieval heating and cooling, and whether the secondary antibody detects the rabbit primary (standard IHC practice; datasheet PB9045). Keep a known positive kidney section in each run and change one condition at a time, because weak staining alone cannot identify retrieval as the cause (HPA: high in distal tubules; standard IHC practice).
Could fixation explain weak or uneven CALB1 staining?
CALB1-specific sensitivity to fixation is unknown from the supplied evidence; the selected paraffin kidney caption does not state a fixative (datasheet PB9045). Record the fixative, fixation duration, tissue thickness, and processing history for each section, then compare suspect material with a reliably stained control processed in the same run (standard IHC practice). Delayed or uneven fixation can create variable antigen preservation and tissue morphology in paraffin sections, so inspect both before increasing primary antibody concentration (standard IHC practice). Do not assign a CALB1-specific fixation effect from renal staining patterns or protein features; use matched processing and a controlled comparison to test that possibility (HPA: distal tubule expression; UniProt P05937; standard IHC practice).
Which staining pattern supports CALB1 identity in tissue?
In chromogenic IHC, look for cell-associated cytoplasmic staining in Purkinje cells and renal tubules, with particularly strong reference staining in cerebellar processes and kidney distal tubules (HPA: selective cytoplasmic expression; HPA: high in cerebellar processes and distal tubules). CALB1 buffers cytosolic calcium and has no annotated transmembrane segment, supporting an intracellular interpretation without defining every possible staining pattern (UniProt P05937). Use morphology and a counterstain to assign signal to the correct cells rather than judging brown intensity alone (standard IHC practice). The HPA subcellular record reports vesicles in ICC/IF images; treat that as context-specific evidence when comparing it with tissue IHC (HPA: vesicles; HPA: tissue IHC profile).
How could isoforms or epitope accessibility affect a negative result?
CALB1 has 2 recorded isoforms and 5 annotated EF-hand regions, but the supplied antibody caption does not map its epitope to either isoform or a particular region (UniProt P05937; datasheet PB9045). Therefore, a negative paraffin section cannot establish that a particular isoform is absent (UniProt P05937; standard IHC interpretation). Check the antibody's documented epitope information if available, and compare a suspect section with a positive control processed under the same retrieval and detection conditions (standard IHC practice). CALB1 has no annotated signal peptide or transmembrane segment; those features do not establish whether fixation or retrieval preserved this antibody's epitope (UniProt P05937).
How should I compare CALB1 IF with this chromogenic IHC result?
For IF on matched tissue, include a marker identifying the expected Purkinje cell or distal tubule population, then compare cell identity and staining distribution with the chromogenic section (HPA: Purkinje cells and distal tubules; standard IF practice). Choose fluorophores in channels with low tissue autofluorescence and check an unstained section before interpreting faint signal (standard IF practice). CALB1 has no transmembrane segment and buffers cytosolic calcium; permeabilise when detecting an intracellular epitope, while recognising that the antibody's precise epitope is not supplied (UniProt P05937; standard IF practice). HPA reports vesicular ICC/IF localisation, so record that pattern without assuming it must match every paraffin tissue IHC pattern (HPA: vesicles; HPA: tissue IHC profile).
What should I check when brown staining appears throughout the section?
First compare a section lacking primary antibody with the complete stain to assess secondary reagent, detection chemistry, and endogenous enzyme background (standard IHC practice). Apply a peroxidase block before HRP and DAB detection, and inspect whether residual pigment or precipitate persists in the control (standard IHC practice). The selected kidney protocol used 10% goat serum, a rabbit primary at 2 μg/ml, a peroxidase-conjugated secondary, and DAB, which provide a starting point for matching its conditions (datasheet PB9045). If diffuse staining remains, optimise blocking, washes, and primary concentration while retaining distal tubules as the expected internal pattern (standard IHC practice; HPA: high in distal tubules).
How should I score CALB1 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the anatomical compartment before scoring, such as distal tubules in kidney or Purkinje cells in cerebellum, and exclude unrelated cells from the denominator (HPA: high in distal tubules and cerebellar processes; standard IHC practice). Record the percentage of positive target cells and an intensity-weighted H-score, or measure positive area per mm² when processes make cell counts impractical (standard IHC practice). Normalise to the number or area of evaluable target cells or tissue, using the same threshold and imaging settings across sections (standard IHC practice). Report separate scores for cytoplasmic signal and diffuse background, and include a same-run positive control to reveal staining drift (HPA: cytoplasmic expression; standard IHC practice).
How can I distinguish genuine CALB1 staining from artefact?
A credible result follows the expected cells and cytoplasmic pattern: Purkinje cells or renal distal tubules should be identifiable by morphology, with signal in the relevant compartment (HPA: selective cytoplasmic expression; HPA: high in distal tubules). Treat strong staining confined to section edges, folds, or necrotic areas as suspect until it persists in intact tissue away from those features (standard IHC practice). Check a no-primary control for endogenous peroxidase signal or DAB deposit, and compare the suspect section with a known positive kidney section in the same run (standard IHC practice; HPA: distal tubules). Staining restricted to unrelated cells or an implausible extracellular compartment needs independent confirmation before being called CALB1 (HPA: tissue IHC profile; UniProt P05937; standard IHC interpretation).
Boster reagents

Best CALB1 / Calbindin IHC Antibodies

Anti-CALB1 antibodies have IHC images from human, mouse, and rat paraffin sections and IF images from rat cerebellum (catalog image captions: PB9045, A03047).

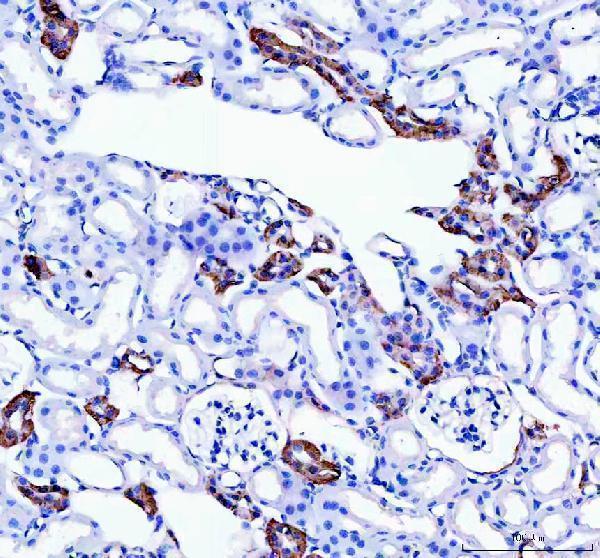
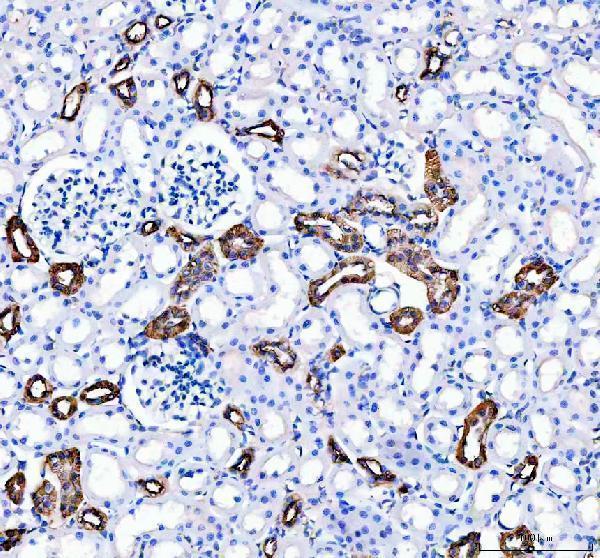
Real IHC data IHC analysis of Calbindin using anti-Calbindin antibody (PB9045). Calbindin was detected in a paraffin-embedded section of mouse kidney tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-Calbindin Antibody (PB9045) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Calbindin/CALB1 Antibody ®
Cat # PB9045
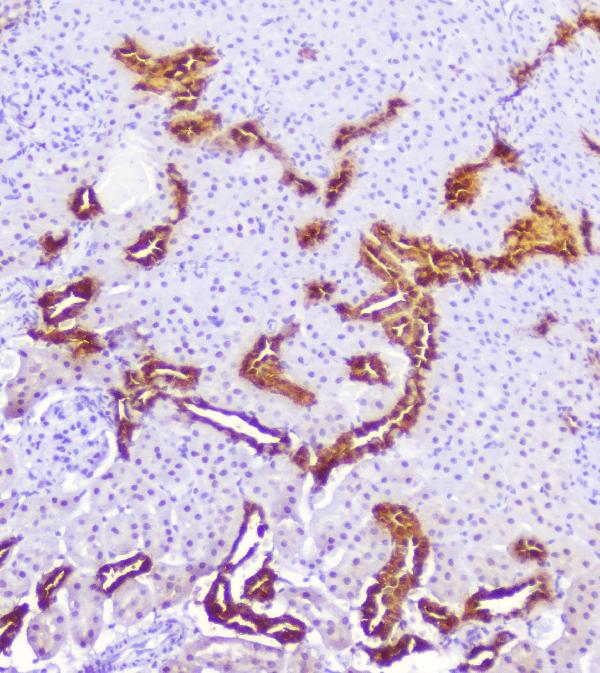
Real IHC data IHC analysis of Calbindin using anti-Calbindin antibody (A03047). Calbindin was detected in paraffin-embedded section of rat kidney tissue. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-Calbindin Antibody (A03047) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-Calbindin/CALB1 Antibody ®
Cat # A03047

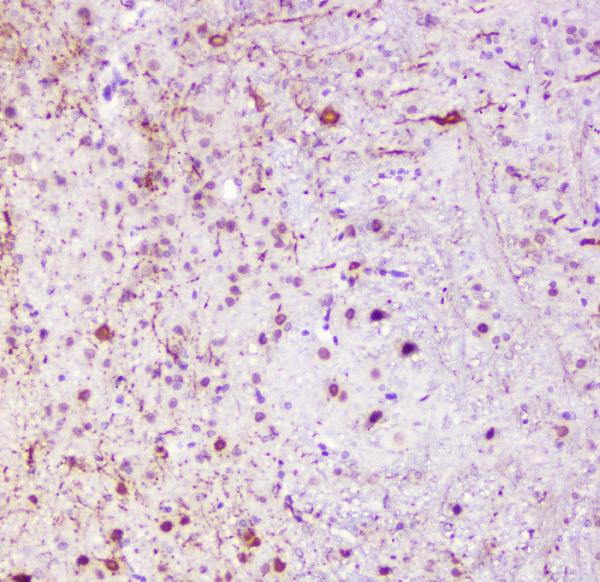
PB9045 will render with its mouse kidney IHC image; its catalog also shows rat and human kidney and human cerebellum IHC (PB9045 IHC image captions). A03047 will render with its rat kidney IHC image; its catalog also shows mouse brain and kidney and human cerebellum IHC, plus rat cerebellum IF (A03047 IHC/IF image captions).

Which to pick: For tissue IHC, choose PB9045 for EDTA pH 8 retrieval or A03047 for citrate pH 6 retrieval; each reagent’s own IHC caption documents a paraffin section, and neither reports the fixative (PB9045 and A03047 IHC image captions). For IF, A03047 has a rat cerebellum image; M03047 lists IF and ICC and is monoclonal, but has no supplied image (A03047 IF image caption; M03047 catalog applications, clone, and image fields). For work across human, mouse, and rat, PB9045 and A03047 each have IHC images from all three species (PB9045 and A03047 IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P05937 (CALB1_HUMAN, Calbindin).
  2. Human Protein Atlas. CALB1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CALB1 subcellular location (ICC-IF): Localized to vesicles..
  4. Human Protein Atlas. CALB1 antibody validation summary (3 antibodies).
  5. Hippocampal calbindin-1 immunoreactivity correlate of recognition memory performance in aged mice. Neuroscience letters 2012 — PMC3338865.
  6. Distinctive genetic activity pattern of the human dental pulp between deciduous and permanent teeth. PloS one 2014 — PMC4105481.
  7. Loss of prostatic acid phosphatase and α-synuclein cause motor circuit degeneration without altering cerebellar patterning. PloS one 2019 — PMC6738605.
  8. Engrailed-2 and inflammation convergently and independently impinge on cerebellar Purkinje cell differentiation. Journal of neuroinflammation 2024 — PMC11603920.
  9. PubMed PMID:3691519 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:16421571 — UniProt-cited evidence.