CCR7 / C-C chemokine receptor type 7 · IHC design guide

Design Immunohistochemistry for CCR7

Plan CCR7 chromogenic IHC on paraffin sections using documented human IHC conditions for the catalog antibody (datasheet A00390-2). Assess cytoplasmic staining in inflammatory-cell subsets, including high staining reported in lymph node non-germinal center cells and spleen white pulp (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CCR7 (IHC for CCR7): expected localisation Cytoplasmic in inflammatory cells (HPA tissue IHC); membrane expected (UniProt), antibody A00390-2, validated IHC image, and IHC protocol steps
Printable CCR7 IHC protocol sheet — expected localisation Cytoplasmic in inflammatory cells (HPA tissue IHC); membrane expected (UniProt), antibody A00390-2, controls and protocol steps. Open the full CCR7 IHC guide →

CCR7 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic in inflammatory cells (HPA tissue IHC); membrane expected (UniProt)
Staining pattern Cytoplasmic staining in subsets of inflammatory cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A00390-2)
Positive control ⓘ Lung+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific)
Caveat Only subsets of inflammatory cells stain; adjacent cells may be negative (HPA tissue IHC)
Regulation Up-regulated in EBV-infected B cells (UniProt)
Isoform / epitope 0 isoforms annotated; signal 1–24 cleaved; epitope side matters (UniProt)
Section 1

Recommended CCR7 IHC & IF Protocols

The catalog antibody’s IHC-P protocol uses EDTA pH 8.0 retrieval (datasheet A00390-2). The published CCR7 IHC protocols below provide tissue-specific starting conditions (PMC6141431; PMC4008409; PMC8149363; PMC3923395).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lymphoma tissue; fixative not specified (datasheet A00390-2)
FixationImage fixative and duration unreported (datasheet A00390-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A00390-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A00390-2)
Primary antibodyRabbit anti-CCR7, 2-5 μg/ml (datasheet A00390-2)
Primary incubationOvernight at 4 °C (datasheet A00390-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A00390-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCCR7-positive staining in alveolar cells of lung (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in subsets of inflammatory cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 for the catalog antibody (datasheet A00390-2); assess staining with appropriate controls before adapting conditions from another antibody’s protocol (standard IHC practice).
Section 2

What Is the Expected CCR7 Staining Pattern?

CCR7 is a 7-transmembrane cell-membrane receptor (UniProt P32248 topology and subcellular location). In paraffin-section IHC, expect staining in subsets of inflammatory cells, with high staining reported in lymph-node and tonsil non-germinal-center cells and spleen white-pulp cells (HPA tissue IHC). HPA rates the tissue pattern Enhanced, while reporting medium consistency between staining and RNA expression (HPA tissue IHC reliability).

What am I looking at on my slide?
Discrete staining in lymph-node or tonsil non-germinal-center cells, or spleen white-pulp cells (HPA tissue IHC).This matches the reported high IHC pattern (HPA tissue IHC). Assess the stained cells and compartment together: HPA describes cytoplasmic staining in subsets of inflammatory cells, while UniProt places the receptor at the cell membrane (HPA tissue IHC; UniProt P32248 subcellular location).
Predominantly nuclear or uniform staining across unrelated compartments (HPA tissue IHC; UniProt P32248 subcellular location).Question the result before scoring it as CCR7: neither nuclear localisation nor a uniform tissue-wide pattern is established by these sources (HPA tissue IHC; UniProt P32248 subcellular location). Review morphology and controls; the HPA mitochondrial ICC-IF result belongs to a separate assay context (HPA subcellular ICC-IF).
Strong staining in adipocytes or respiratory epithelial cells (HPA tissue IHC).These cells are reported as not detected in adipose tissue and bronchus, respectively (HPA tissue IHC). Check for cross-reactivity or endogenous detection activity as possible causes (general IHC practice). A cell-level comparison matters more than calling an entire tissue positive or negative (HPA tissue IHC).
Widespread, indistinct chromogen obscures cell boundaries (general IHC practice).Treat this as background until controls and a dilution check show a cell-specific pattern (general IHC practice). It cannot establish CCR7 expression simply because the section contains lymphoid tissue; HPA reports staining in specified cell subsets (HPA tissue IHC).
No staining in lymph-node non-germinal-center cells or spleen white-pulp cells (HPA tissue IHC).The missing signal conflicts with HPA's high staining observations (HPA tissue IHC). Check the assay controls, antibody suitability, retrieval and detection workflow before interpreting the sample as negative (general IHC practice). HPA's Enhanced rating does not guarantee every section will stain (HPA tissue IHC reliability).
💡Expected CCR7 appearanceCall an IHC result positive when discernible cellular staining occurs in the reported non-germinal-center or white-pulp populations, with high staining expected in those HPA examples; uniform nuclear staining or strong signal in HPA-negative cell types warrants investigation (HPA tissue IHC; UniProt P32248 subcellular location).
How each factor affects the staining
Cell population and tissue (HPA tissue IHC).HPA reports high staining in lung alveolar cells, lymph-node and tonsil non-germinal-center cells, and spleen white-pulp cells; skin corneal-layer cells are medium (HPA tissue IHC). Use the named cells when comparing sections; HPA also reports bone-marrow hematopoietic cells at low level (HPA tissue IHC).
Compartment and antibody epitope (UniProt P32248 topology).CCR7 has 7 transmembrane segments plus extracellular and cytoplasmic regions (UniProt P32248 topology). UniProt does not identify the catalog antibody's epitope, so topology alone cannot predict its staining appearance or establish a retrieval requirement (UniProt P32248 topology; general IHC practice).
Antibody validation (HPA antibodies; HPA tissue IHC reliability).HPA lists CAB003796 as IHC Enhanced and describes the tissue profile as Enhanced with medium staining–RNA consistency (HPA antibodies; HPA tissue IHC reliability). This supports using the reported pattern as a reference while retaining cell-level controls for interpretation (HPA tissue IHC; general IHC practice).
Does IF predict the paraffin-section result? (HPA subcellular ICC-IF).No direct equivalence is established: HPA reports mitochondrial localisation in ICC-IF images from A-549, U2OS and Rh30, while UniProt lists cell membrane and HPA tissue IHC describes cytoplasmic staining in inflammatory-cell subsets (HPA subcellular ICC-IF; UniProt P32248 subcellular location; HPA tissue IHC). Assess IF on its own guide page.
Antigen retrieval and detection setup (general IHC practice).Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The expected lymphoid-cell populations are unstained (HPA tissue IHC).An assay or detection failure is possible; absence of signal alone does not identify its cause (general IHC practice).Verify section integrity, positive-control staining and detection reagents, then review antibody dilution and retrieval against the validated IHC workflow (general IHC practice).
Chromogen covers most cells without clear boundaries (general IHC practice).Excess background can obscure the subset pattern reported by HPA (general IHC practice; HPA tissue IHC).Check blocking, washing, reagent concentration and the negative control; score cells only after the background is resolved (general IHC practice).
Adipocytes or bronchial respiratory epithelium stain strongly (HPA tissue IHC).Cross-reactivity or endogenous detection activity is possible in a discordant pattern (general IHC practice; HPA tissue IHC).Compare a negative control and the expected positive-cell pattern; review endogenous activity blocking and antibody dilution (general IHC practice; HPA tissue IHC).
Signal appears mainly nuclear (general IHC practice).The compartment conflicts with UniProt's membrane assignment and HPA's cytoplasmic tissue-IHC description (UniProt P32248 subcellular location; HPA tissue IHC).Recheck counterstain, cell boundaries and controls before assigning CCR7 positivity; investigate nonspecific signal if the nuclear pattern persists (general IHC practice).
ICC-IF shows mitochondria, but tissue IHC shows another pattern (HPA subcellular ICC-IF; HPA tissue IHC).The supplied HPA observations come from different assay contexts, and UniProt assigns CCR7 to the cell membrane (HPA subcellular ICC-IF; HPA tissue IHC; UniProt P32248 subcellular location).Interpret the paraffin section against tissue-IHC cell populations and controls; evaluate the ICC-IF observation separately (HPA tissue IHC; HPA subcellular ICC-IF; general IHC practice).
A low-signal marrow section seems inconsistent with a high-signal lymphoid section (HPA tissue IHC).HPA reports low staining in bone-marrow hematopoietic cells and high staining in specified lymph-node, tonsil and spleen populations (HPA tissue IHC).Compare like cell populations and review the positive control before changing assay conditions; tissue-level signal alone does not resolve cell-specific staining (HPA tissue IHC; general IHC practice).

Sample controls for CCR7 IHC & IF

🧪Run lymph node first and expect staining in non-germinal center cells (HPA: High); use adipose tissue adipocytes as the negative tissue (HPA: Not detected). On the lymph node slide, compare stained cells with morphologically distinct cells that lack signal, without assuming that an entire compartment is negative (HPA: High in non-germinal center cells).
Positive control tissue: Lung (Alveolar cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CCR7 in A-549, U2OS, Rh30, with annotated localisation: Mitochondria (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a concentration-matched rabbit immunoglobulin control matched to the primary antibody’s clonality (caption: rabbit anti-CCR7); and a verified CCR7 knockout specimen where available. Quench endogenous peroxidase for DAB detection and check background in the no-primary lymph node section (caption: peroxidase secondary and DAB; HPA: High in lymph node non-germinal center cells).
⚠️Feasibility: The selected paraffin-section example used heat retrieval in EDTA at pH 8.0, followed by 2 μg/ml primary antibody overnight at 4°C; it does not establish whether retrieval is required under other conditions (caption: A00390-2). A target-specific fixation window and fixation effect are unreported, and the selected caption does not report a fixative (caption: fixative not stated). Frozen sections or IF cannot be judged easier from the supplied evidence; interpret IF localization cautiously because the HPA ICC-IF summary reports mitochondrial staining whereas UniProt places CCR7 at the cell membrane (HPA: subcellular summary; UniProt P32248: cell membrane).

HPA tissue IHC evidence for CCR7

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Lung Alveolar cells High Protein (IHC) HPA →
Lymph node Non-germinal center cells High Protein (IHC) HPA →
Skin Cells in corneal layer Medium Protein (IHC) HPA →
Spleen Cells in white pulp High Protein (IHC) HPA →
Tonsil Non-germinal center cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Endocrine cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced CCR7 IHC Tips

Troubleshoot CCR7 chromogenic IHC in paraffin sections using the catalog antibody’s tissue evidence, receptor topology, and appropriate controls.

How should I retrieve CCR7 antigen when staining is weak?
Start with heat-mediated EDTA retrieval at pH 8.0 (datasheet A00390-2). The selected paraffin-section image used this retrieval, followed by 10% goat serum blocking and 2 μg/ml primary antibody overnight at 4°C (datasheet A00390-2). If staining remains weak, compare a shorter and longer heating interval on adjacent sections while holding detection and exposure to DAB constant (standard IHC practice). Include a lymph node or tonsil section with non-germinal center cells as a positive reference (HPA: High in these cells). Judge improvement by cleaner cell-associated staining, not simply darker tissue edges (standard IHC practice).
Could fixation explain variable CCR7 staining between paraffin blocks?
The selected CCR7 tissue-IHC caption does not state a fixative, so target-specific fixation sensitivity is unknown (datasheet A00390-2). Record the fixative, fixation duration, processing schedule, section thickness, and block age for each specimen before comparing results (standard IHC practice). Run adjacent sections from contrasting blocks through the same EDTA pH 8.0 retrieval and detection batch (datasheet A00390-2; standard IHC practice). Compare staining in the same cell population against an internal or companion positive control, rather than comparing whole-section darkness (standard IHC practice). Avoid assigning a fixation effect to CCR7 until that comparison separates processing differences from tissue composition (standard IHC practice).
Should CCR7 stain the membrane, cytoplasm, or another compartment?
CCR7 is annotated as a cell-membrane receptor with 7 transmembrane segments (UniProt P32248 topology and subcellular annotation). Tissue IHC reports cytoplasmic staining in subsets of inflammatory cells, while separate subcellular IF evidence reports mitochondria (HPA tissue IHC profile; HPA subcellular: mitochondria, enhanced). Score membrane-associated and cytoplasmic patterns separately in morphologically identified cells, and document the compartment visible with your chromogenic method (standard IHC practice). Compare suspect staining with a no-primary control and a positive lymphoid-tissue reference (standard IHC practice; HPA: lymph node and tonsil non-germinal center cells High). Do not treat mitochondrial-looking DAB deposits alone as confirmation of CCR7 identity (HPA subcellular; standard IHC practice).
How does the unknown antibody epitope affect CCR7 IHC troubleshooting?
The supplied record annotates 0 isoforms, but the antibody epitope is not mapped here (UniProt P32248 isoform record; datasheet A00390-2). CCR7 has extracellular residues 25–59, a glycosylation site at 36, and a cytoplasmic tail at 332–378 (UniProt P32248 topology and glycosylation). These features cannot establish which segment this antibody recognizes or whether retrieval exposes it (UniProt P32248 topology; datasheet A00390-2). Keep EDTA pH 8.0 retrieval as the reference condition and compare staining across adjacent sections when optimizing heating (datasheet A00390-2; standard IHC practice). If an independent antibody is available, agreement in cell type and compartment strengthens interpretation without proving epitope identity (standard IHC practice).
How can I assess CCR7 by IF alongside chromogenic IHC?
Treat IF as a separate validation exercise: the selected antibody evidence describes paraffin-section chromogenic IHC, with no IF conditions supplied for this SKU (datasheet A00390-2). Multiplex CCR7 with a validated marker of the expected lymphocyte population, selecting spectrally separated fluorophores and a far-red channel when tissue autofluorescence obscures shorter wavelengths (UniProt P32248 tissue specificity; standard IF practice). Test permeabilized and nonpermeabilized conditions because extracellular and cytoplasmic CCR7 regions lie on opposite sides of the membrane, while this antibody’s epitope is unspecified (UniProt P32248 topology; datasheet A00390-2). Include single-stain and no-primary controls to assess bleed-through and background (standard IF practice). Compare cell identity and compartment across IF and IHC without assuming identical staining patterns (standard IHC/IF practice).
What should I change when CCR7 DAB staining is diffuse?
Run a no-primary section to identify detection-system deposits and endogenous peroxidase signal before changing the CCR7 antibody concentration (standard IHC practice). For peroxidase detection, verify the peroxidase block, serum or protein block, wash steps, and DAB development time on matched sections (standard IHC practice). The selected image used 10% goat serum, 2 μg/ml primary antibody overnight at 4°C, and a peroxidase-conjugated secondary (datasheet A00390-2). If background persists, shorten DAB development or titrate the primary around that reference concentration while preserving EDTA pH 8.0 retrieval (datasheet A00390-2; standard IHC practice). Assess background separately from staining in inflammatory cells, where cytoplasmic CCR7 signal has been reported (HPA tissue IHC profile).
How should I quantify CCR7 staining across heterogeneous tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and scoring compartment before reading slides; CCR7 tissue IHC can mark subsets of inflammatory cells (HPA tissue IHC profile). Report the percentage of positive eligible cells and intensity, or calculate an H-score from intensity categories 0–3 multiplied by their respective cell percentages (standard IHC practice). For infiltrates, positive-cell density per mm² of viable tissue can complement a percentage (standard IHC practice). Normalize counts to the corresponding eligible-cell denominator or viable area, and exclude folds, edges, and necrotic regions by a prespecified rule (standard IHC practice). Keep retrieval, chromogen development, image settings, and positivity thresholds consistent across the comparison set (standard IHC practice).
How can I distinguish true CCR7 staining from artefact?
Look for reproducible cell-associated staining in the intended population, including non-germinal center cells in lymph node or tonsil, where HPA reports High staining (HPA tissue IHC). CCR7 is annotated at the cell membrane, although tissue IHC also reports cytoplasmic staining in inflammatory-cell subsets (UniProt P32248 subcellular annotation; HPA tissue IHC profile). Treat isolated staining in an unexpected compartment or cell type as uncertain until supported by controls or an independent assay (standard IHC practice). Exclude section edges, necrosis, and deposits that persist in a no-primary control; check endogenous peroxidase when DAB appears broadly positive (standard IHC practice). HPA describes only medium consistency between staining and RNA expression, so morphology and controls remain essential (HPA: Enhanced reliability description).
Boster reagents

Best CCR7 / C-C chemokine receptor type 7 IHC Antibodies

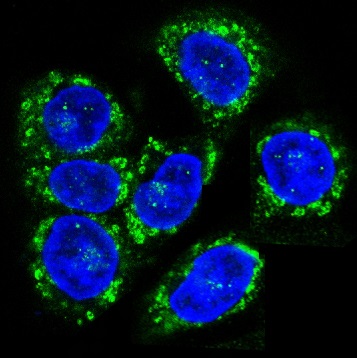
Anti-CCR7 antibodies have IHC images from human lymphoma and spleen sections and IF images from human spleen and HeLa cells (catalog image captions); one also lists mouse and rat reactivity (catalog: M00390).

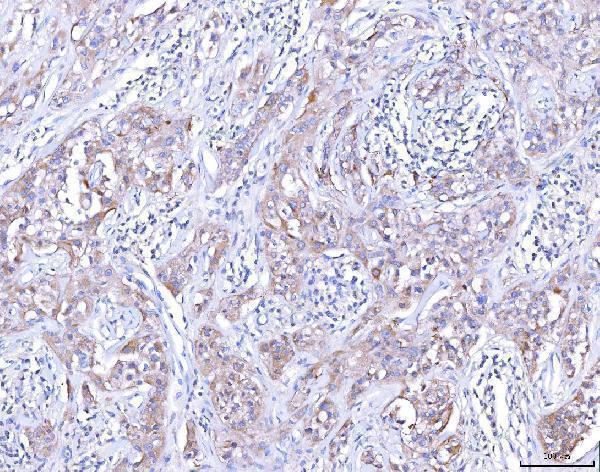
Real IHC data IHC analysis of CCR7 using anti-CCR7 antibody (A00390-2). CCR7 was detected in a paraffin-embedded section of human lymphoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-CCR7 Antibody (A00390-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-CCR7 Antibody
Cat # A00390-2
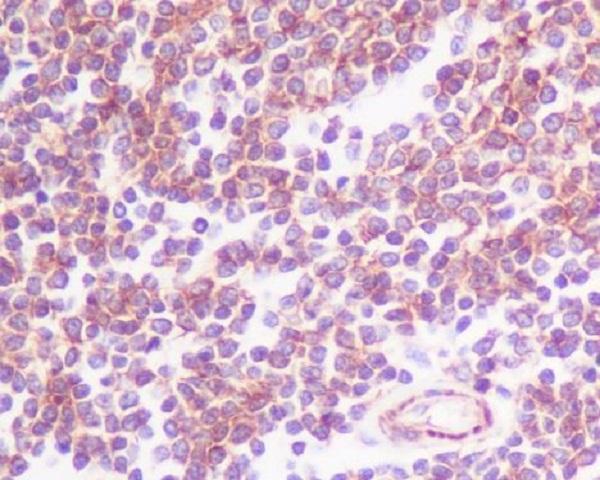
Real IHC data Immunohistochemical analysis of paraffin-embedded human spleen, using CCR7 Antibody.
Anti-CCR7 Rabbit Monoclonal Antibody
Cat # M00390

A00390-2 will render with IHC data from a paraffin-embedded human lymphoma section (A00390-2 image caption). M00390 will render with IHC data from paraffin-embedded human spleen; its catalog also lists ICC/IF and an IF image of HeLa cells (M00390 image captions; catalog applications).

Which to pick: For tissue IHC, choose A00390-2 when a documented paraffin-section procedure is useful: its lymphoma caption reports EDTA retrieval and 2 μg/ml primary antibody (A00390-2 image caption). For IF/ICC, choose M00390, a rabbit monoclonal with ICC/IF listed and a HeLa IF image (M00390 catalog); it also lists human, mouse and rat reactivity for cross-species work (M00390 catalog reactivity). Both IHC captions describe paraffin sections, but neither reports the fixative (A00390-2 and M00390 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P32248 (CCR7_HUMAN, C-C chemokine receptor type 7).
  2. Human Protein Atlas. CCR7 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CCR7 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. CCR7 antibody validation summary (3 antibodies).
  5. Investigation of CCR7 Marker Expression Using Immunohistochemical Method and Its Association with Clinicopathologic Properties in Patients with Breast Cancer. International journal of hematology-oncology and stem cell research 2018 — PMC6141431.
  6. CC-Chemokine receptor CCR7: a key molecule for lymph node metastasis in esophageal squamous cell carcinoma. BMC cancer 2014 — PMC4008409.
  7. Adipose-specific C-C motif chemokine ligand (CCL) 19 overexpression drives the mice to both insulin resistance and weight gain. BMJ open diabetes research & care 2021 — PMC8149363.
  8. Increased expression of the homeostatic chemokines CCL19 and CCL21 in clinical and experimental Rickettsia conorii infection. BMC infectious diseases 2014 — PMC3923395.
  9. PubMed PMID:8383238 — UniProt-cited evidence.
  10. PubMed PMID:7851893 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.