CDC25C / M-phase inducer phosphatase 3 · IHC design guide

Design Immunohistochemistry for CDC25C

Plan chromogenic CDC25C IHC in paraffin sections using the catalog antibody’s documented workflow (datasheet M01343). Use the general nuclear tissue pattern and the staining–RNA consistency warning to choose controls and interpret results (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CDC25C (IHC for CDC25C): expected localisation General nuclear tissue staining (HPA tissue IHC), antibody M01343, validated IHC image, and IHC protocol steps
Printable CDC25C IHC protocol sheet — expected localisation General nuclear tissue staining (HPA tissue IHC), antibody M01343, controls and protocol steps. Open the full CDC25C IHC guide →

CDC25C Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General nuclear tissue staining (HPA tissue IHC)
Staining pattern Nuclear staining across diverse cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M01343)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Liver+3 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining and RNA expression show low consistency (HPA tissue IHC)
Regulation Expression regulation unreported (UniProt)
Isoform / epitope 5 isoforms; no TM segment; epitope coverage unknown (UniProt; datasheet M01343)
Section 1

Recommended CDC25C IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet M01343) with published CDC25C protocols for lung adenocarcinoma (PMC9952919), vulvar carcinoma (PMC2887779), and glioma (PMC12480179).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human stomach cancer tissue; fixative not specified (datasheet M01343)
FixationImage fixative and duration unreported (datasheet M01343); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M01343); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M01343)
Primary antibodyRabbit monoclonal (clone HIG-3) anti-CDC25C, 1:50 recommended; image 1:100 (datasheet M01343)
Primary incubationOvernight at 4 °C (datasheet M01343)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M01343)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCDC25C-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet M01343); published alternatives include EDTA (PMC9952919) and citrate pH 6.0 (PMC2887779; PMC12480179).
Section 2

What Is the Expected CDC25C Staining Pattern?

CDC25C localises to the nucleus and has no transmembrane segment (UniProt P30307). In paraffin sections, expect nuclear staining in the cell populations reported as positive by HPA, including adrenal glandular and cervical squamous epithelial cells (HPA tissue IHC: High). HPA describes general nuclear expression, but rates the tissue IHC pattern Approved with low consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Nuclear staining in adrenal glandular cells or cervical squamous epithelial cells, with identifiable nuclei after counterstaining (HPA tissue IHC: High; general IHC practice).This matches the reported compartment and cell populations (UniProt P30307: nucleus; HPA tissue IHC: general nuclear expression, High in these cells). Judge intensity relative to controls processed in the same run; the HPA level is an observation, not a required score for every section (general IHC practice).
Predominantly cytoplasmic, membranous, or extracellular chromogen, without convincing nuclear staining (UniProt P30307: nucleus; HPA tissue IHC: general nuclear expression).The compartment conflicts with the supplied localisation evidence and warrants an artefact or cross-reactivity check (UniProt P30307; HPA tissue IHC; general IHC practice). It does not, by itself, identify the cause. Compare the no-primary control and examine whether chromogen follows tissue edges or damaged areas (general IHC practice).
Strong staining in cholangiocytes, ovarian stroma cells, smooth muscle cells, or soft-tissue fibroblasts (HPA tissue IHC: Not detected).These cell populations were reported as not detected, so strong signal is discordant and may reflect cross-reactivity or endogenous detection activity (HPA tissue IHC; general IHC practice). Check compartment and controls before interpreting it as CDC25C; an HPA observation is not a universal absence claim (HPA tissue IHC; general IHC practice).
Diffuse colour across nuclei, cytoplasm, and surrounding tissue, including the no-primary control (general IHC practice).A broadly distributed signal that persists without primary antibody points toward background from the detection workflow rather than interpretable CDC25C localisation (general IHC practice). Review blocking, washes, endogenous enzyme control where relevant, and chromogen development alongside the stained section (general IHC practice).
No convincing nuclear signal in an adrenal glandular or esophageal squamous epithelial positive comparison (HPA tissue IHC: High).First consider a failed or weak staining run, section quality, or an antibody-specific performance issue (general IHC practice). HPA reports High staining in those cells, yet its Approved tissue IHC profile has low consistency with RNA data; a negative section alone cannot settle biological absence (HPA tissue IHC).
💡Expected CDC25C appearanceCall the result consistent when nuclear chromogen is clear in HPA-reported positive cells, such as adrenal glandular or cervical squamous epithelial cells, while diffuse background or strong staining in HPA-reported not-detected cells prompts review (UniProt P30307: nucleus; HPA tissue IHC: High/Not detected; general IHC practice).
How each factor affects the staining
Cell population and evidence strength (HPA tissue IHC)HPA reports High staining in several distinct populations, including glial cells in caudate and hippocampus, and Not detected in selected cholangiocytes and stromal cells (HPA tissue IHC). Its overall tissue IHC rating is Approved with low staining–RNA consistency, so interpret these as reported patterns rather than guaranteed controls (HPA tissue IHC).
Antibody validation and epitope coverage (HPA antibodies; UniProt P30307)CAB003800 has Approved IHC validation, while HPA066991 has no IHC status in the supplied record (HPA antibodies). CDC25C has 5 listed isoforms and a rhodanese domain at residues 321–428; without an antibody epitope, isoform recognition cannot be assigned (UniProt P30307).
IF/ICC Q: Should paraffin IHC show nuclear speckles? (HPA ICC-IF)A: HPA ICC-IF supports mainly nuclear-speckle localisation, while tissue IHC is described as general nuclear expression (HPA ICC-IF; HPA tissue IHC). Use nuclear localisation for the chromogenic IHC readout; do not require individual speckles to be resolved in a paraffin section (HPA tissue IHC; general IHC practice).
Antigen retrieval and detection controls (general IHC practice)Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive comparison is blank or markedly weaker than expected (HPA tissue IHC: High in adrenal glandular cells).The run may have insufficient primary-antibody signal or a detection failure; the slide alone does not distinguish these possibilities (general IHC practice).Confirm section integrity and counterstain, then review antibody use, retrieval, reagent activity, and the detection sequence with a positive comparison in the same run (general IHC practice).
Chromogen appears mainly outside nuclei (UniProt P30307: nucleus; HPA tissue IHC: general nuclear expression).Nonspecific binding, deposited chromogen, or damaged tissue may mimic a cellular signal (general IHC practice).Compare matched no-primary and positive sections, inspect morphology, and score only a credible nuclear signal in the expected cells (general IHC practice; HPA tissue IHC).
Strong colour occurs in cholangiocytes or smooth muscle cells (HPA tissue IHC: Not detected).Discordance may come from cross-reactivity or endogenous detection activity; HPA's report does not establish absolute biological absence (HPA tissue IHC; general IHC practice).Run a no-primary control and assess whether the colour follows nuclei, cytoplasm, or tissue-wide background before assigning CDC25C positivity (general IHC practice; UniProt P30307).
Diffuse staining obscures cell boundaries and nuclear assessment (general IHC practice).Excess background can arise from incomplete blocking, inadequate washing, or overdevelopment in a chromogenic workflow (general IHC practice).Inspect the no-primary control, adjust the relevant blocking and washing steps, and stop chromogen development while nuclear and tissue detail remain readable (general IHC practice).
Only faint staining is seen in splenic red-pulp or lymph-node non-germinal-center cells (HPA tissue IHC: Low).A faint result may agree with the reported Low level; it is not sufficient evidence of a failed assay without a stronger positive comparison (HPA tissue IHC; general IHC practice).Compare an HPA High population processed in the same run and score the faint cells by compartment and background rather than intensity alone (HPA tissue IHC; UniProt P30307; general IHC practice).
The stain is nuclear but uneven among cells in the same section (UniProt P30307: nucleus).CDC25C participates in cell-cycle progression, but this record does not establish that every observed intensity difference reflects cell-cycle phase (UniProt P30307). Technical variation also requires consideration (general IHC practice).Check morphology and section quality, compare repeat sections and controls, and avoid assigning a cell-cycle state from chromogenic intensity alone (general IHC practice; UniProt P30307).

Sample controls for CDC25C IHC & IF

🧪Run cerebral cortex first and score neuronal cells for CDC25C staining (HPA: High in cerebral cortex neuronal cells); run liver cholangiocytes as the negative tissue (HPA: Not detected in liver cholangiocytes). On the positive slide, use cells without specific nuclear staining, if present, as internal background comparators; do not assume that all non-neuronal cells are negative (UniProt P30307: nucleus).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Liver (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CDC25C in A-431, U-251MG, U2OS, CACO-2, SiHa, with annotated localisation: Nuclear speckles (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; an irrelevant rabbit IgG control matched to the primary antibody’s clonality and concentration (selected-SKU caption: rabbit anti-CDC25C); and a CDC25C knockout specimen as a biological specificity control. Quench endogenous peroxidase for HRP/DAB detection and assess native pigment in cerebral cortex before scoring (selected-SKU caption: HRP/DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU tissue-IHC caption does not state its fixative (selected-SKU caption: fixative not stated). Heat retrieval in EDTA at pH 8.0 was used for paraffin-section IHC, but whether retrieval is required is unreported (selected-SKU caption: EDTA pH 8.0); the supplied evidence does not establish that frozen sections or tissue IF are easier. Cerebral cortex lipofuscin can resemble brown chromogen or autofluoresce, so distinguish pigment from specific nuclear signal when scoring (HPA: High in cerebral cortex neuronal cells; standard tissue microscopy practice).

HPA tissue IHC evidence for CDC25C

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Caudate Glial cells High Protein (IHC) HPA →
Cerebellum Cells in molecular layer High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Cervix Squamous epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Soft tissue Fibroblasts Not detected Protein (IHC) HPA →
Section 3

Advanced CDC25C IHC Tips

Use nuclear staining, matched controls, and the catalog antibody’s documented paraffin-section conditions to troubleshoot CDC25C chromogenic IHC (UniProt P30307; datasheet M01343).

What retrieval should I start with when CDC25C staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet M01343). The documented stain used this retrieval, followed by a 1:100 primary-antibody incubation overnight at 4°C (datasheet M01343). If nuclei remain weak, compare retrieval heating time on adjacent sections while keeping antibody dilution and chromogen development constant (standard IHC practice). Include a previously staining control section in each run to distinguish poor retrieval from a failed detection step (standard IHC practice). Score nuclear signal separately from tissue damage, since excessive heating can impair section morphology (standard IHC practice).
How should I investigate variable CDC25C staining after fixation?
The selected paraffin-section caption does not report a fixative, so target-specific CDC25C fixation sensitivity is unknown (datasheet M01343). Record the fixative, fixation duration, section thickness, and time in storage for each specimen before comparing staining (standard IHC practice). Process a matched control section with the same EDTA pH 8.0 retrieval and 1:100 primary dilution used in the documented stain (datasheet M01343). If staining differs between batches, compare identically processed sections and inspect nuclear morphology before changing antibody concentration (standard IHC practice). Neither the reported nuclear location nor phosphorylation sites establish a fixation requirement (UniProt P30307).
Where should convincing CDC25C staining appear in a paraffin section?
Expect predominantly nuclear staining when assessing CDC25C chromogenic IHC (UniProt P30307; HPA tissue IHC: general nuclear expression). HPA reports nuclear speckles by ICC/IF, but chromogenic tissue sections may not resolve that fine pattern reliably (HPA subcellular; standard IHC practice). Compare signal within the same cell population against a no-primary control and a morphologically intact, previously staining section (standard IHC practice). Strong diffuse extracellular staining or staining confined to tissue folds warrants a check of background and section quality before interpretation (standard IHC practice). CDC25C has no transmembrane segment, so a membrane-only pattern needs independent validation (UniProt P30307 topology).
Could isoforms or phosphorylation explain discordant CDC25C staining?
CDC25C has 5 annotated isoforms and multiple modified residues, including phosphorylation sites near its N terminus (UniProt P30307). The supplied antibody caption does not identify its epitope or establish equal recognition of those isoforms (datasheet M01343). Ask for epitope information before attributing a negative section to isoform expression or phosphorylation, and compare matched sections under the documented EDTA pH 8.0 retrieval conditions (datasheet M01343; standard IHC practice). If a second independently validated antibody is available, compare its nuclear pattern in the same tissue region (standard IHC practice). Treat disagreement as unresolved antibody specificity or epitope accessibility until supported by additional evidence (standard IHC practice).
How can I adapt the CDC25C localisation check to multiplex IF?
Use IF as a separate localisation check and include a marker identifying the cell population being assessed, such as glandular cells in adrenal gland (HPA tissue IHC: high in adrenal gland glandular cells). Pair a nuclear counterstain with a spectrally distinct CDC25C fluorophore, and favor a far-red channel when tissue autofluorescence obscures shorter wavelengths (standard IF practice). Permeabilise sufficiently to expose intracellular nuclear epitopes, then compare signal with a no-primary control (UniProt P30307: nucleus; standard IF practice). HPA reports supported nuclear-speckle localisation in ICC/IF, providing a pattern to inspect at suitable resolution (HPA subcellular). Optimise IF antibody concentration independently; the 1:100 dilution documents paraffin-section IHC only (datasheet M01343).
What should I check when DAB obscures CDC25C nuclear staining?
First compare the stained section with a no-primary control to identify signal from the detection system or tissue itself (standard IHC practice). The documented chromogenic workflow used 10% goat serum blocking, an HRP-linked secondary reagent, and DAB development (datasheet M01343). Check endogenous peroxidase blocking, wash stringency, and DAB development time before increasing antibody dilution (standard IHC practice). Inspect tissue edges, folds, and damaged areas separately because local reagent accumulation can imitate strong staining (standard IHC practice). Retain a morphologically intact positive-control section so weaker background settings can be judged against preserved nuclear CDC25C signal (UniProt P30307: nucleus; standard IHC practice).
How should I score CDC25C across differently cellular tissue regions? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and region before scoring, then report the percentage of nuclei positive for CDC25C (UniProt P30307: nucleus; standard IHC practice). For an H-score, multiply each intensity category from 0–3 by its percentage of cells and sum to a 0–300 score (standard IHC practice). Alternatively, report positive nuclei per mm² alongside total nuclei per mm² to expose differences in cellularity (standard IHC practice). Normalise comparisons to the same eligible cell type, section area, staining run, and scoring threshold (standard IHC practice). Exclude necrosis, folds, and edge artefacts under a prespecified rule (standard IHC practice).
When is an apparent CDC25C-positive cell likely to be an artefact?
Give most weight to staining within intact nuclei of the cell population being assessed (UniProt P30307: nucleus; HPA tissue IHC: general nuclear expression). Treat staining limited to cut edges, folds, or necrotic regions as suspect and compare it with the no-primary control (standard IHC practice). Investigate DAB signal that persists without primary antibody through the endogenous-peroxidase and detection controls (standard IHC practice). HPA reports high staining in adrenal gland glandular cells and no detection in liver cholangiocytes, but also reports low consistency between antibody staining and RNA expression (HPA tissue IHC). Use those patterns as context, not proof of identity in an individual section (HPA tissue IHC; standard IHC practice).
Boster reagents

Best CDC25C / M-phase inducer phosphatase 3 IHC Antibodies

IHC images cover human paraffin sections; an IF image covers human U2OS cells (catalog image captions). The catalog also lists mouse and rat reactivity for PB9756 (catalog: PB9756 reactivity).

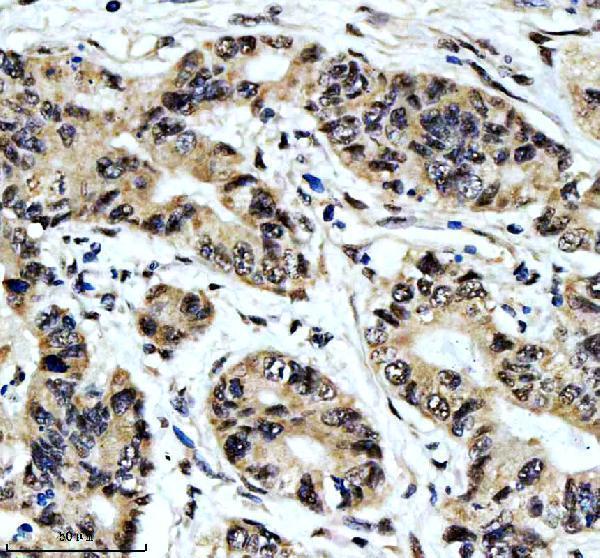
Real IHC data IHC analysis of CDC25C using anti-CDC25C antibody (M01343). CDC25C was detected in a paraffin-embedded section of human stomach cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:100 rabbit anti-CDC25C Antibody (M01343) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Cdc25C Rabbit Monoclonal Antibody
Cat # M01343
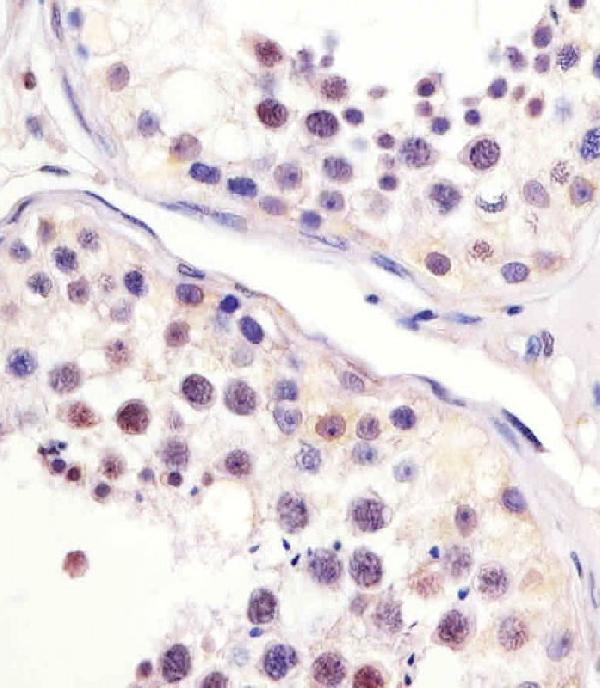
Real IHC data M01343-2 staining MPIP3 in human testis sections by Immunohistochemistry (IHC-P -paraformaldehyde-fixed, paraffin-embedded sections). Tissue was fixed with formaldehyde and blocked with 3% BSA for 0. 5 hour at room temperature; antigen retrieval was by heat mediation with a citrate buffer (pH6). Samples were incubated with primary antibody (1/25) for 1 hours at 37°C. A undiluted biotinylated goat polyvalent antibody was used as the secondary antibody.
Anti-MPIP3 Antibody
Cat # M01343-2
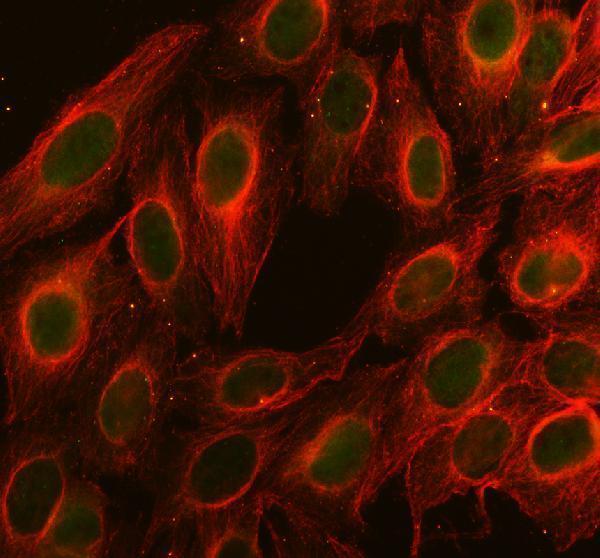
Real IF data IF analysis of Cdc25C using anti-Cdc25C antibody (PB9756) and anti-Tubulin Alpha antibody (M03989-3). Cdc25C was detected in immunocytochemical section of U2OS cell. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5 μg/mL rabbit anti-Cdc25C Antibody (PB9756) and mouse anti-Tubulin Alpha antibody (M03989-3) overnight at 4°C. DyLight®488 Conjugated Goat Anti-Rabbit IgG (BA1127) and Cy3 Conjugated Goat Anti-Mouse IgG (BA1031) were used as secondary antibody at 1:500 dilution and incubated for 30 minutes at 37°C. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-Cdc25C Antibody ®
Cat # PB9756

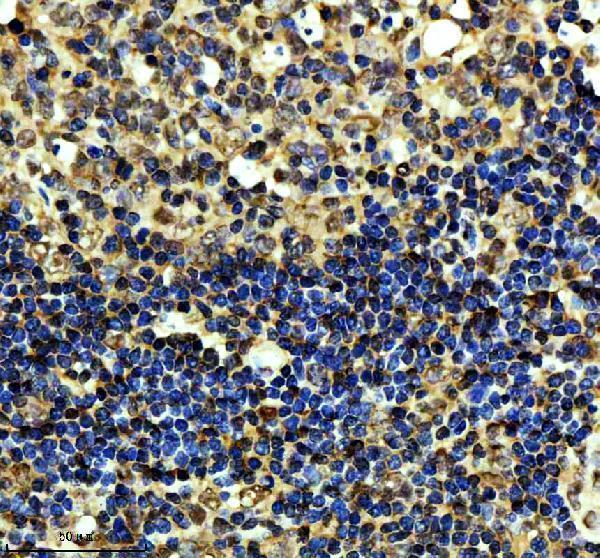
M01343 has IHC images of human stomach cancer, lymph node and stomach paraffin sections; M01343-2 has an IHC-P image of human testis sections (catalog image captions). PB9756 has an IF image of human U2OS cells (catalog image caption).

Which to pick: For tissue IHC, choose M01343 for human paraffin sections with EDTA retrieval; its caption does not report a fixative (M01343 IHC captions). M01343-2 offers a mouse monoclonal option for paraffin-section human testis sections with citrate retrieval (catalog: M01343-2 host and clone; M01343-2 IHC caption). For IF/ICC, choose PB9756 for its human U2OS IF image; mouse and rat are listed as reactive species, but its stated IF validation is human (PB9756 IF caption; PB9756 dilution_raw and reactivity). The selected M01343 tissue-IHC caption documents paraffin sections, but does not specify the fixative (selected-SKU IHC image M01343).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P30307 (MPIP3_HUMAN, M-phase inducer phosphatase 3).
  2. Human Protein Atlas. CDC25C tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. CDC25C subcellular location (ICC-IF): Mainly localized to the nuclear speckles..
  4. Human Protein Atlas. CDC25C antibody validation summary (2 antibodies).
  5. CDC25C Protein Expression Correlates with Tumor Differentiation and Clinical Outcomes in Lung Adenocarcinoma. Biomedicines 2023 — PMC9952919.
  6. Overexpression of Cdc25C predicts response to radiotherapy and survival in esophageal squamous cell carcinoma patients treated with radiotherapy followed by surgery. Chinese journal of cancer 2013 — PMC3845600.
  7. Overexpression of CDC25B, CDC25C and phospho-CDC25C (Ser216) in vulvar squamous cell carcinomas are associated with malignant features and aggressive cancer phenotypes. BMC cancer 2010 — PMC2887779.
  8. Cell division cycle 25 C (CDC25C) mediates cell-cycle progression and immune evasion in glioma. Discover oncology 2025 — PMC12480179.
  9. PubMed PMID:2195549 — UniProt-cited evidence.
  10. PubMed PMID:11078813 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.