CEP78 / Centrosomal protein of 78 kDa · IHC design guide

Design Immunohistochemistry for CEP78

Plan CEP78 IHC on paraffin sections using its reported cytoplasmic tissue staining and cell specific HPA evidence (HPA tissue IHC). Compare positive kidney tubular cells with a tissue reported as undetected, and assess antibody specificity before interpreting intensity (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CEP78 (IHC for CEP78): expected localisation Cytoplasmic tissue staining; centriolar localization is molecular (HPA tissue IHC; UniProt), antibody A13706, validated IHC image, and IHC protocol steps
Printable CEP78 IHC protocol sheet — expected localisation Cytoplasmic tissue staining; centriolar localization is molecular (HPA tissue IHC; UniProt), antibody A13706, controls and protocol steps. Open the full CEP78 IHC guide →

CEP78 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining; centriolar localization is molecular (HPA tissue IHC; UniProt)
Staining pattern Cytoplasmic staining in most tissues, including kidney tubules (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Breast+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Tissue staining has medium RNA concordance; verify specificity (HPA tissue IHC)
Regulation Widely expressed; no specific regulator reported (UniProt)
Isoform / epitope 4 isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended CEP78 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is followed by published CEP78 staining protocols for colorectal tissue, bladder tissue, and human retina (PMC4928268; PMC7607667; PMC8097100).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast carcinoma tissue; fixative not specified (datasheet A13706)
FixationImage fixative and duration unreported (datasheet A13706); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CEP78, 1:100-1:300 (datasheet A13706)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
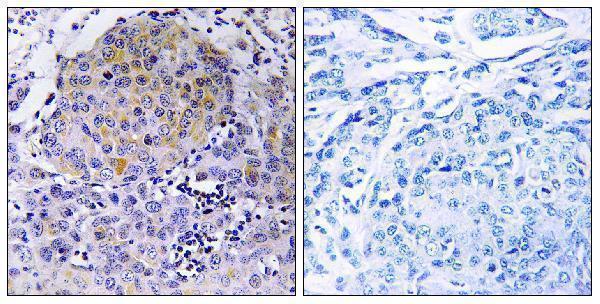
Expected resultCEP78-positive staining in myoepithelial cells of breast (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page retrieval rule). For retinal protocol replication, use its stated retrieval reagent (PMC8097100).
Section 2

What Is the Expected CEP78 Staining Pattern?

CEP78 is a cytoplasmic protein associated with the centrosome, centriole and cilium basal body; it has no transmembrane segment (UniProt Q5JTW2). In paraffin sections, expect cytoplasmic staining in selected cells, including breast myoepithelial cells, bronchial respiratory epithelial cells and kidney tubule cells (HPA: High). HPA rates its tissue IHC profile Approved, with medium consistency between staining and RNA data; external verification is pending (HPA: tissue IHC).

What am I looking at on my slide?
Cytoplasmic staining appears in breast myoepithelial cells, bronchial respiratory epithelium or kidney tubules.This fits the reported high staining in those cell types (HPA: High). Compare cells within the section: an HPA tissue level describes the listed cell population, not every cell in that tissue (HPA: tissue IHC).
A small focus near the nucleus accompanies cytoplasmic staining in a positive cell.A centrosomal focus is biologically plausible because CEP78 localizes mainly to the centriolar wall and also to pericentriolar material (UniProt Q5JTW2). Chromogenic IHC may not resolve that structure; judge the focus alongside the broader tissue pattern (general IHC practice; HPA: cytoplasmic expression in most tissues).
Strong nuclear staining dominates, with little cytoplasmic staining.This conflicts with the reported centrosome, centriole and basal body localization (UniProt Q5JTW2) and HPA's cytoplasmic tissue profile (HPA: tissue IHC). Treat the compartment mismatch as possible nonspecific staining and check controls (general IHC practice).
Strong signal appears chiefly in adipocytes or smooth muscle cells.Those listed cell populations were not detected by HPA tissue IHC (HPA: adipocytes Not detected; smooth muscle cells Not detected). Consider cross-reactivity or endogenous chromogen activity; a reported negative cell type is a comparison, not proof that its whole tissue must be blank (general IHC practice; HPA: tissue IHC).
Diffuse color covers cells and extracellular areas, or a known-positive cell population remains blank.Neither result supports a cell-specific CEP78 call (HPA: cytoplasmic tissue profile). Diffuse color calls for a no-primary control; a blank positive population calls for checks of tissue identity, staining reagents and assay conditions (general IHC practice).
💡Expected CEP78 appearanceCall a positive when cytoplasmic signal is discernible in an HPA High cell population, such as kidney tubule cells, with a possible unresolved centrosomal focus; strong nuclear-only staining or uniform color across unrelated structures is suspicious (HPA: kidney tubules High; HPA: cytoplasmic tissue profile; UniProt Q5JTW2 localization; general IHC practice).
How each factor affects the staining
Cell population selected for comparisonHPA reports High staining in breast myoepithelial cells, bronchial respiratory epithelial cells, kidney tubule cells and late spermatids, but Not detected in adipocytes and smooth muscle cells (HPA: tissue IHC). Score the named cell populations separately (general IHC practice).
Compartment and optical resolutionCEP78 is mainly at the centriolar wall and also occurs in pericentriolar material and the cilium basal body (UniProt Q5JTW2). HPA describes cytoplasmic staining in most tissues (HPA: tissue IHC); a discrete centriole is not required for a chromogenic IHC call (general IHC practice).
Strength of antibody evidenceThe listed antibody HPA048846 has Approved IHC status, while the tissue profile has medium staining-to-RNA consistency and awaits external verification (HPA: antibody validation; HPA: tissue IHC). Interpret an unexpected pattern cautiously rather than treating approval as target-specific proof in every cell type.
Molecular annotationsUniProt lists four CEP78 isoforms, phosphoserines at residues 325 and 327, no transmembrane segment, and no signal peptide or propeptide (UniProt Q5JTW2). These annotations do not establish which isoforms an antibody detects or predict a paraffin-section retrieval response.
IF/ICC Q: Is an HPA punctate IF pattern established?A: HPA supplies no ICC-IF images or main subcellular location for CEP78, and HPA048846 has no listed ICC validation (HPA: subcellular; HPA: antibody validation). UniProt supports centrosomal localization, but this record cannot confirm an antibody-specific IF pattern (UniProt Q5JTW2).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in kidney tubule cells or bronchial respiratory epithelial cellsThese are HPA High populations, so a blank result warrants an assay check, but tissue IHC consistency is only medium (HPA: tissue IHC).Confirm the named cells are present, then check the positive control, reagent sequence and detection system; review retrieval against the assay instructions without assuming CEP78-specific fixation sensitivity (general IHC practice).
Broad color appears in the no-primary controlSignal without primary antibody can reflect endogenous detection activity or background from the detection workflow (general IHC practice).Address endogenous activity appropriate to the chromogen system, review blocking and washes, and repeat the control before assigning CEP78 positivity (general IHC practice).
Strong nuclear staining outweighs cytoplasmic stainingA dominant nuclear pattern conflicts with HPA's cytoplasmic profile and UniProt's centrosomal localization (HPA: tissue IHC; UniProt Q5JTW2).Check the no-primary control and compare with a named HPA High cell population; regard persistent nuclear-only signal as unverified specificity (general IHC practice; HPA: tissue IHC).
Adipocytes or smooth muscle cells stain as strongly as the intended positive cellsHPA lists those cell types as Not detected, making cross-reactivity or background plausible (HPA: tissue IHC; general IHC practice).Identify the stained cell type on the counterstain, inspect controls and reassess antibody specificity before scoring it as CEP78 (general IHC practice).
Only scattered puncta are visible, without a clear cell-associated patternCEP78's centriolar location makes a focus plausible, but a chromogenic punctum alone cannot establish its identity (UniProt Q5JTW2; general IHC practice).Assess whether puncta occur in the expected HPA positive cells and disappear from the no-primary control; record unresolved foci as uncertain (HPA: tissue IHC; general IHC practice).
A low or undetected HPA population gives weak, uneven colorHPA reports Low staining in lung alveolar cells and Not detected in duodenal glandular cells, so weak color alone is inconclusive (HPA: tissue IHC).Use a named HPA High population as the run comparison and score the actual cell type; avoid turning a weak, uneven signal into a definitive positive call (HPA: tissue IHC; general IHC practice).

Sample controls for CEP78 IHC & IF

🧪Run breast first and assess myoepithelial cells for CEP78 staining (HPA: High in breast myoepithelial cells); use adipose tissue as the negative tissue and assess adipocytes (HPA: Not detected in adipocytes). Adjacent breast stromal cells can serve as candidate internal negatives if they lack specific centrosomal staining, but their CEP78 status is not established by the supplied HPA rows (UniProt Q5JTW2: centrosomal localisation).
Positive control tissue: Breast (Myoepithelial cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for CEP78; derive a cell-line control from the positive tissue's cell type (Myoepithelial cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control, an isotype control matched to the primary antibody’s host species and clonality, and peptide competition where the matching peptide is available (selected A13706 tissue-IHC caption: staining blocked with synthesized peptide). For chromogenic breast IHC, quench endogenous peroxidase and check the no-primary slide for residual background (standard IHC practice).
⚠️Feasibility: A target-specific fixation window and retrieval dependency are unreported in the supplied evidence; optimise antigen retrieval for the catalog antibody using matched sections (standard IHC practice). The selected A13706 paraffin-section caption does not report a fixative (selected A13706 tissue-IHC caption: fixative unreported). The evidence does not establish that frozen sections or IF/ICC are easier than paraffin IHC; assess breast-section background before interpreting faint centrosomal staining (UniProt Q5JTW2: centrosomal localisation; standard IHC practice).

HPA tissue IHC evidence for CEP78

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Breast Myoepithelial cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →
Kidney Cells in tubules High Protein (IHC) HPA →
Nasopharynx Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Duodenum Glandular cells Not detected Protein (IHC) HPA →
Fallopian tube Glandular cells Not detected Protein (IHC) HPA →
Hippocampus Glial cells Not detected Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced CEP78 IHC Tips

Troubleshoot CEP78 chromogenic staining in paraffin sections using the page retrieval setting, the catalog antibody image, and tissue and localisation evidence.

What should I change when CEP78 staining is weak after antigen retrieval?
Use citrate buffer at pH 6.0 for heat-induced retrieval at 95–98 °C for 20 min (page retrieval setting). Keep section thickness, cooling, antibody incubation, and chromogen development consistent while comparing adjacent sections (standard IHC practice). Check a reference section alongside the test section; the selected catalog image shows staining in paraffin-embedded human breast carcinoma with a peptide-blocked comparison (A13706 caption). If staining remains weak, assess tissue preservation and antibody concentration before testing another retrieval condition on matched sections (standard IHC practice). Judge improvement by clearer cellular staining without a parallel rise in diffuse background (standard IHC practice).
Can fixation explain weak or inconsistent CEP78 staining in paraffin sections?
Target-specific fixation sensitivity is unknown because the supplied CEP78 evidence reports no fixation condition for the selected tissue image (A13706 caption). The image identifies paraffin-embedded human breast carcinoma and a peptide-blocked comparison, but does not establish how fixation affected staining (A13706 caption). Record the fixative, fixation duration, processing history, and section age for each case before comparing signal intensity (standard IHC practice). When those variables differ, stain adjacent reference and test sections in the same run and inspect morphology alongside the chromogenic signal (standard IHC practice). Do not assign a weak result to CEP78 fixation sensitivity without a controlled comparison (standard IHC practice).
Should CEP78 appear as diffuse cytoplasmic staining or discrete centrosomal puncta?
CEP78 localizes to the centrosome, centriole, and ciliary basal body, mainly at the centriolar wall with some pericentriolar signal (UniProt Q5JTW2). Tissue IHC also reports cytoplasmic staining across most tissues, so diffuse cytoplasmic signal can occur in this assay context (HPA tissue IHC). Inspect higher magnification fields for perinuclear focal enrichment, while recognizing that a small centriole may be unresolved by routine chromogenic microscopy (UniProt Q5JTW2; standard IHC practice). Compare the staining pattern with the peptide-blocked section and a matched reference section before assigning isolated dots to CEP78 (A13706 caption; standard IHC practice). Predominantly nuclear staining warrants specificity review because the supplied localisation evidence places CEP78 in cytoplasmic structures (UniProt Q5JTW2).
Could CEP78 isoforms or phosphorylation change what this antibody detects?
CEP78 has 4 annotated isoforms and phosphoserine sites at residues 325 and 327 (UniProt Q5JTW2). The supplied catalog image includes a synthesized-peptide blocking comparison, but does not identify the antibody epitope or establish isoform coverage (A13706 caption). Ask for an epitope map before attributing differences between sections to alternative splicing or phosphorylation (UniProt Q5JTW2; standard IHC practice). Compare staining under identical retrieval and detection conditions, including a peptide-blocked section where available, and document which compartments retain signal (A13706 caption; standard IHC practice). Peptide competition supports recognition of the competing sequence but alone cannot prove discrimination among CEP78 isoforms (standard IHC practice).
How can I check CEP78 localisation with multiplex immunofluorescence?
Use a separately validated marker of the expected cell type, such as a myoepithelial marker when examining breast myoepithelial cells, and score overlap by cell (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores after checking tissue autofluorescence and single-label controls, favoring a cleaner channel for the weaker CEP78 signal (standard IF practice). Permit intracellular antibody access with controlled permeabilisation because CEP78 is associated with cytoplasmic centriolar structures and has no annotated transmembrane segment (UniProt Q5JTW2; standard IF practice). The epitope is unspecified, so titrate permeabilisation against structural preservation rather than assuming a particular membrane-facing epitope (A13706 caption; standard IF practice). Confirm puncta against nuclear position and a centrosomal reference marker in the same cells (UniProt Q5JTW2; standard IF practice).
How do I separate CEP78 signal from diffuse chromogenic background?
Include a no-primary control and a matched peptide-blocking comparison where material permits; the selected catalog image includes the latter (A13706 caption; standard IHC practice). Quench endogenous peroxidase before horseradish-peroxidase detection, and compare DAB development under identical timing across control and test sections (standard IHC practice). Check whether color follows cell boundaries or instead accumulates at section edges, folds, pigment, or damaged areas (standard IHC practice). Reduce excessive primary-antibody exposure or detection amplification only after confirming that the reference section retains interpretable CEP78 staining (standard IHC practice). Evaluate true cellular signal with morphology and expected cytoplasmic or centrosomal localisation, rather than total brown area alone (HPA tissue IHC; UniProt Q5JTW2).
What should I quantify when CEP78 staining varies across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue region before scoring, since HPA reports both high staining in breast myoepithelial cells and undetected staining in adipocytes (HPA tissue IHC). For broad cytoplasmic staining, record the percentage of positive target cells and an intensity-weighted H-score using the same thresholds across sections (HPA tissue IHC; standard IHC practice). For resolvable focal staining, report CEP78-positive puncta per mm² of viable target-cell area alongside the percentage of target cells assessed (UniProt Q5JTW2; standard IHC practice). Normalize comparisons to viable target-cell count or area, not total section area, and exclude folds and necrosis (standard IHC practice). Keep retrieval and DAB development matched across runs (page retrieval setting; standard IHC practice).
Which CEP78 staining patterns deserve a specificity check?
Give greatest weight to staining in intact target cells with cytoplasmic signal or plausible centrosomal enrichment, consistent with the supplied tissue and localisation evidence (HPA tissue IHC; UniProt Q5JTW2). Review strong nuclear-only staining, acellular deposits, edge accentuation, and staining confined to necrotic regions as possible artefacts (UniProt Q5JTW2; standard IHC practice). Check endogenous enzyme contribution with a no-primary control when interpreting DAB deposits (standard IHC practice). Compare the candidate signal with the selected antibody's peptide-blocked image, while recognizing that peptide blocking alone does not establish cellular specificity (A13706 caption; standard IHC practice). HPA calls its tissue staining Approved but notes medium RNA concordance and pending external verification, so interpret unexpected cell patterns cautiously (HPA tissue IHC).
Boster reagents

Best CEP78 / Centrosomal protein of 78 kDa IHC Antibodies

A13706 has a human paraffin-section IHC image (catalog image caption); IF is listed for human and mouse, with no IF image supplied (catalog applications and reactivity).

Real IHC data Immunohistochemistry analysis of paraffin-embedded human breast carcinoma tissue, using CEP78 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-CEP78 Antibody
Cat # A13706

A13706 has an IHC image of paraffin-embedded human breast carcinoma tissue with a peptide-blocked comparison (catalog image caption). IF is listed and human and mouse reactivity is reported, but no IF image is supplied (catalog applications, reactivity and image records).

Which to pick: Choose A13706 for tissue IHC because its own image shows staining in paraffin-embedded human breast carcinoma tissue; the fixative is unreported (catalog image caption). A13706 is also the IF/ICC candidate because IF is listed, though ICC-specific validation is unreported (catalog applications). For cross-species work, A13706 lists human and mouse reactivity and is polyclonal, but its IHC image documents human tissue only (catalog reactivity, dilution record and image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q5JTW2 (CEP78_HUMAN, Centrosomal protein of 78 kDa).
  2. Human Protein Atlas. CEP78 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. CEP78 subcellular location (ICC-IF): Highest expression in HAP1: 45.5 nTPM.
  4. Human Protein Atlas. CEP78 antibody validation summary (1 antibodies).
  5. Low expression of centrosomal protein 78 (CEP78) is associated with poor prognosis of colorectal cancer patients. Chinese journal of cancer 2016 — PMC4928268.
  6. Centrosome Protein 78 Is Overexpressed in Muscle-Invasive Bladder Cancer and Is Associated with Tumor Molecular Subtypes and Mutation Signatures. Medical science monitor : international medical journal of experimental and clinical research 2020 — PMC7607667.
  7. Long-Read Sequencing to Unravel Complex Structural Variants of CEP78 Leading to Cone-Rod Dystrophy and Hearing Loss. Frontiers in cell and developmental biology 2021 — PMC8097100.
  8. PubMed PMID:15164053 — UniProt-cited evidence.
  9. PubMed PMID:15489334 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.