This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan CHPF chromogenic IHC in paraffin sections around granular cytoplasmic and membranous staining (HPA tissue IHC). Start with the catalog antibody’s 1:100–1:300 IHC dilution range (datasheet), using glandular cells as a positive reference and adipocytes as a negative reference (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Granular cytoplasmic and membranous staining (HPA tissue IHC) | |
| Staining pattern | Granular cytoplasm and membranes in glandular cells (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | Antibody staining has medium consistency with RNA expression (HPA tissue IHC) | |
| Regulation | No specific expression regulator reported (UniProt) | |
| Isoform / epitope | 3 isoforms; epitope map unknown; cytosolic versus luminal side matters (UniProt) |
Compare the catalog antibody’s IHC-P protocol (datasheet) with three published CHPF IHC protocols (PMC8002199; PMC6499445; PMC8464597).
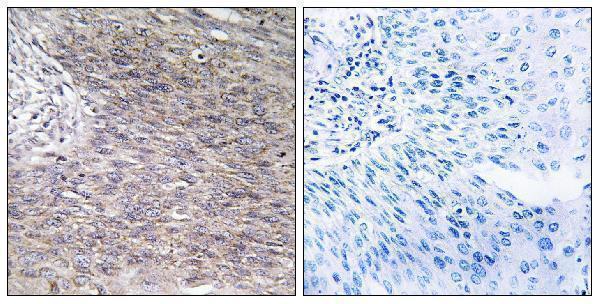
| Sample | Paraffin-embedded human cervix carcinoma tissue; fixative not specified (datasheet A30610) |
| Fixation | Image fixative and duration unreported (datasheet A30610); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-CHPF, 1:100 - 1:300 (datasheet A30610) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CHPF-positive staining in glandular cells of appendix (HPA tissue IHC: Medium). HPA tissue profile: Granular cytoplasmic and membranous expression in several tissues. No signal in the no-primary control. |
CHPF is annotated at the Golgi stack membrane, with cytosolic and mitochondrial locations; its single membrane span is at residues 16–34 (UniProt Q8IZ52 topology and subcellular location). In tissue IHC, expect granular cytoplasmic and membranous staining in selected cells, including glandular and respiratory epithelial cells (HPA tissue IHC). HPA rates the tissue pattern Approved, with medium consistency between staining and RNA data (HPA tissue IHC).
| Granular cytoplasmic or membranous signal in glandular cells of appendix, breast, cervix or duodenum (HPA tissue IHC). | This matches the reported medium staining in those cells (HPA tissue IHC). Use cell identity and compartment together when judging a positive section; neither feature alone establishes antibody specificity. |
| Granular cytoplasmic or membranous signal in bronchial respiratory epithelial cells or caudate neuronal cells (HPA tissue IHC). | Both are reported at medium intensity (HPA tissue IHC). CHPF has multiple annotated locations (UniProt Q8IZ52 subcellular location), so a tissue section need not resolve a single Golgi structure. |
| Predominantly nuclear staining, with little corresponding cytoplasmic or membranous signal. | A dominant nuclear pattern conflicts with the reported tissue pattern (HPA tissue IHC) and annotated locations (UniProt Q8IZ52 subcellular location). Check the control section and detection background before calling it CHPF. |
| Strong signal in adipocytes or oral mucosal squamous epithelial cells, especially if control tissue stains broadly. | Those cell populations are reported as not detected (HPA tissue IHC). Consider cross-reactivity or endogenous detection activity; a single discordant section does not identify which is responsible. |
| Uniform haze across cells and extracellular areas, or no signal in appendix glandular cells. | Diffuse haze lacks the reported granular cellular pattern; appendix glandular cells are reported at medium intensity (HPA tissue IHC). Assess background and assay performance separately before interpreting absence as biology. |
| Cell population and tissue | HPA reports medium signal in several specified cell populations but not detected signal in others (HPA tissue IHC). Score the named cell type within each section, rather than assigning one expectation to the whole organ. |
| Membrane topology and antibody epitope | CHPF has one membrane span at residues 16–34, with residues 1–15 cytoplasmic and 35–775 luminal (UniProt Q8IZ52 topology). The supplied record does not locate the antibody epitope, so it cannot predict epitope-specific retrieval or permeabilisation needs. |
| Isoforms and glycosylation | UniProt lists 3 isoforms and glycosylation sites at residues 138 and 361 (UniProt Q8IZ52). Antibody recognition of individual isoforms and any effect of glycosylation on staining are unspecified; avoid attributing pattern differences to either. |
| Evidence across assay types | Tissue IHC is Approved with medium staining–RNA consistency (HPA tissue IHC); HPA ICC-IF reports supported cytosol plus approved vesicle and centrosome locations (HPA subcellular). IF/ICC expectation? Consult its own guide: these cultured-cell observations do not establish a paraffin-section staining pattern. |
| RNA and protein observations | UniProt describes broad expression, including skeletal muscle (UniProt Q8IZ52 tissue specificity), while HPA reports skeletal myocytes as not detected by tissue IHC (HPA tissue IHC). Treat that difference as assay-context evidence, not proof of an IHC-positive myocyte. |
| Situation | Likely cause | Next action |
|---|---|---|
| No signal in appendix glandular cells. | The expected medium signal is missing (HPA tissue IHC); the section alone cannot distinguish assay failure from sample variation. | Check a matched positive section, antibody and detection controls, then review the general IHC workflow, including retrieval, primary-antibody incubation and chromogen development (general IHC practice). |
| Uniform brown haze obscures cellular boundaries. | This differs from granular cytoplasmic and membranous expression (HPA tissue IHC); nonspecific binding or detection background is possible (general IHC practice). | Compare a primary-antibody omission control; review blocking, washes and detection timing (general IHC practice). Re-score only where cell boundaries and subcellular signal remain interpretable. |
| Strong nuclear staining dominates the section. | A dominant nuclear pattern lacks support from the tissue profile (HPA tissue IHC) or annotated CHPF locations (UniProt Q8IZ52 subcellular location). | Inspect a known-positive tissue alongside the test section and compare omission-control staining (general IHC practice). Do not score nuclear-only signal as a confirmed CHPF positive. |
| Adipocytes or oral mucosal squamous cells stain strongly. | HPA reports these cells as not detected (HPA tissue IHC); cross-reactivity or endogenous detection activity may account for discordant signal. | Compare primary-antibody omission and detection controls, then recheck cell identity and staining distribution (general IHC practice). Investigate persistent signal before assigning CHPF expression. |
| Skeletal myocytes are negative despite broad expression reported by UniProt. | HPA reports skeletal myocytes as not detected by tissue IHC (HPA tissue IHC), whereas UniProt lists skeletal muscle among highly expressed tissues (UniProt Q8IZ52 tissue specificity). | Use an HPA medium cell population as the IHC performance reference (HPA tissue IHC). Record the myocyte result separately; do not infer an antigen-retrieval or fixation defect from this difference. |
| Only diffuse cytosolic signal is visible and a discrete Golgi pattern cannot be resolved. | HPA describes granular cytoplasmic and membranous tissue staining (HPA tissue IHC); UniProt also annotates cytosol and Golgi stack membrane (UniProt Q8IZ52 subcellular location). | Assess granularity, cell specificity and control background at the section's available resolution (general IHC practice). Reserve a positive call for a pattern consistent with the tissue IHC profile (HPA tissue IHC). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Breast | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Medium | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Hippocampus | Glial cells | Not detected | Protein (IHC) | HPA → |
| Oral mucosa | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot CHPF staining in paraffin sections by checking retrieval, compartment, controls and scoring together (UniProt Q8IZ52; HPA tissue IHC).
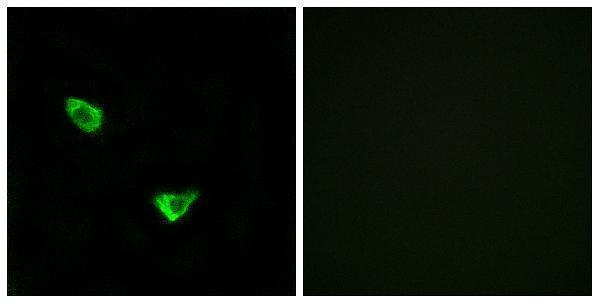
A30610 has IHC data from paraffin-embedded human cervix carcinoma tissue (IHC image caption) and IF data from MCF7 cells (IF image caption); catalog reactivity includes human, mouse, and rat (catalog).
A30610 will render with its IHC image from paraffin-embedded human cervix carcinoma tissue (IHC image caption). Its IF image shows MCF7 cells (IF image caption), while IHC, IF, and ICC are listed applications (catalog).
Which to pick: For tissue IHC, choose A30610; its own image documents paraffin-embedded human cervix carcinoma tissue, with the fixative unreported (IHC image caption). For IF/ICC, A30610 has an IF image in MCF7 cells (IF image caption) and lists ICC as an application (catalog). For cross-species work, this rabbit polyclonal antibody lists human, mouse, and rat reactivity (catalog); the supplied IHC image documents human tissue only (IHC image caption).