COL1A2 / Collagen alpha-2(I) chain · IHC design guide

Design Immunohistochemistry for COL1A2

This paraffin-section IHC guide helps interpret COL1A2 cytoplasmic tissue staining alongside its extracellular matrix location (HPA tissue IHC; UniProt). It covers fixation consistency, the catalog antibody’s 1:100–1:300 IHC dilution range, and a secondary-only control (datasheet A00624-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for COL1A2 (IHC for COL1A2): expected localisation Cytoplasmic tissue staining (HPA tissue IHC); extracellular matrix (UniProt), antibody A00624-1, validated IHC image, and IHC protocol steps
Printable COL1A2 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC); extracellular matrix (UniProt), antibody A00624-1, controls and protocol steps. Open the full COL1A2 IHC guide →

COL1A2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC); extracellular matrix (UniProt)
Staining pattern Cytoplasmic staining; high in cervical glandular cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, heat-mediated (datasheet A00624-1)
Positive control ⓘ Cervix+4 more · see all
Negative control ⓘ None in HPA (detected in all 44 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A00624-1)
Caveat Secreted protein: tissue RNA and staining may differ (HPA tissue IHC)
Regulation Expression regulation not reported (UniProt)
Isoform / epitope 0 isoforms listed; propeptide processing affects epitope choice (UniProt)
Section 1

Recommended COL1A2 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet: A00624-1) with four published COL1A2 IHC protocols (PMC13168407; PMC8043688; PMC6940971; PMC13173883).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded Rat lung tissue; fixative not specified (datasheet A00624-1)
FixationImage fixative and duration unreported (datasheet A00624-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6.0, 20min (datasheet A00624-1)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-COL1A2, 1:100-1:300 (datasheet A00624-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCOL1A2-positive staining in glandular cells of cervix (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 heat retrieval (datasheet: A00624-1). Tris-EDTA pH 9.0 microwave retrieval is a published alternative (PMC8043688).
Section 2

What Is the Expected COL1A2 Staining Pattern?

COL1A2 is secreted into the extracellular matrix and has no transmembrane segment (UniProt P08123 topology). In tissue IHC, HPA reports general cytoplasmic expression, with high staining in cervical glandular cells and placental trophoblastic cells (HPA tissue IHC: Approved). Because COL1A2 is secreted, the location of tissue RNA and protein can differ (HPA tissue IHC: reliability note).

What am I looking at on my slide?
Cytoplasmic staining in cervical glandular cells or placental trophoblastic cells, with possible extracellular staining.This fits the high cellular staining reported by HPA and the secreted, matrix location reported by UniProt; assess cellular and extracellular signal separately (HPA tissue IHC; UniProt P08123 subcellular location).
Predominantly nuclear staining or sharp staining confined to cell membranes.Neither is the expected location: HPA describes general cytoplasmic tissue staining, while UniProt places secreted COL1A2 in extracellular space and matrix and reports no transmembrane segment (HPA tissue IHC; UniProt P08123 topology). Check controls before calling this specific signal (standard IHC practice).
Strong signal in a cell population outside the documented tissue pattern.Do not assign that signal to COL1A2 from intensity alone. Compare with the reported cell types and staining levels; cross-reactivity or endogenous detection activity is possible (HPA tissue IHC; standard IHC practice).
Diffuse chromogen across many compartments, including areas without a clear cellular or matrix pattern.An indiscriminate deposit is difficult to interpret as COL1A2. Evaluate a no-primary control and review blocking, washing and detection conditions (standard IHC practice); HPA's tissue profile does not validate diffuse background as target staining (HPA tissue IHC).
No staining in cervical glandular cells or placental trophoblastic cells.These are reported high-staining examples (HPA tissue IHC). First check that the positive control and detection workflow worked; an absent signal in one section alone cannot establish absent COL1A2 (standard IHC practice).
💡Expected COL1A2 appearanceCall a result positive when defined cytoplasmic staining appears in the reported high-staining cervical glandular or placental trophoblastic cells, with extracellular matrix signal interpreted as compatible with secretion; isolated nuclear or indiscriminate chromogen is suspect (HPA tissue IHC; UniProt P08123 subcellular location; standard IHC practice).
How each factor affects the staining
Tissue and cell contextHPA reports high staining in cervical glandular and placental trophoblastic cells, but low staining in soft-tissue fibroblasts and smooth muscle cells; do not assume every collagen-producing-looking cell will be strongly positive (HPA tissue IHC).
Secretion and processingUniProt lists a signal peptide, propeptides and a mature collagen chain, and places COL1A2 in extracellular matrix (UniProt P08123 processing and subcellular location). The antibody epitope is unspecified here, so these records cannot identify which processed form contributes to a particular stain.
Antibody validationThe listed tissue-IHC antibody CAB032650 has an Approved IHC status; the supplied record does not label its IHC validation Enhanced (HPA antibodies). Interpret unusual compartments against controls rather than treating approval as proof that every deposit is specific (standard IHC practice).
IF/ICC: where should intracellular signal appear?HPA reports a supported, mainly endoplasmic-reticulum location in ICC-IF images (HPA subcellular ICC-IF). That cultured-cell finding complements the tissue-IHC cytoplasmic profile; it does not establish an IHC-P retrieval or IF/ICC protocol (HPA tissue IHC; HPA subcellular ICC-IF).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known high-staining cells are blank.The run or detection may have failed; HPA reports high staining in cervical glandular and placental trophoblastic cells (HPA tissue IHC; standard IHC practice).Review the positive control and reagent steps, then repeat with the validated IHC workflow if controls also fail (standard IHC practice).
Chromogen is widespread and obscures tissue detail.Nonspecific background or endogenous detection activity may contribute (standard IHC practice).Compare a no-primary control; review blocking, washes and detection settings before scoring the section (standard IHC practice).
Signal is mainly nuclear or sharply membrane-bound.That distribution conflicts with HPA's general cytoplasmic tissue profile and UniProt's secreted, non-transmembrane topology (HPA tissue IHC; UniProt P08123 topology).Check compartment assignment with the counterstain and compare controls; withhold a specific COL1A2 call if the pattern persists (standard IHC practice).
An unexpected cell population stains more strongly than the reported high-staining cells.Cross-reactivity or endogenous detection activity is possible; HPA's reported cell-specific levels do not support that pattern by themselves (HPA tissue IHC; standard IHC practice).Compare adjacent tissue features and controls, and confirm the result with an independent specificity check before assigning the cell population as positive (standard IHC practice).
Cytoplasmic signal is present, but extracellular matrix signal is hard to distinguish.HPA describes general cytoplasmic tissue staining, while UniProt places secreted COL1A2 in matrix; neither record guarantees visible matrix staining in each section (HPA tissue IHC; UniProt P08123 subcellular location).Score the observed cellular and extracellular compartments separately; do not require a visible matrix deposit to accept the reported cellular pattern (HPA tissue IHC; standard IHC practice).
A low-staining reference tissue looks blank.HPA lists low staining in soft-tissue fibroblasts and smooth muscle cells; a weak signal may be difficult to distinguish from background (HPA tissue IHC; standard IHC practice).Use a reported high-staining cell population to judge assay performance, then interpret the low-staining tissue against its controls (HPA tissue IHC; standard IHC practice).

Sample controls for COL1A2 IHC & IF

🧪Run cervix first and assess its glandular cells, which HPA scores High for COL1A2 (HPA: High in cervix glandular cells). HPA detects COL1A2 in all 44 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and expect cells without specific signal on the positive slide to remain at background even where adjacent extracellular matrix stains (HPA: detected in all 44 scored tissues; UniProt P08123: extracellular matrix).
Positive control tissue: Cervix (Glandular cells, HPA High)
Negative control tissue: None in HPA: COL1A2 is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show COL1A2 in ASC52telo, BJ [Human fibroblast], U2OS, with annotated localisation: Endoplasmic reticulum (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only section and an irrelevant IgG control matched to the primary antibody’s host species and isotype, or matched polyclonal IgG where appropriate (standard IHC practice). A COL1A2 knockout specimen, if available, or an immunizing-peptide block can test specificity; quench endogenous peroxidase for chromogenic detection (standard IHC practice).
⚠️Feasibility: The selected A00624-1 paraffin-section caption reports sodium citrate retrieval at pH 6.0, >98°C for 20 min, in rat lung; this supports a starting retrieval condition, but does not establish that retrieval is required in cervix (selected A00624-1 tissue-IHC caption). Its fixative is unreported, and no target-specific fixation window or fixation effect is reported in the supplied evidence (selected A00624-1 tissue-IHC caption). The evidence does not establish that frozen sections or IF are easier; extracellular matrix staining can complicate assignment of signal to individual glandular cells (UniProt P08123: extracellular matrix).

HPA tissue IHC evidence for COL1A2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Secreted protein, tissue location of RNA and protein is expected to differ.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cervix Glandular cells High Protein (IHC) HPA →
Placenta Trophoblastic cells High Protein (IHC) HPA →
Adipose tissue Adipocytes Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: COL1A2 is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced COL1A2 IHC Tips

Troubleshoot COL1A2 staining by separating extracellular matrix signal from intracellular signal and documenting the processing and detection conditions used.

What retrieval should I try when COL1A2 staining is weak in paraffin sections?
Start with heat-mediated retrieval in sodium citrate at pH 6.0 (datasheet A00624-1). The selected paraffin-section image used sodium citrate above 98°C for 20 minutes, followed by primary antibody at 1:200 overnight at 4°C (caption A00624-1). If signal remains weak, compare a shorter and a longer heating interval on adjacent sections while holding antibody dilution and detection constant (general IHC practice). Check whether increased staining follows plausible matrix structures or merely raises diffuse background; the caption does not report a fixative, so its retrieval result cannot establish fixation tolerance (caption A00624-1; UniProt P08123 localisation).
How should I investigate suspected fixation-related loss of COL1A2 staining?
Target-specific fixation sensitivity is unknown from the supplied evidence; the selected image identifies paraffin sections but does not state a fixative (caption A00624-1). Record the actual fixative, fixation duration, section age, and retrieval conditions for each specimen before comparing staining (general IHC practice). On matched sections, keep the documented pH 6.0 citrate retrieval and 1:200 primary dilution constant while assessing any processing differences (caption A00624-1; general IHC practice). Judge changes against tissue architecture and secondary-only controls, since stronger diffuse colour alone cannot demonstrate recovery of COL1A2 antigen (general IHC practice).
Should COL1A2 appear in extracellular matrix or inside cells?
Expect a substantial extracellular pattern because COL1A2 is secreted and assigned to the extracellular matrix, with no transmembrane segment (UniProt P08123 localisation and topology). Intracellular staining can also be plausible: tissue IHC reports general cytoplasmic expression, while subcellular IF places COL1A2 mainly in the endoplasmic reticulum (HPA tissue IHC; HPA subcellular). At 1:200 primary dilution, inspect matrix and cell-associated signal separately rather than combining them into one score (caption A00624-1; general IHC practice). Compare serial sections and morphology before calling isolated nuclear, luminal, or edge-restricted colour specific; these locations lack support in the supplied localisation records (UniProt P08123 localisation; HPA subcellular).
Could epitope location explain differences between cellular and matrix staining?
Map the antibody immunogen, if disclosed, against the precursor before interpreting discrepant patterns; its epitope is not supplied here (UniProt P08123 processing; supplied catalog evidence). COL1A2 has a 1,366-aa precursor, a mature chain spanning residues 80–1119, and propeptide regions at 23–79 and 1120–1366 (UniProt P08123 processing). An antibody recognizing a cleaved propeptide could show a different distribution from one recognizing the mature chain, so verify epitope information rather than assuming equivalence (UniProt P08123 processing; general IHC practice). The record lists 0 isoforms and reports glycosylation and hydroxylation, but those facts alone do not establish this antibody's epitope accessibility in paraffin sections (UniProt P08123 isoforms and modifications).
How can I check COL1A2 localisation by multiplex immunofluorescence?
Use a cell-type marker alongside COL1A2 to relate intracellular signal to glandular cells where tissue IHC reports high staining, and retain a separate channel for matrix signal (HPA tissue IHC; UniProt P08123 localisation). Choose fluorophores after inspecting unstained tissue for autofluorescence, and include single-stain controls when setting exposure and spectral separation (general IF practice). If the antibody epitope is intracellular, permeabilise to access the endoplasmic reticulum; for an accessible extracellular epitope, compare without permeabilisation to preserve spatial detail (HPA subcellular; UniProt P08123 topology; general IF practice). The IHC caption's 1:200 dilution and pH 6.0 retrieval describe paraffin-section IHC, not an established IF condition (caption A00624-1).
How do I distinguish COL1A2 staining from chromogenic background?
Run a secondary-only section beside each experimental condition; this control was included in the selected paraffin-section image (caption A00624-1). Apply an appropriate protein block, suppress endogenous peroxidase before peroxidase-based detection, and develop DAB for a controlled interval while watching the negative control (general IHC practice). If diffuse colour persists, compare shorter DAB development or a lower primary concentration against the documented 1:200 condition, changing one variable at a time (caption A00624-1; general IHC practice). Accept signal only when its distribution fits extracellular matrix or credible cell-associated staining and exceeds the matched control; COL1A2 is secreted, while HPA also reports cytoplasmic tissue staining (UniProt P08123 localisation; HPA tissue IHC).
What should I measure when COL1A2 stains both cells and matrix? ⚠ ANSWER MARKED FOR VERIFICATION
Define cellular and extracellular compartments before scoring because COL1A2 is assigned to the extracellular matrix and tissue IHC also reports cytoplasmic staining (UniProt P08123 localisation; HPA tissue IHC). For cells, record percent positive cells and an intensity-weighted H-score; for matrix, measure positive area or optical density per mm² of evaluable tissue (general IHC practice). Normalise cellular counts to the relevant cell population and matrix measurements to tissue area, excluding folds, empty spaces, and damaged regions by a prespecified rule (general IHC practice). Keep retrieval, 1:200 dilution, imaging settings, and DAB development consistent across compared sections, and report the compartments separately (caption A00624-1; general IHC practice).
What makes a positive COL1A2 IHC result convincing?
Look for reproducible extracellular staining consistent with a secreted matrix protein, while allowing cell-associated signal because HPA reports cytoplasmic tissue staining (UniProt P08123 localisation; HPA tissue IHC). Interpret cellular signal in its tissue context: HPA reports high staining in cervix glandular cells and placenta trophoblastic cells, but these observations do not validate every specimen or staining pattern (HPA tissue IHC). Reject colour confined to section edges, necrotic areas, or secondary-only controls, and investigate persistent colour after a peroxidase block as possible detection artefact (general IHC practice). Compare morphology and compartment-specific scoring on adjacent sections under the documented pH 6.0 retrieval and 1:200 primary condition before making a biological claim (caption A00624-1; general IHC practice).
Boster reagents

Best COL1A2 / Collagen alpha-2(I) chain IHC Antibodies

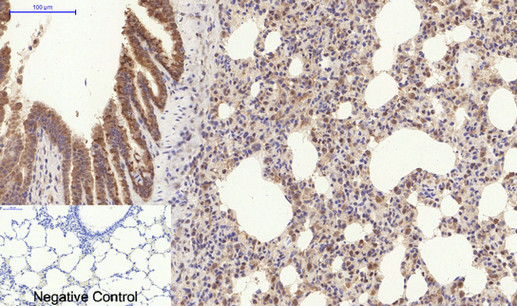
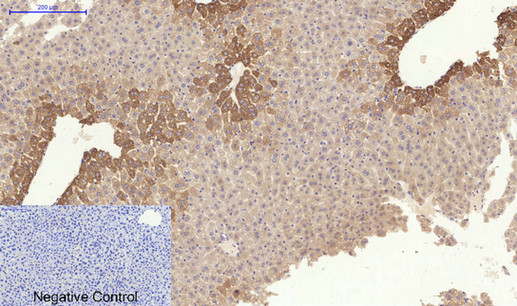
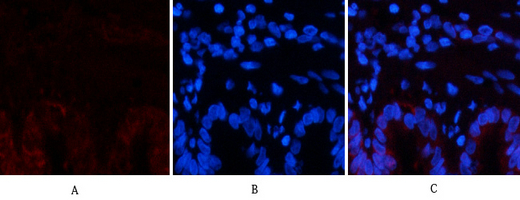
A00624-1 has IHC images from paraffin-embedded rat lung and mouse liver and IF images from rat lung and NIH/3T3 cells (catalog image captions). Human, mouse, and rat reactivity is listed (catalog: reactivity).

Real IHC data Immunohistochemical analysis of paraffin-embedded Rat-lung tissue. 1, COL1A2 Polyclonal Antibody was diluted at 1:200 (4°C, overnight). 2, Sodium citrate pH 6.0 was used for antibody retrieval (>98°C, 20min). 3, Secondary antibody was diluted at 1:200 (room tempeRature, 30min). Negative control was used by secondary antibody only.
Anti-Collagen alpha-2(I) chain COL1A2 Antibody
Cat # A00624-1

A00624-1 will render with its rat-lung paraffin-section IHC figure (card figure caption). Its catalog also shows mouse-liver IHC and rat-lung and NIH/3T3 IF images (catalog image captions).

Which to pick: Choose A00624-1 for tissue IHC: its polyclonal antibody has paraffin-section images from rat lung and mouse liver, with a listed IHC dilution of 1:100–1:300 (catalog: IHC captions, dilution). For IF/ICC, A00624-1 has rat-lung IF and an NIH/3T3 cell IF image, with a listed IF dilution of 1:200–1:1000 (catalog: IF captions, dilution). It is the cross-species option listed for human, mouse, and rat (catalog: reactivity); the IHC captions support paraffin sections but do not report the fixative (catalog: IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P08123 (CO1A2_HUMAN, Collagen alpha-2(I) chain).
  2. Human Protein Atlas. COL1A2 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. COL1A2 subcellular location (ICC-IF): Mainly localized to the endoplasmic reticulum..
  4. Human Protein Atlas. COL1A2 antibody validation summary (3 antibodies).
  5. Collagen type I alpha 2 acts as a potential diagnostic biomarker and therapeutic targets for the prognosis in gastric cancer. Discover oncology 2026 — PMC13168407.
  6. Expression of cornulin in tongue squamous cell carcinoma. Ecancermedicalscience 2021 — PMC8043688.
  7. A Novel Hepatic Anti-Fibrotic Strategy Utilizing the Secretome Released from Etanercept-Synthesizing Adipose-Derived Stem Cells. International journal of molecular sciences 2019 — PMC6940971.
  8. Microbiota-gut-muscle axis shapes fish muscle texture by regulating collagen synthesis. Microbiome 2026 — PMC13173883.
  9. PubMed PMID:2824475 — UniProt-cited evidence.
  10. PubMed PMID:9016532 — UniProt-cited evidence.
  11. PubMed PMID:9443882 — UniProt-cited evidence.