This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic IHC for CPAMD8 in paraffin sections using the catalog antibody’s documented conditions. Compare cytoplasmic and membranous staining with suitable controls, bearing in mind that tissue IHC evidence has uncertain reliability (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic and membranous tissue staining (HPA tissue IHC) | |
| Staining pattern | Glandular cells: cytoplasmic and membranous staining (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6 HIER, heat-mediated (datasheet A12898) | |
| Positive control | Adipose tissue+4 more · see all | |
| Negative control | Appendix+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet A12898); verify before use. | |
| Caveat | Secreted protein may appear away from RNA-positive cells (HPA tissue IHC) | |
| Regulation | Regulation unreported (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope overlap is unreported (UniProt) |
The catalog antibody uses citrate pH 6 retrieval (datasheet A12898); the published bovine ciliary body IHC protocol uses TE pH 9 retrieval (PMC5500361).
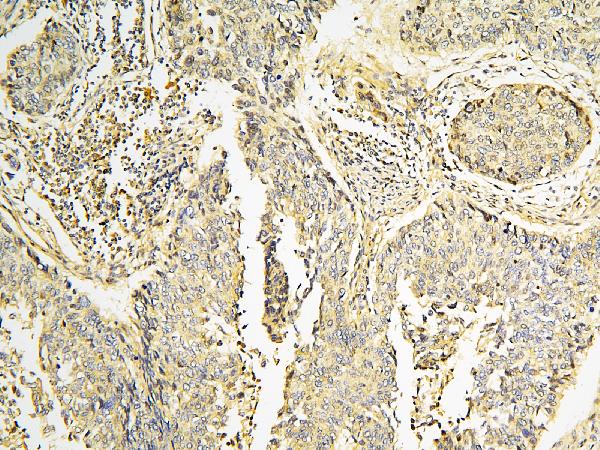
| Sample | Paraffin-embedded human lung cancer tissue; fixative not specified (datasheet A12898) |
| Fixation | Image fixative and duration unreported (datasheet A12898); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Citrate pH 6, 20 min (datasheet A12898) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A12898) |
| Primary antibody | Rabbit anti-CPAMD8, 0.5-1μg/ml (datasheet A12898) |
| Primary incubation | Overnight at 4 °C (datasheet A12898) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet A12898) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CPAMD8-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and membranous expression in several different tissue types. No signal in the no-primary control. |
CPAMD8 is annotated as secreted and cell membrane associated, with no transmembrane segment (UniProt Q8IZJ3 topology). In paraffin section IHC, expect cytoplasmic and membranous staining in selected cells, including adipocytes, glandular cells, respiratory epithelial cells, Purkinje cells and cardiomyocytes (HPA: tissue IHC). Treat the pattern as provisional: HPA rates tissue staining Uncertain because antibody staining and RNA expression have low consistency (HPA: tissue IHC reliability).
| Cytoplasmic and membranous staining in adipocytes, adrenal glandular cells or cardiomyocytes. | These are reported High staining examples (HPA: tissue IHC). Compare the signal with cell morphology and a negative control (standard IHC practice). The HPA reliability rating is Uncertain, so a matching pattern supports interpretation without establishing antibody specificity (HPA: tissue IHC reliability). |
| Strong nuclear staining dominates in cells expected to show cytoplasmic or membranous signal. | Dominant nuclear staining departs from the reported tissue pattern (HPA: tissue IHC). Check the negative control and review detection and counterstain before calling it CPAMD8 (standard IHC practice). UniProt lists secreted and cell membrane locations, with no transmembrane segment; it does not list a nuclear location (UniProt Q8IZJ3 topology). |
| Prominent staining in bone marrow hematopoietic cells or appendix glandular cells. | HPA reports CPAMD8 as Not detected in these cell populations (HPA: tissue IHC). If the negative control also stains, investigate endogenous detection activity; if it does not, consider antibody cross-reactivity (standard IHC practice). A single unexpected field needs replication and tissue review. |
| Diffuse chromogen obscures cell borders across both expected positive and negative areas. | The distribution cannot be scored reliably against HPA's cytoplasmic and membranous pattern (HPA: tissue IHC). Inspect the negative control and reagent background, then reassess antibody concentration, blocking and wash conditions (standard IHC practice). Diffuse staining alone does not establish extracellular CPAMD8. |
| No staining in a well-preserved adrenal gland or heart muscle section. | HPA reports High signal in adrenal glandular cells and cardiomyocytes (HPA: tissue IHC). Confirm tissue identity and control performance, then review retrieval, antibody dilution and detection steps (standard IHC practice). Because HPA tissue reliability is Uncertain, one absent signal is not definitive evidence of absent CPAMD8. |
| Secreted and cell membrane annotation | CPAMD8 has a signal peptide at residues 1–25 and no transmembrane segment (UniProt Q8IZJ3 topology). Its secreted annotation makes a strict membrane-only scoring rule unsuitable; evaluate any extracellular signal with morphology and controls rather than assuming its identity (standard IHC practice). |
| Tissue pattern and confidence | HPA describes cytoplasmic and membranous expression across several tissues, but rates tissue IHC Uncertain because staining and RNA data have low consistency (HPA: tissue IHC). Use the listed positive and undetected cell populations as comparisons, not absolute pass/fail standards. |
| Processing and isoforms | UniProt lists a mature chain at residues 26–1885 and 2 isoforms (UniProt Q8IZJ3 processing, isoforms). If an antibody's epitope is documented elsewhere, check whether it is retained in the form being assessed; this payload provides no antibody epitope location. |
| Antigen retrieval in paraffin IHC | Compare retrieval conditions against a positive tissue and matched controls when optimizing an assay (standard IHC practice). The supplied HPA and UniProt records report no CPAMD8-specific fixation sensitivity or retrieval requirement; do not attribute a changed signal to a documented CPAMD8 fixation effect. |
| Situation | Likely cause | Next action |
|---|---|---|
| Positive tissue has no interpretable chromogen. | Tissue identity, retrieval, dilution or detection may need review (standard IHC practice); HPA calls the tissue IHC pattern Uncertain. | Verify tissue and cell morphology, review a working assay control, and check retrieval and detection steps (standard IHC practice). Compare with an HPA High cell population, such as adrenal glandular cells (HPA: tissue IHC). |
| Negative control and test section both show broad color. | Shared signal suggests background from reagents or endogenous detection activity (standard IHC practice). | Review the negative control, endogenous-activity block, antibody concentration and washes; score CPAMD8 only after the shared background is resolved (standard IHC practice). |
| Nuclei stain more strongly than cell bodies or borders. | This conflicts with HPA's cytoplasmic and membranous tissue description (HPA: tissue IHC). | Review counterstain and detection controls, then repeat with an independently validated antibody if needed (standard IHC practice). HPA lists IHC validation as Uncertain for HPA031327, HPA031328 and HPA031330. |
| Unexpected cells stain while listed positive cells do not. | Possible cross-reactivity or assay background requires investigation (standard IHC practice); HPA tissue observations carry an Uncertain rating. | Compare cell morphology with HPA's cell-specific entries and inspect negative controls. Repeat the comparison before assigning the unexpected signal to CPAMD8 (HPA: tissue IHC; standard IHC practice). |
| A liver section appears inconsistent with the expected pattern. | UniProt reports lower liver tissue expression, while HPA reports cholangiocytes as Not detected; these describe different scopes (UniProt Q8IZJ3 tissue specificity; HPA: tissue IHC). | Identify the stained liver cell type before interpreting the result. Do not treat UniProt's tissue-level statement as a prediction that cholangiocytes must stain. |
| Q: Does focal adhesion signal in IF establish the expected IHC pattern? | HPA reports focal adhesion sites as an uncertain ICC-IF location, while its tissue IHC summary is cytoplasmic and membranous (HPA: subcellular; HPA: tissue IHC). | A: Interpret paraffin section IHC against the tissue IHC pattern and its Uncertain reliability rating. Assess ICC-IF localization in its separate guide; it does not establish an IHC protocol or compartment requirement (HPA: tissue IHC; HPA: subcellular). |
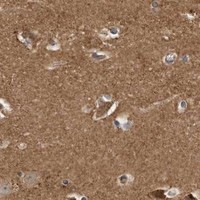


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data. At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | High | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Colon | Endothelial cells | Not detected | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot CPAMD8 staining in paraffin sections using the catalog antibody’s tissue IHC conditions, with separate considerations for IF/ICC.
The catalog antibody has IHC images from paraffin-embedded human lung and mammary cancer sections (catalog image captions). Human and monkey reactivity is listed; IF data are absent (catalog applications/reactivity; image captions).
A12898 has IHC images from paraffin-embedded human lung and mammary cancer sections (A12898 image captions). Its listed applications are ELISA, IHC and WB, with human and monkey reactivity; the captions document human tissue only (A12898 catalog; image captions).
Which to pick: Choose A12898 for paraffin-section IHC: its images document citrate retrieval at pH 6 for 20 minutes and primary antibody at 1 μg/ml (A12898 image captions). No IF/ICC application or image is listed, so there is no catalog-supported IF/ICC choice (A12898 catalog). Monkey reactivity is listed, but the IHC images show human tissue only; the fixative is unreported (A12898 catalog; image captions).