CRISP2 / Cysteine-rich secretory protein 2 · IHC design guide

Design Immunohistochemistry for CRISP2

Plan CRISP2 IHC-P in human testis with the catalog antibody starting at 10 μg/mL (datasheet: 10 μg/mL). Assess nuclear staining in elongated or late spermatids and watch for presumed off-target staining (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CRISP2 (IHC for CRISP2): expected localisation Nuclear in testis (HPA tissue IHC), antibody A10681, validated IHC image, and IHC protocol steps
Printable CRISP2 IHC protocol sheet — expected localisation Nuclear in testis (HPA tissue IHC), antibody A10681, controls and protocol steps. Open the full CRISP2 IHC guide →

CRISP2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear in testis (HPA tissue IHC)
Staining pattern Nuclear staining in elongated or late spermatids (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Testis
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A10681)
Caveat Presumed off-target staining may confound interpretation (HPA tissue IHC)
Regulation Testis-enriched RNA expression (HPA tissue RNA)
Isoform / epitope 2 isoforms; mature chain 22–243; epitope unknown (UniProt)
Section 1

Recommended CRISP2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by one published CRISP2 protocol for adult boar testis (PMC8119884).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A10681); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CRISP2, 10 μg/mL (datasheet A10681)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCRISP2-positive staining in elongated or late spermatids of testis (HPA tissue IHC: High). HPA tissue profile: Selective nuclear expression in testis. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page retrieval); the published boar testis protocol also uses citrate pH 6.0 (PMC8119884).
Section 2

What Is the Expected CRISP2 Staining Pattern?

CRISP2 staining is expected in the nuclei of elongated or late spermatids in testis (HPA: selective nuclear expression; High in elongated or late spermatids). HPA rates the tissue IHC pattern Enhanced, while noting medium agreement with RNA data and disregarded presumed off-target staining (HPA: reliability description). CRISP2 is secreted and has no transmembrane segment (UniProt P16562: subcellular location and topology); those annotations do not resolve the observed nuclear pattern.

What am I looking at on my slide?
Strong nuclear stain in elongated or late spermatids, with little stain elsewhere in the section.This matches the reported positive cell type, intensity and compartment (HPA: High in elongated or late spermatids; selective nuclear expression). Identify the cells on the counterstained section before scoring: a strong signal alone does not establish that it is in the expected spermatids (general IHC practice).
Predominantly cytoplasmic or membrane-like stain in testis, without the expected nuclear pattern.The observed compartment does not match the tissue IHC profile (HPA: selective nuclear expression). Review morphology, distribution and controls before assigning it to CRISP2. Secreted status and absence of a transmembrane segment do not, by themselves, explain an alternative staining compartment (UniProt P16562: location and topology).
Prominent stain in other testicular cells, or in a reported negative cell type.Question specificity if the expected late-spermatid nuclear signal is absent or outweighed (HPA: selective nuclear expression; presumed off-target binding disregarded). For example, adrenal glandular cells and adipocytes in adipose tissue were not detected in the supplied HPA tissue IHC record (HPA: Not detected). Check controls before calling such staining CRISP2.
Weak, widespread colour obscures cell boundaries or the nuclear pattern.Treat diffuse colour as background until controls and tissue morphology support a specific call (general IHC practice). The expected result is selective nuclear staining, so diffuse colour cannot establish the reported pattern (HPA: selective nuclear expression). Examine the no-primary control and detection background, then reassess the positive cells (general IHC practice).
No visible stain in a testis section expected to be positive.First confirm that elongated or late spermatids are present in the section; they are the reported high-staining cells (HPA: High in elongated or late spermatids). If present, review the positive control and IHC detection workflow before concluding that CRISP2 is absent (general IHC practice). A negative result in an unsuitable section cannot test the reported pattern.
💡Expected CRISP2 appearanceCall the section positive when elongated or late spermatid nuclei show strong, selective staining (HPA: High; selective nuclear expression); predominant diffuse, cytoplasmic or unrelated-cell staining is discordant with that profile (HPA: tissue IHC profile).
How each factor affects the staining
Tissue and cell selectionTestis is the reported enriched tissue, and elongated or late spermatids are the high-staining cells (HPA: tissue-enriched RNA; High IHC staining). UniProt also lists testis and epididymis as tissue-specific sites (UniProt P16562: tissue specificity). This record gives no epididymal IHC pattern, so use the documented testis pattern for interpretation.
Compartment and secretionHPA describes selective nuclear expression in testis, while both sources describe CRISP2 as secreted (HPA: tissue IHC profile and subcellular summary; UniProt P16562: secreted). HPA cautions that RNA and protein tissue locations may differ for secreted proteins (HPA: reliability description). Neither annotation establishes a distinct extracellular IHC pattern here.
Processing and antibody epitopeThe recorded precursor has a signal peptide at residues 1–21 and a chain at residues 22–243 (UniProt P16562: processing). The antibody epitope is not supplied, so these positions cannot predict which form the stain detects or whether a particular retrieval condition changes its signal. Assess retrieval with routine IHC controls (general IHC practice).
Isoforms and validation scopeTwo isoforms are listed (UniProt P16562: isoforms 1 and 2), but no isoform-specific staining is supplied. Antibody HPA031248 has Enhanced IHC status (HPA: antibody IHC validation). HPA also reports medium staining-to-RNA consistency and disregarded presumed off-target binding (HPA: reliability description); interpret discordant cells with that caveat.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Testis is blank despite visible elongated or late spermatids.The high-staining cells are present, so the result conflicts with the reported pattern (HPA: High in elongated or late spermatids).Check a positive-control section, antibody and detection steps, and the counterstain used to identify the cells (general IHC practice). Record the result as unresolved if the controls fail.
The expected nuclei stain, but the whole section also looks brown.Background may be obscuring the selective nuclear pattern (HPA: selective nuclear expression; general IHC practice).Compare with a no-primary control and inspect blocking, washes and chromogenic detection conditions (general IHC practice). Score the target cells only where cell boundaries and nuclei remain interpretable.
Colour appears in cells reported as negative by HPA.Such staining conflicts with the supplied negative-cell observations and may reflect nonspecific binding or detection activity (HPA: Not detected in listed cells; general IHC practice).Compare tissue morphology and no-primary controls; do not assign CRISP2 solely from colour in those cells (general IHC practice).
Staining is mainly cytoplasmic or at cell edges in testis.That distribution differs from HPA's selective nuclear IHC profile (HPA: tissue IHC profile).Recheck spermatid identification and the positive-control pattern; report the discordant compartment rather than converting it into the expected nuclear call (general IHC practice).
A testis section lacks the reported positive spermatids.The section cannot show staining in elongated or late spermatids if those cells are absent (HPA: positive cell type).Select a section containing identifiable elongated or late spermatids, then assess nuclear staining with the same control workflow (general IHC practice).
Can an IF/ICC signal be judged against this IHC pattern?HPA lists CRISP2 as secreted but provides no main ICC-IF location or cell-line images in the supplied record (HPA: subcellular summary).Use the separate IF/ICC guide for that application. Do not treat the testis chromogenic IHC pattern as an independently validated IF/ICC localisation (HPA: tissue IHC and subcellular records).

Sample controls for CRISP2 IHC & IF

🧪Run human testis first and look for staining in elongated or late spermatids (HPA: High in elongated or late spermatids). Run adipose tissue as a negative comparison (HPA: Not detected in adipocytes); on the testis slide, use cells outside the elongated or late spermatid compartment to assess background, without assuming they are validated negatives.
Positive control tissue: Testis (Elongated or late spermatids, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for CRISP2; derive a cell-line control from the positive tissue's cell type (Elongated or late spermatids) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control; an isotype control matched to the primary antibody’s host species and clonality; and, if available, CRISP2 knockout tissue or an immunizing-peptide block as a biological specificity control. Block endogenous peroxidase for chromogenic IHC, and check for endogenous biotin if using avidin–biotin detection (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect and a retrieval dependency are unreported in the supplied evidence; optimize antigen retrieval empirically, and note that the selected testis IHC caption does not report a fixative (caption: A10681, human testis, 10 μg/mL). The evidence does not establish whether frozen sections or IF/ICC are easier; no ICC-IF cell-line images are listed (HPA: no cell lines with ICC-IF images). Dense spermatid staining may complicate cell-level scoring, so use morphology and counterstain to distinguish signal from background (HPA: High in elongated or late spermatids).

HPA tissue IHC evidence for CRISP2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Secreted protein, tissue location of RNA and protein is expected to differ. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Testis Elongated or late spermatids High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced CRISP2 IHC Tips

Use testis spermatid staining as the reference pattern while evaluating chromogenic CRISP2 IHC (HPA tissue IHC).

How should I retrieve CRISP2 in paraffin sections when spermatid staining is weak?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 minutes (page retrieval specification). Cool sections consistently, then compare staining in elongated or late spermatids with a no-primary control; these are the high-staining cells in testis (HPA tissue IHC). The product image reports human testis staining at 10 µg/mL, but its caption does not report fixation or retrieval conditions (A10681 tissue-IHC caption). If signal remains weak, compare a second retrieval condition on adjacent sections while holding antibody concentration and detection constant (standard IHC practice). Avoid interpreting stronger staining alone as improved specificity, because presumed off-target binding was observed in the tissue survey (HPA tissue IHC).
Could fixation explain inconsistent CRISP2 staining between testis sections?
CRISP2-specific sensitivity to fixative type or fixation time is unknown from the supplied evidence (A10681 tissue-IHC caption). The human testis image reports antibody use at 10 µg/mL but does not state its fixative, so it cannot establish a preferred fixation schedule (A10681 tissue-IHC caption). For paraffin IHC, record the fixative, time before fixation, fixation duration and processing history for each specimen before comparing signal (standard IHC practice). Test adjacent sections with the same citrate pH 6.0, 95–98 °C, 20-minute retrieval and detection run (page retrieval specification). Compare elongated or late spermatids and matched negative controls across runs; the tissue staining pattern alone does not identify a fixation effect (HPA tissue IHC; standard IHC practice).
Which CRISP2 staining compartment should count as plausible in testis?
The reported tissue IHC pattern is selective nuclear staining in testis, with high signal in elongated or late spermatids (HPA tissue IHC). CRISP2 is also annotated as secreted, with a 1–21 signal peptide and no transmembrane segment, so assess staining against cell morphology rather than assuming a membrane outline is expected (UniProt P16562). Record nuclear, cytoplasmic and extracellular signal separately on chromogenic sections (standard IHC practice). If a new protocol mainly stains unrelated cells or section edges, compare it with no-primary and matched control sections before scoring (standard IHC practice). Interpret any compartment difference cautiously because secreted proteins can have different RNA and protein tissue locations, and presumed off-target staining was disregarded in the tissue survey (HPA tissue IHC).
How can epitope uncertainty affect CRISP2 IHC interpretation?
CRISP2 has 2 annotated isoforms, but the supplied product caption does not identify the antibody epitope or establish isoform selectivity (UniProt P16562; A10681 tissue-IHC caption). The precursor has a 1–21 signal peptide, and the annotated mature chain spans residues 22–243 (UniProt P16562). Its SCP region spans 41–169 and its ShKT region 205–238; do not infer which region this antibody detects without epitope documentation (UniProt P16562; A10681 tissue-IHC caption). Compare staining after one controlled retrieval change at a time, using elongated or late spermatids as the expected positive population (page retrieval specification; HPA tissue IHC). A changed staining pattern cannot, by itself, demonstrate isoform-specific detection or epitope loss (standard IHC interpretation).
How should I check CRISP2 by IF alongside the chromogenic IHC result?
For the separate IF/ICC workflow, pair CRISP2 with a validated marker identifying elongated or late spermatids, the high-staining population reported by tissue IHC (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores and place the weaker signal in a channel with low testis autofluorescence, verified using unstained and single-stain controls (standard IF practice). CRISP2 is secreted and has no transmembrane segment, while the antibody epitope is unspecified (UniProt P16562; A10681 tissue-IHC caption). If testing an intracellular epitope, compare mild permeabilisation with an unpermeabilised condition; an accessible extracellular epitope may not require permeabilisation (standard IF practice). No supplied IF/ICC image establishes this antibody’s fixation, permeabilisation or multiplex performance (HPA subcellular record; A10681 tissue-IHC caption).
What should I change when CRISP2 IHC stains broadly?
First inspect no-primary controls and tissue morphology to separate detection background from staining in elongated or late spermatids (standard IHC practice; HPA tissue IHC). Block endogenous peroxidase before chromogenic detection, then use appropriate protein blocking and controlled wash times; these are general IHC steps rather than CRISP2-specific validation (standard IHC practice). Titrate antibody around the image-caption concentration of 10 µg/mL on comparable sections, keeping retrieval and DAB development constant (A10681 tissue-IHC caption; standard IHC practice). Adipocytes in adipose tissue and glandular cells in adrenal gland were reported as not detected and can inform control selection when those specimens are available (HPA tissue IHC). Broad staining warrants scrutiny because the tissue survey noted presumed off-target binding (HPA tissue IHC).
How should I score CRISP2 positivity across testis sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define elongated or late spermatids as the primary scoring population because they had high staining in the tissue survey (HPA tissue IHC). Record the percentage of positive cells and staining intensity, or calculate an H-score using consistent intensity categories and thresholds across sections (standard IHC practice). Normalise positive counts to the number of eligible spermatids assessed, or report positive-cell density per mm² of evaluable testis area when cell counting is impractical (standard IHC practice). Score nuclear and other compartment signals separately because the reported IHC pattern is selective nuclear expression despite CRISP2’s secreted annotation (HPA tissue IHC; UniProt P16562). Exclude damaged tissue and section edges by prespecified criteria, and include matched controls in each staining run (standard IHC practice).
When should apparent CRISP2 positivity be treated as artefact?
A convincing result should reproduce high staining in elongated or late spermatids and the reported selective nuclear testis pattern under controlled conditions (HPA tissue IHC; standard IHC practice). Flag dominant staining in unrelated cells or an unexpected compartment for follow-up; CRISP2 is annotated as secreted, so localisation alone cannot settle specificity (HPA tissue IHC; UniProt P16562). Check whether signal concentrates at section edges, folds or necrotic areas, where chromogenic artefacts can occur (standard IHC practice). If a no-primary control develops DAB, investigate endogenous peroxidase activity and detection reagents before attributing signal to CRISP2 (standard IHC practice). Use particular caution with isolated unexpected staining because presumed off-target binding was observed and disregarded in the tissue survey (HPA tissue IHC).
Boster reagents

Best CRISP2 / Cysteine-rich secretory protein 2 IHC Antibodies

A10681 is listed for human IHC-P and IF, with IHC and IF images of human testis tissue (catalog: applications, reactivity, image captions).

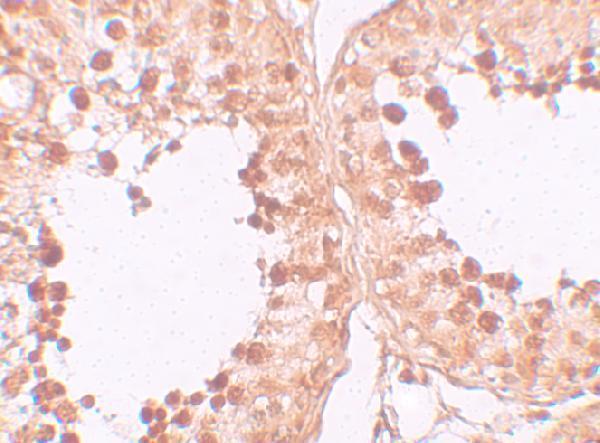
Real IHC data Immunohistochemistry of CRISP2 in human testis tissue with CRISP2 antibody at 10 μg/mL.
Anti-CRISP2 Antibody
Cat # A10681

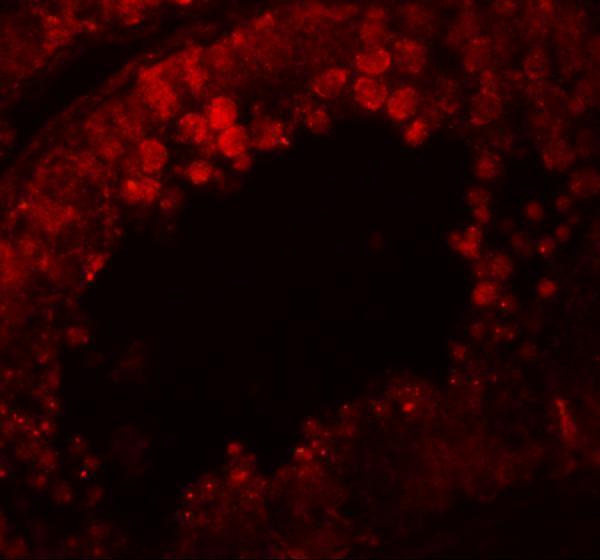
A10681 is listed for human IHC-P and IF (catalog: applications, reactivity). Its IHC caption shows human testis at 10 μg/mL, and its IF caption describes human testis at 20 μg/mL (catalog: A10681 image captions).

Which to pick: Choose A10681 for human tissue IHC-P: its own IHC caption shows human testis staining at 10 μg/mL; the fixative is unreported (catalog: A10681 applications, IHC caption). For IF, choose A10681 based on its listed IF application and human testis IF caption; ICC validation is unreported (catalog: A10681 applications, IF caption). No cross-species choice is supported because A10681 lists Human only; its clonality is unreported (catalog: A10681 reactivity, clone).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P16562 (CRIS2_HUMAN, Cysteine-rich secretory protein 2).
  2. Human Protein Atlas. CRISP2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. CRISP2 subcellular location (ICC-IF): Secreted.
  4. Human Protein Atlas. CRISP2 antibody validation summary (1 antibodies).
  5. Investigation Into the Relationship Between Sperm Cysteine-Rich Secretory Protein 2 (CRISP2) and Sperm Fertilizing Ability and Fertility of Boars. Frontiers in veterinary science 2021 — PMC8119884.
  6. Discovery and validation of novel biomarkers for detection of cervical cancer. Cancer medicine 2021 — PMC7957177.
  7. PubMed PMID:2613236 — UniProt-cited evidence.
  8. PubMed PMID:8665901 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.