CYP2C19 / Cytochrome P450 2C19 · IHC design guide

Design Immunohistochemistry for CYP2C19

Plan chromogenic paraffin IHC using hepatocytes as a high-staining reference and duodenal glandular cells as a medium-staining reference (HPA tissue IHC). This guide covers fixation, antibody titration, controls, and interpretation of cytoplasmic staining, including the reported cross-gene detection caveat (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CYP2C19 (IHC for CYP2C19): expected localisation Cytoplasmic staining (HPA tissue IHC); ER membrane (UniProt), antibody A02102-2, validated IHC image, and IHC protocol steps
Printable CYP2C19 IHC protocol sheet — expected localisation Cytoplasmic staining (HPA tissue IHC); ER membrane (UniProt), antibody A02102-2, controls and protocol steps. Open the full CYP2C19 IHC guide →

CYP2C19 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining (HPA tissue IHC); ER membrane (UniProt)
Staining pattern High in hepatocytes; medium in duodenal glandular cells; cytoplasmic (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A02102-2)
Positive control ⓘ Liver+1 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Antibody may detect proteins from more than one gene (HPA tissue IHC)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope No isoforms; one 1–490 chain; epitope side unannotated (UniProt)
Section 1

Recommended CYP2C19 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A02102-2) is accompanied by a published rat liver paraffin-section workflow (PMC12840301).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded rat liver tissues; fixative not specified (datasheet A02102-2)
FixationImage fixative and duration unreported (datasheet A02102-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A02102-2)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02102-2)
Primary antibodyRabbit anti-CYP2C19, 1μg/ml (datasheet A02102-2)
Primary incubationOvernight at 4 °C (datasheet A02102-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A02102-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
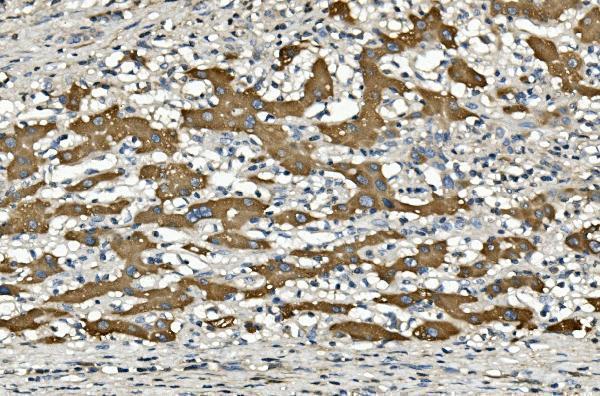
Expected resultCYP2C19-positive staining in hepatocytes of liver (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in liver and small intestines. No signal in the no-primary control.
💡Decision noteStart with heat-mediated citrate pH 6 retrieval for the catalog antibody (datasheet A02102-2); the published workflow does not specify retrieval (PMC12840301).
Section 2

What Is the Expected CYP2C19 Staining Pattern?

CYP2C19 is associated with the endoplasmic reticulum and microsome membranes, with no transmembrane segment annotated (UniProt P33261 topology). In paraffin-section IHC, expect cytoplasmic staining chiefly in hepatocytes, with weaker staining in duodenal glandular cells (HPA: High in hepatocytes; Medium in duodenal glandular cells). HPA rates the tissue pattern Supported but reports medium agreement with RNA data and cautions that the staining antibodies can target proteins from more than one gene (HPA tissue IHC).

What am I looking at on my slide?
Strong cytoplasmic signal in hepatocytes, with a weaker duodenal glandular-cell signal.This matches the reported tissue pattern (HPA: High in hepatocytes; Medium in duodenal glandular cells). The membrane association supports an intracellular pattern, but routine chromogenic IHC does not by itself resolve the endoplasmic reticulum (UniProt P33261 subcellular location).
Predominantly nuclear staining, or a crisp cell-surface rim where cytoplasmic signal is absent.These compartments conflict with the reported cytoplasmic tissue stain and endoplasmic reticulum or microsome association (HPA tissue IHC; UniProt P33261 subcellular location). Treat the result as suspect and assess staining specificity and section-level artefact before assigning it to CYP2C19.
Strong staining in a cell population reported as undetected, such as adipocytes.HPA reports no detection in adipocytes (HPA: Not detected in adipocytes). Unexpected signal could reflect antibody cross-reactivity or endogenous chromogenic detection activity; it cannot establish CYP2C19 expression on its own. HPA also cautions that its staining antibodies target proteins from more than one gene (HPA tissue IHC).
Uniform color across cells and surrounding section, with little cell-type contrast.A diffuse deposit lacks the hepatocyte-enriched distribution reported by HPA (HPA: High in hepatocytes). As a general IHC interpretation, consider nonspecific antibody binding, incomplete blocking, endogenous detection activity, or inadequate washing; compare the staining run with its negative detection control.
No detectable hepatocyte staining in a liver section.This conflicts with the reported high hepatocyte staining (HPA: High in hepatocytes). As general IHC troubleshooting, check tissue preservation, retrieval, antibody and detection steps, and the counterstained section. A failed run should not be scored as biological absence without a working positive control.
💡Expected CYP2C19 appearanceCall a convincing positive strong cytoplasmic hepatocyte stain, with possible medium duodenal glandular-cell staining (HPA tissue IHC); isolated nuclear, surface-rim, or uniform background color is suspect against the reported localization (HPA tissue IHC; UniProt P33261 subcellular location).
How each factor affects the staining
Compartment and apparent textureUniProt places CYP2C19 at endoplasmic reticulum and microsome membranes and annotates no transmembrane segment (UniProt P33261 topology). HPA describes cytoplasmic tissue staining (HPA tissue IHC). Score the broad compartment in chromogenic sections; do not claim organelle-level resolution from that pattern alone.
Tissue and cell selectionLiver hepatocytes offer the strongest reported positive comparison; duodenal glandular cells are medium, while adipocytes are reported undetected (HPA tissue IHC). Lower staining in stomach glandular cells, enterocytes of small intestine or colon, and gallbladder glandular cells may be less decisive (HPA tissue IHC).
Antibody evidence and specificityHPA lists IHC support for HPA015066; HPA074424 has ICC support, with no IHC status listed (HPA antibodies). Tissue staining has Supported reliability with medium RNA agreement, and HPA cautions that antibodies target proteins from more than one gene (HPA tissue IHC). Interpret unexpected positives conservatively.
Antigen retrievalNo target-specific fixation or retrieval effect is supplied (UniProt P33261; HPA tissue IHC). Retrieval optimization is a general paraffin-section IHC workflow decision. Evaluate any chosen condition against a positive liver section and detection controls; do not infer a CYP2C19-specific sensitivity change from these sources.
ICC-IF evidence boundaryHPA describes mainly vesicular ICC-IF localization as uncertain and cautions that the antibodies can target proteins from multiple genes (HPA subcellular ICC-IF). That observation does not replace the cytoplasmic liver and duodenal pattern reported for tissue IHC (HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Liver positive control is blank or much weaker than expected.A missed antibody or detection step, unsuitable retrieval, or a poorly preserved section may impair an IHC run; HPA provides no CYP2C19-specific fixation-effect evidence (HPA tissue IHC).Repeat with a liver section and check the staining sequence, reagent activity, retrieval condition, and counterstain. Use the reported high hepatocyte signal as the comparison (HPA: High in hepatocytes).
Color is diffuse across the section or appears in the negative detection control.General chromogenic IHC causes include endogenous enzyme activity, nonspecific binding, or insufficient washing. Diffuse color lacks the cell-selective pattern reported for CYP2C19 (HPA tissue IHC).Review the detection control, apply the appropriate endogenous-activity block for the detection system, and optimize blocking and washes. Reassess whether hepatocytes stand out from background (HPA: High in hepatocytes).
Nuclei or cell surfaces dominate while cytoplasm remains unstained.That distribution disagrees with cytoplasmic tissue staining and the endoplasmic reticulum or microsome location (HPA tissue IHC; UniProt P33261 subcellular location).Inspect morphology and control sections, then review antibody and detection conditions. Withhold a positive CYP2C19 call until a reproducible cytoplasmic pattern appears in reported positive cells (HPA tissue IHC).
Strong staining appears in adipocytes or another HPA-undetected cell population.Cross-reactivity or endogenous detection activity is possible. HPA reports adipocytes as undetected and warns that its staining antibodies can target proteins from more than one gene (HPA tissue IHC).Compare with the detection control and hepatocyte positive control, then review antibody specificity before interpreting the new cell population as CYP2C19-positive (HPA: High in hepatocytes; Not detected in adipocytes).
Duodenal staining is weaker than liver staining.This difference can match the reported pattern: duodenal glandular cells are Medium and hepatocytes are High (HPA tissue IHC).Compare the correct cell types on well-preserved sections and score each against its reported level (HPA tissue IHC). Investigate a complete loss of liver signal as a run issue before treating weaker duodenal staining as failure.
Can this tissue IHC result serve as an ICC-IF localization guide?HPA reports uncertain, mainly vesicular ICC-IF localization with a multiple-gene antibody caution; its tissue IHC report describes cytoplasmic staining in liver and small intestine (HPA subcellular ICC-IF; HPA tissue IHC).Use the separate IF/ICC guide for that application. Treat vesicular fluorescence as uncertain and assess antibody specificity there; use hepatocyte cytoplasmic staining to judge this paraffin-section IHC result (HPA tissue IHC).

Sample controls for CYP2C19 IHC & IF

🧪Run liver first: hepatocytes should show strong CYP2C19 staining (HPA: High in hepatocytes). Run adipose tissue as a negative, assessing adipocytes for absent staining (HPA: Not detected in adipocytes); on the liver slide, nonhepatocyte cells should lack the strong hepatocyte pattern and serve as an internal background reference (HPA: High in hepatocytes).
Positive control tissue: Liver (Hepatocytes, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CYP2C19 in OE19, SiHa, U2OS, with annotated localisation: Vesicles (uncertain) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a host-matched rabbit IgG isotype control appropriate to the primary antibody’s clonality (selected SKU caption: rabbit primary antibody); use CYP2C19 knockout material as a biological negative control (standard IHC practice). In liver sections, block endogenous peroxidase and check for endogenous biotin when using the caption’s biotin-based detection with DAB (selected SKU caption: biotinylated secondary, SABC and DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact selected-SKU paraffin-section caption does not state a fixative (selected SKU caption: fixative not stated). The demonstrated IHC workflow uses citrate retrieval at pH 6 for 20 minutes; whether CYP2C19 staining depends on that retrieval condition is unreported (selected SKU caption: heat-mediated antigen retrieval). Frozen sections and IF cannot be judged easier from the supplied evidence; the liver IHC workflow calls for attention to endogenous peroxidase and biotin background (selected SKU caption: SABC and DAB; standard IHC practice).

HPA tissue IHC evidence for CYP2C19

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Liver Hepatocytes High Protein (IHC) HPA →
Duodenum Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Endocrine cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced CYP2C19 IHC Tips

Troubleshoot CYP2C19 staining by checking retrieval, cell identity and compartment before comparing signal intensity across paraffin sections.

How should I optimize retrieval when CYP2C19 staining is weak?
Start with heat-mediated retrieval in citrate buffer at pH 6 for 20 minutes (datasheet A02102-2). The selected paraffin-section image used 1 μg/mL primary antibody overnight at 4°C, so keep antibody incubation consistent while assessing retrieval (datasheet A02102-2). Compare a retrieval time series on adjacent sections, recording tissue integrity and background alongside staining intensity (standard IHC practice). If staining remains weak, test another retrieval buffer or pH as a fallback, with the citrate condition retained as the reference (standard IHC practice). Judge improvement by the expected cytoplasmic staining in hepatocytes, while recognizing that the HPA tissue antibody may detect proteins from multiple genes (HPA: high in hepatocytes; HPA: Supported, multi-gene caution).
Could fixation explain weak or uneven CYP2C19 staining?
The selected CYP2C19 image documents a paraffin section but does not state its fixative, so target-specific fixation sensitivity is unknown (datasheet A02102-2). Record the fixative, duration and processing history for each specimen before comparing staining results (standard IHC practice). On adjacent sections from the same block, check whether retrieval changes signal without damaging morphology, and keep section thickness and detection conditions consistent (standard IHC practice). If staining varies across a batch, examine fixation and processing records alongside section age and reagent performance; none of these checks establishes a CYP2C19-specific fixation effect (standard IHC practice). Use hepatocyte morphology and matched controls to distinguish lost antigen accessibility from poor tissue preservation (HPA: high in hepatocytes; standard IHC practice).
What staining pattern should count as CYP2C19 in tissue sections?
Expect a predominantly cytoplasmic pattern compatible with endoplasmic reticulum and microsomal localization, rather than using nuclear staining as the positive readout (UniProt P33261: endoplasmic reticulum and microsome membranes; HPA: cytoplasmic expression). Assess that pattern within identified hepatocytes, where HPA reports high staining, and compare it with glandular cells in duodenum, where staining is medium (HPA: high in hepatocytes; HPA: medium in duodenal glandular cells). The record annotates no transmembrane segment, so it does not establish an antibody epitope's membrane orientation or a sharp plasma-membrane outline (UniProt P33261 topology). HPA's vesicular IF localization is uncertain and carries a multi-gene antibody caution (HPA subcellular: vesicles, uncertain; multi-gene caution). Recheck diffuse or nuclear DAB against morphology and controls before scoring it (standard IHC practice).
How can I assess whether the antibody detects CYP2C19 specifically?
The supplied record annotates no isoforms, domains, glycosylation sites or modified residues for CYP2C19 (UniProt P33261 record). Those annotations do not identify the catalog antibody's epitope or demonstrate discrimination from related proteins, so review its immunogen and validation data before making that claim (UniProt P33261 record; standard antibody-validation practice). Interpret tissue staining with particular caution because HPA rates its IHC evidence Supported but warns that its antibody targets proteins from more than one gene (HPA: Supported, multi-gene caution). Include a primary-antibody omission control for detection background and, where available, an independently validated antibody or specific biological control for identity (standard IHC practice). Agreement in cell type and cytoplasmic pattern supports interpretation but cannot alone prove molecular specificity (HPA: high in hepatocytes, cytoplasmic expression; standard IHC practice).
How should I compare multiplex IF with chromogenic CYP2C19 IHC?
Keep chromogenic paraffin-section IHC as the reference application: the selected image used citrate retrieval at pH 6 for 20 minutes and DAB detection (datasheet A02102-2). For a separate multiplex IF assessment, pair CYP2C19 with an independently validated hepatocyte marker and inspect single channels before interpreting overlap (HPA: high in hepatocytes; standard IF practice). Choose fluorophores after measuring tissue autofluorescence, assigning the cleaner detection channel to the weaker signal when practical (standard IF practice). Because the antibody epitope and its side of the ER membrane are unspecified, optimize permeabilisation empirically and avoid inferring epitope access from the absence of an annotated transmembrane segment (UniProt P33261 topology; standard IF practice). Treat HPA's uncertain vesicular IF result cautiously because its antibodies may target multiple genes (HPA subcellular: uncertain, multi-gene caution).
What should I check when CYP2C19 DAB staining is widespread?
First compare the stained section with a primary-antibody omission control to identify signal from detection reagents or endogenous tissue activity (standard IHC practice). The selected image used biotinylated secondary antibody, streptavidin-biotin detection and DAB, making matched detection-only controls relevant to that workflow (datasheet A02102-2). Apply an endogenous peroxidase block and assess whether the chosen detection system adds background before raising the threshold for a positive cell (standard chromogenic IHC practice). If background persists, titrate primary antibody below the image's 1 μg/mL condition and adjust blocking and washes systematically (datasheet A02102-2; standard IHC practice). Evaluate residual signal against hepatocyte morphology and the expected cytoplasmic distribution, with HPA's multi-gene caution in mind (HPA: high in hepatocytes, cytoplasmic expression; HPA: multi-gene caution).
How should I quantify CYP2C19 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and scoring rule before review; for hepatocytes, report the percentage of cytoplasmically positive cells or an H-score combining intensity and percentage (HPA: high in hepatocytes, cytoplasmic expression; standard IHC practice). If counting discrete positive cells, report density per mm² of evaluable tissue and the area sampled (standard IHC practice). Normalize comparisons to the same cell population, viable tissue area, section thickness, staining run and exposure or scan settings (standard IHC practice). Exclude folds, edges and necrotic regions using a prespecified rule, and subtract or flag signal seen in detection controls (standard IHC practice). Report compartment-specific scores because a nuclear or surface signal does not match the expected ER-associated cytoplasmic pattern (UniProt P33261: ER and microsome membranes; HPA: cytoplasmic expression).
When is a CYP2C19-positive section likely to be misleading?
A convincing positive result has cytoplasmic staining in morphologically identified hepatocytes and agrees with an adequately controlled detection run (HPA: high in hepatocytes, cytoplasmic expression; standard IHC practice). Strong nuclear or crisp cell-surface staining warrants review because the supplied localization places CYP2C19 at ER and microsome membranes (UniProt P33261: ER and microsome membranes). Signal concentrated at section edges, folds or necrotic areas suggests a preparation artefact and should be excluded from scoring (standard IHC practice). DAB signal that remains after omitting primary antibody points to the detection workflow, including possible endogenous enzyme activity, rather than antibody-dependent staining (standard IHC practice). Even an expected pattern needs independent specificity support because HPA cautions that its tissue antibody targets proteins from more than one gene (HPA: Supported, multi-gene caution).
Boster reagents

Best CYP2C19 / Cytochrome P450 2C19 IHC Antibodies

Anti-CYP2C19 antibodies have IHC images from human, mouse, and rat paraffin sections (catalog IHC captions). A02102 also lists human IF (catalog applications/reactivity); no IF image is supplied (catalog IF image alts).

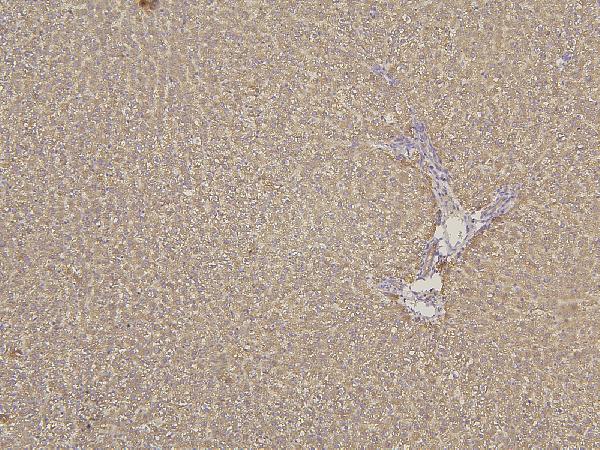
Real IHC data IHC analysis of CYP2C19 using anti-CYP2C19 antibody (A02102-2). CYP2C19 was detected in paraffin-embedded section of rat liver tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-CYP2C19 Antibody (A02102-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-Cytochrome p450 2C19/CYP2C19 Antibody ®
Cat # A02102-2
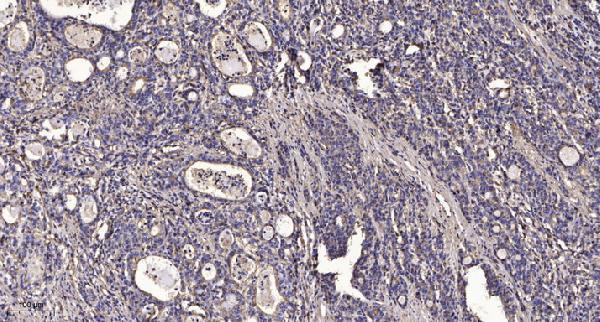
Real IHC data Immunohistochemical analysis of paraffin-embedded human Gastric adenocarcinoma. 1, Antibody was diluted at 1:200 (4° overnight). 2, Tris-EDTA, pH9.0 was used for antigen retrieval. 3, Secondary antibody was diluted at 1:200 (room temperature, 45min).
Anti-CYP2C19/Cytochrome P450 2C19 Antibody
Cat # A02102
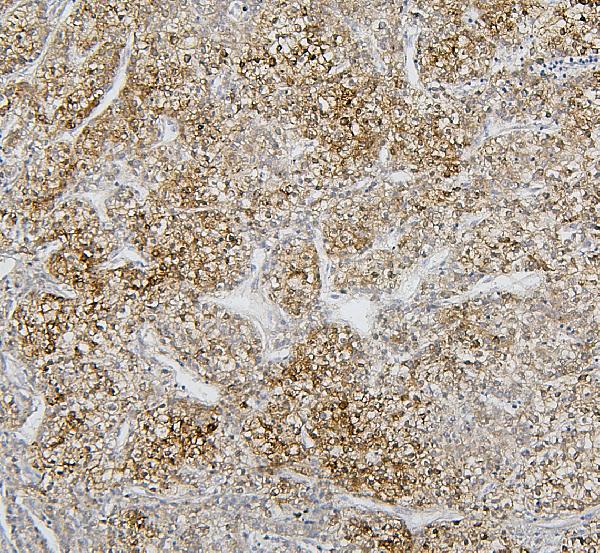
Real IHC data IHC analysis of Cytochrome p450 2C19/CYP2C19 using anti-Cytochrome p450 2C19/CYP2C19 antibody (M02102). Cytochrome p450 2C19/CYP2C19 was detected in paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml mouse anti-Cytochrome p450 2C19/CYP2C19 Antibody (M02102) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-Cytochrome p450 2C19/CYP2C19 Antibody ® (monoclonal, 10G5)
Cat # M02102
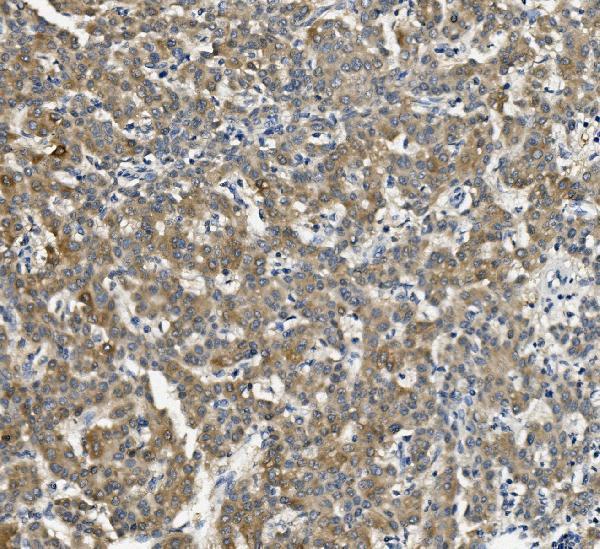
Real IHC data IHC analysis of Cytochrome p450 2C19/CYP2C19 using anti-Cytochrome p450 2C19/CYP2C19 antibody (M02102-1). Cytochrome p450 2C19/CYP2C19 was detected in paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml mouse anti-Cytochrome p450 2C19/CYP2C19 Antibody (M02102-1) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-Cytochrome p450 2C19/CYP2C19 Antibody ® (monoclonal, 5G4)
Cat # M02102-1

A02102-2 has IHC images from rat and mouse liver and human liver cancer paraffin sections (A02102-2 IHC captions); A02102 has a human gastric adenocarcinoma paraffin-section image and lists IF (A02102 IHC caption; catalog applications). M02102 and M02102-1 each have a human liver cancer paraffin-section IHC image (their respective IHC captions); both are mouse monoclonals (catalog host/clones).

Which to pick: For human tissue IHC, choose M02102 or M02102-1 if a monoclonal is preferred (catalog clones 10G5/5G4; respective human liver cancer IHC captions), or A02102 for its human gastric adenocarcinoma example (A02102 IHC caption). For human IF, A02102 is the listed option (catalog applications/reactivity); ICC validation and an IF image are unreported (catalog applications/IF image alts). For cross-species tissue IHC, A02102-2 has paraffin-section images from human, mouse, and rat samples (A02102-2 IHC captions); those captions do not report a fixative (A02102-2 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P33261 (CP2CJ_HUMAN, Cytochrome P450 2C19).
  2. Human Protein Atlas. CYP2C19 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. CYP2C19 subcellular location (ICC-IF): Mainly localized to vesicles. Caution: Based on antibodies targeting proteins from multiple genes..
  4. Human Protein Atlas. CYP2C19 antibody validation summary (2 antibodies).
  5. Alleviation of Aflatoxin B1-Induced Hepatic Damage by Propolis: Effects on Inflammation, Apoptosis, and Cytochrome P450 Enzyme Expression. Current issues in molecular biology 2026 — PMC12840301.
  6. Triptolide Induces hepatotoxicity via inhibition of CYP450s in Rat liver microsomes. BMC complementary and alternative medicine 2017 — PMC5217299.
  7. The down-regulation of the CYP2C19 gene is associated with aggressive tumor potential and the poorer recurrence-free survival of hepatocellular carcinoma. Oncotarget 2018 — PMC5955155.
  8. The humanised CYP2C19 transgenic mouse exhibits cerebellar atrophy and movement impairment reminiscent of ataxia. Neuropathology and applied neurobiology 2023 — PMC10108232.
  9. PubMed PMID:2009263 — UniProt-cited evidence.
  10. PubMed PMID:8095407 — UniProt-cited evidence.
  11. PubMed PMID:15164054 — UniProt-cited evidence.