DEPDC1B / DEP domain-containing protein 1B · IHC design guide

Design Immunohistochemistry for DEPDC1B

Plan DEPDC1B staining in paraffin sections using gallbladder glandular cells or testicular late spermatids as positive tissue controls (HPA tissue IHC). This guide covers fixation, detection and interpretation of the cytoplasmic tissue staining pattern (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for DEPDC1B (IHC for DEPDC1B): expected localisation Cytoplasmic staining (HPA tissue IHC), antibody A11735, validated IHC image, and IHC protocol steps
Printable DEPDC1B IHC protocol sheet — expected localisation Cytoplasmic staining (HPA tissue IHC), antibody A11735, controls and protocol steps. Open the full DEPDC1B IHC guide →

DEPDC1B Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining (HPA tissue IHC)
Staining pattern Cytoplasm in gallbladder glandular cells and late spermatids (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Gallbladder+3 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A11735)
Caveat Staining varies by sampled cell population (HPA tissue IHC)
Regulation Tissue-enhanced RNA expression (HPA RNA)
Isoform / epitope 2 isoforms; verify epitope coverage for each (UniProt)
Section 1

Recommended DEPDC1B IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by published DEPDC1B IHC methods for lung, ovarian, and cholangiocarcinoma samples (PMC9332445; PMC10088892; PMC9769124).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A11735); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-DEPDC1B, 5 μg/mL (datasheet A11735)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultDEPDC1B-positive staining in glandular cells of gallbladder (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissues, most abundant in gallbladder and testis. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page antigen retrieval); the lung study used EDTA for 30 min (PMC9332445).
Section 2

What Is the Expected DEPDC1B Staining Pattern?

In paraffin-section IHC, expect mainly cytoplasmic DEPDC1B staining, strongest in gallbladder glandular cells and elongated or late spermatids (HPA: tissue IHC). DEPDC1B has no annotated transmembrane segment, which is consistent with a non-membranous pattern but does not establish its precise location (UniProt Q8WUY9: topology). HPA rates its tissue IHC pattern Approved, with medium consistency against RNA data and external verification pending (HPA: tissue IHC reliability).

What am I looking at on my slide?
Cytoplasmic staining is strong in gallbladder glandular cells or elongated or late spermatids.This matches the reported high-signal cell populations (HPA: tissue IHC, High). Assess the named cells, since signal elsewhere in the section cannot substitute for the expected cellular pattern (standard IHC interpretation).
Staining is confined to cell borders or appears exclusively nuclear in tissue IHC.Treat this as discordant with the mainly cytoplasmic tissue profile and investigate artefact (HPA: tissue IHC). Nuclear signal alone is not proof of an off-target result: nucleoplasm is an additional location in ICC-IF (HPA: subcellular ICC-IF).
Strong staining appears in a cell population reported as not detected, such as adipocytes.Check antibody specificity and endogenous detection activity before calling it DEPDC1B (HPA: adipocytes, Not detected; standard IHC practice). A tissue-level label should be checked against the particular cell type being scored (HPA: tissue IHC).
Weak colour covers tissue broadly, including spaces between cells and the negative control.This distribution suggests background rather than a cellular DEPDC1B pattern (HPA: tissue IHC; standard IHC interpretation). Review blocking, antibody concentration and detection controls as general IHC troubleshooting steps (standard IHC practice).
No staining appears in gallbladder glandular cells or elongated or late spermatids.The result conflicts with reported high staining in those cells (HPA: tissue IHC, High). Check that the expected cells are present, then review the IHC workflow and a known-positive control before interpreting the test section as negative (standard IHC practice).
💡Expected DEPDC1B appearanceCall a convincing positive when cytoplasmic colour is strong in gallbladder glandular cells or elongated or late spermatids (HPA: tissue IHC, High); isolated border staining or colour across cell-free areas warrants review (HPA: tissue IHC; standard IHC interpretation).
How each factor affects the staining
Which cell population is being scoredGallbladder glandular cells and elongated or late spermatids are High; lymph-node non-germinal-center cells and tonsil germinal-center cells are Medium (HPA: tissue IHC). Compare like cells when judging intensity (standard IHC interpretation).
Strength of the tissue referenceThe tissue profile is Approved, with medium staining–RNA consistency and external verification pending (HPA: tissue IHC reliability). Use it as an expected pattern rather than definitive proof that every stained cell contains DEPDC1B (standard IHC interpretation).
Topology and protein formsUniProt annotates no transmembrane segment, signal peptide or propeptide and lists two isoforms (UniProt Q8WUY9). The supplied record gives no antibody epitope or isoform coverage, so it cannot predict isoform-specific IHC staining (UniProt Q8WUY9; supplied antibody data).
Antibody validation contextHPA072558 is Approved for IHC; HPA038255 is Approved for ICC, with no IHC status supplied for it (HPA: antibody validation). Interpret tissue and cell-image evidence in their respective applications (HPA: antibody validation).
IF/ICC Q: Where should fluorescence appear?A: Mainly at the Golgi apparatus, with additional nucleoplasm and cytosol signal (HPA: subcellular ICC-IF, approved locations). This cell-image pattern adds context; the expected paraffin-section IHC pattern remains mainly cytoplasmic (HPA: tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive gallbladder or testis is blankThe result disagrees with High staining in the specified cells; their absence from the section or an IHC workflow failure may explain it (HPA: tissue IHC; standard IHC practice).Confirm the named cells are present, then check positive control, primary incubation, detection reagents and counterstain (standard IHC practice).
Predominantly nuclear colour in tissue sectionsNuclear-only IHC differs from the reported mainly cytoplasmic tissue profile, although nucleoplasm is an additional ICC-IF location (HPA: tissue IHC; HPA: subcellular ICC-IF).Compare with a matched control and reassess cytoplasmic signal before assigning DEPDC1B localisation (standard IHC interpretation).
Strong colour in adipocytes or adrenal glandular cellsThose cells are reported as Not detected; off-target binding or endogenous detection activity is possible (HPA: tissue IHC; standard IHC practice).Inspect a no-primary control and the antibody's IHC validation; score the reported cell type separately from neighbouring cells (standard IHC practice; HPA: antibody validation).
Diffuse colour obscures cell boundariesBroad noncellular colour can reflect background from antibody concentration, blocking or detection chemistry (standard IHC practice).Compare no-primary control and tissue background; review blocking and antibody dilution under the chosen IHC workflow (standard IHC practice).
Only faint staining in an expected positiveIntensity may reflect the sampled cell population: HPA reports High in gallbladder glandular cells and late spermatids, but Medium in the listed lymphoid populations (HPA: tissue IHC).Identify and score the exact cells present, then compare the section with a known-positive control processed in the same run (standard IHC practice).
ICC-IF shows a Golgi signal while IHC looks broadly cytoplasmicThe two observations can fit their respective HPA reports: mainly Golgi in ICC-IF and cytoplasmic expression in tissue IHC (HPA: subcellular ICC-IF; HPA: tissue IHC).Interpret each assay against its own reference pattern and antibody validation; reserve IF/ICC workflow decisions for its separate guide (HPA: antibody validation; standard IHC/IF interpretation).

Sample controls for DEPDC1B IHC & IF

🧪Run gallbladder first and look for staining in glandular cells (HPA: High in gallbladder glandular cells). Use cervix glandular cells as the negative tissue (HPA: Not detected in cervix glandular cells); on the gallbladder slide, neighboring cells without specific signal should show only background staining, though HPA does not designate an internal negative cell type.
Positive control tissue: Gallbladder (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show DEPDC1B in A-431, U-251MG, U2OS, with annotated localisation: Golgi apparatus (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, a concentration-matched isotype control appropriate to the primary antibody’s host species and clonality, and DEPDC1B knockout tissue as a biological specificity control (standard IHC practice). Block endogenous peroxidase for chromogenic detection, and check gallbladder bile pigment against the no-primary slide because pigment may resemble deposited chromogen (standard IHC practice).
⚠️Feasibility: No matched source reports a DEPDC1B-specific fixation window or retrieval effect; the selected spleen IHC caption does not state a fixative (A11735 tissue-IHC caption: fixative not stated). Optimize heat-induced retrieval for the paraffin-section assay; the supplied evidence does not establish whether frozen sections or IF would be easier (standard IHC practice; supplied evidence: retrieval and format comparison unreported). In gallbladder, inspect pigmented areas carefully when scoring chromogenic signal (standard IHC practice).

HPA tissue IHC evidence for DEPDC1B

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Gallbladder Glandular cells High Protein (IHC) HPA →
Testis Elongated or late spermatids High Protein (IHC) HPA →
Lymph node Non-germinal center cells Medium Protein (IHC) HPA →
Tonsil Germinal center cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Epididymis Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced DEPDC1B IHC Tips

Troubleshoot DEPDC1B chromogenic IHC by checking retrieval, compartment, cell type and controls before interpreting staining intensity.

Which retrieval conditions should I start with for DEPDC1B in paraffin sections?
Start with citrate pH 6.0 heat induced epitope retrieval at 95–98 °C for 20 min (page retrieval rule). Keep section thickness, cooling time and the IHC-validated antibody concentration constant while comparing retrieval conditions (standard IHC practice); the selected tissue image used 5 µg/ml, although its fixative was unreported (A11735 caption). If staining is weak, test a second retrieval condition on adjacent sections while retaining the citrate condition as the reference (standard IHC practice). Score the same cell population and watch for tissue lifting or diffuse background before treating a stronger signal as improved DEPDC1B detection (standard IHC practice).
How should I investigate weak staining when fixation history varies?
Target-specific DEPDC1B sensitivity to fixation is unknown: the selected spleen IHC caption gives 5 µg/ml antibody but does not state the fixative (A11735 caption). Record fixative, fixation duration and processing history for each block, then compare sections with similar handling and the same citrate pH 6.0 retrieval at 95–98 °C for 20 min (standard IHC practice; page retrieval rule). Include a known staining control on each run and inspect whether weak signal tracks processing history rather than tissue identity (standard IHC practice). Do not infer a DEPDC1B-specific fixation effect from tissue expression, domain structure or phosphorylation annotations (HPA tissue IHC; UniProt Q8WUY9).
Which staining compartments are plausible for DEPDC1B?
Evaluate chromogenic staining primarily within cells: HPA tissue IHC describes cytoplasmic expression, while HPA ICC/IF places DEPDC1B mainly at the Golgi apparatus with additional nucleoplasm and cytosol signal (HPA tissue IHC; HPA subcellular). UniProt gives no subcellular annotation or transmembrane segment, so a sharply continuous cell-surface rim has no support from that record (UniProt Q8WUY9). Compare the pattern at the same magnification with citrate pH 6.0 retrieval held constant, and use a counterstain to distinguish cytoplasm from nuclei (page retrieval rule; standard IHC practice). Treat isolated extracellular deposits or a pattern confined to tissue edges as possible staining artefacts pending controls (standard IHC practice).
Could isoforms or epitope position explain discordant DEPDC1B staining?
DEPDC1B has 2 annotated isoforms, a DEP domain at residues 24–108 and a Rho-GAP domain at 201–393 (UniProt Q8WUY9). Its phosphoserines at 160 and 436 make epitope position relevant to assay interpretation, but the supplied evidence does not establish a phosphorylation-sensitive antibody (UniProt Q8WUY9; supplied antibody evidence). Check the antibody's stated immunogen or epitope and its coverage of each isoform before attributing different cellular patterns to alternative splicing (standard IHC practice). Compare adjacent sections under identical citrate pH 6.0 retrieval and detection conditions, then seek an independent antibody with a documented, distinct epitope if discordance persists (page retrieval rule; standard IHC practice).
How can IF help assess a questionable chromogenic DEPDC1B pattern?
Use IF/ICC as a separate localisation check: HPA reports mainly Golgi signal with additional nucleoplasm and cytosol signal in imaged cell lines (HPA subcellular). For tissue multiplexing, pair DEPDC1B with a glandular epithelial marker when assessing gallbladder glandular cells, which HPA scores High, and choose spectrally separated fluorophores after checking tissue autofluorescence (HPA tissue IHC; standard IF practice). Because UniProt lists no transmembrane segment, optimise mild permeabilisation for intracellular epitope access; the exact antibody epitope is not supplied (UniProt Q8WUY9; standard IF practice). Compare matched no-primary and single-colour controls, and keep the chromogenic IHC result tied to its own retrieval and detection controls (standard IF/IHC practice).
What should I check when DEPDC1B staining is diffuse or widespread?
First compare the stain with a no-primary control and review endogenous peroxidase blocking, antibody concentration, wash stringency and DAB development time (standard chromogenic IHC practice). The selected spleen image used 5 µg/ml antibody, which is a documented image condition rather than a universal optimum (A11735 caption). HPA reports cytoplasmic expression in several tissues and no detected staining in specified cells such as adipocytes, so ubiquitous dark deposits warrant scrutiny (HPA tissue IHC). Optimise one variable at a time under citrate pH 6.0 retrieval, checking section folds, edges and pigment before assigning diffuse colour to DEPDC1B (page retrieval rule; standard IHC practice).
How should I quantify DEPDC1B chromogenic staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring: HPA identifies High staining in gallbladder glandular cells and elongated or late spermatids, with cytoplasmic expression across several tissues (HPA tissue IHC). For a homogeneous region, report the percentage of positive target cells and an H-score from intensity categories; for scattered cells, report positive-cell density per mm² of viable tissue (standard IHC practice). Normalise counts to the number of eligible cells or viable tissue area, and use the same threshold, counterstain review and imaging settings across cases (standard IHC practice). Exclude folds, necrosis and edge staining, and document retrieval and detection batches before comparing scores (standard IHC practice).
When should I question an apparent DEPDC1B-positive IHC result?
Check whether signal occupies the expected cells and compartments: HPA reports High staining in gallbladder glandular cells and late spermatids, and describes cytoplasmic tissue expression (HPA tissue IHC). A continuous membrane rim is difficult to support from a record with no transmembrane segment; HPA ICC/IF instead reports Golgi, nucleoplasm and cytosol localisation (UniProt Q8WUY9; HPA subcellular). Review no-primary controls and tissue morphology to identify edge effects, necrosis, pigment or endogenous peroxidase before calling focal DAB deposits positive (standard IHC practice). HPA tissue staining is Approved with medium RNA consistency and pending external verification, so corroborate unexpected patterns with an independent assay (HPA tissue IHC).
Boster reagents

Best DEPDC1B / DEP domain-containing protein 1B IHC Antibodies

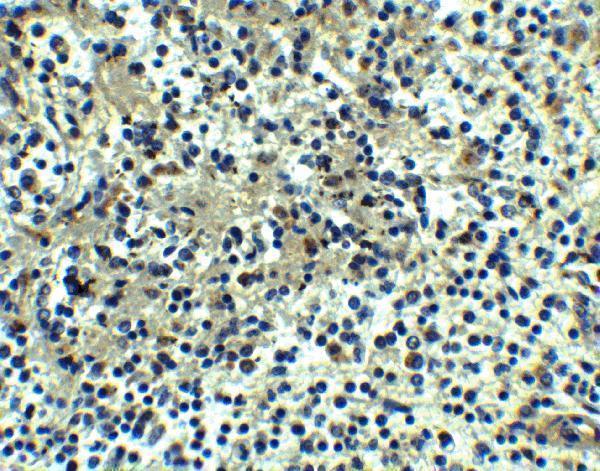
One human-reactive anti-DEPDC1B antibody has IHC-P data from human spleen; no IF/ICC data are listed (catalog: A11735 applications and image caption).

Real IHC data Immunohistochemistry of DEPDC1B in human spleen tissue with DEPDC1B antibody at 5 μg/ml.
Anti-DEPDC1B Antibody
Cat # A11735

A11735 is listed for human IHC-P (catalog: A11735 applications and reactivity). Its IHC image shows human spleen stained at 5 μg/mL (catalog: A11735 image caption).

Which to pick: Choose A11735 for human paraffin-section IHC; the catalog lists IHC-P, and its own image shows staining in human spleen at 5 μg/mL (catalog: A11735 applications and image caption). The fixative and clonality are unreported (catalog: A11735 image caption and clone field). No listed SKU supports an IF/ICC or cross-species recommendation: A11735 lists human reactivity and no IF/ICC application or image (catalog: A11735 reactivity, applications, and image records).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q8WUY9 (DEP1B_HUMAN, DEP domain-containing protein 1B).
  2. Human Protein Atlas. DEPDC1B tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. DEPDC1B subcellular location (ICC-IF): Mainly localized to the Golgi apparatus. In addition localized to the nucleoplasm and cytosol..
  4. Human Protein Atlas. DEPDC1B antibody validation summary (2 antibodies).
  5. High Expression of DEPDC1B Predicts Poor Prognosis in Lung Adenocarcinoma. Journal of inflammation research 2022 — PMC9332445.
  6. Role of DEP domain-containing protein 1B (DEPDC1B) in epithelial ovarian cancer. Journal of Cancer 2023 — PMC10088892.
  7. DEPDC1B collaborates with GABRD to regulate ESCC progression. Cancer cell international 2022 — PMC9202211.
  8. DEPDC1B promotes development of cholangiocarcinoma through enhancing the stability of CDK1 and regulating malignant phenotypes. Frontiers in oncology 2022 — PMC9769124.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:15372022 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.