This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section DGCR8 IHC using general nuclear staining as the tissue benchmark (HPA tissue IHC). Compare high-staining glandular cells with cell populations reported as low or undetected, using the IHC-validated antibody's documented conditions (HPA tissue IHC; datasheet A00475-1).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | General nuclear staining (HPA tissue IHC) | |
| Staining pattern | Nuclear staining across diverse tissue cell types (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6 HIER, heat-mediated (datasheet A00475-1) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Staining varies by cell type; adipocytes may be negative (HPA tissue IHC) | |
| Regulation | Ubiquitously expressed (UniProt) | |
| Isoform / epitope | 3 isoforms; map the antibody epitope to each sequence (UniProt) |
Compare the catalog antibody’s IHC-P protocol with published DGCR8 staining of testis, breast carcinoma, and melanoma sections (PMC7237130; PMC8242032; PMC12797089).
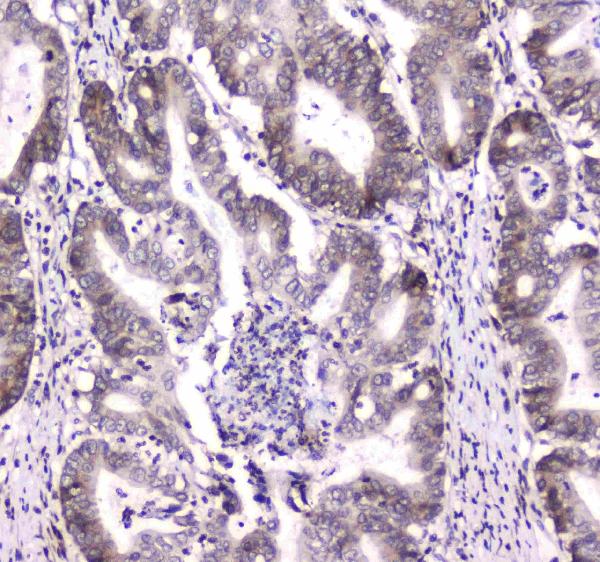
| Sample | Paraffin-embedded human rectal cancer tissue; fixative not specified (datasheet A00475-1) |
| Fixation | Image fixative and duration unreported (datasheet A00475-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Citrate pH 6, 20 min (datasheet A00475-1) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A00475-1) |
| Primary antibody | Rabbit anti-DGCR8, 0.5-1μg/ml (datasheet A00475-1) |
| Primary incubation | Overnight at 4 °C (datasheet A00475-1) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet A00475-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | DGCR8-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: General nuclear expression. No signal in the no-primary control. |
DGCR8 is a nuclear protein with no transmembrane segment (UniProt Q8WYQ5 topology). In paraffin-section IHC, expect predominantly nuclear staining, including in glandular cells of the colon and appendix and trophoblastic cells of the placenta (HPA: general nuclear expression; High in these cells). HPA rates its tissue IHC profile Approved, with medium consistency between antibody staining and RNA expression; interpret intensity with that limitation (HPA: reliability).
| Distinct nuclear staining in colon or appendix glandular cells, with relatively clear surrounding tissue. | This fits the reported high staining in those cells and the general nuclear IHC pattern (HPA: High in colon and appendix glandular cells; general nuclear expression). Score the nuclear signal in the named cells. Nucleolar detail may be difficult to resolve with chromogenic detection, even though DGCR8 has been detected there (UniProt Q8WYQ5 localization; standard IHC practice). |
| Strong staining is predominantly cytoplasmic or membranous while nuclei are faint. | This is the wrong dominant compartment for the reported tissue pattern (HPA: general nuclear expression). DGCR8 has no transmembrane segment (UniProt Q8WYQ5 topology). Treat the result as suspect and compare it with a known-positive nuclear pattern before assigning the signal to DGCR8 (standard IHC interpretation practice). |
| A cell type reported as undetected stains strongly, such as smooth muscle cells or adipocytes. | HPA reports no detected staining in smooth muscle cells and adipocytes in the listed tissues (HPA: Not detected). A strong result there warrants checks for antibody cross-reactivity or endogenous detection activity (standard IHC practice). It does not, by itself, overturn the reported pattern; assess it alongside nuclear localization and controls. |
| Weak color spreads across nuclei, cytoplasm, and extracellular areas with little cell-to-cell distinction. | Diffuse staining without nuclear enrichment is hard to reconcile with DGCR8's reported localization (HPA: general nuclear expression; UniProt Q8WYQ5 localization). Check background with a no-primary control, then review blocking, washes, detection, and counterstain as general IHC variables (standard IHC practice). |
| No nuclear signal appears in an adequately preserved colon glandular-cell section. | That conflicts with the reported high staining in colon glandular cells (HPA: High in colon glandular cells). First verify the positive-control section and detection run; then review the catalog antibody's validated IHC-P instructions and the run's retrieval and dilution settings (standard IHC practice). The supplied sources do not establish DGCR8-specific fixation sensitivity. |
| Choice of comparison tissue and cell type | Colon, appendix, duodenum, gallbladder, rectum, and salivary-gland glandular cells are reported High; placenta trophoblastic cells and testis round or early spermatids are also High (HPA: tissue IHC). Judge a run against its specific expected cell type, since HPA also lists Low and Not detected cell populations in other tissues (HPA: tissue IHC). |
| Subcellular resolution and application | UniProt describes nucleolar patches and small nucleoplasmic foci (UniProt Q8WYQ5 localization). HPA tissue IHC summarizes general nuclear expression, while its ICC-IF data support nucleoplasm and nuclear bodies (HPA: tissue IHC; ICC-IF). Use those finer locations as context, without requiring individual puncta to be visible in chromogenic paraffin sections (standard IHC practice). |
| Antibody validation and isoform coverage | The tissue profile is Approved with medium RNA-to-staining consistency, and HPA079351 is IHC Approved (HPA: reliability; antibody validation). DGCR8 has 3 listed isoforms (UniProt Q8WYQ5 isoforms). The supplied evidence gives no epitope location or isoform-specific staining comparison, so do not infer that an IHC result detects every isoform. |
| Endogenous detection activity | A no-primary control can reveal color generated by the detection system rather than primary-antibody binding (standard chromogenic IHC practice). This check matters when color appears in HPA-undetected cell types or outside nuclei, but it cannot alone identify antibody cross-reactivity (HPA: Not detected cell types; general nuclear expression; standard IHC practice). |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected-positive glandular cells have no visible nuclear staining. | The run may have a detection or setup problem; HPA reports High staining in colon glandular cells (HPA: tissue IHC; standard IHC practice). | Check the positive-control section and detection reagents, then follow the catalog antibody's validated IHC-P instructions for retrieval and dilution (standard IHC practice). Do not assume a DGCR8-specific fixation effect from the supplied evidence. |
| Brown signal is strong in cytoplasm or at cell borders. | The dominant location disagrees with general nuclear tissue staining and DGCR8's lack of a transmembrane segment (HPA: tissue IHC; UniProt Q8WYQ5 topology). | Compare with a known-positive nuclear pattern and a no-primary control; review blocking and detection background before scoring these cells positive (standard IHC practice). |
| Smooth muscle cells or adipocytes stain as strongly as the intended positive cells. | HPA lists these cell types as Not detected in the specified tissues; cross-reactivity or endogenous detection activity is possible (HPA: tissue IHC; standard IHC practice). | Check cell identity and localization, inspect the no-primary control, and interpret the result against the positive-control tissue (standard IHC practice). Avoid treating one unexpected cell population as proof of DGCR8 expression. |
| The whole section has a weak, even haze. | Broad background can obscure nuclear enrichment and may reflect general staining or detection conditions (standard IHC practice). | Inspect the no-primary control and review blocking, washes, detection, and counterstain (standard IHC practice). Reassess whether nuclei of the HPA-listed positive cells remain distinguishable (HPA: tissue IHC). |
| One section stains while another tissue or cell population appears negative. | HPA reports High, Low, and Not detected populations despite low RNA tissue specificity (HPA: tissue IHC; RNA specificity). | Compare like cell types and use a reported High population as the run control (HPA: tissue IHC; standard IHC practice). Do not classify every negative population as an assay failure. |
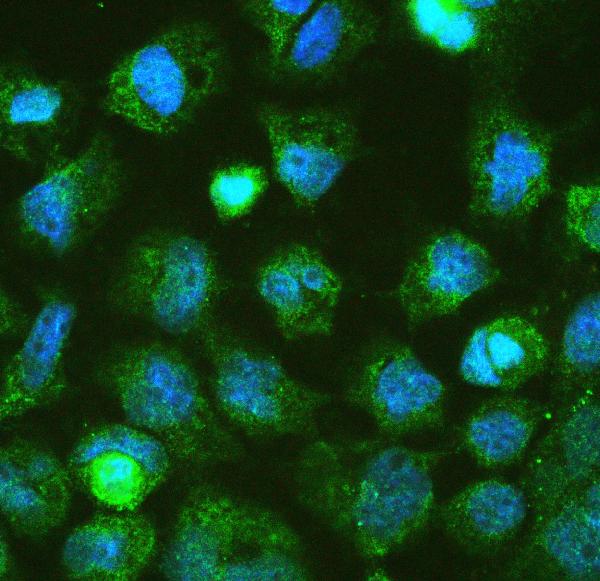
| Does an IF/ICC image with nucleoplasmic and nuclear-body signal fit DGCR8? | HPA supports both ICC-IF locations; UniProt also reports nucleolar and nucleoplasmic localization (HPA: ICC-IF; UniProt Q8WYQ5 localization). | Yes—interpret that image within its IF/ICC context (HPA: ICC-IF). For paraffin IHC, use the general nuclear tissue pattern to score staining (HPA: tissue IHC); IF/ICC methods belong in their separate guide. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | High | Protein (IHC) | HPA → |
| Placenta | Trophoblastic cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Liver | Cholangiocytes | Not detected | Protein (IHC) | HPA → |
| Ovary | Follicle cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot DGCR8 staining in paraffin sections by checking nuclear localisation, tissue controls and the documented conditions for the IHC-validated antibody.
A00475-1 has IHC images from human rectal cancer and mouse small intestine paraffin sections, plus IF in A431 cells (catalog image captions); both SKUs list human, mouse and rat reactivity (catalog).
A00475-1 has IHC images from human rectal cancer and mouse small intestine paraffin sections, and an IF image from A431 cells (catalog image captions). M00475 lists ICC/IF among its applications and human, mouse and rat reactivity, but has no supplied IHC or IF image (catalog).
Which to pick: For tissue IHC, choose A00475-1: its paraffin-section captions document citrate retrieval for 20 minutes and 1 μg/ml primary antibody; the fixative is unreported (A00475-1 IHC image captions). For IF/ICC, A00475-1 has an A431 IF image at 2 μg/ml, while M00475 is a monoclonal ICC/IF option without a supplied image (catalog IF image caption; catalog applications and clone). Both list human, mouse and rat reactivity, but the supplied tissue IHC images show only human and mouse samples (catalog reactivity; A00475-1 IHC image captions).