This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic DNMT1 IHC in paraffin sections around the nuclear staining seen mainly in proliferative cells (HPA tissue IHC). Use high-staining cell populations as reference points and assess nuclear signal by cell type (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear staining in proliferative cells (HPA tissue IHC) | |
| Staining pattern | Distinct nuclear signal, mainly in proliferative cells (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A00172-1) | |
| Positive control | Bone marrow+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep paraffin-section fixation consistent across samples. (standard IHC practice; not target-specific) | |
| Caveat | Cell-type mix can obscure positive nuclei (HPA tissue IHC) | |
| Regulation | Higher in proliferative cells (HPA tissue IHC) | |
| Isoform / epitope | 3 isoforms; isoform 2 is less expressed than 1 (UniProt) |
The catalog antibody uses heat retrieval with EDTA pH 8.0 (datasheet A00172-1). The published DNMT1 IHC protocols below cover pancreatic and cervical cancer tissue (PMC2920347; PMC5476577).
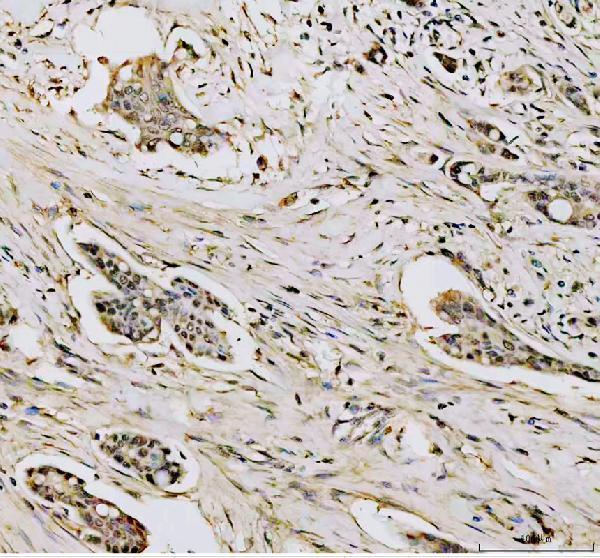
| Sample | Paraffin-embedded human breast cancer tissue; fixative not specified (datasheet A00172-1) |
| Fixation | Image fixative and duration unreported (datasheet A00172-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A00172-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A00172-1) |
| Primary antibody | Rabbit anti-DNMT1, 2-5μg/ml (datasheet A00172-1) |
| Primary incubation | Overnight at 4 °C (datasheet A00172-1) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A00172-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | DNMT1-positive staining in hematopoietic cells of bone marrow (HPA tissue IHC: High). HPA tissue profile: Distinct nuclear expression in several different cell types, mainly in highly proliferative cells. No signal in the no-primary control. |
DNMT1 should appear chiefly in nuclei, with the clearest IHC staining in proliferative cell populations (UniProt P26358: nucleus and chromosome; HPA tissue IHC: distinct nuclear expression, mainly in highly proliferative cells). HPA rates its tissue staining evidence “Enhanced,” citing consistency between antibody staining and RNA expression (HPA tissue IHC: reliability). DNMT1 has no transmembrane segment, so a membrane pattern would be unexpected (UniProt P26358: topology).
| Distinct nuclear staining in bone marrow hematopoietic cells, lymph node or tonsil germinal center cells, placental cytotrophoblasts, or testicular spermatogonia (HPA tissue IHC: High). | This matches the reported compartment and several cell populations with High staining (HPA tissue IHC: nuclear profile and High entries). Compare nuclei within the relevant population; an entire tissue section need not stain uniformly because the HPA observations name specific cells (HPA tissue IHC: cell level entries). |
| Predominantly membrane or cytoplasmic chromogen, with little convincing nuclear signal (UniProt P26358: nuclear location and no transmembrane segment). | The compartment conflicts with the expected DNMT1 pattern (UniProt P26358: subcellular location; HPA tissue IHC: nuclear profile). Treat it as possible nonspecific staining or detection artefact; compartment alone cannot identify the cause (general IHC interpretation). Check whether the signal survives appropriate negative controls (general IHC practice). |
| Strong staining in adipocytes or another cell population listed as Not detected, while expected positive nuclei are weak (HPA tissue IHC: adipocytes Not detected). | The cell level distribution raises concern for cross-reactivity or endogenous detection activity; it does not prove either mechanism (general IHC interpretation). HPA’s Not detected designation applies to its listed cell population and observations, so review matched morphology and controls before calling the whole tissue DNMT1 negative (HPA tissue IHC: cell level entries). |
| A diffuse brown haze spans nuclei, cytoplasm, and extracellular areas without a clear cell pattern (general chromogenic IHC observation). | This obscures the distinct nuclear pattern reported by HPA (HPA tissue IHC: nuclear profile). Consider nonspecific antibody binding, inadequate blocking or washing, or chromogen background as general IHC possibilities; assess a negative detection control and compare with intact tissue morphology (general IHC practice). |
| No nuclear staining in an intact expected positive population, such as tonsil germinal center cells or placental cytotrophoblasts (HPA tissue IHC: High). | A negative run in those cells calls for a technical check before interpreting the test specimen (general IHC practice). Confirm section quality, retrieval and detection controls, and the antibody’s IHC-P instructions; the supplied HPA and UniProt data do not specify a DNMT1 fixation sensitivity or an optimal retrieval condition. |
| Cell population and proliferation context | HPA describes nuclear staining mainly in highly proliferative cells and rates bone marrow hematopoietic cells, germinal center cells, cytotrophoblasts, and spermatogonia High (HPA tissue IHC). Choose and score the named populations instead of assuming every cell in a positive tissue has equal intensity (HPA tissue IHC: cell level entries). |
| Nuclear distribution | DNMT1 associates with chromosomes and replication foci during S phase and can localize near the nucleolus (UniProt P26358: subcellular location). Nuclear staining may therefore vary within or between nuclei; HPA’s tissue IHC profile supports a nuclear call, but does not establish a required punctate IHC pattern (HPA tissue IHC: profile). |
| Antibody validation | Both listed rabbit antibodies, HPA002694 and CAB005876, have Enhanced IHC validation; HPA describes Enhanced as agreement from independent antibodies or orthogonal data (HPA antibodies: IHC validation). This supports the reported pattern, but does not validate an unlisted antibody, a particular dilution, or a retrieval method (HPA antibodies: scope of supplied data). |
| Isoform and epitope coverage | UniProt lists 3 DNMT1 isoforms and reports isoform 2 at lower expression than isoform 1 (UniProt P26358: isoforms and tissue specificity). The payload gives no antibody epitope or isoform recognition data; do not assign an unusual staining pattern to isoform selectivity without antibody specific evidence. |
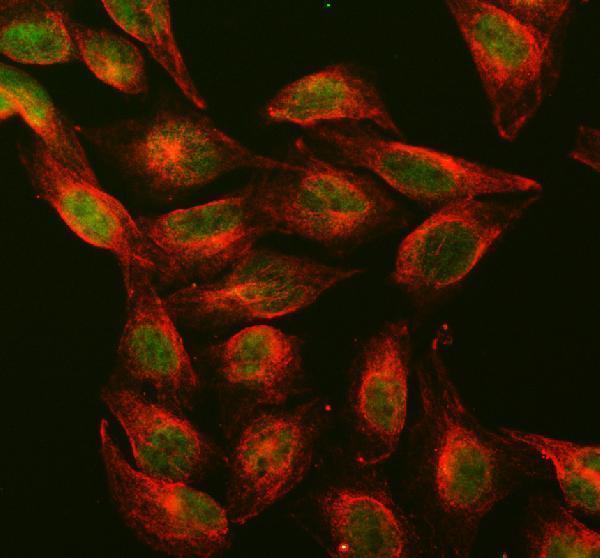
| IF/ICC Q&A: where should signal appear? | Answer: HPA reports supported nucleoplasmic localization in ICC-IF, consistent with UniProt’s nuclear assignment (HPA subcellular ICC-IF: Nucleoplasm; UniProt P26358: nucleus). That observation is a localization cross-check for this IHC guide; it does not provide an IF/ICC protocol or transfer an IHC staining intensity to cultured cells. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected positive nuclei are blank. | A failed or weak IHC workflow is possible; no target specific fixation or retrieval effect is established by the supplied sources. | Run a named High population alongside the specimen, then verify section integrity, the catalog antibody’s IHC-P instructions, retrieval, and detection controls (HPA tissue IHC: High entries; general IHC practice). |
| Chromogen is mostly membranous or cytoplasmic. | The distribution conflicts with DNMT1’s nuclear localization and lack of a transmembrane segment (UniProt P26358: location and topology). | Compare with expected positive nuclei and an appropriate negative detection control; check staining specificity before scoring those cells as positive (HPA tissue IHC: nuclear profile; general IHC practice). |
| Adipocytes stain strongly. | HPA lists adipocytes as Not detected; cross-reactivity or endogenous detection activity is possible, but the image alone cannot distinguish them (HPA tissue IHC: adipocytes; general IHC interpretation). | Check the cell identity and a negative detection control, then reassess whether nuclear staining in a named High population remains convincing (HPA tissue IHC: High entries; general IHC practice). |
| Diffuse background hides nuclear detail. | Nonspecific binding, incomplete washing, or detection background can obscure compartment calls (general chromogenic IHC practice). | Review blocking and washing steps and the negative detection control; adjust the workflow according to the catalog antibody’s IHC-P instructions, then reassess nuclear definition (general IHC practice). |
| Only a subset of otherwise similar cells stains. | DNMT1 associates with replication foci during S phase, and HPA reports staining mainly in proliferative cells (UniProt P26358: subcellular note; HPA tissue IHC: profile). | Score the cell population and compartment, compare intact neighboring cells, and avoid treating uneven intensity alone as assay failure (HPA tissue IHC: cell level pattern; general IHC interpretation). |
| Weak staining appears in a low or Not detected HPA population. | HPA’s categories describe observed cell level staining, not a universal threshold for every specimen or antibody (HPA tissue IHC: low and Not detected entries). | Check morphology, background, and controls before calling it positive; report the observed compartment and intensity rather than extrapolating from a whole tissue label (general IHC practice; HPA tissue IHC: cell level entries). |
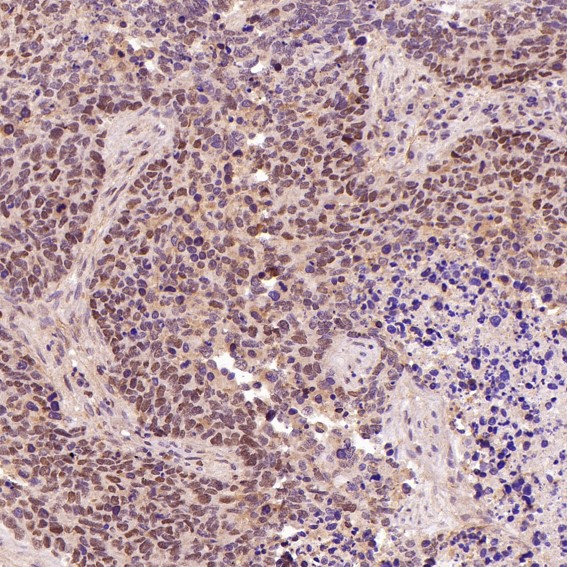
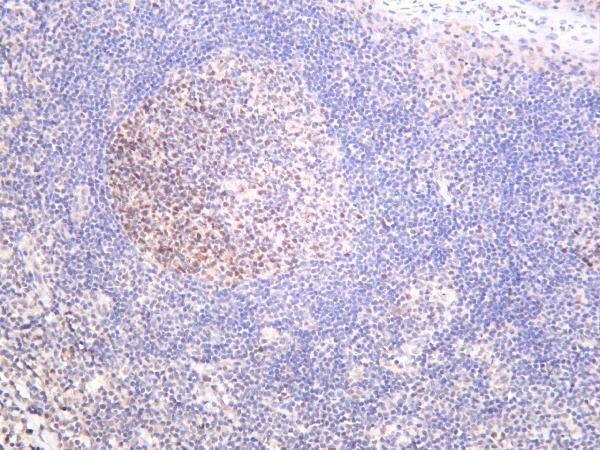
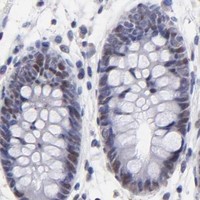


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Lymph node | Germinal center cells | High | Protein (IHC) | HPA → |
| Placenta | Cytotrophoblasts | High | Protein (IHC) | HPA → |
| Testis | Spermatogonia cells | High | Protein (IHC) | HPA → |
| Tonsil | Germinal center cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
Troubleshoot DNMT1 staining in paraffin-section IHC by checking nuclear localisation, tissue context, processing, and controls before interpreting signal intensity.
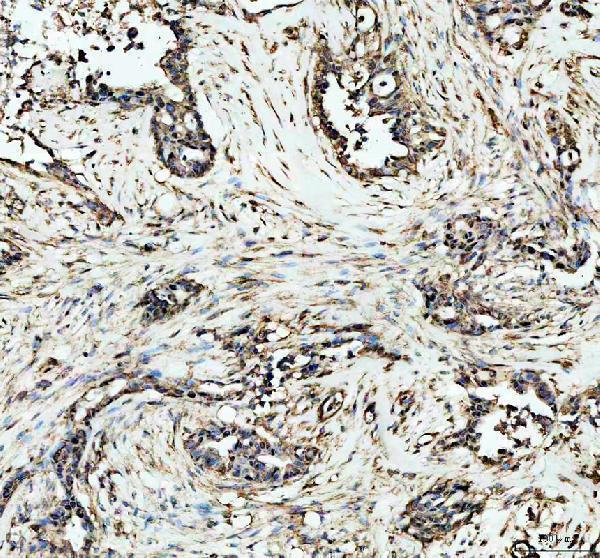
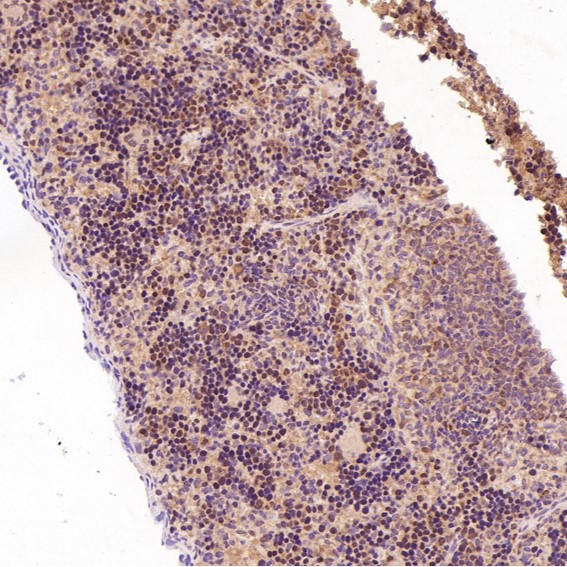
The catalog lists human-reactive DNMT1 antibodies with IHC images from human tissue, rat spleen and mouse lung; A00172-1 also has an IF image from U2OS cells (catalog applications, reactivity and image captions).
A00172-1 shows IHC in paraffin-embedded human breast and pancreas cancer sections and IF in U2OS cells (A00172-1 image captions). M00172 shows IHC in paraffin-embedded rat spleen, human lung cancer and glioblastoma, and mouse lung; M00172-3 shows IHC staining of human tonsil (M00172 and M00172-3 image captions).
Which to pick: For human tissue IHC, choose A00172-1 when its documented paraffin-section workflow is useful; M00172-3 offers a human tonsil IHC example, but its caption does not report section processing (A00172-1 and M00172-3 IHC image captions). For IF/ICC, A00172-1 has a documented U2OS IF example and lists both applications (A00172-1 IF image caption and applications). For cross-species tissue IHC, M00172 lists human, mouse and rat reactivity and shows paraffin-section images from each; the fixative is unreported in its captions (M00172 reactivity and IHC image captions).