This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan EBAG9 staining in paraffin sections around the granular cytoplasmic pattern observed in tissue (HPA tissue IHC). The guide covers the catalog antibody’s IHC dilution of 0.5–1 μg/ml (datasheet PB9553) and how to assess staining against that pattern (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Granular cytoplasm (HPA tissue IHC); Golgi membrane expected (UniProt) | |
| Staining pattern | Many cell types show granular cytoplasmic staining (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet PB9553) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific) | |
| Caveat | A soluble form could alter staining, but its existence is uncertain (UniProt) | |
| Regulation | No staining regulator specified (UniProt) | |
| Isoform / epitope | 2 isoforms; check whether the epitope lies outside the aa 7–27 anchor (UniProt) |
The catalog antibody protocol uses EDTA retrieval (datasheet PB9553). Two published EBAG9 IHC protocols provide ovarian cancer and mouse bone examples (PMC2409481 methods; PMC10835455 methods).
| Sample | Paraffin-embedded mouse testis tissue; fixative not specified (datasheet PB9553) |
| Fixation | Image fixative and duration unreported (datasheet PB9553); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet PB9553); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet PB9553) |
| Primary antibody | Rabbit anti-EBAG9, 0.5-1μg/ml (datasheet PB9553) |
| Primary incubation | Overnight at 4 °C (datasheet PB9553) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet PB9553) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | EBAG9-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression with a granular pattern. No signal in the no-primary control. |
EBAG9 should appear as granular cytoplasmic staining in many cell types, including glandular cells in appendix, cervix and colon (HPA tissue IHC: ubiquitous granular cytoplasmic expression; High in these cells). A Golgi-associated distribution is consistent with its membrane location and transmembrane topology (UniProt O00559: Golgi membrane; residues 7–27 transmembrane). Tissue IHC evidence is rated Enhanced for agreement with RNA expression (HPA tissue IHC: Enhanced).
| Granular cytoplasmic signal in appendix or cervix glandular cells. | This matches the reported pattern and High staining in these cells (HPA tissue IHC: ubiquitous granular cytoplasmic expression; High in appendix and cervix glandular cells). Judge the cellular pattern alongside the counterstain; intensity alone cannot establish specificity (general IHC practice). |
| Predominantly nuclear or uniformly surface-rim staining, without cytoplasmic granules. | This conflicts with tissue IHC and Golgi localization (HPA tissue IHC: granular cytoplasm; HPA subcellular: Golgi apparatus). Review morphology and controls before scoring it as EBAG9. Its transmembrane segment alone does not establish a surface-rim IHC pattern (UniProt O00559: residues 7–27 transmembrane). |
| Strong staining mainly in cardiomyocytes, myocytes or adipocytes. | These cells have reported Low staining (HPA tissue IHC: cardiomyocytes, skeletal myocytes and adipocytes Low). Disproportionately strong signal raises concern for cross-reactivity or endogenous detection activity; compare a no-primary control and known-positive glandular cells (general IHC practice). |
| Diffuse color over cells and surrounding section, obscuring granules. | This is hard to reconcile with the reported granular cytoplasmic pattern (HPA tissue IHC). Background can arise from nonspecific binding or endogenous detection activity (general IHC practice). Assess the no-primary control and whether the signal follows tissue structures before assigning a cell-level score. |
| No signal in appendix glandular cells on an otherwise interpretable section. | Appendix glandular cells are reported High (HPA tissue IHC). An absent result warrants a technical check of retrieval, antibody dilution and detection (general IHC practice). One negative run does not establish that the sample lacks EBAG9. |
| Compartment and topology (UniProt O00559; HPA subcellular) | EBAG9 is annotated at the Golgi membrane, with one transmembrane segment at 7–27 and a cytoplasmic region at 28–213 (UniProt O00559). A granular cytoplasmic IHC pattern fits the reported tissue observations (HPA tissue IHC); topology does not identify the antibody's epitope. |
| Tissue choice (HPA tissue IHC; UniProt O00559) | Appendix, cervix and colon glandular cells are reported High; cardiomyocytes and skeletal myocytes are Low (HPA tissue IHC). UniProt's tissue-specificity note lists colon among sites without expression, so treat colon as a source discrepancy rather than a definitive negative (UniProt O00559; HPA tissue IHC: colon glandular cells High). |
| Antibody evidence (HPA antibodies; HPA tissue IHC) | HPA021153 and HPA021154 have Enhanced IHC status, while CAB072810 has Supported IHC status (HPA antibodies). The tissue profile has Enhanced reliability for antibody staining and RNA agreement (HPA tissue IHC). These ratings support pattern interpretation; they do not validate an unspecified catalog antibody or its dilution. |
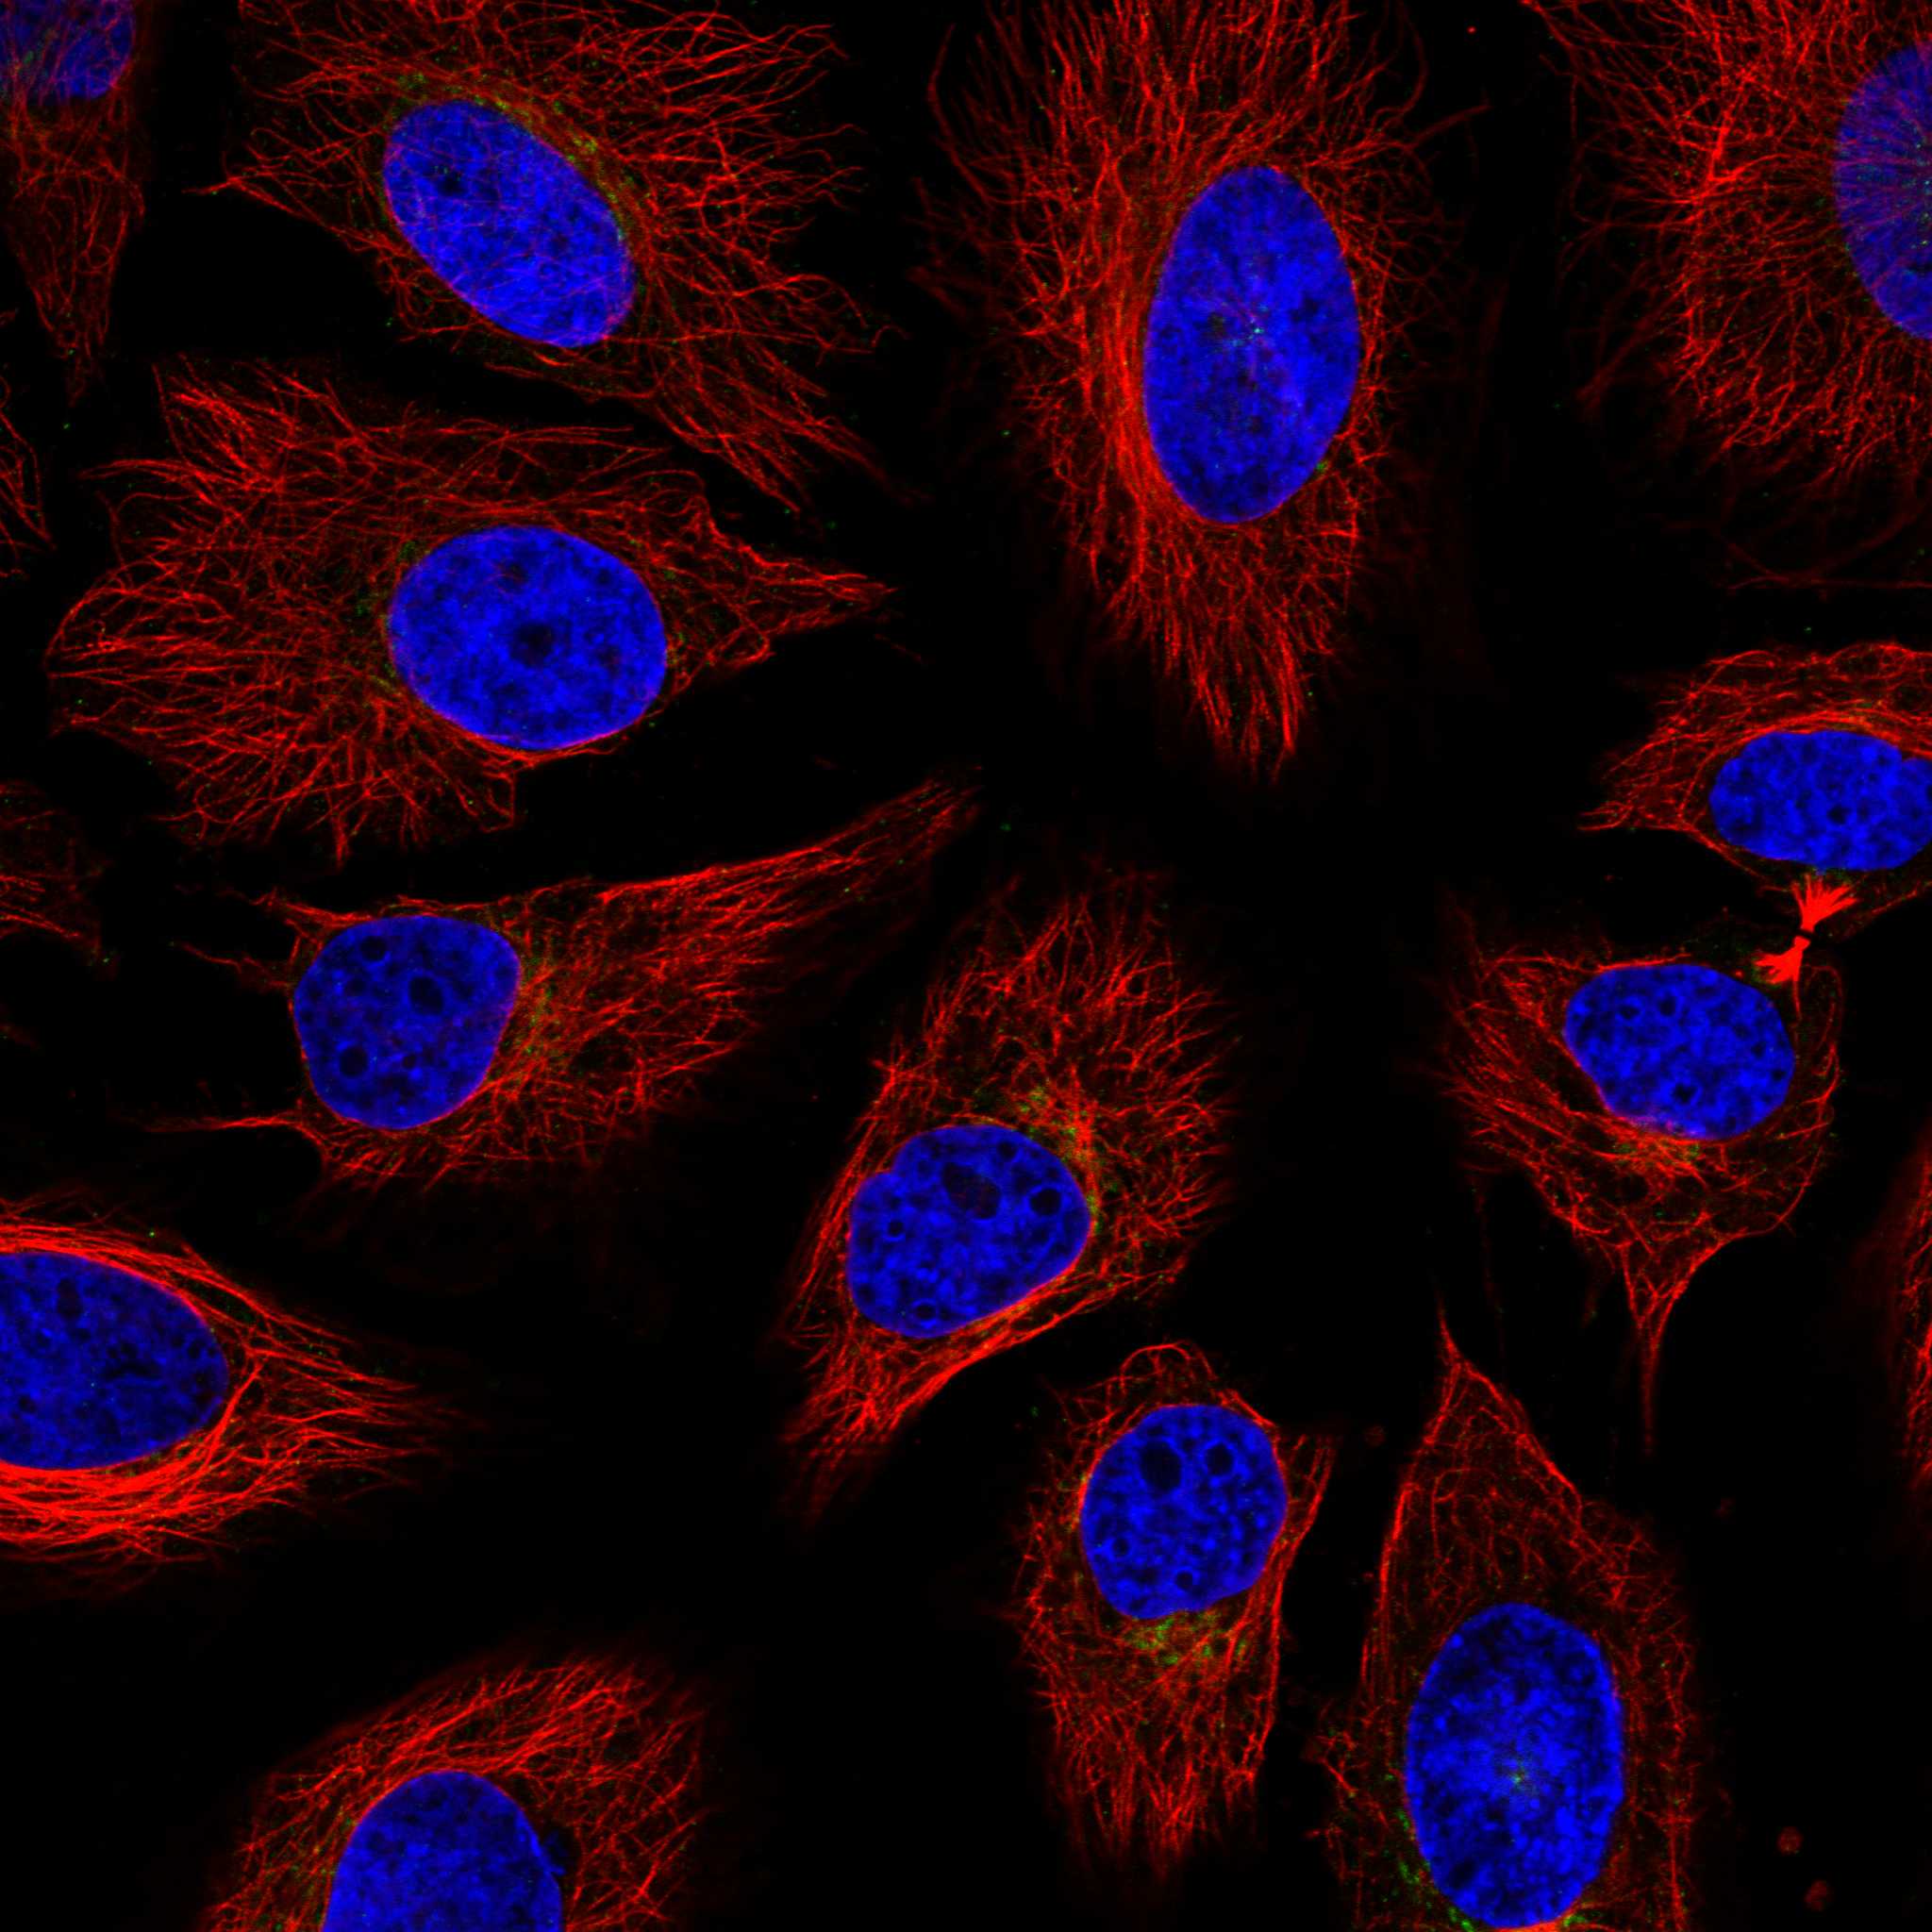
| IF/ICC Q&A: where should EBAG9 appear? (HPA subcellular) | In IF/ICC, a Golgi-associated signal is expected (HPA subcellular: Golgi apparatus, enhanced). Images are listed for HeLa, MCF-7 and U2OS (HPA subcellular). This is a localization cross-check, not an IHC-P staining protocol or evidence that every paraffin section will resolve the Golgi. |
| Isoforms and soluble-form claim (UniProt O00559) | UniProt lists 2 isoforms but supplies no isoform-specific staining pattern here (UniProt O00559). It also says a reported soluble form is uncertain (UniProt O00559). Do not assign diffuse extracellular color to shedding or infer which isoform an antibody detects without epitope evidence. |
| Antigen retrieval (general IHC practice) | Retrieval conditions can affect routine paraffin IHC performance (general IHC practice). No EBAG9-specific retrieval or fixation-sensitivity result is supplied, so select and assess conditions using the antibody's validated IHC-P instructions and tissue controls; do not infer an EBAG9-specific fixation effect. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected glandular-cell signal is absent (HPA tissue IHC: appendix glandular cells High). | Retrieval, dilution or detection may have failed (general IHC practice). | Run a known-positive section alongside the sample; check the antibody's IHC-P instructions, retrieval settings and detection reagents (general IHC practice). Interpret a sample negative only after the control stains as expected. |
| Brown color is widespread with little cellular detail. | Nonspecific binding or endogenous detection activity may obscure the granular pattern (general IHC practice; HPA tissue IHC: granular cytoplasm). | Compare a no-primary control, review blocking and washes, and confirm the detection system's endogenous-activity controls (general IHC practice). Score only cell-associated signal that remains distinguishable from background. |
| Signal is chiefly nuclear. | The compartment conflicts with cytoplasmic tissue staining and Golgi localization (HPA tissue IHC; HPA subcellular). | Check the counterstain and control sections, then reassess antibody specificity or detection background (general IHC practice). Do not count nuclear-only color as the expected EBAG9 pattern. |
| Muscle or adipose cells dominate the positive field. | These cells are reported Low; prominent staining may reflect cross-reactivity or background (HPA tissue IHC; general IHC practice). | Compare their signal with known-positive glandular cells and a no-primary control (HPA tissue IHC: appendix glandular cells High; general IHC practice). Reassess the result if the low-level cells remain strongest. |
| Colon stains strongly, but a reference note calls it absent. | The supplied sources disagree: colon glandular cells are High in HPA tissue IHC, while UniProt's tissue note lists colon as unexpressed (HPA tissue IHC; UniProt O00559). | Report the observed cell type and compartment with its source context. Use a second reported high-staining tissue, such as appendix, to check the run (HPA tissue IHC: appendix glandular cells High). |
| A diffuse extracellular deposit is interpreted as shed EBAG9. | UniProt describes the existence of a soluble form as uncertain (UniProt O00559). | Check whether the deposit persists in a no-primary control and whether cellular granules are present (general IHC practice; HPA tissue IHC: granular cytoplasm). Describe the deposit as observed; do not assign it to a soluble form from morphology alone. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | High | Protein (IHC) | HPA → |
| Cerebral cortex | Neuronal cells | High | Protein (IHC) | HPA → |
| Cervix | Glandular cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: EBAG9 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot EBAG9 staining in paraffin sections by checking retrieval, tissue preservation, cellular pattern and controls before comparing scores.
PB9553 has real IHC images of paraffin sections from human prostatic cancer and mouse and rat testis (PB9553 IHC image captions).
PB9553 is listed for IHC in human, mouse and rat samples (catalog: PB9553 applications and reactivity). Its IHC captions document staining in paraffin sections of mouse and rat testis and human prostatic cancer (PB9553 IHC image captions).
Which to pick: Choose PB9553 for tissue IHC in paraffin sections; its listed IHC dilution is 0.5–1 μg/ml, and the fixative is unreported (catalog: PB9553 IHC dilution; PB9553 IHC image captions). For work across human, mouse and rat samples, PB9553 has listed reactivity and IHC images for all three species (catalog: PB9553 reactivity; PB9553 IHC image captions). No IF/ICC antibody can be recommended from this catalog entry: PB9553 lists IHC and WB, has no IF image or dilution, and reports no clone (catalog: PB9553 applications, IF images, IF dilution and clone).