This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic FBXL20 IHC around cytoplasmic staining and cells in seminiferous ducts, where staining is high (HPA tissue IHC). Start the IHC-validated antibody at 2.5 μg/mL (datasheet), and interpret tissue patterns cautiously because their reliability is uncertain (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic in most cell types (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic signal in most cell types (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Testis+4 more · see all | |
| Negative control | Adrenal gland+4 more · see all |
| Fixation | Keep fixation conditions consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Tissue staining is uncertain; RNA concordance is low (HPA tissue IHC) | |
| Regulation | No expression regulator annotated (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope coverage is unreported (UniProt) |
Compare the catalog antibody’s IHC-P protocol with published FBXL20 IHC protocols for breast and pancreatic tissue (PMC8507197; PMC8570931).
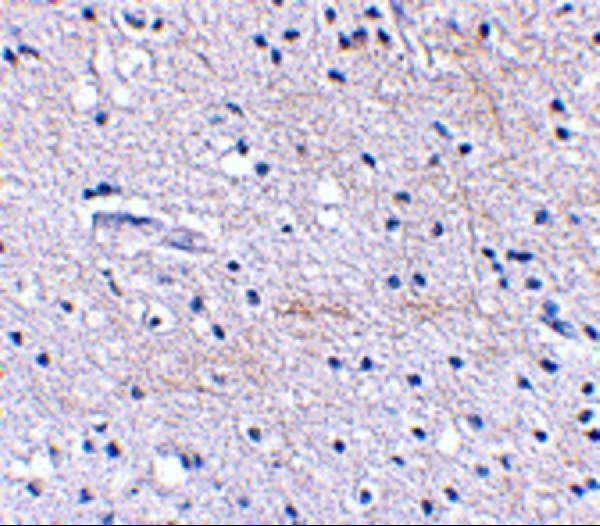
| Sample | human brain tissue; fixation not specified (datasheet A12714) |
| Fixation | Image fixative and duration unreported (datasheet A12714); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-FBXL20, 2.5 μg/mL (datasheet A12714) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | FBXL20-positive staining in cells in seminiferous ducts of testis (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most cell types. No signal in the no-primary control. |
FBXL20 is cytoplasmic and has no transmembrane segment (UniProt Q96IG2 localization and topology). In paraffin sections, expect cytoplasmic staining in many cell types, especially cells in seminiferous ducts of testis, where staining is reported as high (HPA tissue IHC). Treat the pattern as provisional: HPA rates tissue IHC reliability Uncertain because antibody staining has low consistency with RNA expression data (HPA tissue IHC reliability).
| Cytoplasmic staining in cells of seminiferous ducts is stronger than nearby background. | This matches the reported high testis signal and cytoplasmic tissue profile (HPA tissue IHC). It is a useful positive-control pattern, but HPA's Uncertain reliability means morphology alone cannot establish specificity (HPA tissue IHC reliability). |
| A crisp membrane rim or predominantly nuclear stain appears without convincing cytoplasmic signal. | That compartment does not match UniProt's cytoplasmic annotation or HPA's cytoplasmic tissue profile (UniProt Q96IG2 localization; HPA tissue IHC). Review morphology and detection controls before interpreting it as FBXL20; the observed compartment may reflect nonspecific staining. |
| Strong stain appears mainly in adrenal glandular cells while the testis comparison is weak. | HPA reports adrenal glandular cells as not detected and cells in seminiferous ducts as high (HPA tissue IHC). Investigate cross-reactivity or endogenous detection activity. Because HPA tissue IHC is Uncertain, this comparison is a warning rather than proof of an unexpected biological pattern (HPA tissue IHC reliability). |
| Color spreads through tissue or extracellular spaces and cell boundaries are hard to resolve. | This is diffuse background, so a cellular FBXL20 score is unreliable. General IHC practice: inspect the no-primary control, blocking and washes, and assess whether the chromogen reaction has obscured the cytoplasm. |
| The run shows no cytoplasmic signal in cells of seminiferous ducts. | That conflicts with HPA's reported high testis staining (HPA tissue IHC). Check section integrity, retrieval and detection with appropriate run controls before calling the sample negative. HPA's Uncertain reliability limits how strongly one tissue can establish assay failure (HPA tissue IHC reliability). |
| Tissue and cell selection | Testis cells in seminiferous ducts are reported high; adipocytes and several listed cell populations are medium, while adrenal glandular cells are not detected (HPA tissue IHC). Choose comparison cells by their stated level rather than assuming every cell in an organ stains alike. |
| Antibody validation | Both listed antibodies have Uncertain IHC status, and the overall tissue profile awaits external verification (HPA antibodies; HPA tissue IHC reliability). A matching stain is supportive, but control agreement and cellular localization remain necessary for interpretation. |
| Topology and localization | FBXL20 has no transmembrane segment and is annotated as cytoplasmic (UniProt Q96IG2 topology and localization). Judge chromogenic staining within cell cytoplasm; a membrane-only outline is inconsistent with these supplied annotations. |
| Isoforms and epitope coverage | UniProt lists two isoforms, but the payload gives no antibody epitope or isoform coverage (UniProt Q96IG2 isoforms). Isoform-specific detection cannot be inferred from a positive or negative IHC section. |
| IF/ICC: should a filament-like pattern be expected? | HPA reports approved microtubule localization by ICC-IF, with images from Rh30, SiHa and U2OS (HPA subcellular ICC-IF). This supports an IF interpretation question; it does not establish that paraffin chromogenic IHC must resolve individual microtubules (HPA tissue IHC). |
| Situation | Likely cause | Next action |
|---|---|---|
| Testis control is blank. | The expected high signal was not observed in cells of seminiferous ducts (HPA tissue IHC); the cause is undetermined. | General IHC practice: check section quality, retrieval, primary incubation, detection reagents and a working run control. Do not assign a FBXL20-specific fixation sensitivity; none is supplied. |
| Most cells stain uniformly, including a no-primary control. | A detection-system contribution is possible; uniform color does not demonstrate the HPA cytoplasmic cell pattern (HPA tissue IHC). | General IHC practice: inspect endogenous enzyme or biotin controls as relevant to the detection system, adjust blocking and washes, and compare with a no-primary section. |
| Only nuclei or cell borders stain. | The observed compartment conflicts with the cytoplasmic annotation and lacks the reported cytoplasmic tissue pattern (UniProt Q96IG2 localization; HPA tissue IHC). | General IHC practice: confirm cell boundaries with the counterstain, inspect control sections and reassess background before scoring the stain as FBXL20. |
| Adrenal glandular cells are strong while testis cells are weak. | This reverses the supplied not-detected versus high comparison, though the HPA IHC profile itself is Uncertain (HPA tissue IHC). | Compare matched runs and no-primary controls; investigate cross-reactivity or endogenous detection activity before claiming a tissue-specific exception. |
| Cytoplasmic color is too diffuse to score individual cells. | Background or excessive chromogen development may obscure the reported cellular pattern (HPA tissue IHC profile; general IHC practice). | General IHC practice: inspect the no-primary control, review blocking and washing, and shorten chromogen development if the run conditions support that adjustment. |
| IF/ICC shows microtubule-associated signal, but paraffin IHC looks broadly cytoplasmic. | HPA describes microtubules in ICC-IF and cytoplasmic expression in tissue IHC (HPA subcellular ICC-IF; HPA tissue IHC). The two observations have different reported resolution. | Interpret each assay against its own HPA annotation. Assess the IHC section for cellular cytoplasmic staining and controls; use the separate IF/ICC guide for imaging workflow. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Testis | Cells in seminiferous ducts | High | Protein (IHC) | HPA → |
| Adipose tissue | Adipocytes | Medium | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
| Breast | Adipocytes | Medium | Protein (IHC) | HPA → |
| Endometrium | Glandular cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
| Cervix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot FBXL20 chromogenic IHC by checking retrieval, tissue preservation, cytoplasmic localisation and controls before interpreting staining intensity (UniProt Q96IG2; standard IHC practice).
A12714 has an IHC image from human brain tissue at 2.5 μg/mL (catalog image caption). Human, mouse, and rat reactivity is listed; no IF data are supplied (catalog: A12714).
A12714 is the only card and lists IHC-P (catalog: A12714); its image shows staining of human brain tissue at 2.5 μg/mL (catalog image caption). Human, mouse, and rat reactivity is listed, while IF/ICC validation is unreported (catalog: A12714).
Which to pick: Choose A12714 for paraffin-section IHC (catalog: IHC-P); its IHC image depicts human brain tissue, but the fixative is unreported (catalog image caption). There is no IF/ICC pick because A12714 has no listed IF/ICC application or image (catalog: A12714). For cross-species planning, A12714 lists human, mouse, and rat reactivity, though its depicted IHC evidence is limited to human brain tissue (catalog: A12714; catalog image caption).