FLT4 / Vascular endothelial growth factor receptor 3 · IHC design guide

Design Immunohistochemistry for FLT4

Plan FLT4 staining in paraffin sections around the membranous and cytoplasmic pattern reported across tissues, including endothelial cells (HPA tissue IHC). Use the IHC-validated antibody's paraffin-section conditions as a starting point (datasheet: A01276-2), and interpret staining with the secreted isoform in mind (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for FLT4 (IHC for FLT4): expected localisation Membranous and cytoplasmic staining (HPA tissue IHC), antibody A01276-2, validated IHC image, and IHC protocol steps
Printable FLT4 IHC protocol sheet — expected localisation Membranous and cytoplasmic staining (HPA tissue IHC), antibody A01276-2, controls and protocol steps. Open the full FLT4 IHC guide →

FLT4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Membranous and cytoplasmic staining (HPA tissue IHC)
Staining pattern Cytoplasmic and membranous staining, including endothelial cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A01276-2)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Bone marrow+3 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Secreted isoform 3 may alter tissue staining (UniProt)
Regulation FLT4 signaling enhances VEGFC production (UniProt)
Isoform / epitope Three isoforms; isoform 2 has a shorter cytoplasmic tail, while isoform 3 is secreted, so epitope location matters (UniProt)
Section 1

Recommended FLT4 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A01276-2) is followed by published FLT4 IHC methods for colorectal tissue (PMC4413649) and Kaposi sarcoma biopsies (PMC10093722).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon cancer tissue; fixative not specified (datasheet A01276-2)
FixationImage fixative and duration unreported (datasheet A01276-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A01276-2)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01276-2)
Primary antibodyRabbit anti-FLT4, 0.5-1μg/ml (datasheet A01276-2)
Primary incubationOvernight at 4 °C (standard)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A01276-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultFLT4-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and membranous expression in most tissues, including endothelial cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated citrate pH 6 retrieval (datasheet A01276-2); published FLT4 IHC used citrate pH 6.0 for 15 min at 98 °C (PMC10093722).
Section 2

What Is the Expected FLT4 Staining Pattern?

FLT4 is a single-pass membrane receptor with an extracellular region and a cytoplasmic kinase region (UniProt P35916 topology). In paraffin tissue sections, expect membranous and cytoplasmic staining, including in endothelial cells (HPA tissue IHC: Approved). HPA also reports high staining in selected epithelial and other cell populations, so endothelial staining is not the sole expected positive pattern (HPA tissue IHC).

What am I looking at on my slide?
Membranous and cytoplasmic staining in endothelial cells or documented positive cell populations.This matches the approved tissue profile (HPA tissue IHC: Approved). Judge intensity against the cell type: kidney tubule cells and bronchial respiratory epithelial cells are reported as high (HPA tissue IHC: High).
Predominantly nuclear staining, without the expected membrane or cytoplasmic pattern.Treat an isolated nuclear pattern as inconclusive and check controls and antibody specificity (HPA tissue IHC: cytoplasmic and membranous profile). Nuclear localization is listed by UniProt, so nuclear signal alone does not prove an artefact (UniProt P35916 subcellular location).
Strong staining in a cell population reported as undetected, such as bone marrow hematopoietic cells.This conflicts with that cell-specific HPA observation and warrants checks for cross-reactivity or endogenous detection activity (HPA tissue IHC: Not detected in bone marrow hematopoietic cells; standard IHC practice). It does not establish that the entire tissue is negative.
Diffuse chromogen across cells and extracellular areas, with little anatomical definition.Interpret the slide cautiously: the reported tissue pattern has cellular membrane and cytoplasmic localization (HPA tissue IHC). Review blocking, antibody concentration and detection background as general IHC variables (standard IHC practice).
No staining in a known-positive cell population, such as kidney tubule cells.Do not score the sample as FLT4-negative until a positive control works (HPA tissue IHC: High in kidney tubule cells; standard IHC practice). Check that the intended cells are present and review the staining workflow.
💡Expected FLT4 appearanceA convincing positive shows anatomically defined membranous and cytoplasmic staining in the relevant cells, potentially strong in HPA high populations; widespread featureless chromogen or strong signal in an HPA-undetected cell population calls for controls (HPA tissue IHC; standard IHC practice).
How each factor affects the staining
Membrane topology and internalizationThe extracellular region spans residues 25–775 and the cytoplasmic region spans 797–1363 (UniProt P35916 topology); ligand-mediated autophosphorylation can rapidly internalize FLT4, making cytoplasmic signal biologically plausible (UniProt P35916 subcellular location).
Isoforms and secreted proteinFLT4 has three isoforms, and isoform 3 may be secreted (UniProt P35916 isoforms/function). Antibody epitope information is needed to determine which isoforms a stain can detect; the supplied record gives no epitope (UniProt P35916 isoforms; standard IHC interpretation).
Tissue and cell specificityHPA describes cytoplasmic and membranous expression in most tissues, including endothelial cells, but its high and undetected calls apply to named cell populations (HPA tissue IHC). Choose control cells accordingly.
Antibody validationHPA067906 and HPA074389 are approved for IHC; HPA074389 is supported for ICC (HPA antibodies). These statuses support their recorded applications, but do not establish identical staining or interchangeable performance for every antibody (HPA antibodies).
IF/ICC: what localization should be expected?HPA reports mainly cytosolic signal, with supported plasma membrane and approved centrosome localization in ICC-IF (HPA subcellular). Use the separate IF/ICC guide for that application; the paraffin IHC pattern is reported as cytoplasmic and membranous (HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in the sample or its positive control.A failed staining run is possible when a population reported as high also lacks signal (HPA tissue IHC: High in kidney tubule cells; standard IHC practice).Confirm the positive-control cells are present, then review antigen retrieval, antibody concentration and detection steps as general paraffin IHC checks (standard IHC practice); no FLT4-specific retrieval condition is supplied.
Diffuse staining obscures cell boundaries.Nonspecific binding or detection background may obscure localization (standard IHC practice); the HPA tissue profile is cellular and membranous/cytoplasmic (HPA tissue IHC).Review blocking, washes and antibody concentration; compare a no-primary control for detection background (standard IHC practice).
Strong staining appears in HPA-undetected cells.Cross-reactivity or endogenous detection activity is possible (standard IHC practice); HPA reports no detection in bone marrow hematopoietic cells and lymph-node germinal-center cells (HPA tissue IHC).Check the exact stained cell type, inspect a no-primary control and assess another validated antibody if available (standard IHC practice; HPA antibodies: two IHC-approved entries).
Only nuclear staining is visible.The pattern differs from HPA's usual tissue IHC profile, although UniProt lists nuclear localization (HPA tissue IHC; UniProt P35916 subcellular location).Review positive and no-primary controls, then corroborate the nuclear pattern before assigning it to FLT4 (standard IHC practice).
Endothelial signal is weak while nearby epithelial cells stain strongly.Intensity can differ by cell population: HPA reports high staining in several epithelial populations as well as endothelial expression (HPA tissue IHC).Score endothelial and epithelial cells separately, using the relevant HPA cell-specific observations and an anatomically matched positive control (HPA tissue IHC; standard IHC practice).
An HPA-undetected cell population stains weakly or inconsistently.HPA's undetected calls describe specific sampled cell populations, and its tissue reliability is Approved with a caveat about unannotated stained structures (HPA tissue IHC).Verify cell identity and reproducibility, compare controls and avoid extending a cell-specific undetected call to the whole tissue (HPA tissue IHC; standard IHC practice).

Sample controls for FLT4 IHC & IF

🧪Run appendix first: glandular cells should stain (HPA: High in appendix glandular cells). Use endometrial stromal cells as the negative tissue (HPA: Not detected in endometrial stromal cells); on the appendix slide, neighboring nonglandular cells should show only background signal, while their FLT4 status remains unassigned by these HPA rows (HPA: High in appendix glandular cells).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Bone marrow (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show FLT4 in HEK293, MCF-7, U2OS, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and host-matched rabbit IgG isotype controls, matching clonality when known, plus a FLT4 knockout biological negative (A01276-2 caption: rabbit primary; standard IHC control practice). Quench endogenous peroxidase and check for nonspecific DAB signal in appendix tissue (A01276-2 caption: DAB detection; standard chromogenic IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the exact A01276-2 tissue-IHC caption does not state the fixative (A01276-2 caption: fixative unreported). Its paraffin-section example uses heat retrieval in citrate buffer at pH 6 for 20 minutes, a starting condition rather than evidence that retrieval is required (A01276-2 caption: citrate retrieval). The supplied evidence does not establish whether frozen sections or IF/ICC are easier; in appendix glands, exclude luminal DAB deposits from cell-associated scoring (standard chromogenic IHC practice; HPA: High in appendix glandular cells).

HPA tissue IHC evidence for FLT4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex. Antibody staining in cells/structures not annotated, view images.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Cerebellum Purkinje cells High Protein (IHC) HPA →
Heart muscle Cardiomyocytes High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Endometrium Cells in endometrial stroma Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Lymph node Germinal center cells Not detected Protein (IHC) HPA →
Section 3

Advanced FLT4 IHC Tips

Troubleshoot FLT4 staining in paraffin sections by checking retrieval, compartment, cell identity and detection controls before interpreting signal intensity.

What retrieval should I try when FLT4 staining is weak?
Start with heat-mediated citrate buffer at pH 6 for 20 minutes on paraffin sections (datasheet A01276-2). Use the same retrieval conditions for test and control sections before comparing staining intensity (standard IHC practice). The reported image detected FLT4 in a human colon cancer section after this treatment, but does not establish that it is optimal for every specimen (datasheet A01276-2). If staining remains weak, adjust heating or cooling in a controlled series while checking tissue integrity (standard IHC practice). Record each condition because extracellular glycosylation and epitope location may affect antibody access, while this antibody’s epitope is unspecified (UniProt P35916 topology and glycosylation; datasheet A01276-2).
Could fixation explain weak or uneven FLT4 staining?
The selected paraffin-section image does not state a fixative, so target-specific fixation sensitivity for this antibody is unknown (datasheet A01276-2). Record the actual fixative and fixation duration for each specimen, then compare sections processed together using the same retrieval and detection conditions (standard IHC practice). Include the reported human colon cancer section as a practical positive control if comparable material is available (datasheet A01276-2). Assess weak areas for poor morphology or uneven processing before attributing them to FLT4 biology (standard IHC practice). Neither tissue staining patterns nor FLT4 topology establish a fixation effect for this antibody (HPA tissue IHC; UniProt P35916 topology).
How should membrane and cytoplasmic FLT4 staining be assessed?
Score membrane and cytoplasmic staining separately because both occur in tissue IHC, including endothelial cells (HPA tissue IHC). FLT4 has an extracellular region at residues 25–775, a membrane span at 776–796 and a cytoplasmic region at 797–1363 (UniProt P35916 topology). Cytoplasmic signal can reflect receptor internalization after ligand stimulation, but staining alone cannot establish that mechanism (UniProt P35916 subcellular annotation). The cell imaging record supports cytosol and plasma membrane localisation and also reports centrosomal localisation (HPA subcellular). Confirm which cell population carries each pattern on matched morphology; avoid treating diffuse staining across unrelated structures as endothelial signal (standard IHC practice; UniProt P35916 tissue specificity).
Can this stain distinguish FLT4 isoforms or receptor activation?
Do not assign an isoform from this stain unless the antibody epitope and its presence in each isoform are established (standard IHC interpretation; UniProt P35916 isoforms). FLT4 has 3 isoforms; isoform 3 is secreted, while isoform 2 has a truncated C terminus and lacks several phosphorylation sites (UniProt P35916 isoforms and function). The membrane receptor’s extracellular region contains immunoglobulin-like domains and multiple glycosylation sites, which makes epitope placement relevant to interpretation (UniProt P35916 domains, topology and glycosylation). This payload does not specify the catalog antibody’s epitope (datasheet A01276-2). Total FLT4 staining cannot by itself demonstrate phosphorylation or signaling, even where membrane or cytoplasmic signal is clear (UniProt P35916 function; standard IHC interpretation).
How can IF help check the FLT4 staining pattern?
On the separate IF/ICC workflow, pair FLT4 with a validated endothelial-cell marker to test the identity of stained cells (UniProt P35916 tissue specificity; standard IF practice). Choose spectrally separated fluorophores and place the weaker signal in a channel with low tissue autofluorescence after inspecting unstained sections (standard IF practice). If the antibody recognizes a cytoplasmic epitope, permeabilise appropriately; for an accessible extracellular epitope, assess staining without permeabilisation first (UniProt P35916 topology; standard IF practice). The catalog antibody’s epitope is unspecified, so the appropriate access condition requires testing (datasheet A01276-2). Compare membrane and intracellular signal with compartment and marker controls; the IHC image does not validate an IF protocol (HPA subcellular; datasheet A01276-2).
What causes widespread brown staining in FLT4 IHC?
First compare a section lacking primary antibody with the test section to locate signal arising from the chromogenic detection system (standard IHC practice). The reported method used 10% goat serum, a biotinylated secondary antibody, a streptavidin–biotin complex and DAB (datasheet A01276-2). Include a peroxidase block and assess endogenous biotin where relevant to this detection system (standard IHC practice). If background persists, compare antibody concentration and wash conditions while preserving the same retrieval and development time across sections (standard IHC practice). Interpret broad cytoplasmic staining cautiously because FLT4 expression is reported in many tissues and cell types (HPA tissue IHC).
How should FLT4 staining be quantified across specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the tissue compartment and cell population before scoring, then keep those definitions fixed across specimens (standard IHC practice). For cellular staining, record the percentage of positive cells and intensity separately, or use an H-score from 0–300 with a documented intensity scale (standard IHC practice). For vessels, report FLT4-positive vessel density per mm² of viable analysed tissue and specify how vessels were identified (standard IHC practice). Normalise cell counts to the number of eligible cells and vessel counts to analysed area, excluding necrosis and damaged edges consistently (standard IHC practice). Record membrane and cytoplasmic results separately because both patterns are reported for FLT4 (HPA tissue IHC).
How do I distinguish true FLT4 signal from artefact?
Prioritise reproducible staining in morphologically intact cells and compare its location with the expected membrane and cytoplasmic patterns (HPA tissue IHC; standard IHC practice). Check cell identity carefully: FLT4 protein is detected in endothelial cells, while high staining is also reported in several epithelial or glandular populations (UniProt P35916 tissue specificity; HPA tissue IHC). Treat isolated edge staining, necrotic deposits and signal retained in a no-primary control as possible artefacts (standard IHC practice). Investigate unexpected nuclear-only staining with an independent control rather than assigning it to a specific isoform; nuclear localisation is listed, but this antibody’s epitope is unspecified (UniProt P35916 subcellular annotation; datasheet A01276-2). With DAB detection, rule out endogenous peroxidase before interpreting brown deposits as FLT4 (datasheet A01276-2; standard IHC practice).
Boster reagents

Best FLT4 / Vascular endothelial growth factor receptor 3 IHC Antibodies

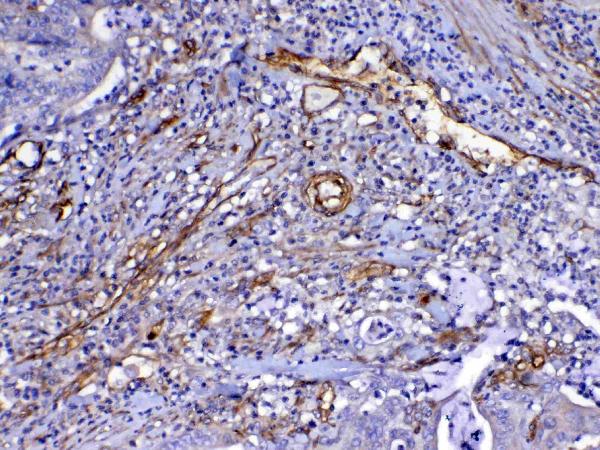
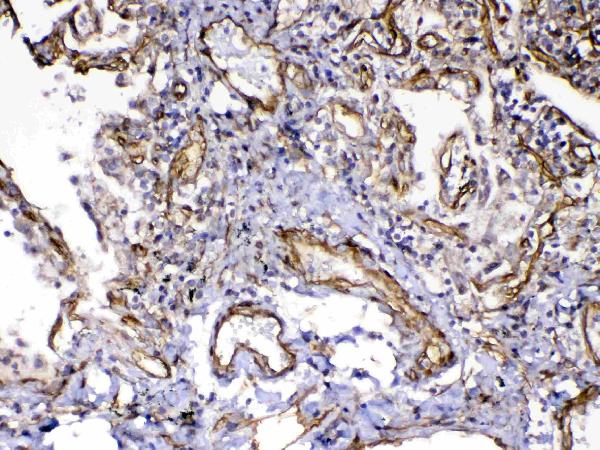
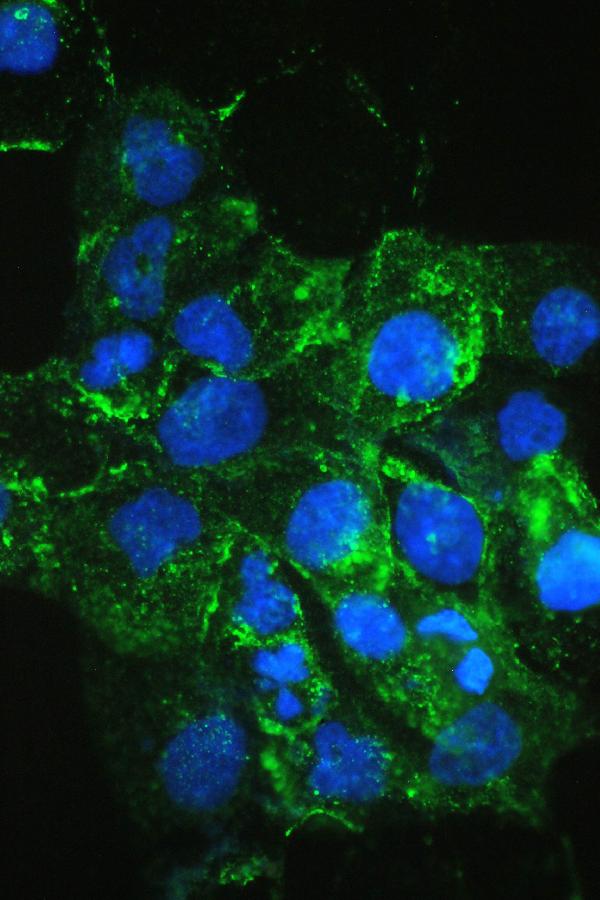
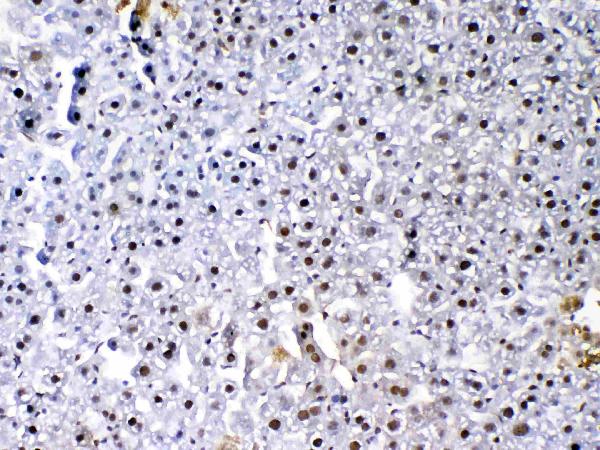
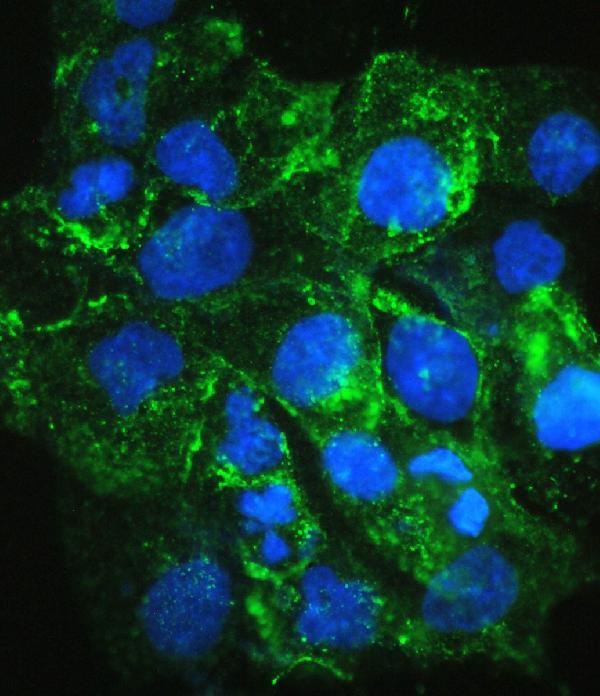
IHC-validated anti-FLT4 antibodies have paraffin-section images from human colon cancer, mouse liver, and human testis (catalog IHC captions: A01276-2, A01276-3, M01276-1); IF/ICC images show A431 cells (catalog IF captions: A01276-2, A01276-3).

Real IHC data IHC analysis of VEGF Receptor 3 using anti-VEGF Receptor 3 antibody (A01276-2). VEGF Receptor 3 was detected in paraffin-embedded section of human colon cancer tissue. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1ug/ml rabbit anti-VEGF Receptor 3 Antibody (A01276-2) overnight at 4 Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37 The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-VEGF Receptor 3/FLT4 Antibody ®
Cat # A01276-2
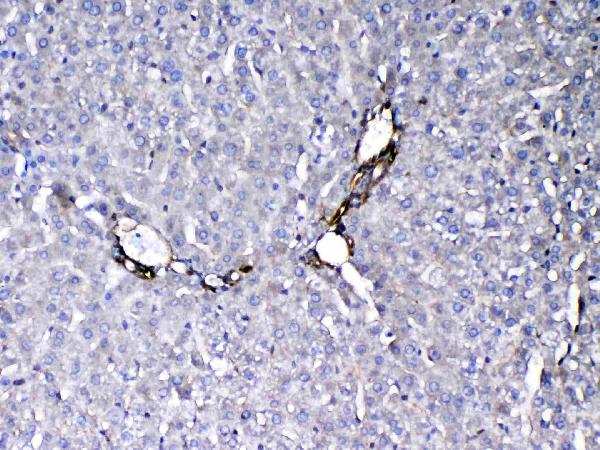
Real IHC data IHC analysis of VEGF Receptor 3 using anti-VEGF Receptor 3 antibody (A01276-3). VEGF Receptor 3 was detected in paraffin-embedded section of mouse liver tissue. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-VEGF Receptor 3 Antibody (A01276-3) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-VEGF Receptor 3/FLT4 Antibody ®
Cat # A01276-3
Real IHC data Immunohistochemical analysis of paraffin-embedded H. testis section using VEGFR3. was diluted at 1:25 dilution. A peroxidase-conjugated goat anti-mouse IgG at 1:400 dilution was used as the secondary antibody, followed by DAB staining.
Anti-VEGFR3 Antibody
Cat # M01276-1

A01276-2 shows IHC in human colon cancer paraffin sections and IF/ICC in A431 cells; A01276-3 shows IHC in mouse liver paraffin sections and IF/ICC in A431 cells (catalog image captions: A01276-2, A01276-3). M01276-1 shows IHC-P in human testis paraffin sections (catalog IHC caption: M01276-1).

Which to pick: For human tissue IHC, choose the mouse monoclonal M01276-1 if that host suits your detection system; its paraffin-section image uses 1:25 in human testis, with fixation unreported (catalog: M01276-1 clone 818CT12.1.1; catalog IHC caption: M01276-1). For IF/ICC, choose A01276-2 or A01276-3: both list IF and ICC and show A431 cell images (catalog applications and IF captions: A01276-2, A01276-3). For cross-species tissue IHC, A01276-3 lists human, mouse, and rat reactivity and has paraffin-section images in each species; its captions do not report fixation (catalog reactivity and IHC captions: A01276-3).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P35916 (VGFR3_HUMAN, Vascular endothelial growth factor receptor 3).
  2. Human Protein Atlas. FLT4 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. FLT4 subcellular location (ICC-IF): Mainly localized to the cytosol. In addition localized to the plasma membrane and centrosome..
  4. Human Protein Atlas. FLT4 antibody validation summary (2 antibodies).
  5. Genistein suppresses FLT4 and inhibits human colorectal cancer metastasis. Oncotarget 2015 — PMC4413649.
  6. Upregulation of Cell Surface Glycoproteins in Correlation with KSHV LANA in the Kaposi Sarcoma Tumor Microenvironment. Cancers 2023 — PMC10093722.
  7. FLT4 Mutations Are Associated with Segmental Lymphatic Dysfunction and Initial Lymphatic Aplasia in Patients with Milroy Disease. Genes 2021 — PMC8535675.
  8. PubMed PMID:1327515 — UniProt-cited evidence.
  9. PubMed PMID:1319394 — UniProt-cited evidence.
  10. PubMed PMID:8386825 — UniProt-cited evidence.