GCLM / Glutamate--cysteine ligase regulatory subunit · IHC design guide

Design Immunohistochemistry for GCLM

Plan chromogenic GCLM IHC on paraffin sections using the catalog antibody’s 1:50 human tissue protocol (datasheet M02948-2). Compare cytoplasmic staining with the HPA tissue profile, while accounting for its uncertain reliability (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for GCLM (IHC for GCLM): expected localisation General cytoplasmic staining (HPA tissue IHC), antibody M02948-2, validated IHC image, and IHC protocol steps
Printable GCLM IHC protocol sheet — expected localisation General cytoplasmic staining (HPA tissue IHC), antibody M02948-2, controls and protocol steps. Open the full GCLM IHC guide →

GCLM Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General cytoplasmic staining (HPA tissue IHC)
Staining pattern Cytoplasmic stain in glandular and neuronal cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M02948-2)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Ovary+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific)
Caveat Antibody staining and RNA expression show low consistency (HPA tissue IHC)
Regulation Stimulus response is unreported (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended GCLM IHC & IF Protocols

The catalog antibody has an IHC-P protocol (datasheet M02948-2). Two published GCLM IHC methods provide additional conditions (PMC4887909; PMC9010439).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human clear cell renal cell carcinoma tissue; fixative not specified (datasheet M02948-2)
FixationImage fixative and duration unreported (datasheet M02948-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M02948-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M02948-2)
Primary antibodyRabbit monoclonal (clone 28G35) anti-GCLM, 1:50 (datasheet M02948-2)
Primary incubationOvernight at 4 °C (datasheet M02948-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M02948-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultGCLM-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet M02948-2). A published alternative uses high-pH retrieval at 97°C (PMC4887909).
Section 2

What Is the Expected GCLM Staining Pattern?

In paraffin-section IHC, expect mainly cytoplasmic GCLM staining in sampled glandular, hematopoietic, respiratory epithelial, and neuronal cells (HPA tissue IHC). HPA rates the tissue IHC pattern Uncertain because staining and RNA data have low consistency (HPA tissue IHC). ICC-IF also places GCLM in the nucleoplasm and cytosol, with additional plasma-membrane signal (HPA subcellular ICC-IF). GCLM has no annotated transmembrane segment (UniProt P48507 topology).

What am I looking at on my slide?
Cytoplasmic staining in adrenal or appendix glandular cells, or bone-marrow hematopoietic cells.This matches HPA's general cytoplasmic IHC profile and Medium staining in those cells (HPA tissue IHC). Treat it as a plausible positive pattern, not proof of antibody specificity: HPA rates the tissue IHC evidence Uncertain because staining and RNA expression have low consistency (HPA tissue IHC).
Predominantly nuclear or membrane staining in a paraffin section, with little cytoplasmic staining.This differs from HPA's general cytoplasmic tissue IHC profile (HPA tissue IHC). Nucleoplasmic and additional plasma-membrane localization are reported from ICC-IF, so compartment alone cannot settle the discrepancy (HPA subcellular ICC-IF). Review morphology, counterstain, and controls before calling the IHC pattern specific (general IHC practice).
Strong staining confined to ovarian stromal cells or vaginal squamous epithelial cells.Both cell populations are listed as Not detected by HPA tissue IHC (HPA tissue IHC). Check cell identification and compare the signal with an appropriate negative control; unexpected chromogen can reflect nonspecific binding or endogenous detection activity (general IHC practice). The HPA IHC rating is Uncertain, so these observations are reference points rather than absolute exclusions (HPA tissue IHC).
Similar weak color across tissue structures and empty areas of the section.A pattern that does not follow cell boundaries is difficult to score as GCLM staining (general IHC practice). Compare with a no-primary control and inspect blocking, washes, and detection reagents for background (general IHC practice). HPA's tissue profile describes general cytoplasmic expression, not uniform extracellular color (HPA tissue IHC).
No convincing staining in adrenal glandular cells or bone-marrow hematopoietic cells.HPA reports Medium staining in those sampled cell populations, so absence of signal warrants a run check (HPA tissue IHC). Confirm tissue identity and assay controls, then review retrieval, primary-antibody use, and detection performance (general IHC practice). A negative result alone cannot establish biological absence, particularly with HPA tissue IHC rated Uncertain (HPA tissue IHC).
💡Expected GCLM appearanceCall a result plausible when cytoplasmic chromogen is discernible in the sampled glandular, hematopoietic, respiratory epithelial, or neuronal cells scored Medium by HPA; uniform background or strong staining restricted to HPA Not detected cell populations warrants control review (HPA tissue IHC; general IHC practice).
How each factor affects the staining
Tissue and cell populationHPA reports Medium IHC staining in adrenal, appendix, and breast glandular cells; bone-marrow hematopoietic cells; bronchial respiratory epithelial cells; and sampled neuronal populations (HPA tissue IHC). It reports Low staining in several other sampled populations and Not detected in ovarian stroma and vaginal squamous epithelium (HPA tissue IHC). Score the identified cell population, not the whole tissue, and retain HPA's Uncertain reliability rating (HPA tissue IHC).
IHC versus IF compartmentHPA describes tissue IHC as generally cytoplasmic, while approved ICC-IF locations include nucleoplasm and cytosol, with additional plasma-membrane localization (HPA tissue IHC; HPA subcellular ICC-IF). For the IF/ICC question, report those observed compartments; do not treat the ICC-IF images as a paraffin-section IHC validation (HPA subcellular ICC-IF; HPA antibodies).
Antibody validationHPA lists IHC as Uncertain and ICC as Approved for HPA023696, CAB009568, and CAB040554 (HPA antibodies). The tissue IHC reliability note cites low consistency between staining and RNA expression and pending external verification (HPA tissue IHC). An IHC result therefore needs interpretation alongside controls and cell morphology (general IHC practice).
Protein architecture and variantsUniProt lists no transmembrane segment or signal peptide, one chain spanning residues 1–274, and two isoforms (UniProt P48507 topology, processing, isoforms). These annotations do not establish which epitopes an antibody recognizes, whether isoforms stain differently, or whether antigen retrieval will improve staining (UniProt P48507; general IHC practice). Target-specific fixation sensitivity is unreported in the supplied evidence.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive-control cell population is blank.The run may have failed at primary-antibody binding or chromogenic detection (general IHC practice); HPA reports Medium staining in several sampled cell populations (HPA tissue IHC).Confirm tissue identity, inspect the positive and no-primary controls, and check retrieval, antibody application, and detection steps against the assay record (general IHC practice). Do not infer GCLM absence from this run alone (general IHC practice).
The entire section has diffuse chromogen.Background may arise from nonspecific reagent binding, inadequate washing, or endogenous detection activity (general IHC practice).Compare with a no-primary control; review blocking, washes, and detection-system controls before scoring cells (general IHC practice). HPA's reported tissue pattern is cytoplasmic rather than diffuse color across the section (HPA tissue IHC).
Nuclei dominate the IHC signal.The finding departs from HPA's general cytoplasmic tissue IHC profile, although nucleoplasm is an approved ICC-IF location (HPA tissue IHC; HPA subcellular ICC-IF).Verify nuclear boundaries with the counterstain and compare controls; record the compartment and avoid equating the ICC-IF location with validated paraffin-section IHC staining (general IHC practice; HPA antibodies).
Strong color appears in ovarian stroma or vaginal squamous epithelium.Those cell populations are listed as Not detected in HPA tissue IHC; nonspecific binding or endogenous detection activity is possible (HPA tissue IHC; general IHC practice).Recheck cell identification and the no-primary control, then review blocking and detection conditions (general IHC practice). Treat HPA's Not detected entries cautiously because overall tissue IHC reliability is Uncertain (HPA tissue IHC).
Two tissues yield different staining strengths.HPA reports Medium, Low, and Not detected results across sampled cell populations, and rates the tissue IHC profile Uncertain (HPA tissue IHC).Compare the same identified cell populations and consistent scoring criteria; use run controls before attributing the difference to GCLM expression (general IHC practice).
IF shows nuclear signal while IHC appears cytoplasmic.HPA reports approved nucleoplasmic and cytosolic ICC-IF localization alongside a general cytoplasmic tissue IHC profile (HPA subcellular ICC-IF; HPA tissue IHC).Describe each assay's observed compartment separately and assess its own controls; the HPA ICC-IF result does not resolve the Uncertain tissue IHC validation (HPA antibodies; HPA tissue IHC; general IHC practice).

Sample controls for GCLM IHC & IF

🧪Run appendix first: glandular cells should stain (HPA: Medium in appendix glandular cells). Use ovarian stroma as the negative tissue (HPA: Not detected in ovarian stroma cells); within the appendix section, compare glandular staining with any unstained cells actually observed, without assuming a particular cell type is negative.
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Ovary (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show GCLM in U-251MG, U2OS, A-431, KOLF2.1J, with annotated localisation: Nucleoplasm (approved), Cytosol (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and matched rabbit IgG isotype controls (caption: rabbit anti-GCLM antibody); use GCLM knockout material as a biological specificity control, or a peptide block if the immunizing peptide is available. Quench endogenous peroxidase and check inflammatory cells in appendix for background before interpreting HRP/DAB staining (caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected M02948-2 tissue-IHC caption does not state a fixative (caption: fixative unreported). The caption uses heat retrieval in EDTA at pH 8.0 for a paraffin section; whether GCLM staining depends on retrieval is unreported (caption: EDTA retrieval). Frozen sections and IF are not established as easier by the supplied evidence; for appendix IHC, distinguish glandular staining from possible endogenous peroxidase signal in inflammatory cells (HPA: Medium in appendix glandular cells; caption: HRP/DAB detection; standard IHC practice).

HPA tissue IHC evidence for GCLM

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Vagina Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced GCLM IHC Tips

Troubleshoot GCLM staining in paraffin sections by checking retrieval, cellular distribution, controls, and scoring against the evidence available for this antibody.

Which retrieval conditions should I try first for GCLM in paraffin sections?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 (datasheet M02948-2). The catalog antibody stained a paraffin section of human clear cell renal cell carcinoma after this retrieval, followed by 1:50 primary antibody overnight at 4°C (datasheet M02948-2). If staining is weak, check heating consistency, section adherence, and whether the same detection conditions were used before comparing alternative retrieval buffers (standard IHC practice). Run the alternatives beside the EDTA condition on adjacent sections and judge both signal and tissue morphology (standard IHC practice). A stronger stain alone does not establish specificity, especially given uncertain tissue IHC reliability (HPA: Uncertain).
How should I assess whether fixation is limiting GCLM staining?
The selected image documents a paraffin section but does not state its fixative, so target-specific fixation sensitivity is unknown (datasheet M02948-2). Record the specimen's actual fixation history and compare sections with known processing histories using the same EDTA pH 8.0 retrieval and 1:50 primary dilution (datasheet M02948-2; standard IHC practice). Inspect morphology and compare staining with a no-primary control before attributing weak signal to fixation (standard IHC practice). HPA tissue patterns do not measure fixation sensitivity, and the absence of a transmembrane segment does not establish it either (HPA: tissue IHC; UniProt P48507 topology).
Which cellular compartment should count as GCLM-positive in tissue IHC?
Use cytoplasmic staining as the principal tissue IHC pattern, while treating its specificity cautiously because the tissue assessment has uncertain reliability (HPA: general cytoplasmic expression; HPA: Uncertain). Cell imaging also places GCLM mainly in the cytosol and nucleoplasm, with an additional plasma membrane location (HPA: subcellular). Because GCLM has no annotated transmembrane segment, a sharp membrane-only chromogenic rim needs independent validation before it is scored as specific (UniProt P48507 topology; standard IHC practice). Compare the same cell population across adjacent sections and review its counterstained nuclei to distinguish cytoplasmic signal from overlapping cells (standard IHC practice). Keep the 1:50 dilution constant during that comparison (datasheet M02948-2).
Can this antibody distinguish GCLM isoforms or modified epitopes in IHC?
GCLM has 2 listed isoforms, but the supplied antibody caption does not identify its epitope or establish isoform selectivity (UniProt P48507 isoforms; datasheet M02948-2). Its annotated chain spans residues 1–274, and a modified lysine is reported at position 263; neither annotation establishes whether the antibody recognizes that region (UniProt P48507 processing and modified residues). Do not assign different staining patterns to isoforms or acetylation without epitope information and an independent validation experiment (standard IHC practice). Compare adjacent sections under identical EDTA pH 8.0 retrieval, then interpret any staining difference as an assay observation rather than an isoform measurement (datasheet M02948-2; standard IHC practice).
How should I investigate GCLM by IF after seeing a tissue IHC signal?
For IF, pair GCLM with a marker that identifies the cell population being examined; glandular cells in adrenal tissue are one documented tissue IHC population (HPA: adrenal gland, glandular cells Medium; standard IF practice). Choose a fluorophore in a channel with low tissue autofluorescence and include single-stain and no-primary controls before judging colocalisation (standard IF practice). GCLM is reported mainly in cytosol and nucleoplasm, so assess permeabilisation when testing access to intracellular epitopes; its antibody epitope is unspecified (HPA: subcellular; datasheet M02948-2; standard IF practice). A possible plasma membrane signal does not prove an extracellular epitope, because GCLM has 0 annotated transmembrane segments (HPA: subcellular; UniProt P48507 topology).
What should I check when GCLM DAB staining looks diffuse?
Start with a no-primary section to assess secondary reagent and endogenous peroxidase background, and inspect whether DAB appears outside intact cells (standard IHC practice). The selected assay used 10% goat serum blocking, a 1:50 rabbit primary overnight at 4°C, and a peroxidase-conjugated secondary for 30 minutes at 37°C (datasheet M02948-2). If the control is clean, compare shorter primary exposure or a lower antibody concentration while keeping retrieval and development matched (standard IHC practice). If the control stains, check peroxidase blocking, secondary binding, and DAB development before interpreting a diffuse cytoplasmic signal as GCLM (standard IHC practice; HPA: general cytoplasmic expression).
How can I score GCLM staining reproducibly across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring; cytoplasmic tissue staining is reported, but the tissue IHC reliability is uncertain (HPA: general cytoplasmic expression; HPA: Uncertain). For DAB sections, record both the percentage of positive cells and intensity by a consistent H-score scheme, or measure positive-cell density per mm² of viable tissue (standard IHC practice). Normalise to the number or area of eligible cells in the same annotated region, excluding folds, edges, and necrosis by preset rules (standard IHC practice). Keep EDTA pH 8.0 retrieval, primary dilution, development, imaging, and thresholds matched across comparisons (datasheet M02948-2; standard IHC practice).
How do I separate credible GCLM staining from artefact?
Look for staining within intact cells in a plausible compartment, especially the cytoplasm reported for tissue IHC, and compare it with a no-primary section (HPA: general cytoplasmic expression; standard IHC practice). HPA reports medium staining in adrenal glandular cells and no detected staining in ovarian stromal cells, although its overall tissue IHC reliability is uncertain (HPA: adrenal gland glandular cells Medium; HPA: ovarian stroma cells Not detected; HPA: Uncertain). Treat isolated edge staining, necrotic deposits, and signal reproduced without primary antibody as potential artefacts, including endogenous peroxidase activity (standard IHC practice). Recheck questionable fields at the same 1:50 primary dilution and EDTA pH 8.0 retrieval before comparing biological groups (datasheet M02948-2; standard IHC practice).
Boster reagents

Best GCLM / Glutamate--cysteine ligase regulatory subunit IHC Antibodies

Catalog antibodies cover human, mouse and rat GCLM IHC, with tissue images for two products; IF is listed as an application for another product (catalog applications, reactivity and image captions).

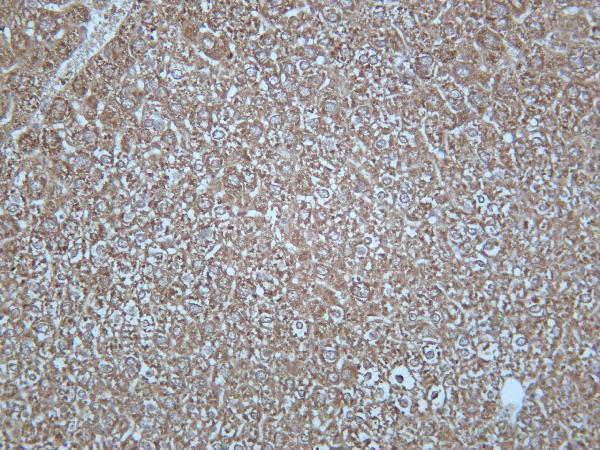
Real IHC data IHC analysis of GCLM using anti-GCLM antibody (M02948-2). GCLM was detected in a paraffin-embedded section of human clear cell renal cell carcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-GCLM Antibody (M02948-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-GCLM Rabbit Monoclonal Antibody
Cat # M02948-2
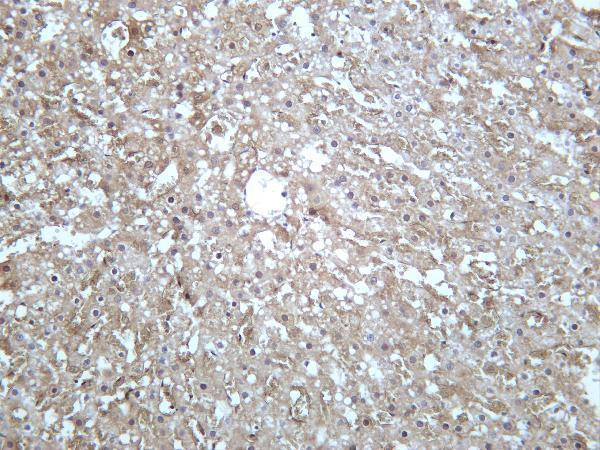
Real IHC data Mouse liver was stained with anti-GCLM rabbit antibody
Anti-GCLM Rabbit Monoclonal Antibody
Cat # M02948-3

M02948-2 has an IHC image of a paraffin-embedded human clear cell renal cell carcinoma section (M02948-2 image caption). M02948-3 has an IHC image of mouse liver and lists human, mouse and rat reactivity plus IF among its applications (M02948-3 image caption; catalog applications and reactivity).

Which to pick: For paraffin-section IHC, choose rabbit monoclonal M02948-2: its own caption documents EDTA retrieval at pH 8.0 and a 1:50 primary dilution; the fixative is unreported (M02948-2 image caption). For IF/ICC, choose rabbit monoclonal M02948, which lists both applications but has no IF image in the payload (M02948 catalog applications and image captions). For cross-species tissue IHC, consider M02948-3: its IHC images include mouse, rat and human liver, and its listed reactivity covers all three species; the image captions do not report processing or fixation (M02948-3 image captions and catalog reactivity).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P48507 (GSH0_HUMAN, Glutamate--cysteine ligase regulatory subunit).
  2. Human Protein Atlas. GCLM tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. GCLM subcellular location (ICC-IF): Mainly localized to the nucleoplasm and cytosol. In addition localized to the plasma membrane..
  4. Human Protein Atlas. GCLM antibody validation summary (3 antibodies).
  5. Nuclear localization of glutamate-cysteine ligase is associated with proliferation in head and neck squamous cell carcinoma. Oncology letters 2016 — PMC4887909.
  6. Anti-CD47 Antibody Enhances the Efficacy of Chemotherapy in Patients with Gastric Cancer Liver Metastasis. Journal of Cancer 2023 — PMC9969583.
  7. Topical Bixin Confers NRF2-Dependent Protection Against Photodamage and Hair Graying in Mouse Skin. Frontiers in pharmacology 2018 — PMC5880955.
  8. Persistent ferroptosis promotes cervical squamous intraepithelial lesion development and oncogenesis by regulating KRAS expression in patients with high risk-HPV infection. Cell death discovery 2022 — PMC9010439.
  9. PubMed PMID:7826375 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:16710414 — UniProt-cited evidence.