GNG2 / Guanine nucleotide-binding protein G(I)/G(S)/G(O) subunit gamma-2 · IHC design guide

Design Immunohistochemistry for GNG2

This guide uses adipose adipocytes as a high-staining reference for GNG2 chromogenic IHC in paraffin sections (HPA tissue IHC). Score membranous and cytoplasmic staining cautiously because the tissue profile awaits external verification (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for GNG2 (IHC for GNG2): expected localisation Membranous and cytoplasmic tissue staining (HPA tissue IHC), antibody A06975-1, validated IHC image, and IHC protocol steps
Printable GNG2 IHC protocol sheet — expected localisation Membranous and cytoplasmic tissue staining (HPA tissue IHC), antibody A06975-1, controls and protocol steps. Open the full GNG2 IHC guide →

GNG2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Membranous and cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Widespread membrane/cytoplasm; high in adipocytes and neuropil (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A06975-1)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ Adrenal gland+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Tissue staining awaits external verification (HPA tissue IHC)
Regulation Fetal tissue expression is reported (UniProt)
Isoform / epitope No annotated isoforms; mature chain spans 2–68 (UniProt)
Section 1

Recommended GNG2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by three published chromogenic GNG2 IHC protocols for claustrum studies (PMC6555083; PMC3434180; PMC3975097).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human appendicitis tissue; fixative not specified (datasheet A06975-1)
FixationImage fixative and duration unreported (datasheet A06975-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A06975-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A06975-1)
Primary antibodyRabbit anti-GNG2, 2-5μg/ml (datasheet A06975-1)
Primary incubationOvernight at 4 °C (datasheet A06975-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A06975-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultGNG2-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: Ubiquitous membranous and cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet A06975-1); the published protocols describe different section preparations (PMC6555083; PMC3434180; PMC3975097).
Section 2

What Is the Expected GNG2 Staining Pattern?

GNG2 is annotated at the cell membrane and has no transmembrane segment (UniProt P59768 topology). In paraffin-section IHC, expect membranous and cytoplasmic staining in selected cell populations, including adipocytes and smooth muscle cells (HPA tissue IHC). Treat the pattern as provisional: HPA rates tissue IHC reliability Uncertain because staining includes cells or structures that have not been annotated, and external verification is pending (HPA tissue IHC).

What am I looking at on my slide?
Adipocytes or smooth muscle cells show distinct membranous staining with some cytoplasmic signal.This fits HPA's ubiquitous membranous and cytoplasmic tissue-IHC profile and its High calls for adipocytes in adipose tissue and smooth muscle cells. Judge the stained cells and compartment together; HPA rates the tissue-IHC pattern Uncertain (HPA tissue IHC).
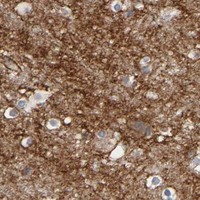
Cerebral cortex neuropil stains strongly, while individual cell borders are difficult to resolve.Neuropil is a High staining structure in the HPA tissue record, so its appearance can support the expected distribution. Do not assign that signal to a particular cell type from neuropil staining alone; HPA's tissue-IHC reliability remains Uncertain (HPA tissue IHC).
Nuclei dominate the staining, with little signal at cell borders or in cytoplasm.A nuclear-dominant pattern conflicts with the reported membrane and cytoplasmic tissue profile (HPA tissue IHC) and cell-membrane annotation (UniProt P59768). Investigate assay artefact or nonspecific staining before interpreting the nuclei as GNG2; the supplied sources do not establish nuclear localisation.
A population listed as not detected stains strongly, such as adrenal glandular cells or bone marrow hematopoietic cells.The staining conflicts with those specific HPA observations and warrants checks for cross-reactivity or endogenous detection activity (HPA tissue IHC; general chromogenic IHC practice). A single discordant population is not proof of either cause: HPA rates tissue IHC Uncertain, and its calls are cell specific.
Diffuse colour covers tissue and empty areas, or a known positive population shows no convincing signal.Colour beyond cellular structures suggests background from the detection workflow; absence in adipocytes or smooth muscle cells conflicts with HPA High calls (HPA tissue IHC; general IHC practice). Check controls and assay performance before scoring an experimental specimen as positive or negative.
💡Expected GNG2 appearanceCall a section positive when adipocytes or smooth muscle cells show convincing membrane-associated staining, potentially with cytoplasmic signal, at a level consistent with their HPA High calls; nuclear-dominant colour or diffuse deposit is suspect, and the call remains provisional because HPA tissue-IHC reliability is Uncertain (HPA tissue IHC; UniProt P59768 cell-membrane annotation).
How each factor affects the staining
Cellular location and topologyUniProt places GNG2 at the cell membrane and annotates no transmembrane segment (UniProt P59768 topology). HPA reports membranous and cytoplasmic tissue staining (HPA tissue IHC); assess both compartments instead of requiring a sharp membrane-only outline.
Choice of reference tissueAdipose adipocytes, cerebral cortex neuropil and smooth muscle cells are High HPA observations (HPA tissue IHC). Use an identified positive population when judging assay performance; neuropil provides a structure-level comparison rather than a cell-type call.
Limits of a negative comparisonHPA lists adrenal glandular cells and bone marrow hematopoietic cells as not detected, while other cells and tissues stain (HPA tissue IHC). Compare the specified population rather than treating the whole organ as a universal negative control.
Strength of antibody evidenceBoth listed antibodies have Uncertain IHC status, and the tissue profile awaits external verification (HPA antibodies; HPA tissue IHC). Give weight to localisation, cell identity and controls together; an isolated positive field cannot establish specificity.
Antigen retrieval and detection controlsNo GNG2-specific retrieval condition or fixation-sensitivity result is supplied. Optimise retrieval against a positive section and include detection controls as general paraffin-IHC practice; these steps do not predict a GNG2-specific fixation effect.
IF/ICC Q: What distribution should be expected?A: HPA reports an approved main plasma-membrane location and additional vesicular location in ICC-IF (HPA subcellular). This is a localisation reference for IF/ICC, not an IHC protocol or proof that vesicles will resolve in chromogenic paraffin sections.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A known positive section has no signal in adipocytes or smooth muscle cells.The result conflicts with HPA High observations in those populations (HPA tissue IHC); assay setup or an unsuitable antibody may be involved, but the supplied sources do not identify a GNG2-specific fixation cause.Check section integrity, retrieval, primary-antibody and detection steps against assay controls, then repeat with a verified positive section (general IHC practice). Do not infer true tissue absence from an unvalidated run.
Colour appears mainly in nuclei.Nuclear-dominant staining does not match HPA's membranous and cytoplasmic tissue profile or UniProt's cell-membrane annotation (HPA tissue IHC; UniProt P59768).Compare with a no-primary control and an identified positive population, then review counterstain and detection deposits (general chromogenic IHC practice). Withhold a GNG2 localisation call unless the expected compartments are convincing.
Strong signal appears in adrenal glandular cells or bone marrow hematopoietic cells.Those populations are listed as Not detected (HPA tissue IHC). Cross-reactivity or endogenous detection activity is possible, but HPA's Uncertain reliability prevents a definitive explanation.Confirm the cell population, inspect a no-primary control, and reassess blocking and detection conditions (general IHC practice). Compare with a HPA High population before assigning the discordant signal to GNG2.
Diffuse stain obscures cell boundaries or appears outside tissue.The distribution cannot be assessed against the expected membrane and cytoplasmic profile (HPA tissue IHC). Background may arise from the chromogenic detection workflow (general IHC practice).Inspect no-primary and detection controls, then adjust blocking, washing or detection development as indicated by those controls (general IHC practice). Score only cellular signal with a discernible location.
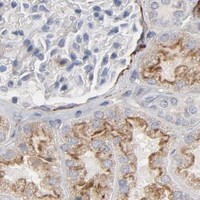
Only weak staining is seen in a selected region.HPA reports different levels by population: kidney tubular cells and ovarian stroma cells are Medium, while some brain and epithelial populations are Low (HPA tissue IHC). Weakness alone does not establish assay failure.Identify the population and compare it with a High reference in the same run (HPA tissue IHC; general IHC practice). Interpret intensity by cell type and keep the HPA reliability caveat in the report.
A section shows cytoplasmic signal without a crisp membrane outline.HPA explicitly describes membranous and cytoplasmic tissue expression, while UniProt annotates GNG2 at the cell membrane (HPA tissue IHC; UniProt P59768). Cytoplasmic staining alone therefore needs context, not automatic rejection.Assess whether signal follows the reported positive population, check background controls, and avoid claiming a precise compartment from diffuse chromogenic colour (HPA tissue IHC; general IHC practice).

Sample controls for GNG2 IHC & IF

🧪Run adipose tissue first and look for staining in adipocytes (HPA: High in adipocytes). Use duodenal glandular cells as a negative tissue comparator (HPA: Not detected in duodenal glandular cells); on the adipose slide, count non-adipocyte cells as internal negatives only if their signal matches the no-primary background, because their GNG2 status is not specified by the adipocyte row (HPA: High in adipocytes).
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: Adrenal gland (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show GNG2 in A-431, U-251MG, U2OS, with annotated localisation: Plasma membrane (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and concentration-matched nonimmune rabbit IgG controls (selected-SKU caption: rabbit primary antibody); a matched GNG2 knockout specimen, if available, provides a biological negative. Quench endogenous peroxidase and check endogenous biotin background when using the caption’s biotin–streptavidin/DAB detection (selected-SKU caption: biotinylated secondary and streptavidin–biotin complex).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact selected-SKU tissue-IHC caption does not state the fixative (selected-SKU caption: fixative not stated). The demonstrated paraffin-section procedure used heat retrieval in EDTA at pH 8.0, but whether GNG2 staining requires that retrieval condition is unreported (selected-SKU caption: heat-mediated EDTA retrieval). HPA places GNG2 mainly at the plasma membrane, with additional vesicular signal in ICC-IF, but the supplied evidence does not establish that frozen sections or IF are easier than paraffin IHC (HPA: subcellular summary); in adipose sections, distinguish specific adipocyte staining from empty lipid spaces caused by routine paraffin processing (standard IHC practice).

HPA tissue IHC evidence for GNG2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Antibody staining in cells/structures not annotated, view images. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Cerebral cortex Neuropil High Protein (IHC) HPA →
Smooth muscle Smooth muscle cells High Protein (IHC) HPA →
Breast Adipocytes Medium Protein (IHC) HPA →
Kidney Cells in tubules Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Duodenum Glandular cells Not detected Protein (IHC) HPA →
Fallopian tube Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced GNG2 IHC Tips

Use compartment-aware controls and the catalog antibody’s documented paraffin-section conditions when troubleshooting GNG2 chromogenic IHC (UniProt P59768; caption A06975-1).

How should I adjust retrieval when GNG2 staining is weak in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A06975-1). The documented paraffin-section example then used 10% goat serum and 2 µg/mL primary antibody overnight at 4°C (caption A06975-1). If staining remains weak, vary heating time on adjacent sections while holding antibody concentration and detection conditions constant (standard IHC practice). Include a positive-reference section and a no-primary control in each comparison so increased signal can be distinguished from increased background (standard IHC practice). The example reports paraffin embedding but does not state its fixative, which limits direct comparison with differently processed sections (caption A06975-1).
Could fixation explain inconsistent GNG2 staining between specimens?
Target-specific fixation sensitivity is unknown because the selected paraffin-section caption does not identify a fixative (caption A06975-1). Record fixation type and duration for each specimen, then compare sections processed and stained together before attributing differences to GNG2 abundance (standard IHC practice). Keep retrieval at EDTA pH 8.0 and the primary antibody at 2 µg/mL for an initial controlled comparison (datasheet A06975-1; caption A06975-1). If signal differs between fixation batches, test matched reference material across batches and examine morphology alongside staining (standard IHC practice). Neither the reported tissue staining nor GNG2 membrane localisation establishes how this epitope responds to fixation (HPA tissue IHC; UniProt P59768).
Where should convincing GNG2 staining appear in tissue sections?
Prioritise membranous signal, while allowing some cytoplasmic signal, because the tissue profile reports both and UniProt places GNG2 at the cell membrane (HPA tissue IHC; UniProt P59768). GNG2 has no annotated transmembrane segment, so a membrane pattern does not by itself establish antibody specificity (UniProt P59768 topology; standard IHC practice). Compare staining with cell boundaries and the counterstain at high magnification; diffuse precipitate obscuring those boundaries warrants caution (standard IHC practice). For a reference, the tissue atlas reports high signal in cerebral-cortex neuropil and smooth muscle cells, with uncertain staining reliability overall (HPA tissue IHC). Score membrane and cytoplasmic patterns separately across matched sections (standard IHC practice).
How can I assess whether the antibody recognises a processing-sensitive GNG2 epitope?
The supplied record annotates 0 isoforms and a mature chain spanning residues 2–68; its terminal propeptide spans residues 69–71 (UniProt P59768). It also lists N-acetylalanine at residue 2 and a cysteine methyl ester at residue 68 (UniProt P59768). The antibody epitope is not specified in the supplied caption, so these annotations cannot identify which processing event would affect staining (caption A06975-1; UniProt P59768). Ask for epitope mapping or validate specificity with a suitable GNG2-depleted control before assigning a weak result to processing (standard IHC practice). Compare adjacent sections under identical retrieval and detection conditions when assessing a suspected epitope effect (standard IHC practice).
How could I corroborate a GNG2 IHC pattern with multiplex IF?
Use IF as a separate corroborating assay and include a marker identifying the expected cell population, such as a validated smooth-muscle-cell marker when examining smooth muscle (HPA tissue IHC; standard IF practice). Choose fluorophores after inspecting unstained tissue autofluorescence, favouring a channel with clear separation from that background (standard IF practice). HPA reports plasma-membrane localisation with additional vesicular localisation, but the antibody epitope’s side of the membrane is unspecified (HPA subcellular; caption A06975-1). Compare mild permeabilisation with an unpermeabilised condition rather than assuming an intracellular epitope is accessible (standard IF practice). Use the documented 2 µg/mL concentration only as an IHC reference, then optimise IF independently with appropriate single-label controls (caption A06975-1; standard IF practice).
What should I check when DAB obscures GNG2-positive structures?
Run a no-primary control to reveal detection-system background and inspect unstained or counterstained sections for pigment that could resemble DAB (standard IHC practice). The documented workflow uses biotinylated secondary antibody, a streptavidin-biotin complex and DAB, making a biotin-system control useful when background persists (caption A06975-1; standard IHC practice). Apply a peroxidase block before chromogenic detection and assess whether reducing development time improves contrast without losing the reference signal (standard IHC practice). Reassess the documented 10% goat-serum block and 2 µg/mL primary concentration before increasing antibody exposure (caption A06975-1). Judge any improvement against tissue architecture and the no-primary section stained in the same run (standard IHC practice).
How should I quantify GNG2 IHC across heterogeneous tissue? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because reported GNG2 staining is membranous and cytoplasmic across multiple tissue structures (HPA tissue IHC). Within each annotated region, report the percentage of positive cells and a prespecified intensity score, or calculate an H-score from those observations (standard IHC practice). For sparse positive structures, report positive-cell density per mm² of viable, analysable tissue rather than per whole image (standard IHC practice). Keep section thickness, retrieval at pH 8.0, staining batch and image exposure comparable across groups (datasheet A06975-1; standard IHC practice). Normalise counts to the corresponding viable cell population or tissue area and document exclusions before comparing specimens (standard IHC practice).
Which patterns would make a GNG2-positive IHC result questionable?
A credible pattern should follow cell membranes or plausible cytoplasmic structures, consistent with the tissue profile and reported plasma-membrane localisation (HPA tissue IHC; HPA subcellular). Interpret staining in the expected cell population: the atlas reports high signal in smooth muscle cells and cerebral-cortex neuropil but labels its tissue staining reliability uncertain (HPA tissue IHC). Strong nuclear-only staining, section-edge concentration or staining confined to necrotic regions warrants review of morphology and controls (UniProt P59768; standard IHC practice). Check a no-primary section for endogenous enzyme or detection background before calling DAB deposits positive (standard IHC practice). Confirm the pattern in independently processed sections and interpret negative cells within their annotated tissue context (standard IHC practice; HPA tissue IHC).
Boster reagents

Best GNG2 / Guanine nucleotide-binding protein G(I)/G(S)/G(O) subunit gamma-2 IHC Antibodies

Validated anti-GNG2 antibodies have IHC images from human paraffin sections and an IF image from human cells (catalog image captions); catalog reactivity spans human, mouse and rat (catalog reactivity).

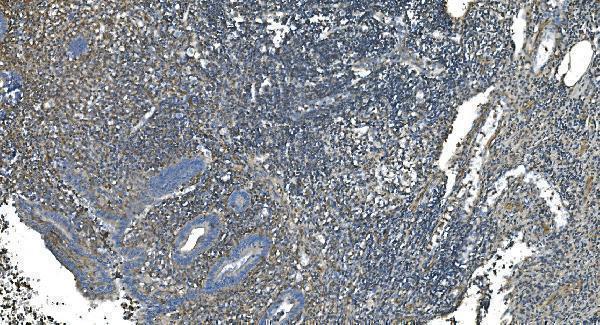
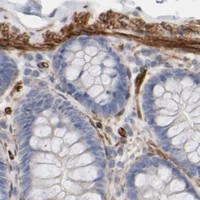
Real IHC data IHC analysis of GNG2 using anti-GNG2 antibody (A06975-1). GNG2 was detected in paraffin-embedded section of human appendicitis tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml rabbit anti-GNG2 Antibody (A06975-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-GNG2 Antibody ®
Cat # A06975-1
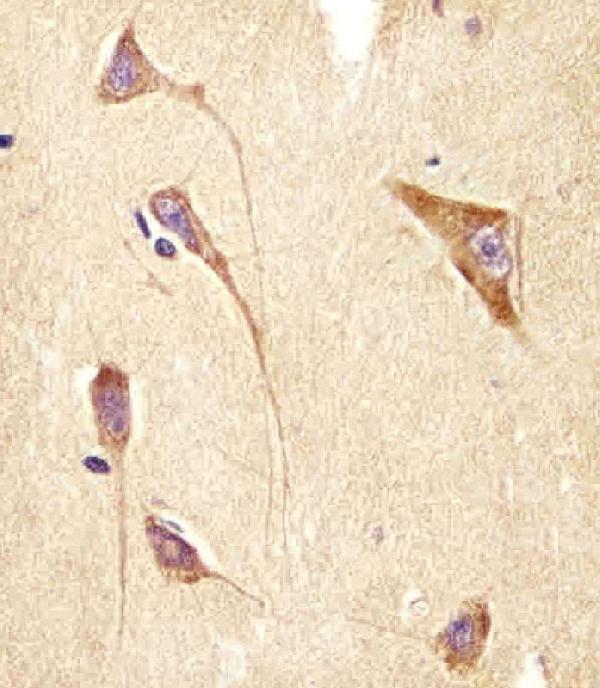
Real IHC data M06975 staining GNG2 in human brain tissue sections by Immunohistochemistry (IHC-P -paraformaldehyde-fixed, paraffin-embedded sections). Tissue was fixed with formaldehyde and blocked with 3% BSA for 0. 5 hour at room temperature; antigen retrieval was by heat mediation with a citrate buffer (pH6). Samples were incubated with primary antibody (1/25) for 1 hours at 37°C. A undiluted biotinylated goat polyvalent antibody was used as the secondary antibody.
Anti-GNG2 Antibody (N-Term)
Cat # M06975
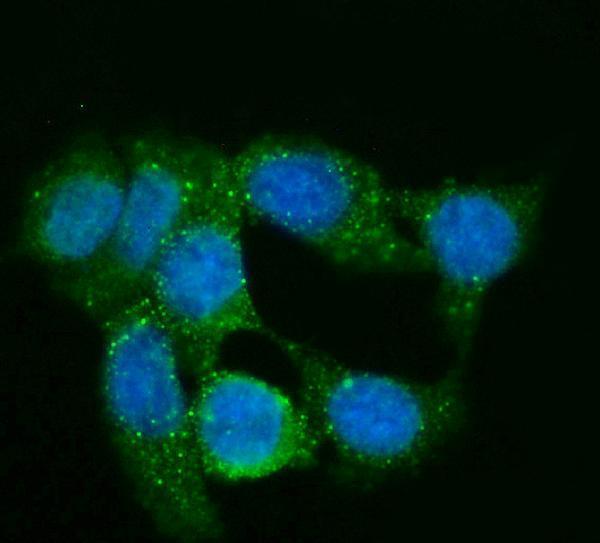
Real IF data IF analysis of GNG2 using anti-GNG2 antibody (M06975-1). GNG2 was detected in an immunocytochemical section of Caco-2 cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5 μg/mL mouse anti-GNG2 Antibody (M06975-1) overnight at 4°C. DyLight®488 Conjugated Goat Anti-Mouse IgG (BA1126) was used as secondary antibody at 1:100 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-GNG2 Antibody ® (monoclonal, 7C13)
Cat # M06975-1

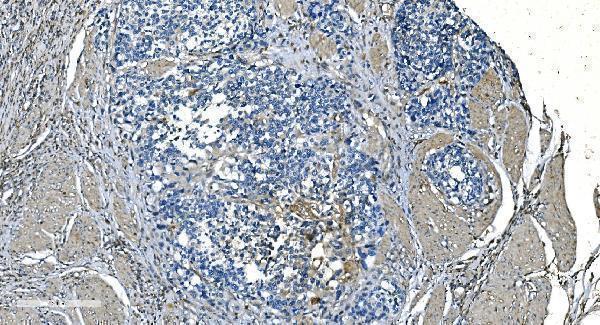
A06975-1 has IHC images from human appendicitis, bladder cancer and lung cancer paraffin sections; M06975 has an IHC image from human brain paraffin sections (catalog image captions). M06975-1 has an IF/ICC image from Caco-2 cells (catalog image caption).

Which to pick: For tissue IHC, choose A06975-1 for human paraffin sections; its caption does not report the fixative (A06975-1 IHC caption). M06975 is another tissue option with an image from paraffin-section human brain paraffin sections (M06975 IHC caption). For IF/ICC, choose mouse monoclonal M06975-1, which has a Caco-2 IF image (catalog clone and M06975-1 IF caption); for cross-species planning, A06975-1 lists human, mouse and rat reactivity, though its documented IHC images are human only (catalog reactivity; A06975-1 IHC captions). The selected A06975-1 tissue-IHC caption documents paraffin sections, but does not specify the fixative (selected-SKU IHC image A06975-1).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P59768 (GBG2_HUMAN, Guanine nucleotide-binding protein G(I)/G(S)/G(O) subunit gamma-2).
  2. Human Protein Atlas. GNG2 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. GNG2 subcellular location (ICC-IF): Mainly localized to the plasma membrane. In addition localized to vesicles..
  4. Human Protein Atlas. GNG2 antibody validation summary (2 antibodies).
  5. The Anatomical Boundary of the Rat Claustrum. Frontiers in neuroanatomy 2019 — PMC6555083.
  6. Topography of Gng2- and NetrinG2-expression suggests an insular origin of the human claustrum. PloS one 2012 — PMC3434180.
  7. The role of Tec kinase signaling pathways in the development of Mallory Denk Bodies in balloon cells in alcoholic hepatitis. Experimental and molecular pathology 2017 — PMC5680109.
  8. The claustrum of the bottlenose dolphin Tursiops truncatus (Montagu 1821). Frontiers in systems neuroscience 2014 — PMC3975097.
  9. PubMed PMID:10833460 — UniProt-cited evidence.
  10. PubMed PMID:17974005 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.