GOLPH3 / Golgi phosphoprotein 3 · IHC design guide

Design Immunohistochemistry for GOLPH3

Plan GOLPH3 staining in paraffin sections using the catalog antibody at 2–5 μg/mL (datasheet A01333-1). Compare the observed signal with the Golgi-like cytoplasmic pattern reported in tissue IHC (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
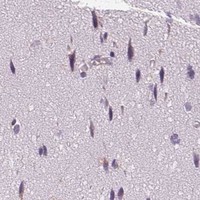
Immunohistochemistry protocol sheet for GOLPH3 (IHC for GOLPH3): expected localisation Golgi-like cytoplasm in several tissues (HPA tissue IHC), antibody A01333-1, validated IHC image, and IHC protocol steps
Printable GOLPH3 IHC protocol sheet — expected localisation Golgi-like cytoplasm in several tissues (HPA tissue IHC), antibody A01333-1, controls and protocol steps. Open the full GOLPH3 IHC guide →

GOLPH3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Golgi-like cytoplasm in several tissues (HPA tissue IHC)
Staining pattern Golgi-like cytoplasmic staining in glandular cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01333-1)
Positive control ⓘ Stomach+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Staining and RNA show only medium consistency (HPA tissue IHC)
Regulation Detected in diseased muscle fibers (UniProt)
Isoform / epitope No annotated isoforms; one 1–298 chain (UniProt)
Section 1

Recommended GOLPH3 IHC & IF Protocols

The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet A01333-1). Four published GOLPH3 IHC protocols provide tissue-specific examples (PMC4007226; PMC3480894; PMC5624675; PMC5356558).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human intestinal cancer tissue; fixative not specified (datasheet A01333-1)
FixationImage fixative and duration unreported (datasheet A01333-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01333-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01333-1)
Primary antibodyRabbit anti-GOLPH3, 2-5μg/ml (datasheet A01333-1)
Primary incubationOvernight at 4 °C (datasheet A01333-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A01333-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultGOLPH3-positive staining in glandular cells of stomach (HPA tissue IHC: High). HPA tissue profile: Golgi-like cytoplasmic expression in several tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A01333-1); published alternatives include citrate pH 6.0 (PMC4007226; PMC5624675).
Section 2

What Is the Expected GOLPH3 Staining Pattern?

GOLPH3 should appear as Golgi-like cytoplasmic staining in several tissues, including stomach glandular cells with high staining and glandular cells in several other listed tissues with medium staining (HPA tissue IHC). It associates with Golgi membranes without a transmembrane segment (UniProt Q9H4A6 topology and localization). HPA rates the tissue staining Approved, with medium consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Compact, Golgi-like cytoplasmic staining in stomach glandular cells.This matches the reported compartment and a high staining example (HPA tissue IHC). Judge the pattern within identifiable glandular cells, not by the overall darkness of the section (standard IHC practice).
Signal appears predominantly nuclear, along cell borders, or uniformly throughout the cytoplasm.These patterns diverge from the reported Golgi-like tissue pattern (HPA tissue IHC) and Golgi localization (UniProt Q9H4A6). Check morphology and controls before interpreting them as GOLPH3; compartment mismatch alone does not identify the cause (standard IHC practice).
Strong staining appears in a cell population listed as not detected, such as adipocytes in adipose tissue.That result conflicts with the listed HPA observation for that cell type (HPA tissue IHC). Investigate cross-reactivity or endogenous detection activity with appropriate controls; an HPA ‘not detected’ entry is a comparator, not proof that every specimen must be negative (standard IHC practice).
Diffuse color obscures cell boundaries or appears across unrelated structures.The distribution is difficult to reconcile with a Golgi-like intracellular pattern (HPA tissue IHC). Background from staining or detection may be involved; compare with a negative reagent control and assess whether discrete intracellular signal remains (standard IHC practice).
No discernible signal appears in stomach glandular cells.Stomach glandular cells are a reported high staining example (HPA tissue IHC). Recheck tissue identity, antibody conditions, detection reagents, and the run’s positive control before calling the sample negative (standard IHC practice).
💡Expected GOLPH3 appearanceCall a section positive when identifiable glandular cells show discrete Golgi-like cytoplasmic staining, strongest in the listed stomach example; predominant nuclear or uniform tissue-wide color warrants investigation (HPA tissue IHC; UniProt Q9H4A6 localization; standard IHC practice).
How each factor affects the staining
Tissue and cell choiceHPA reports high staining in stomach glandular cells and medium staining in glandular cells of adrenal gland, appendix, breast, cervix, colon, and endometrium (HPA tissue IHC). Use the named cell population when judging a section; neighboring cells need not share its rating (standard IHC practice).
Reference negatives and weak comparatorsHPA lists adipocytes in adipose tissue and squamous epithelial cells in esophagus as not detected, while thyroid glandular cells are low (HPA tissue IHC). These are cell-specific observations; weak or absent staining in an unlisted specimen cannot be predicted from them (HPA tissue IHC).
Localization and topologyGOLPH3 is reported at Golgi stack and trans-Golgi network membranes and has no transmembrane segment (UniProt Q9H4A6 topology and localization). Its expected tissue appearance is Golgi-like cytoplasmic staining, not a required continuous cell-membrane outline (HPA tissue IHC; UniProt Q9H4A6).
Antibody evidenceBoth listed antibodies, HPA044564 and HPA055841, have Approved IHC status (HPA antibodies). The tissue profile has medium consistency with RNA expression (HPA tissue IHC). Interpret an unusual pattern with the cell-specific reference and controls; Approved status does not establish that every stained structure is specific (standard IHC practice).
IF/ICC Q: Where should GOLPH3 appear?A: HPA supports Golgi apparatus and vesicle localization in ICC-IF images; the supplied image list includes A-431, U-251MG, U2OS, and NIH 3T3 (HPA subcellular). This is localization context for IF/ICC, not an IHC staining intensity prediction (HPA subcellular; HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Stomach glandular cells lack visible staining.The result differs from HPA’s high stomach glandular-cell observation; the section or staining run may have failed (HPA tissue IHC; standard IHC practice).Confirm the glandular cells are present, check the run’s positive control and detection reagents, and optimize IHC conditions using the known-positive tissue (standard IHC practice).
Staining is mostly nuclear or outlines cell borders.The compartment differs from the Golgi-like tissue profile and Golgi membrane localization; its cause cannot be assigned from appearance alone (HPA tissue IHC; UniProt Q9H4A6).Review cellular morphology and compare a matched negative reagent control before scoring the unexpected compartment as specific (standard IHC practice).
Color is diffuse across the section.Widespread background may obscure the discrete Golgi-like cytoplasmic pattern reported by HPA (HPA tissue IHC; standard IHC practice).Compare negative controls, inspect blocking and wash performance, and reassess whether signal is confined to identifiable cells (standard IHC practice).
Cells listed as not detected show strong signal.The result conflicts with that cell-specific HPA observation; cross-reactivity or endogenous detection activity is possible (HPA tissue IHC; standard IHC practice).Verify cell identity and use controls that assess primary-antibody dependence and endogenous detection activity before interpreting the signal (standard IHC practice).
Only faint staining is seen in thyroid glandular cells.HPA lists this population as low, so weak signal can fit its reported tissue profile (HPA tissue IHC).Compare it with a stronger reference, such as stomach glandular cells, in the same staining run before changing conditions (HPA tissue IHC; standard IHC practice).
A change in antigen retrieval appears to alter staining.Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.Assess retrieval conditions against matched positive tissue, morphology, and controls; report the observed effect for the tested conditions without attributing it to a known GOLPH3 fixation mechanism (standard IHC practice).

Sample controls for GOLPH3 IHC & IF

🧪Run stomach first: its glandular cells should stain (HPA: stomach glandular cells High). Use adipose tissue adipocytes as the negative tissue (HPA: adipocytes Not detected); on the stomach slide, score other cells as internal negative comparators only if they are unstained, since their GOLPH3 status is not specified by the supplied HPA row.
Positive control tissue: Stomach (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show GOLPH3 in A-431, U-251MG, U2OS, NIH 3T3, with annotated localisation: Golgi apparatus (supported), Vesicles (supported) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, a control using nonimmune rabbit IgG matched to the primary antibody, and a GOLPH3 knockout sample or peptide-block control if available (caption: rabbit primary antibody; standard IHC controls). Block endogenous peroxidase before chromogenic detection and check for residual background in the stomach section (caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A01333-1 paraffin-section caption does not state the fixative (caption: fixative unreported). The caption documents heat retrieval in EDTA at pH 8.0, but does not establish whether retrieval is required (caption: EDTA heat retrieval). Whether frozen sections or IF are easier is unreported; assess stomach background with the peroxidase control when interpreting glandular staining (caption: HRP/DAB detection; standard IHC practice).

HPA tissue IHC evidence for GOLPH3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Stomach Glandular cells High Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →
Bronchus Ciliated cells (cell body) Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Cerebral cortex Endothelial cells Not detected Protein (IHC) HPA →
Esophagus Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced GOLPH3 IHC Tips

Use GOLPH3’s Golgi-like pattern and documented paraffin-section conditions to troubleshoot chromogenic IHC; assess IF separately.

Which retrieval conditions should I try first for weak GOLPH3 staining in paraffin sections?
Start with heat-mediated antigen retrieval in EDTA buffer at pH 8.0 for paraffin sections (datasheet A01333-1). The selected tissue image used that retrieval condition before staining with 2 μg/ml primary antibody overnight at 4°C (caption A01333-1). If signal is weak, first check complete deparaffinization and compare retrieval duration across adjacent sections while keeping antibody concentration and DAB development constant (standard IHC practice). Include a section with expected Golgi-like staining, such as stomach glandular cells, to distinguish retrieval failure from a low-expressing specimen (HPA tissue IHC: high in stomach glandular cells).
Could fixation explain weak or patchy GOLPH3 staining?
Target-specific sensitivity to fixation is unknown: the selected paraffin-section caption does not state a fixative (caption A01333-1). Record fixative, fixation duration, processing history, and section age for each specimen, then compare sections processed alike before changing antibody conditions (standard IHC practice). If fixation varies between cases, assess staining in a comparably processed positive tissue alongside each run; stomach glandular cells are a documented high-expression reference (HPA tissue IHC). Keep the reported EDTA pH 8.0 retrieval and 2 μg/ml overnight primary incubation constant during that comparison so differences are easier to attribute (caption A01333-1).
What cellular pattern should count as plausible GOLPH3 staining?
Look primarily for a compact, Golgi-like cytoplasmic pattern in intact cells (HPA tissue IHC: Golgi-like expression; HPA subcellular: Golgi apparatus and vesicles). GOLPH3 associates with Golgi stack and trans-Golgi network membranes through phosphatidylinositol 4-phosphate binding and oligomerization, despite having no transmembrane segment (UniProt Q9H4A6). Compare staining with cell boundaries and a nuclear counterstain; a perinuclear focus is more interpretable than uniform nuclear color (standard IHC practice). Document vesicular or diffuse cytoplasmic staining separately, because endosome, cell membrane, and mitochondrial intermembrane-space locations are also annotated and morphology alone cannot establish which compartment is stained (UniProt Q9H4A6).
How should I investigate an unexpected staining pattern when the antibody epitope is unspecified?
The record lists 0 isoforms and one chain spanning residues 1–298, so an alternate annotated isoform does not explain a second pattern (UniProt Q9H4A6). It lists no transmembrane segment or glycosylation sites, but does list phosphoserines at positions 35 and 36 (UniProt Q9H4A6). Because the catalog antibody’s epitope is unspecified here, do not assume those modifications alter its IHC signal or predict which side of a membrane it recognizes. Compare serial sections with an independently validated antibody against a disclosed epitope, and retain compartment-level images when judging agreement (standard IHC practice).
How can IF help resolve the compartment producing GOLPH3 IHC signal?
Use IF as a separate localization check, pairing GOLPH3 with a Golgi marker and a marker for the expected cell type, such as a glandular epithelial marker in glandular tissue (HPA tissue IHC: glandular-cell staining; HPA subcellular: Golgi apparatus). Choose a far-red fluorophore when tissue autofluorescence obscures shorter-wavelength channels, and inspect single-channel controls before interpreting overlap (standard IF practice). For an intracellular epitope, titrate gentle permeabilization, but confirm epitope accessibility experimentally because this antibody’s epitope is unspecified; GOLPH3 has no transmembrane segment (UniProt Q9H4A6). Record Golgi and vesicle signals separately, as both locations have supported IF evidence (HPA subcellular).
What should I check when DAB obscures the expected Golgi-like pattern?
First inspect a no-primary control for endogenous peroxidase and detection-reagent signal, then apply a peroxidase block where needed (standard chromogenic IHC practice). The selected image used 10% goat-serum blocking, a peroxidase-conjugated anti-rabbit secondary for 30 minutes at 37°C, and DAB development (caption A01333-1). If staining remains diffuse, compare shorter DAB development or a lower primary concentration across adjacent sections while preserving the same retrieval conditions (standard IHC practice). Judge improvement by clearer Golgi-like cytoplasmic staining, rather than by darker total color; that pattern is reported in tissues (HPA tissue IHC).
How should I score GOLPH3 across cases with different cell composition? ⚠ ANSWER MARKED FOR VERIFICATION
Score viable cells in a predefined compartment and report both the percentage positive and staining intensity; an H-score from 0–300 can combine them (standard IHC scoring practice). Normalize to the number of evaluable cells of the same type, rather than total section area, when glandular and stromal proportions differ (standard IHC practice). Annotate Golgi-like cytoplasmic staining separately from diffuse staining because the former is the reported tissue pattern (HPA tissue IHC). Use identical retrieval, imaging, and DAB development settings across cases, and exclude folds, necrosis, and tissue edges from the scored region (standard IHC practice).
How can I distinguish convincing GOLPH3 staining from artefact?
A convincing result shows reproducible Golgi-like cytoplasmic staining in intact cells, consistent with the tissue pattern and supported Golgi localization (HPA tissue IHC; HPA subcellular). Check the cell type: stomach glandular cells show high staining, whereas adipocytes and esophageal squamous epithelial cells were not detected in the listed tissue observations (HPA tissue IHC). Treat staining confined to section edges, folds, or necrotic areas as suspect, and use a no-primary control to identify endogenous peroxidase or detection background (standard IHC practice). Do not dismiss every non-Golgi punctum automatically, because vesicles and endosomes are also documented locations (HPA subcellular; UniProt Q9H4A6).
Boster reagents

Best GOLPH3 / Golgi phosphoprotein 3 IHC Antibodies

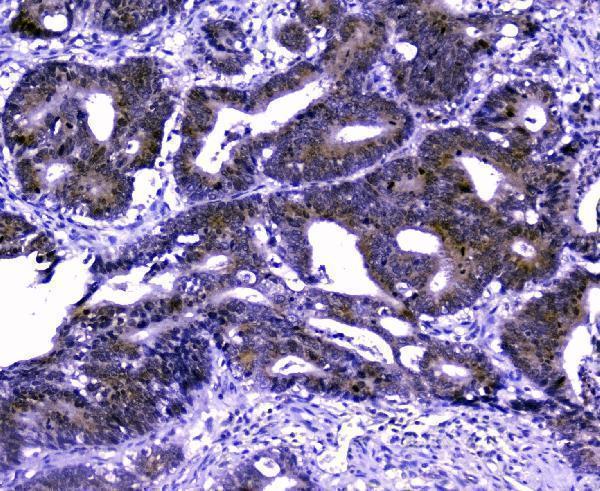
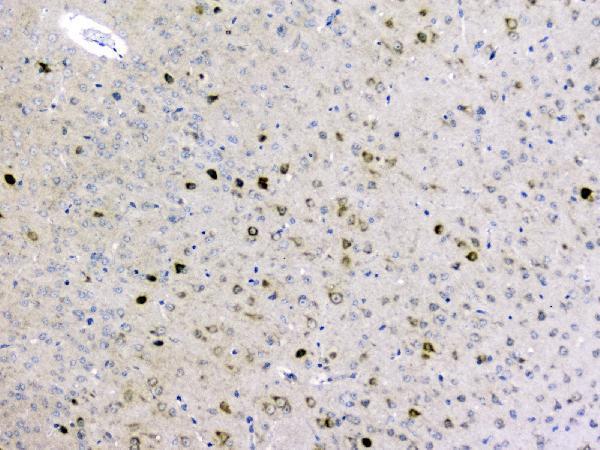
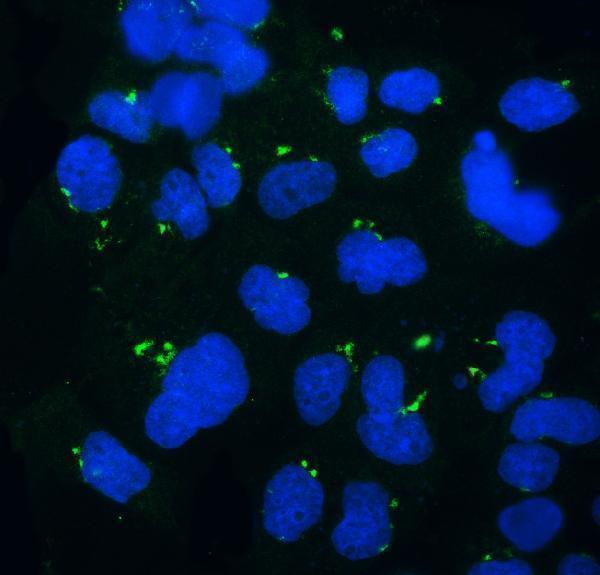
Anti-GOLPH3 antibodies have illustrated IHC data from human intestinal cancer, mouse brain and rat brain paraffin sections (A01333-1 IHC captions), and IF data from A431 and rat lung cells (A01333-1 and A01333 IF captions).

Real IHC data IHC analysis of GOLPH3 using anti-GOLPH3 antibody (A01333-1). GOLPH3 was detected in a paraffin-embedded section of human intestinal cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-GOLPH3 Antibody (A01333-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-GOLPH3 Antibody ®
Cat # A01333-1
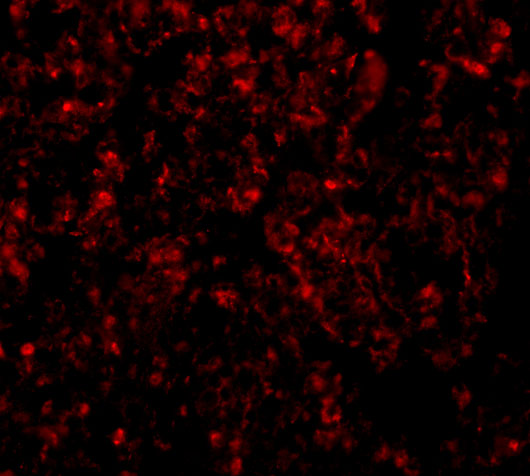
Real IF data Immunofluorescence of GOLPH3 in Rat Lung cells with GOLPH3 antibody at 20 μg/mL.
Anti-Golgi phosphoprotein 3 GOLPH3 Antibody
Cat # A01333

A01333-1 has IHC images from human intestinal cancer, mouse brain and rat brain paraffin sections, plus an IF image from A431 cells (A01333-1 image captions). A01333 has an IF image from rat lung cells; its application list does not include IHC (A01333 IF caption; catalog applications).

Which to pick: Choose A01333-1 for tissue IHC: its paraffin-section captions document human, mouse and rat samples, with 2 μg/mL primary antibody, EDTA retrieval at pH 8.0 and DAB detection; the fixative is unreported (A01333-1 IHC captions). For IF/ICC, A01333-1 lists both applications and shows A431 cell IF, while A01333 lists IF and shows rat lung cell IF (catalog applications; A01333-1 and A01333 IF captions). For IHC across the three illustrated species, select A01333-1; both antibodies are rabbit antibodies with no clone reported, so clonality does not distinguish them (A01333-1 IHC captions; catalog host and clone fields).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9H4A6 (GOLP3_HUMAN, Golgi phosphoprotein 3).
  2. Human Protein Atlas. GOLPH3 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. GOLPH3 subcellular location (ICC-IF): Localized to the Golgi apparatus and vesicles..
  4. Human Protein Atlas. GOLPH3 antibody validation summary (2 antibodies).
  5. GOLPH3 is a novel marker of poor prognosis and a potential therapeutic target in human renal cell carcinoma. British journal of cancer 2014 — PMC4007226.
  6. GOLPH3 overexpression correlates with tumor progression and poor prognosis in patients with clinically N0 oral tongue cancer. Journal of translational medicine 2012 — PMC3480894.
  7. GOLPH3 and YB-1 Are Novel Markers Correlating With Poor Prognosis in Prostate Cancer. World journal of oncology 2015 — PMC5624675.
  8. GOLPH3 overexpression correlates with poor response to neoadjuvant therapy and prognosis in locally advanced rectal cancer. Oncotarget 2016 — PMC5356558.
  9. PubMed PMID:11042173 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:16710414 — UniProt-cited evidence.