This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan HSPH1 chromogenic IHC on paraffin sections using its expected cytoplasmic location and tissue staining profile (UniProt; HPA tissue IHC). The guide highlights controls and interpretation limits because the HPA rates its tissue staining evidence uncertain (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining in most tissues (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining in glandular and neuronal cells (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet M04168) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image M04168) | |
| Caveat | Staining has very low concordance with RNA data (HPA tissue IHC) | |
| Regulation | Overexpressed in cancer cells (UniProt) | |
| Isoform / epitope | 4 isoforms; epitope coverage is unknown (UniProt; datasheets) |
The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet M04168). Three published HSPH1 IHC protocols cover esophageal, liver, and head and neck tissues (PMC13339864; PMC12375714; PMC6139602).
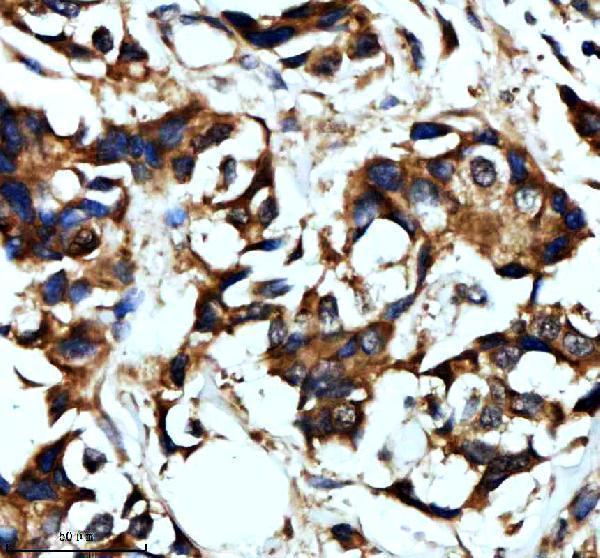
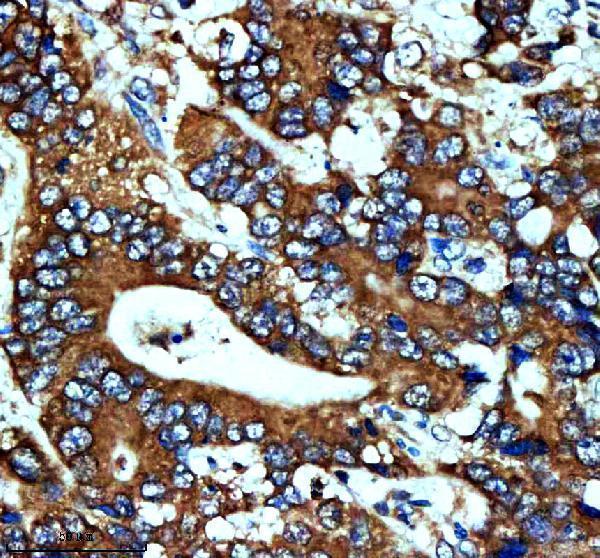
| Sample | Paraffin-embedded human breast cancer tissue; fixative not specified (datasheet M04168) |
| Fixation | Image fixative and duration unreported (datasheet M04168); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet M04168); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet M04168) |
| Primary antibody | Rabbit monoclonal (clone IOG-8) anti-HSPH1, 1:50 (datasheet M04168) |
| Primary incubation | Overnight at 4 °C (datasheet M04168) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet M04168) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | HSPH1-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control. |
HSPH1 should appear mainly in the cytoplasm, with high staining reported in selected glandular, respiratory epithelial and neuronal cells (HPA: tissue IHC; UniProt Q92598: cytoplasm). It has no transmembrane segment (UniProt Q92598: topology). Treat tissue intensity as provisional: HPA rates its tissue IHC profile Uncertain because antibody staining and RNA expression show very low consistency (HPA: tissue IHC reliability).
| Cytoplasmic staining is strong in appendix or colon glandular cells, bronchial respiratory epithelial cells, or neurons in caudate or cerebral cortex (HPA: High in these cells). | This matches the reported compartment and selected high-staining cell populations (HPA: tissue IHC; UniProt Q92598: cytoplasm). Compare cell-level staining with a matched negative control; HPA's Uncertain IHC rating limits how confidently intensity alone identifies HSPH1 (HPA: tissue IHC reliability; general IHC practice). |
| Staining is confined to nuclei, without convincing cytoplasmic signal (HPA: cytoplasmic tissue profile). | A nuclear-only IHC result conflicts with the expected predominant cytoplasmic pattern (HPA: tissue IHC; UniProt Q92598: cytoplasm). Limited nucleoplasmic signal is possible in ICC-IF (HPA: additional nucleoplasm), so assess the staining distribution and controls before calling a nuclear signal artefactual (general IHC practice). |
| Adipocytes, cardiomyocytes or skeletal myocytes stain strongly while the expected cytoplasmic positive cells do not (HPA: Not detected in these cell types). | This reverses HPA's reported cell-type contrast and raises concern about cross-reactivity or endogenous chromogenic activity (HPA: tissue IHC; general IHC practice). HPA's Uncertain reliability means a single discordant specimen cannot establish true absence or presence (HPA: tissue IHC reliability). |
| Diffuse colour covers tissue and blank spaces, obscuring cell boundaries (general IHC practice). | This distribution is hard to score as cellular HSPH1 staining; nonspecific reagent binding or excess chromogen development may contribute (general IHC practice). Examine the negative control and identify whether colour follows cells, tissue edges or the whole section (general IHC practice). |
| No cytoplasmic signal appears in glandular cells of appendix or colon, or bronchial respiratory epithelial cells (HPA: High in these cells). | A technical loss of signal is possible, but HPA's tissue IHC profile is Uncertain (HPA: tissue IHC reliability). Confirm tissue preservation, the antibody's IHC-P instructions, detection reagents and a suitable control before interpreting a blank section as HSPH1 absence (general IHC practice). |
| Tissue and cell population (HPA: tissue IHC) | HPA reports High staining in selected glandular, respiratory epithelial and neuronal cells, but Not detected in adipocytes, cardiomyocytes and skeletal myocytes (HPA: tissue IHC). Interpret these as reported contrasts, subject to HPA's Uncertain IHC reliability (HPA: tissue IHC reliability). |
| Antibody evidence (HPA: antibody validation) | The two HPA antibodies with an IHC status are both rated Uncertain, while the ICC-IF ratings are Enhanced or Approved (HPA: HPA028675, CAB002060, HPA031569). ICC-IF validation does not resolve the uncertainty of tissue IHC (HPA: antibody validation). |
| Compartment and processing (UniProt Q92598) | HSPH1 is cytoplasmic, has no transmembrane segment and has no signal peptide or propeptide annotation (UniProt Q92598: subcellular location, topology, processing). An isolated membrane rim or secreted-looking deposit would therefore need control-based review (general IHC practice). |
| Isoforms and antibody recognition (UniProt Q92598) | Four isoforms are listed—Alpha, Beta, 3 and 4 (UniProt Q92598: isoforms). The payload gives no antibody epitope, so it cannot establish which isoforms the catalog antibody detects; avoid attributing staining differences to a particular isoform (UniProt Q92598: isoforms; supplied antibody data). |
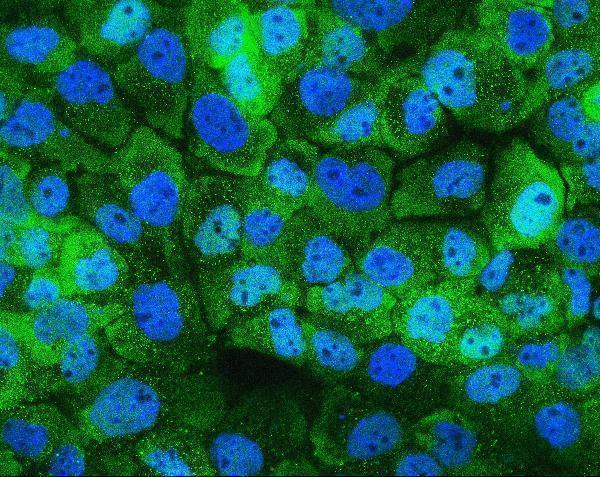
| IF/ICC interpretation (HPA: subcellular ICC-IF) | For the separate IF/ICC guide, HPA reports mainly cytosolic signal with additional nucleoplasmic localisation (HPA: subcellular ICC-IF). This supports checking both compartments in cell images, without treating the IF pattern as proof of tissue IHC specificity (HPA: antibody validation). |
| Situation | Likely cause | Next action |
|---|---|---|
| The presumed positive tissue is blank (HPA: High in selected cells). | The specimen or IHC workflow may have failed, or the selected field may lack the reported positive cell population (general IHC practice; HPA: tissue IHC). | Locate the named cell population, inspect morphology and controls, then check the catalog antibody's IHC-P instructions and detection steps (general IHC practice). Keep HPA's Uncertain tissue rating in mind (HPA: tissue IHC reliability). |
| Nuclei stain more strongly than cytoplasm in tissue (HPA: cytoplasmic tissue profile). | The pattern is discordant with predominant cytoplasmic HSPH1 in tissue; ICC-IF nevertheless reports additional nucleoplasmic localisation (HPA: tissue IHC; HPA: subcellular ICC-IF). | Review whether cytoplasm is also stained, compare a negative control and repeat assessment in a reported positive cell population before assigning localisation (general IHC practice; HPA: tissue IHC). |
| Cells reported as Not detected stain strongly (HPA: adipocytes, cardiomyocytes or skeletal myocytes). | Cross-reactivity or endogenous detection activity may mimic target staining (general IHC practice); HPA's tissue rating remains Uncertain (HPA: tissue IHC reliability). | Compare matched negative controls and the cell-by-cell pattern in reported High and Not detected populations; avoid calling the unexpected signal HSPH1 from intensity alone (general IHC practice; HPA: tissue IHC). |
| Diffuse colour obscures cells (general IHC practice). | Nonspecific binding, endogenous detection activity or overdevelopment can raise background in chromogenic IHC (general IHC practice). | Check the negative control and reagent blank as appropriate; review blocking, washes and chromogen development using the existing IHC-P workflow (general IHC practice). |
| A sharp membrane rim dominates (UniProt Q92598: no transmembrane segment). | A membrane-dominant pattern does not fit the annotated cytoplasmic localisation or topology (UniProt Q92598: subcellular location, topology). | Inspect cell boundaries and controls, then compare the same compartment in a reported High-staining tissue; treat persistent rim-only staining as unresolved (general IHC practice; HPA: tissue IHC). |
| Signal differs between specimens or IHC and IF/ICC (HPA: tissue IHC reliability; subcellular ICC-IF). | HPA reports very low consistency between tissue antibody staining and RNA data, while its ICC-IF localisation evidence has separate antibody ratings (HPA: tissue IHC reliability; antibody validation). | Record the cell type, compartment, controls and assay used; assess each application against its own evidence rather than transferring an ICC-IF validation rating to IHC (general IHC practice; HPA: antibody validation). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Very low consistency between antibody staining and RNA expression data. Pending external verification. Significant inter-individual differences was observed between vagina RNA expression values.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | High | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | High | Protein (IHC) | HPA → |
| Cerebral cortex | Neuronal cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Not detected | Protein (IHC) | HPA → |
| Ovary | Ovarian stroma cells | Not detected | Protein (IHC) | HPA → |
| Skeletal muscle | Myocytes | Not detected | Protein (IHC) | HPA → |
| Smooth muscle | Smooth muscle cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot HSPH1 staining in paraffin sections by checking retrieval, cellular location and controls before comparing signal across specimens.
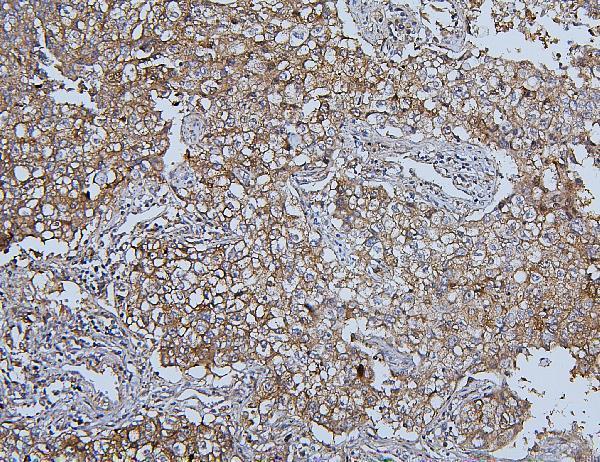
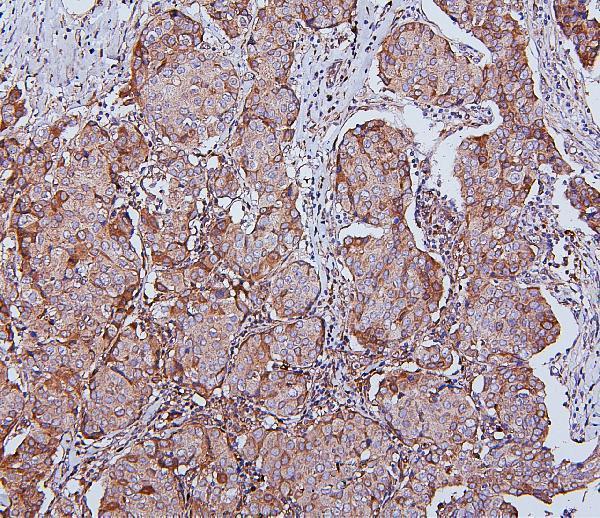
HSPH1 antibodies have IHC images from human cancer tissues and rat brain, plus IF/ICC images from A431 and MCF7 cells (catalog IHC/IF captions).
M04168 renders with human breast cancer paraffin-section IHC; additional images show human stomach cancer, stomach tissue and rat brain (M04168 IHC captions). M04168-1 renders with human lung cancer paraffin-section IHC; additional images show human mammary and intestinal cancer IHC and IF/ICC in A431 and MCF7 cells (M04168-1 IHC/IF captions).
Which to pick: For tissue IHC, M04168 has a human breast cancer paraffin-section example using EDTA at pH 8.0 and 1:50 primary, while M04168-1 has a human lung cancer paraffin-section example using citrate at pH 6 and 1 μg/ml primary; fixation is unreported in both captions (M04168 and M04168-1 IHC captions). For IF/ICC, choose M04168-1, a mouse monoclonal with IF images in A431 and MCF7 cells (catalog host/clone; M04168-1 IF captions). For cross-species IHC, choose M04168, a rabbit monoclonal listed as reactive with Human, Mouse and Rat and shown in rat brain paraffin sections; the payload provides no Mouse IHC image for it (catalog host/clone/reactivity; M04168 IHC captions).