HTR4 / 5-hydroxytryptamine receptor 4 · IHC design guide

Design Immunohistochemistry for HTR4

Plan chromogenic IHC for HTR4 in paraffin sections using intestinal endocrine cells as positive controls (HPA tissue IHC). Assess cytoplasmic staining and account for presumed off-target binding when interpreting results (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
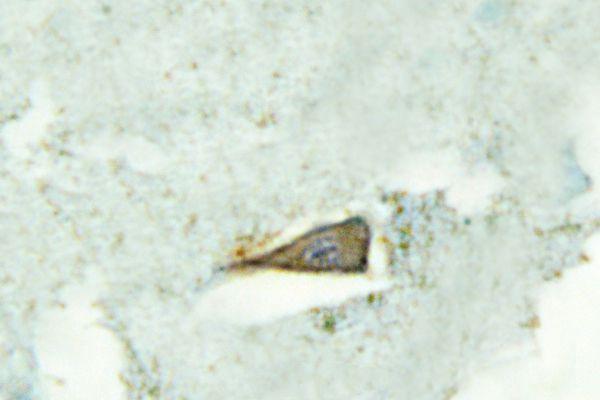
Immunohistochemistry protocol sheet for HTR4 (IHC for HTR4): expected localisation Cytoplasmic in tissue sections (HPA tissue IHC), antibody A03681-3, validated IHC image, and IHC protocol steps
Printable HTR4 IHC protocol sheet — expected localisation Cytoplasmic in tissue sections (HPA tissue IHC), antibody A03681-3, controls and protocol steps. Open the full HTR4 IHC guide →

HTR4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic in tissue sections (HPA tissue IHC)
Staining pattern Cytoplasmic staining in endocrine and neuronal cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Presumed off-target staining was observed (HPA tissue IHC)
Regulation Tissue-dependent expression (UniProt)
Isoform / epitope 9 isoforms; verify whether the epitope is extracellular or cytoplasmic (UniProt)
Section 1

Recommended HTR4 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is followed by published HTR4 staining protocols for mouse colon, human glial tumors, and mouse brain (PMC12503411; PMC13028221; PMC4731785).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human brain tissue; fixative not specified (datasheet A03681-3)
FixationImage fixative and duration unreported (datasheet A03681-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-HTR4, 1:50-1:200 (datasheet A03681-3)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultHTR4-positive staining in endocrine cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in endocrines cells and neuronal cells. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min; published protocols also used citrate pH 6 or 99 °C for 30 min (PMC13028221; PMC4731785).
Section 2

What Is the Expected HTR4 Staining Pattern?

HTR4 is a seven-pass receptor annotated at the cell membrane and endosome membrane (UniProt Q13639 topology; UniProt Q13639 subcellular location). In tissue IHC, expect predominantly cytoplasmic staining in endocrine cells of the appendix and intestine, with lower staining in some neuronal cells (HPA: tissue IHC). HPA rates its tissue staining “Enhanced,” while reporting medium agreement with RNA data and disregarded presumed off-target staining (HPA: reliability description).

What am I looking at on my slide?
Strong cytoplasmic staining in scattered intestinal endocrine cells.This matches the reported high endocrine-cell staining in appendix, colon, duodenum, rectum and small intestine (HPA: tissue IHC). Score the identified cells and their compartment; avoid treating the entire mucosa as uniformly positive.
Faint staining in neuronal cells of cerebral cortex, hippocampus or caudate.Low neuronal-cell staining is reported in these regions (HPA: tissue IHC). Compare the signal with local background before calling it positive; a weak neuronal result should not be judged against the intensity expected in intestinal endocrine cells.
Predominantly nuclear staining, with no discernible cytoplasmic or membrane-associated pattern.A nuclear-only pattern conflicts with the reported cytoplasmic tissue profile and the receptor’s membrane and endosome annotations (HPA: tissue IHC; UniProt Q13639 subcellular location). Treat it as suspect staining and check controls before scoring.
Strong staining across a cell population reported as negative, such as adipocytes.HPA reports no detection in adipocytes from adipose tissue and breast (HPA: tissue IHC). Widespread signal there warrants a specificity check; the HPA reliability note also records presumed off-target binding that was disregarded (HPA: reliability description).
Diffuse colour across cells and surrounding tissue, obscuring cell boundaries.An uninterpretable field cannot establish the reported endocrine-cell pattern (HPA: tissue IHC). In chromogenic IHC, background can arise from nonspecific reagent binding or endogenous detection activity (general IHC practice); compare a primary-omission control.
💡Expected HTR4 appearanceCall a result positive when high cytoplasmic staining is concentrated in intestinal endocrine cells (HPA: tissue IHC); diffuse field-wide, nuclear-only or uniformly strong staining in reported negative cells is suspect (HPA: tissue IHC; UniProt Q13639 subcellular location).
How each factor affects the staining
Cellular compartmentHPA describes cytoplasmic tissue staining, while UniProt annotates cell and endosome membranes and seven transmembrane segments (HPA: tissue IHC; UniProt Q13639 topology and subcellular location). Assess the cell-type pattern alongside compartment; these descriptions do not require a sharply outlined plasma membrane in chromogenic sections.
Choice of comparison tissueAppendix, colon, duodenum, rectum and small intestine contain endocrine cells reported as high; cerebral cortex, hippocampus and caudate have low neuronal staining (HPA: tissue IHC). A low-level neuronal field is therefore a less clear intensity reference than a section containing identifiable intestinal endocrine cells.
Interpretive confidenceThe HPA IHC rating is Enhanced, but its description notes medium staining–RNA consistency and presumed off-target binding that was disregarded (HPA: reliability description). Use the reported cell type and a negative comparison when judging unexpected signal; the rating does not validate every stained cell.
Isoform and epitope coverageUniProt lists nine HTR4 isoforms and a cytoplasmic C-terminal region spanning residues 315–388 (UniProt Q13639 isoforms and topology). The supplied record gives no antibody epitope, so isoform coverage or a specific retrieval requirement cannot be inferred.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in a section selected as a positive comparison.The sampled field may lack identifiable endocrine cells, or the IHC run may have failed (HPA: high in intestinal endocrine cells; general IHC practice).Locate endocrine-cell-rich fields, then check the run control and staining steps; judge absence only in the reported positive cell population (HPA: tissue IHC; general IHC practice).
Staining appears only in nuclei.This conflicts with HPA’s cytoplasmic profile and UniProt’s membrane annotations (HPA: tissue IHC; UniProt Q13639 subcellular location).Compare with the primary-omission control and an intestinal endocrine-cell reference before calling the nuclear signal HTR4 (general IHC practice; HPA: tissue IHC).
Strong colour appears in adipocytes or broadly across unrelated cells.Adipocytes are reported as not detected; HPA also notes presumed off-target binding (HPA: tissue IHC; HPA: reliability description).Check cell identification and the omission control, then limit scoring to a pattern supported by the tissue profile (HPA: tissue IHC; general IHC practice).
Background masks the endocrine-cell pattern.Nonspecific reagent binding or endogenous detection activity can obscure chromogenic IHC (general IHC practice).Check the primary-omission control and the detection-system blocking steps; reassess whether discrete endocrine cells remain distinguishable (general IHC practice; HPA: tissue IHC).
A brain section looks weaker than an intestinal section.HPA reports low neuronal staining in cerebral cortex, hippocampus and caudate, versus high staining in intestinal endocrine cells (HPA: tissue IHC).Compare like cell types and tissue regions; record a weak neuronal pattern separately from the high intestinal reference (HPA: tissue IHC).
Q: Can the IHC pattern establish an IF/ICC result?HPA lists an ICC/IF membrane summary but provides no main location or cell-line images in this payload (HPA: subcellular ICC/IF).A: Use the separate IF/ICC guide for that application; do not infer a validated IF/ICC staining pattern from the tissue IHC result (HPA: subcellular ICC/IF; HPA: tissue IHC).

Sample controls for HTR4 IHC & IF

🧪Run colon first; its endocrine cells should stain for HTR4 (HPA: High in colon endocrine cells). Use adipose tissue as the negative tissue (HPA: Not detected in adipocytes), and compare endocrine cells with neighboring non-endocrine cells on the colon slide as an internal background reference without assuming those cells are HTR4-negative (HPA: cell-specific colon result).
Positive control tissue: Appendix (Endocrine cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for HTR4; derive a cell-line control from the positive tissue's cell type (Endocrine cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control; an irrelevant antibody matched to the primary antibody’s host species, isotype and clonality where applicable; and HTR4-knockout tissue as a biological negative if available (standard IHC control practice). For chromogenic colon IHC, block and check endogenous peroxidase activity; assess tissue autofluorescence if using IF (standard IHC/IF practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported in the supplied evidence, and the fixative for the selected paraffin-section image is unreported (selected-SKU tissue-IHC caption). Antigen-retrieval dependency is also unreported, so optimize retrieval empirically for paraffin IHC; the evidence does not establish that frozen sections or IF are easier (supplied application evidence). In colon, endogenous peroxidase can complicate chromogenic interpretation, while autofluorescence can complicate IF interpretation (standard IHC/IF practice).

HPA tissue IHC evidence for HTR4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded. External characterization data supports antibody staining.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Endocrine cells High Protein (IHC) HPA →
Colon Endocrine cells High Protein (IHC) HPA →
Duodenum Endocrine cells High Protein (IHC) HPA →
Rectum Endocrine cells High Protein (IHC) HPA →
Small intestine Endocrine cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Section 3

Advanced HTR4 IHC Tips

Troubleshoot HTR4 staining in paraffin sections by checking retrieval, cellular pattern, controls, and scoring against the available tissue evidence.

How should I retrieve HTR4 before chromogenic IHC?
Start with citrate pH 6.0 heat-induced antigen retrieval at 95–98 °C for 20 min (page retrieval rule: cytoplasmic / membrane antigen). Keep section thickness, cooling, and detection conditions consistent across a retrieval comparison so that a change in staining can be attributed to retrieval (standard IHC practice). Assess signal in intestinal endocrine cells, which show high HTR4 staining, alongside a matched negative control (HPA: high in intestinal endocrine cells; standard IHC practice). If staining remains weak, compare a longer citrate retrieval on adjacent sections while monitoring tissue integrity and background (standard IHC practice). Do not treat stronger diffuse staining alone as improved HTR4 detection (HPA: presumed off-target binding observed and disregarded; standard IHC practice).
Does fixation explain weak HTR4 staining in paraffin sections?
The selected antibody image shows staining in paraffin-embedded human brain, but its caption does not report a fixative; HTR4-specific fixation sensitivity is therefore unknown (caption: A03681-3). Record the fixative, fixation duration, and processing history for every specimen before comparing staining intensity (standard IHC practice). If fixation differs between samples, test adjacent sections with the same citrate pH 6.0, 95–98 °C, 20 min retrieval and detection conditions (page retrieval rule; standard IHC practice). Evaluate morphology and control staining together: poor preservation or a failed control can explain an uninterpretable result without establishing a target-specific fixation effect (standard IHC practice). HPA tissue patterns do not establish how fixation alters this antibody’s epitope (HPA: tissue IHC profile).
Should HTR4 stain the membrane or cytoplasm?
Expect a membrane-associated receptor pattern because HTR4 is a 7-transmembrane protein assigned to the cell membrane and endosome membrane (UniProt Q13639: topology and subcellular location). Cytoplasmic staining can be plausible in tissue sections: HPA reports cytoplasmic expression in endocrine and neuronal cells, while UniProt describes recruitment to early endosomes through SNX27 (HPA: tissue profile; UniProt Q13639: subcellular location). Compare the signal with cell boundaries, cytoplasm, and the counterstained nucleus at the same magnification (standard IHC practice). Diffuse nuclear staining lacks support from the supplied localisation evidence and warrants review against controls and tissue morphology before scoring (UniProt Q13639: subcellular location; standard IHC practice).
Could splice variants or epitope accessibility change the IHC pattern?
HTR4 has 9 listed isoforms, so interpretation depends on which sequence the catalog antibody recognizes; its epitope is not supplied here (UniProt Q13639: isoforms; supplied antibody evidence). The receptor has extracellular, transmembrane, and cytoplasmic regions, including a cytoplasmic segment at residues 315–388 (UniProt Q13639: topology). Check the antibody’s documented immunogen or epitope before attributing different cell patterns to splice variants (standard IHC practice). Retrieval may expose epitopes differently in processed sections, so compare adjacent sections under the page’s citrate pH 6.0, 20 min condition before changing interpretation (page retrieval rule; standard IHC practice). Staining alone cannot identify a specific HTR4 isoform (UniProt Q13639: isoforms; standard IHC practice).
How can IF help resolve an ambiguous chromogenic HTR4 pattern?
On a separate IF section, multiplex HTR4 with a validated endocrine-cell marker when assessing intestinal tissue, where HPA reports high endocrine-cell staining (HPA: appendix, colon, duodenum, rectum, and small intestine; standard IF practice). Choose fluorophores after checking the specimen’s autofluorescence, and inspect each channel separately before interpreting overlap (standard IF practice). HTR4 contains extracellular and cytoplasmic regions; match permeabilisation to the antibody’s documented epitope side, which is not specified in the supplied evidence (UniProt Q13639: topology; supplied antibody evidence; standard IF practice). Include single-stain and secondary-only controls to evaluate bleed-through and background (standard IF practice). Treat IF colocalisation as supporting evidence, not proof that every chromogenic deposit represents HTR4 (standard IHC/IF practice).
What should I check when HTR4 IHC has widespread background?
First compare the test section with a no-primary control and inspect tissue edges, folds, and damaged areas at matched exposure or illumination (standard IHC practice). Check the peroxidase block before chromogenic detection and shorten DAB development if precipitate or diffuse color obscures cell boundaries (standard IHC practice). HPA reports presumed off-target binding that was disregarded, so broad staining outside its reported endocrine and neuronal pattern needs independent scrutiny (HPA: reliability description and tissue profile). Titrate the catalog antibody only within its documented IHC range, which is not supplied here, and keep washing and detection conditions constant (supplied antibody evidence; standard IHC practice). Judge improvement by cleaner cellular localisation and controls, not intensity alone (UniProt Q13639: subcellular location; standard IHC practice).
How should I score HTR4 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population before scoring: HPA reports high staining in intestinal endocrine cells and low staining in cerebral cortex, hippocampus, and caudate neuronal cells (HPA: tissue IHC). For a consistent cell population, report an H-score based on staining intensity and percentage positive, or report the percentage of positive cells with the denominator stated (standard IHC practice). For sparse endocrine cells, positive-cell density per mm² can complement those measures (standard IHC practice). Normalize to the number of eligible cells or the annotated tissue area, and apply the same threshold, counterstain, and exclusion rules across slides (standard IHC practice). Score membrane-associated and cytoplasmic patterns separately if both are visible (UniProt Q13639: subcellular location; HPA: tissue profile).
When is an apparent HTR4-positive cell likely to be artefact?
A credible result should fit the sampled cell population and a plausible membrane-associated or cytoplasmic pattern (UniProt Q13639: subcellular location; HPA: tissue profile). High staining in intestinal endocrine cells has HPA support, whereas staining in a cell population HPA lists as undetected needs stronger control evidence before attribution to HTR4 (HPA: tissue IHC). Exclude deposits confined to section edges, folds, or necrotic areas, and compare suspicious staining with the no-primary control (standard IHC practice). Check whether color persists after an appropriate peroxidase block, since endogenous enzyme activity can mimic a positive chromogenic signal (standard IHC practice). HPA’s enhanced reliability does not eliminate its reported off-target binding concern (HPA: reliability description).
Boster reagents

Best HTR4 / 5-hydroxytryptamine receptor 4 IHC Antibodies

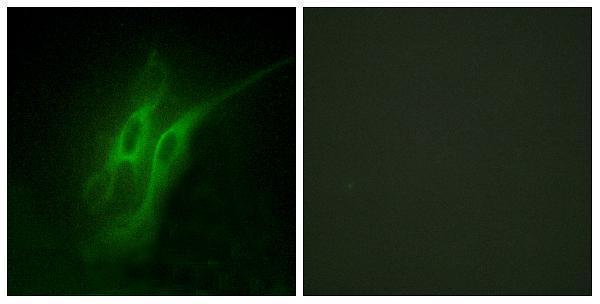
HTR4 antibody figures show IHC in paraffin-embedded human brain (A03681-3 image caption) and IF in HeLa cells (A03681-1 image caption); both catalog entries list Human, Mouse, and Rat reactivity (catalog).

Real IHC data Immunohistochemistry (IHC) analyzes of SR-4 (D47) pAb in paraffin-embedded human brain tissue.
Anti-SR-4 (D47) HTR4 Antibody
Cat # A03681-3
Real IF data Immunofluorescence analysis of HeLa cells, using 5-HT-4 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-SR-4 HTR4 Antibody
Cat # A03681-1

A03681-3 is listed for IHC and IF (catalog), with an IHC figure from paraffin-embedded human brain (image caption) and an IHC dilution range of 1:50–1:200 (datasheet). A03681-1 is listed for IHC and IF (catalog), with an IF figure from HeLa cells that includes peptide blocking (image caption) and an IF dilution range of 1:200–1:1000 (datasheet).

Which to pick: Choose A03681-3 for paraffin-section IHC: its own caption identifies a polyclonal antibody and shows human brain staining in paraffin sections; the fixative is unreported (A03681-3 image caption). Choose A03681-1 for cell-based IF/ICC because its own figure shows HeLa-cell IF with peptide blocking; its clone is unreported (A03681-1 image caption; catalog). For cross-species work, both list Human, Mouse, and Rat reactivity and IHC and IF applications, while the supplied figures show human samples only (catalog; image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q13639 (5HT4R_HUMAN, 5-hydroxytryptamine receptor 4).
  2. Human Protein Atlas. HTR4 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. HTR4 subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. HTR4 antibody validation summary (1 antibodies).
  5. Polysaccharide from Trichosanthes kirilowii Maxim ameliorates diphenoxylate-induced functional constipation in mice. Frontiers in microbiology 2025 — PMC12503411.
  6. HTR4 gene structure and altered expression in the developing lung. Respiratory research 2013 — PMC3750317.
  7. Protein Expression Status of HTR4 and PDE4D Genes in Glial Brain Tumors Followed by the Study of Genomic Instability. Life (Basel, Switzerland) 2026 — PMC13028221.
  8. Probable involvement of p11 with interferon alpha induced depression. Scientific reports 2016 — PMC4731785.
  9. PubMed PMID:9603189 — UniProt-cited evidence.
  10. PubMed PMID:9351641 — UniProt-cited evidence.
  11. PubMed PMID:10220570 — UniProt-cited evidence.