This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan IFITM1 chromogenic IHC on paraffin sections with the catalog antibody at 0.5–1 μg/mL (datasheet). Assess membranous staining in epididymal glands and account for endothelial and lymphoid signal when scoring (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Membranous staining in epididymal glands (HPA tissue IHC) | |
| Staining pattern | Distinct epididymal gland membranes; endothelial and lymphoid signal (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Epididymis+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image PA1112) | |
| Caveat | Endothelial and lymphoid positivity can complicate scoring (HPA tissue IHC) | |
| Regulation | Interferon induced expression (UniProt) | |
| Isoform / epitope | No annotated isoforms; cytoplasmic vs extracellular epitope matters (UniProt) |
The catalog antibody’s IHC-P protocol is followed by three published IFITM1 staining protocols (PMC4867989; PMC7404048; PMC6172064).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet PA1112); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-IFITM1, 0.5-1μg/ml (datasheet PA1112) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | IFITM1-positive staining in glandular cells of epididymis (HPA tissue IHC: High). HPA tissue profile: Distinct membranous expression in epididymis, also expressed in endothelial cells and in lymphoid tissue. No signal in the no-primary control. |
IFITM1 is a membrane protein with a transmembrane segment at residues 87–107 and cell membrane and lysosome membrane annotations (UniProt P13164 topology; UniProt P13164 subcellular). In paraffin-section IHC, expect the clearest membranous staining in epididymal glandular cells, with staining also reported in endothelial and lymphoid cells (HPA: High in epididymal glandular cells; HPA: tissue IHC profile). HPA rates its tissue IHC evidence Enhanced, citing agreement between staining and RNA expression (HPA: tissue IHC reliability).
| Crisp membrane staining in epididymal glandular cells, with little staining in adjacent unstained areas. | This matches HPA’s distinct membranous profile and High glandular-cell staining in epididymis (HPA: tissue IHC profile; HPA: High in epididymal glandular cells). Compare cells within the same section when judging whether the signal follows the expected anatomy (general IHC practice). |
| Staining follows endothelial cells or lymphoid areas outside the epididymis. | These can be expected positive populations: HPA reports endothelial staining, Medium lymphoid-tissue staining in appendix, and Medium germinal-center staining in lymph node (HPA: tissue IHC profile; HPA: appendix and lymph-node IHC). Judge the labeled cell population, rather than treating every cell in a positive tissue as positive. |
| Strong, widespread nuclear staining replaces a discernible membrane pattern. | A dominant nuclear pattern does not match the reported cell membrane or lysosome membrane locations, or HPA’s membranous tissue profile (UniProt P13164 subcellular; HPA: tissue IHC profile). Treat it as suspect and check controls before assigning it to IFITM1 (general IHC practice). |
| Signal appears mainly in a cell population HPA reports as undetected, or as uniform staining across unrelated cells. | For example, HPA reports IFITM1 as Not detected in adipocytes and cardiomyocytes (HPA: adipose-tissue and heart-muscle IHC). Consider antibody cross-reactivity or endogenous detection activity, especially if the pattern persists in a no-primary control (general IHC practice). |
| A diffuse haze obscures cell borders, or no staining appears in an epididymal positive control. | Haze prevents a reliable membrane call against HPA’s distinct membranous reference pattern (HPA: tissue IHC profile). Absence in a known-positive cell population makes a negative test section inconclusive; review the run controls and detection workflow before interpreting it (HPA: High in epididymal glandular cells; general IHC practice). |
| Membrane location and topology | UniProt places IFITM1 at the cell and lysosome membranes and maps its transmembrane segment to 87–107 (UniProt P13164 subcellular and topology). The expected tissue IHC readout is membranous; the supplied topology does not identify the catalog antibody’s epitope or establish an antigen-retrieval requirement (HPA: tissue IHC profile). |
| Tissue and cell selection | The strongest listed normal-tissue example is epididymal glandular cells (High), while several endothelial, lymphoid, stromal, and epithelial populations are Medium or Low (HPA: tissue IHC). Select and score the documented cell population; a whole-section average can obscure a localized positive pattern. |
| Antibody-validation scope | HPA lists IHC as Enhanced for HPA004810 and CAB017615, and describes tissue-level agreement with RNA expression (HPA: antibody validation; HPA: tissue IHC reliability). This supports the reported tissue pattern; it does not establish the performance of an unlisted antibody or every staining condition. |
| Tumor versus normal tissue | UniProt reports greatly elevated IFITM1 levels in colon, cervical, esophageal, and ovarian cancers (UniProt P13164 tissue specificity). Do not transfer that statement to normal tissue: HPA lists Low staining in normal colon endothelial cells and normal cervical glandular cells (HPA: tissue IHC). Interpret the specimen and cell population separately. |
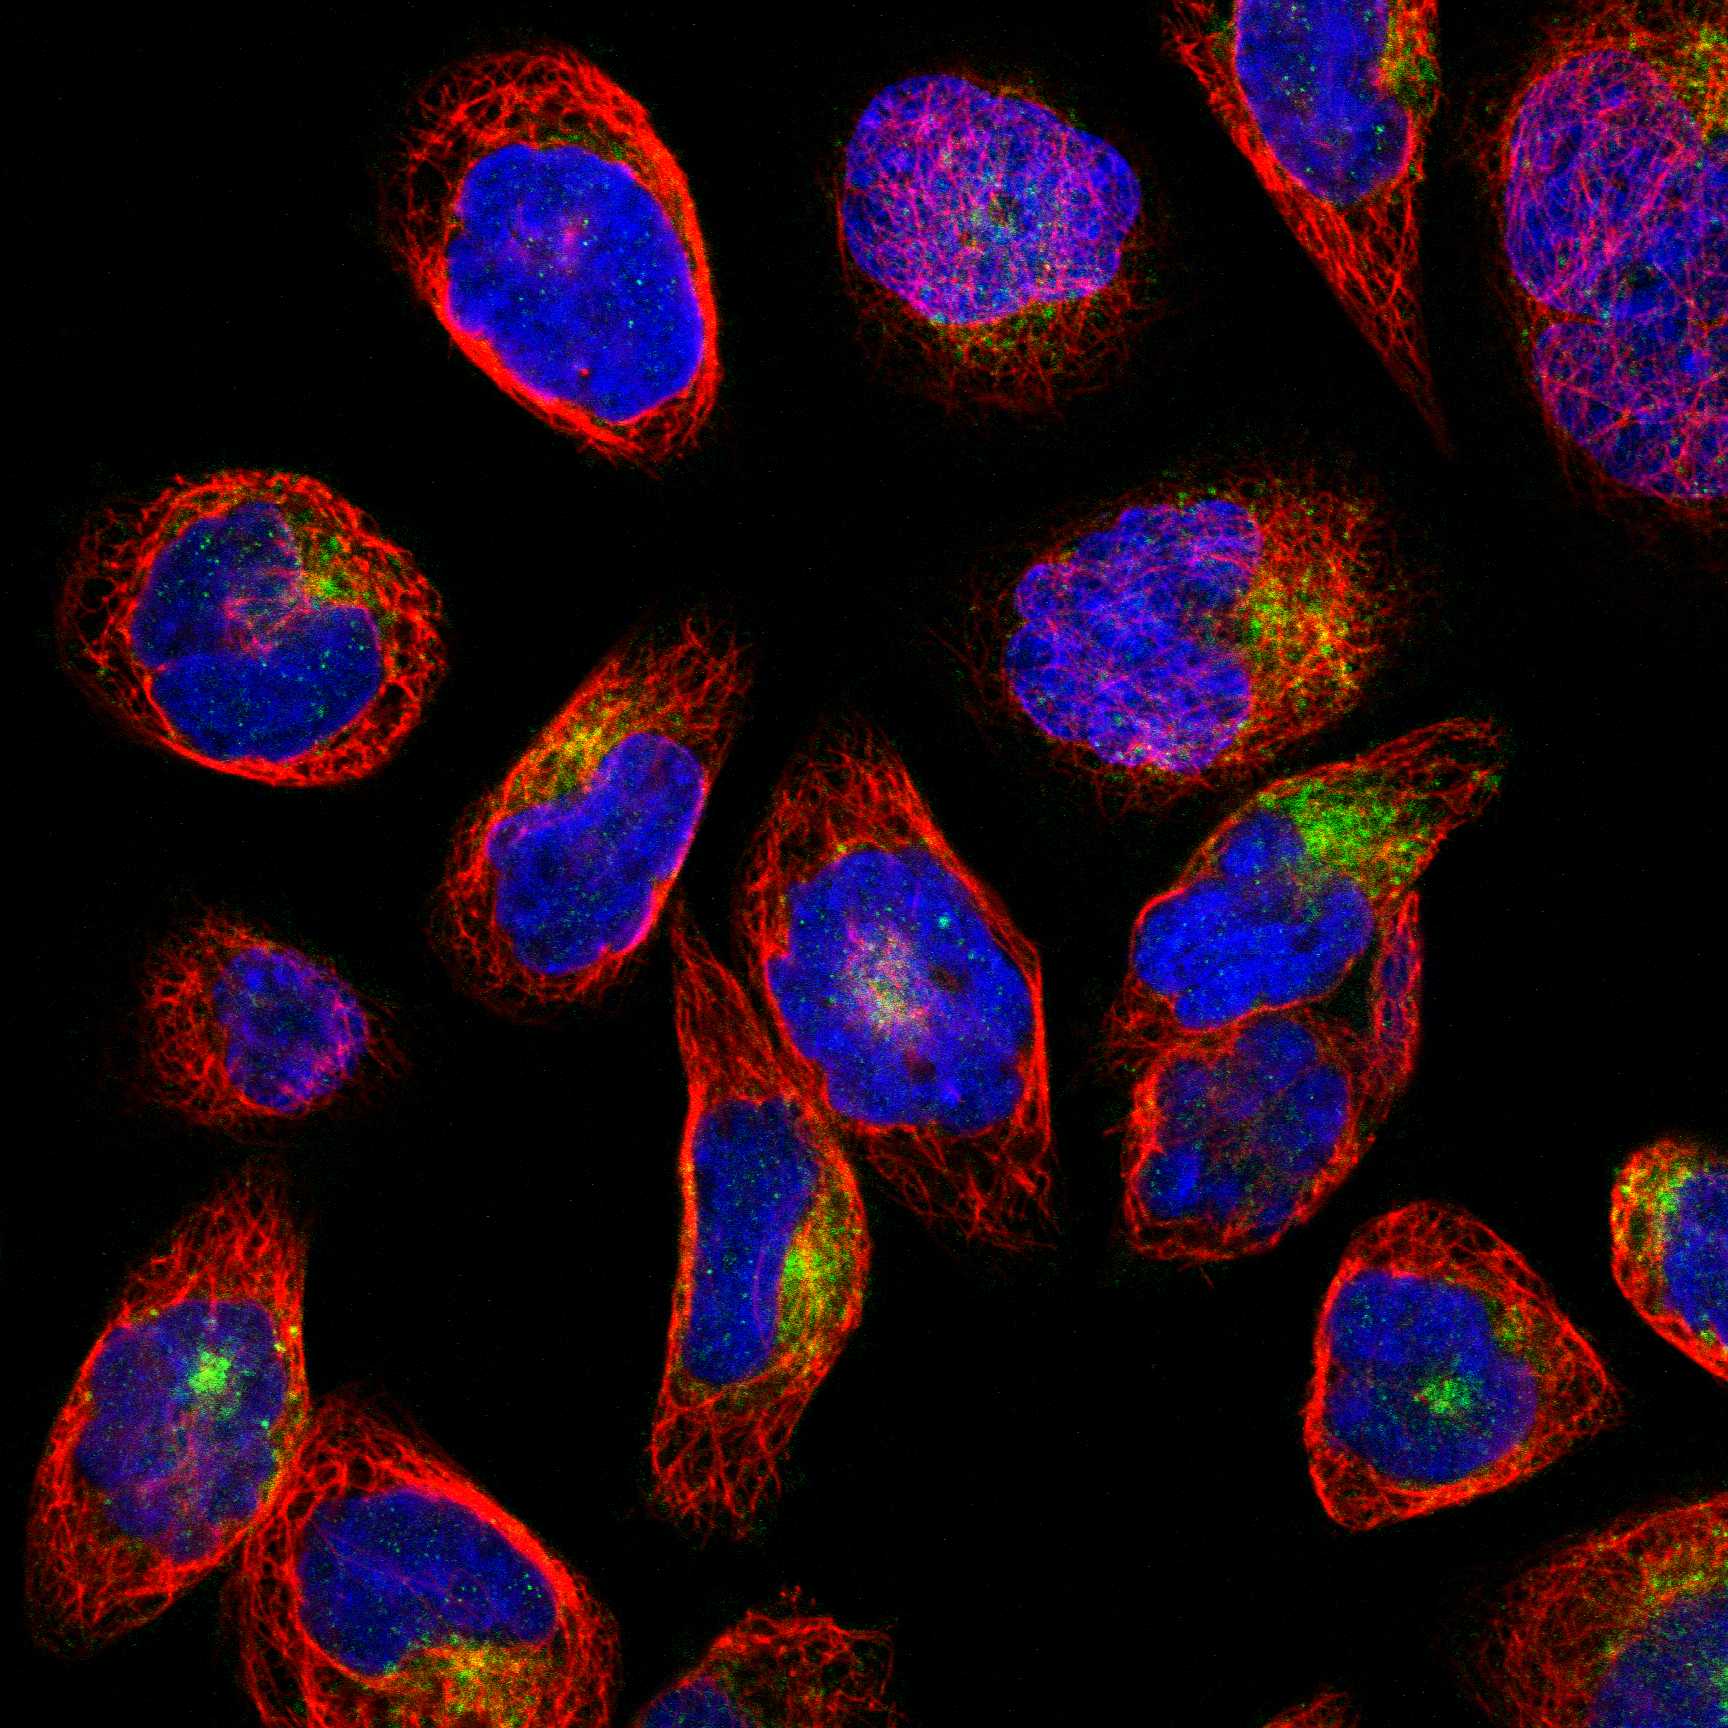
| Subcellular evidence by application | HPA ICC-IF supports plasma-membrane localization and labels Golgi localization uncertain; UniProt also annotates lysosome membrane (HPA: subcellular ICC-IF; UniProt P13164 subcellular). These sources make intracellular signal worth examining, but they do not establish a routine Golgi or lysosomal pattern in paraffin-section IHC. |
| Situation | Likely cause | Next action |
|---|---|---|
| Epididymal positive-control cells are blank. | The run may have failed, or the chosen conditions may not reveal detectable staining; HPA reports these cells as High (HPA: epididymis IHC). | Check the control section, primary-antibody step, detection reagents, and staining run. Review antigen retrieval as a general IHC variable; target-specific retrieval or fixation sensitivity is unreported in the supplied sources (general IHC practice). |
| Most of the section has diffuse chromogen haze. | Nonspecific binding, excess detection signal, or endogenous detection activity can obscure cell borders (general IHC practice). | Inspect the no-primary control and adjust blocking, washing, and detection conditions as appropriate (general IHC practice). Reassess for defined membrane staining in the HPA-reported positive cells (HPA: tissue IHC profile). |
| Strong nuclear color dominates the positive tissue. | This conflicts with the supplied membrane locations and HPA’s membranous tissue profile (UniProt P13164 subcellular; HPA: tissue IHC profile). | Check no-primary and other run controls, then confirm whether any cell-border staining remains (general IHC practice). Do not score isolated nuclear color as the expected IFITM1 pattern. |
| Cells reported as undetected show strong color. | Cross-reactivity or endogenous detection activity is possible; HPA reports adipocytes and cardiomyocytes as Not detected (HPA: adipose-tissue and heart-muscle IHC). | Compare the same cell type with the HPA reference pattern and examine a no-primary control (HPA: tissue IHC; general IHC practice). If controls are clean, confirm the finding independently before interpreting it as IFITM1. |
| A lymphoid or endothelial region looks weaker than epididymis. | HPA reports Medium staining in appendix lymphoid tissue, lymph-node germinal-center cells, and skin endothelial cells, versus High epididymal glandular staining (HPA: tissue IHC). | Score the documented cell population and its expected level. A weaker, localized positive can be consistent with the HPA pattern; compare it with run controls before changing conditions. |
| Q: Does an ICC-IF Golgi signal establish the expected IHC pattern? | HPA calls ICC-IF Golgi localization uncertain, while supporting plasma-membrane localization (HPA: subcellular ICC-IF). | A: No. Interpret paraffin-section staining against HPA’s membranous tissue IHC profile and its named positive cell populations (HPA: tissue IHC). Evaluate ICC-IF localization on its own guide page. |




Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Epididymis | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Lymphoid tissue | Medium | Protein (IHC) | HPA → |
| Endometrium | Cells in endometrial stroma | Medium | Protein (IHC) | HPA → |
| Fallopian tube | Ciliated cells (tip of cilia) | Medium | Protein (IHC) | HPA → |
| Kidney | Cells in glomeruli | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bronchus | Basal cells | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
Use membrane pattern, cell identity and matched controls to troubleshoot IFITM1 staining in paraffin sections; interpret fluorescence separately.
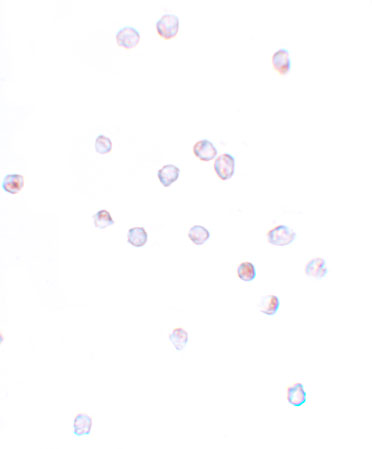
Anti-IFITM1 antibodies have IHC data from human intestinal cancer tissue (PA1112 image caption) and IF/ICC data from Jurkat cells (A02633 image captions). Listed reactivity includes human, mouse and rat (catalog reactivity).
PA1112 will render with an IHC(P) image of human intestinal cancer tissue and lists human reactivity (PA1112 image caption; catalog reactivity). A02633 will render with IF/ICC images of Jurkat cells and lists human, mouse and rat reactivity (A02633 image captions; catalog applications and reactivity).
Which to pick: Choose PA1112 for paraffin-section tissue IHC, supported by its IHC(P) image of human intestinal cancer tissue; the fixative is unreported (PA1112 image caption). Choose A02633 for IF/ICC in Jurkat cells, supported by its images and application list (A02633 image captions; catalog applications). For mouse or rat samples, A02633 lists reactivity with those species, but the provided IF/ICC images show only Jurkat cells (A02633 catalog reactivity; image captions).