IGF1R / Insulin-like growth factor 1 receptor · IHC design guide

Design Immunohistochemistry for IGF1R

Plan IGF1R staining in paraffin sections using the granular cytoplasmic pattern seen mainly in glandular cells as a tissue reference (HPA tissue IHC). The guide covers fixation, controls, epitope choice and scoring in light of IGF1R’s membrane topology and α/β chain processing (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for IGF1R (IHC for IGF1R): expected localisation Granular cytoplasm in tissue (HPA tissue IHC); cell membrane at the molecular level (UniProt), antibody M00070-12, validated IHC image, and IHC protocol steps
Printable IGF1R IHC protocol sheet — expected localisation Granular cytoplasm in tissue (HPA tissue IHC); cell membrane at the molecular level (UniProt), antibody M00070-12, controls and protocol steps. Open the full IGF1R IHC guide →

IGF1R Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm in tissue (HPA tissue IHC); cell membrane at the molecular level (UniProt)
Staining pattern Granular cytoplasmic staining, mainly in glandular cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Granular tissue staining may differ from membrane expectation (HPA tissue IHC) (UniProt)
Regulation Overexpressed in some tumors (UniProt)
Isoform / epitope No isoforms listed; α versus β epitope matters (UniProt)
Section 1

Recommended IGF1R IHC & IF Protocols

The catalog antibody’s IHC-P protocol is followed by published IGF1R IHC methods from three PMC articles (PMC3502638; PMC6730551; PMC8432056).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet M00070-12); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-IGF1R, 1:100-1:200 (datasheet M00070-12)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultIGF1R-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: Ubiquitous granular cytoplasmic expression, mostly in glandular cells. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page retrieval); use high-pH retrieval when following PMC3502638.
Section 2

What Is the Expected IGF1R Staining Pattern?

Expect membrane IGF1R (UniProt P08069 topology) and glandular granules (HPA: Approved; medium consistency).

What am I looking at on my slide?
Granular glandular staining (HPA: tissue IHC)Matches the reported IHC pattern (HPA: Approved).
Nuclear-only IHC stainDiscordant with membrane topology (UniProt P08069); assess for artefact.
Strong smooth muscle staining (HPA: Low)Unexpected intensity may reflect cross-reactivity or endogenous detection activity.
Diffuse stain across the sectionBackground may reflect inadequate blocking or washing (general IHC practice).
No adipocyte stain (HPA: High in adipocytes)Check the positive control and IHC detection workflow (general IHC practice).
💡Expected IGF1R appearanceStrong adrenal glandular granules (HPA: High); membrane signal fits (UniProt P08069); uniform haze is suspect.
How each factor affects the staining
Epitope locationAlpha chain is extracellular; beta chain spans the membrane (UniProt P08069 topology).
ProcessingSignal peptide 1–30; mature alpha 31–736 and beta 741–1367 (UniProt P08069).
Tissue choiceAdipocytes are High; breast glandular cells are Low (HPA: tissue IHC).
IF/ICC: expected location?Plasma membrane is supported; nucleolar staining is uncertain (HPA: ICC-IF).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No stain in adipocytes (HPA: High)Possible IHC workflow failure (general IHC practice).Check controls, antibody dilution, retrieval and detection (general IHC practice).
Nuclear-only IHC signalDiscordant with membrane topology (UniProt P08069).Review controls and detection background (general IHC practice).
Strong smooth muscle signal (HPA: Low)Possible cross-reactivity or endogenous activity.Run reagent controls and review blocking (general IHC practice).
Diffuse section-wide colorPossible nonspecific background (general IHC practice).Review blocking, dilution and washes (general IHC practice).
Patchy staining within a sectionPossible uneven reagent coverage (general IHC practice).Check section coverage and reagent application (general IHC practice).

Sample controls for IGF1R IHC & IF

🧪Run adipose tissue first and expect staining in adipocytes (HPA: High in adipocytes). HPA detects IGF1R in all 45 scored tissues, so use no-primary and isotype controls instead of a negative tissue (HPA: no negative tissue rows); cells without specific signal on the positive slide should show counterstain only, but no cell population there is established as IGF1R-negative.
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: None in HPA: IGF1R is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show IGF1R in MCF-7, SiHa, U2OS, ASC52telo, RPTEC/TERT1, hTERT-RPE1 (serum starved), with annotated localisation: Nucleoli (uncertain), Plasma membrane (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control (selected IHC caption: rabbit antibody); use IGF1R knockout tissue or cells as a biological negative where available. For chromogenic IHC, block endogenous peroxidase and check adipose sections for staining at tissue edges or folds (standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the selected M00070-12 tissue-IHC caption does not state a fixative. Antigen retrieval requirements for this antibody are unreported; assess retrieval on the positive adipose control (HPA: High in adipocytes). Frozen sections or IF cannot be judged easier from the supplied evidence; lipid extraction can leave empty adipocyte vacuoles in paraffin sections, so assess staining at the cell rim against the negative controls (standard histology practice).

HPA tissue IHC evidence for IGF1R

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Caudate Neuronal cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: IGF1R is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced IGF1R IHC Tips

Use the supplied IGF1R topology and staining evidence to troubleshoot paraffin-section chromogenic IHC; assess IF separately when comparing compartments.

How should I troubleshoot weak IGF1R staining after antigen retrieval?
For paraffin-section chromogenic IHC, start with citrate pH 6.0 HIER at 95–98 °C for 20 min (page retrieval rule). Keep section thickness, cooling, antibody incubation and chromogen development matched when comparing retrieval conditions (standard IHC practice). If staining remains weak, test an alternative retrieval buffer on adjacent sections as a fallback, while monitoring tissue damage and background (standard IHC practice). Compare membrane-associated signal with the supported plasma-membrane location, while allowing for the granular cytoplasmic pattern reported in tissue IHC (HPA: subcellular; HPA: tissue IHC). Include a no-primary control so increased background is not mistaken for recovered antigen (standard IHC practice).
Could fixation explain weak IGF1R staining in paraffin sections?
IGF1R-specific sensitivity to fixation is unknown from the supplied evidence; the selected tissue-IHC caption does not state a fixative (caption: M00070-12). Record the fixative, duration and processing schedule for each specimen before comparing staining intensity across blocks (standard IHC practice). Assess adjacent sections with the same citrate pH 6.0, 95–98 °C, 20 min retrieval and matched detection conditions (page retrieval rule; standard IHC practice). Check tissue preservation and control staining before attributing a weak result to lost IGF1R antigen (standard IHC practice). Do not infer fixation sensitivity from the receptor’s membrane topology or reported tissue staining patterns (UniProt P08069 topology; HPA: tissue IHC).
How should I assess cytoplasmic IGF1R staining when membrane staining is expected?
IGF1R is annotated at the cell membrane, with a transmembrane segment at residues 936–959 (UniProt P08069 topology). Tissue IHC also reports ubiquitous granular cytoplasmic expression, mostly in glandular cells, so cytoplasmic signal warrants assessment rather than automatic rejection (HPA: tissue IHC). Compare the distribution within intact cells and across neighboring sections processed with identical retrieval and detection conditions (standard IHC practice). Plasma-membrane localization is supported in subcellular imaging, whereas reported nucleolar localization is uncertain (HPA: subcellular). If nuclear or diffuse staining dominates, inspect the no-primary control and tissue morphology before assigning that signal to IGF1R (standard IHC practice; HPA: subcellular).
Why might two IGF1R antibodies stain different compartments?
The record lists 0 isoforms and describes processing into an alpha chain at residues 31–736 and a beta chain at 741–1367 (UniProt P08069 processing; UniProt P08069 isoforms). The beta chain contains the 936–959 transmembrane segment, followed by a cytoplasmic region at 960–1367 (UniProt P08069 topology). Check each antibody’s documented immunogen or epitope before comparing staining, because the supplied evidence does not locate the catalog antibody’s epitope (standard IHC practice). IGF1R also has listed glycosylation and phosphorylation sites, but their effects on this antibody’s IHC staining are unreported (UniProt P08069 modifications). Compare matched sections and controls before interpreting different patterns as distinct protein forms (standard IHC practice).
How can I compare IGF1R IF with the chromogenic IHC pattern?
In IF, multiplex IGF1R with a marker for the cell type being assessed so compartment and cell identity can be compared directly (standard IF practice). For glandular regions, that choice follows the reported predominance of granular cytoplasmic staining in glandular cells (HPA: tissue IHC). Choose a fluorophore channel after checking tissue autofluorescence with an unstained control, and use single-stain controls to assess bleed-through (standard IF practice). Set permeabilisation according to the documented epitope: an extracellular epitope may be accessible without it, whereas a cytoplasmic epitope requires access across the membrane (UniProt P08069 topology; standard IF practice). The supplied IF evidence does not establish fixation or permeabilisation conditions for this antibody (HPA: subcellular; caption: M00070-12).
What should I check when IGF1R IHC has widespread background?
Run no-primary and detection-only controls to identify staining from the detection system, then compare them with the IGF1R slide (standard IHC practice). For chromogenic detection, verify the peroxidase block, blocking step, washes and DAB development under otherwise matched conditions (standard IHC practice). Titrate the antibody using a documented starting condition if available; no dilution is supplied in this payload (standard IHC practice). Because tissue IHC describes widespread granular cytoplasmic expression, distribution alone cannot establish that a widespread signal is background (HPA: tissue IHC). Examine edges, folds, damaged areas and endogenous pigment separately from intact-cell staining, with the same exposure and counterstain across comparisons (standard IHC practice).
How should I quantify IGF1R staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the compartment and cell population before scoring, using supported plasma-membrane localization and the reported granular cytoplasmic tissue pattern as separate observations (HPA: subcellular; HPA: tissue IHC). Report an H-score from intensity and percentage of positive cells, or report percentage positive within a predefined region (standard IHC practice). If counting positive cells, express density per mm² of viable tissue and retain the region definition across samples (standard IHC practice). Normalize cell-based measures to eligible cells and area-based measures to measured viable area, excluding folds and necrosis (standard IHC practice). Keep retrieval, detection, imaging and scoring thresholds consistent, and assess reader agreement when scores are subjective (standard IHC practice).
How can I distinguish convincing IGF1R staining from artefact?
Look for reproducible staining in intact cells with interpretable morphology, and compare it with no-primary and detection-only controls (standard IHC practice). Membrane-associated staining fits the supported plasma-membrane location; granular cytoplasmic staining also occurs in tissue IHC, mostly in glandular cells (HPA: subcellular; HPA: tissue IHC). Treat isolated strong nucleolar staining cautiously because that location is marked uncertain in the supplied subcellular evidence (HPA: subcellular). Check whether signal follows section edges, folds, necrosis, pigment or residual endogenous peroxidase activity before calling those regions positive (standard IHC practice). Finally, compare the proposed positive-cell population with morphology and control sections, since IGF1R expression is reported across many tissues (UniProt P08069 tissue specificity; standard IHC practice).
Boster reagents

Best IGF1R / Insulin-like growth factor 1 receptor IHC Antibodies

Both antibodies have human carcinoma IHC images and list IF as an application; M00070-12 lists human reactivity, while A00070Y1161-1 lists human, mouse, and rat reactivity (catalog images and applications).

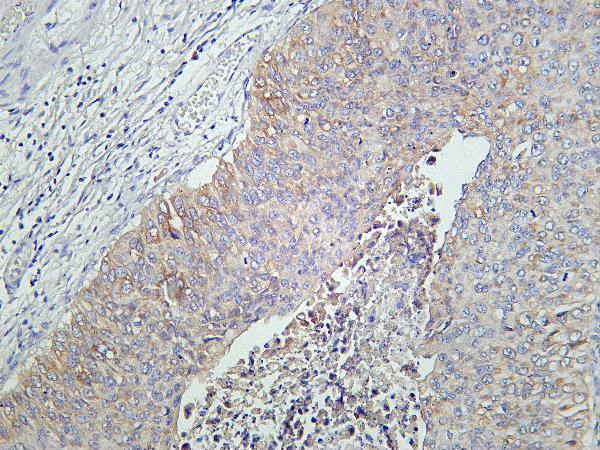
Real IHC data Human bladder carcinoma was stained with Anti-IGF1 Receptor rabbit antibody
Anti-IGF1 Receptor Rabbit Monoclonal Antibody
Cat # M00070-12
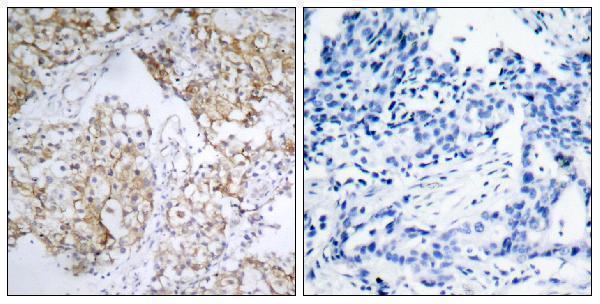
Real IHC data Immunohistochemistry analysis of paraffin-embedded human breast carcinoma, using IGF1R (Phospho-Tyr1161) Antibody. The picture on the right is blocked with the phospho peptide.
Anti-Phospho-IGF-IR (Y1161) IGF1R Antibody
Cat # A00070Y1161-1

M00070-12 has an IHC image of human bladder carcinoma and lists human reactivity and IF (catalog image and applications). A00070Y1161-1 has a phospho-Tyr1161 IHC image of paraffin-embedded human breast carcinoma and lists human, mouse, and rat reactivity and IF (catalog image and applications).

Which to pick: For human tissue IHC, choose M00070-12 for IGF1R staining shown in bladder carcinoma, or A00070Y1161-1 for phospho-Tyr1161 staining shown in paraffin-embedded breast carcinoma; the M00070-12 caption does not report section processing, and neither caption reports a fixative (catalog IHC images). For IF, M00070-12 is the human-reactive monoclonal option, but the catalog provides no IF figure or ICC validation (catalog applications, description, and images). For mouse or rat IHC or IF, choose A00070Y1161-1 on the basis of listed reactivity and applications; its shown paraffin-section result is from human tissue (catalog reactivity, applications, and IHC image).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P08069 (IGF1R_HUMAN, Insulin-like growth factor 1 receptor).
  2. Human Protein Atlas. IGF1R tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. IGF1R subcellular location (ICC-IF): Mainly localized to the nucleoli and plasma membrane. In addition localized to the nucleoli rim and primary cilium..
  4. Human Protein Atlas. IGF1R antibody validation summary (3 antibodies).
  5. Expression of the receptor for type i insulin-like growth factor (IGF1R) in gastrointestinal stromal tumors: an immunohistochemical study of 1078 cases with diagnostic and therapeutic implications. The American journal of surgical pathology 2013 — PMC3502638.
  6. Insulin-like growth factor-1 receptor expression in upper tract urothelial carcinoma. Virchows Archiv : an international journal of pathology 2019 — PMC6730551.
  7. No preclinical rationale for IGF1R directed therapy in chondrosarcoma of bone. BMC cancer 2016 — PMC4946092.
  8. +3179G/A Insulin-Like Growth Factor-1 Receptor Polymorphism: A Novel Susceptibility Contributor in Anti-Ro/SSA Positive Patients with Sjögren's Syndrome: Potential Clinical and Pathogenetic Implications. Journal of clinical medicine 2021 — PMC8432056.
  9. PubMed PMID:2877871 — UniProt-cited evidence.
  10. PubMed PMID:1316909 — UniProt-cited evidence.
  11. PubMed PMID:16572171 — UniProt-cited evidence.