This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Use the IHC-validated antibody at 2–5 μg/ml to assess IRF7 in paraffin sections (datasheet A00115-3). Score nuclear staining against the tissue pattern and consider activation-dependent nuclear accumulation when interpreting results (HPA tissue IHC; UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear staining in most tissues (HPA tissue IHC) | |
| Staining pattern | Nuclear staining in most tissues; distinct in lymphatic organs (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A00115-3) | |
| Positive control | Adipose tissue+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep paraffin-section fixation consistent across samples. (standard IHC practice; not target-specific) | |
| Caveat | Activation can shift IRF7 from cytoplasm to nucleus (UniProt) | |
| Regulation | Viral/TLR signaling activates IRF7 (UniProt) | |
| Isoform / epitope | 4 isoforms (A–D); check epitope coverage before isoform scoring (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet A00115-3) is accompanied by published IRF7 IHC methods from 3 articles (PMC6423323; PMC11759022; PMC10876010).
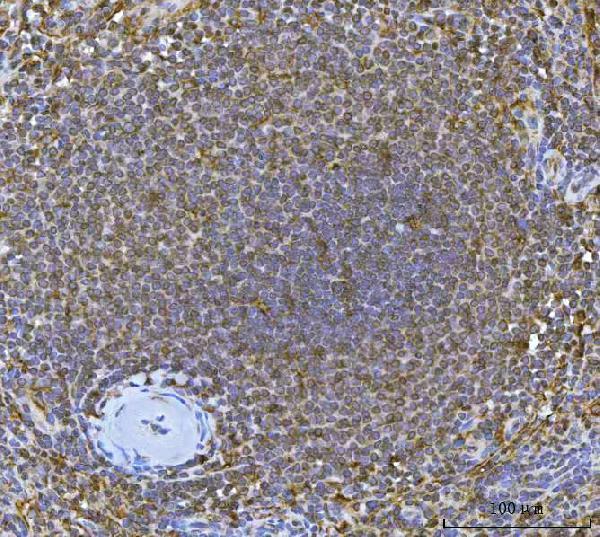
| Sample | Paraffin-embedded human spleen tissue; fixative not specified (datasheet A00115-3) |
| Fixation | Image fixative and duration unreported (datasheet A00115-3); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A00115-3); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A00115-3) |
| Primary antibody | Rabbit anti-IRF7, 2-5 μg/ml (datasheet A00115-3) |
| Primary incubation | Overnight at 4 °C (datasheet A00115-3) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A00115-3) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | IRF7-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in most tissues, distinct expression in lymphatic organs. No signal in the no-primary control. |
IRF7 staining is expected mainly in nuclei across many tissues, with distinct expression in lymphatic organs (HPA tissue IHC). Cytoplasmic staining can also be biologically plausible: IRF7 is a protein without a transmembrane segment, and its phosphorylated active form accumulates selectively in nuclei (UniProt Q92985). Interpret signal by cell type: HPA reports high staining in bone marrow hematopoietic cells and several epithelial and other cell populations, with medium consistency between staining and RNA data (HPA tissue IHC: Approved).
| Nuclear staining in identifiable cells, especially bone marrow hematopoietic cells; adjacent cells may vary in intensity. | This fits the predominantly nuclear tissue pattern and a reported high-staining cell population (HPA tissue IHC). Compare compartments and cell types within the section before calling a positive result; the Approved tissue profile has medium consistency with RNA data (HPA tissue IHC). |
| Predominantly cytoplasmic staining with little nuclear signal in a sample expected to show the tissue IHC pattern. | Review the pattern before calling it artefact. Cytoplasmic inactive IRF7 is plausible, whereas active phosphorylated IRF7 accumulates in nuclei (UniProt Q92985). HPA also supports cytosolic signal in ICC-IF (HPA subcellular). Cytoplasm alone does not establish activation or prove staining failure. |
| Strong signal appears in an unexpected cell population, or acellular material stains as intensely as the cells. | Check morphology and controls for cross-reactivity or endogenous chromogenic activity (general IHC practice). HPA reports high staining in diverse cell populations, including adipocytes, glia and epithelial cells; an unfamiliar positive cell type is therefore a reason to investigate, not grounds for automatic rejection (HPA tissue IHC). |
| A diffuse wash of chromogen obscures nuclei and cell boundaries across the section. | The compartment cannot be scored reliably. Review the negative control and detection background, then adjust blocking, antibody dilution or washing as appropriate for the assay (general IHC practice). A uniform haze is less informative than the cell-associated nuclear pattern described for IRF7 (HPA tissue IHC). |
| No cellular signal appears in bone marrow hematopoietic cells used as a positive tissue check. | HPA reports high staining in this population, so a blank result warrants review of tissue identity, antibody concentration, retrieval, detection reagents and run controls (HPA tissue IHC; general IHC practice). A failed run cannot establish that IRF7 is absent from the test specimen. |
| Compartment and activation | IRF7 can reside in cytoplasm and nucleus; its phosphorylated active form accumulates selectively in nuclei (UniProt Q92985). Nuclear enrichment is compatible with activation, but localisation alone does not measure phosphorylation (general IHC interpretation). |
| Tissue and cell selection | HPA describes nuclear expression in most tissues and distinct expression in lymphatic organs; it reports high staining in bone marrow hematopoietic cells and low staining in prostate glandular cells (HPA tissue IHC). Use the stated cell population when comparing sections; low is not negative. |
| Antibody evidence | HPA052757 and CAB017694 are IHC Approved; HPA052757 is also ICC Supported (HPA antibodies). The tissue profile is Approved with medium staining-to-RNA consistency (HPA tissue IHC). These labels support pattern review but do not make every unexpected cell signal specific. |
| Isoforms and modifications | UniProt lists four IRF7 isoforms and phosphorylation sites, including residues 471, 472, 475 and 477 (UniProt Q92985). The supplied record gives no antibody epitope or isoform coverage, so staining cannot identify an isoform or modification without separate validation. |
| IF/ICC Q: Where should IRF7 fluorescence appear? | A: Mainly in the nucleoplasm, with additional cytosolic signal (HPA subcellular: supported). HPA lists HEK293, PC-3 and U2OS ICC-IF images and marks HPA052757 ICC Supported (HPA subcellular; HPA antibodies). These IF observations guide localisation only; this section specifies no IF/ICC protocol. |
| Situation | Likely cause | Next action |
|---|---|---|
| No signal in the test section or the bone marrow positive check. | The positive check conflicts with reported high staining in hematopoietic cells (HPA tissue IHC); a run or specimen problem remains possible (general IHC practice). | Verify the positive cell population and run controls. Review antigen retrieval, primary antibody dilution and chromogenic detection against the IHC-validated antibody's instructions (general IHC practice); do not infer IRF7 absence from a failed check. |
| Only cytoplasmic color appears where a nuclear pattern was expected. | Cytoplasmic IRF7 can be real, but HPA describes predominantly nuclear tissue staining (UniProt Q92985; HPA tissue IHC). | Inspect nuclear counterstain and cell boundaries, compare a positive tissue and negative control, and score nuclear and cytoplasmic signal separately (general IHC practice). Do not call cytoplasmic staining alone proof of antibody failure. |
| Strong staining extends through cells or acellular areas and hides morphology. | Diffuse chromogen may reflect nonspecific antibody or detection background (general IHC practice). | Examine the negative control; review blocking, primary antibody dilution, washing and detection timing according to the assay controls (general IHC practice). Reassess only where cell boundaries and nuclear localisation remain visible. |
| Unexpected cells stain strongly, including cells in a tissue with a lower reported level. | HPA records low staining in prostate glandular cells, but its broader profile includes many high-staining populations (HPA tissue IHC). Cross-reactivity or endogenous detection activity is possible (general IHC practice). | Identify the stained cell type morphologically and compare negative controls and a reported positive population before judging specificity (general IHC practice). Treat a low HPA level as context, not a universal negative control (HPA tissue IHC). |
| The positive pattern differs between tissue regions or specimens. | HPA reports cell-specific staining across tissues and medium consistency between antibody staining and RNA expression (HPA tissue IHC). Mixed cell populations can change the apparent pattern (general IHC interpretation). | Score the named cell population and nuclear versus cytoplasmic signal separately; compare equivalent regions and the same run controls (general IHC practice). Avoid converting a whole-section average into a cell-specific claim. |
| Nuclear staining is being reported as proof of phosphorylated IRF7. | Active phosphorylated IRF7 selectively accumulates in nuclei, but nuclear localisation does not identify a modification site (UniProt Q92985; general IHC interpretation). | Report nuclear enrichment as a localisation observation. Reserve a phosphorylation claim for a separately validated modification-specific assay; the supplied antibody evidence does not establish such specificity (HPA antibodies). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | High | Protein (IHC) | HPA → |
| Cerebral cortex | Glial cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: IRF7 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot IRF7 staining in paraffin sections, with one note on translating the assay to immunofluorescence.
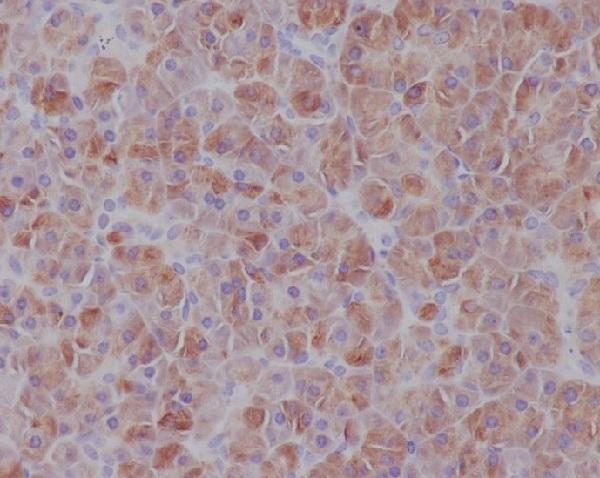
Both anti-IRF7 antibodies have real IHC images from human paraffin sections: spleen and pancreas (IHC captions). M00115 also lists IF/ICC and mouse/rat reactivity (catalog: M00115).
A00115-3 is listed for human IHC and shows staining in a paraffin-embedded human spleen section (catalog: A00115-3 applications and reactivity; A00115-3 IHC caption). M00115 is listed for human, mouse and rat IHC/IF/ICC and shows IHC staining in a paraffin-embedded human pancreas section (catalog: M00115 applications and reactivity; M00115 IHC caption).
Which to pick: Choose A00115-3 for human paraffin-section IHC when its documented EDTA pH 8 retrieval and DAB workflow suits the experiment (A00115-3 IHC caption). Choose M00115 for IF/ICC or cross-species experiments because it is a rabbit monoclonal listed for IF/ICC and human, mouse and rat reactivity (catalog: M00115 host, clone, applications and reactivity). Both IHC captions document paraffin sections; neither reports the fixative (A00115-3 and M00115 IHC captions).