This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic IHC for KANK2 using its observed cytoplasmic tissue pattern and cell-specific controls (HPA tissue IHC). Compare staining in cervical squamous epithelial cells, where expression is high, with pancreatic exocrine glandular cells, where it is undetected (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining in squamous epithelia and smooth muscle (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Cervix+4 more · see all | |
| Negative control | Pancreas+2 more · see all |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Staining shows low consistency with RNA expression (HPA tissue IHC) | |
| Regulation | Pro-apoptotic stimuli promote degradation (UniProt) | |
| Isoform / epitope | 3 isoforms; epitope coverage is unknown (UniProt) |
The catalog antibody’s IHC-P protocol is followed by published KANK2 staining methods for tumor and mouse lung sections (PMC11786046; PMC8946178).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A07999-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-KANK2, 1:100–1:500 starting range (standard) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | KANK2-positive staining in squamous epithelial cells of cervix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissues, including squamous epithelia and smooth muscle. No signal in the no-primary control. |
For paraffin-section IHC, expect mainly cytoplasmic KANK2 staining, especially in cervical and esophageal squamous epithelial cells and endometrial stromal cells (HPA tissue IHC: High; cytoplasmic profile). KANK2 has no transmembrane segment, and UniProt lists cytoplasmic and mitochondrial locations (UniProt Q63ZY3: topology; subcellular location). Interpret the tissue pattern cautiously: HPA rates its IHC evidence Approved but reports low consistency between antibody staining and RNA expression, pending external verification (HPA tissue IHC: reliability).
| Distinct cytoplasmic staining in cervical or esophageal squamous epithelium, or endometrial stromal cells. | This fits the reported high IHC signal in those cell populations and the tissue-wide cytoplasmic profile (HPA tissue IHC: High; cytoplasmic profile). Judge the named cells, rather than assigning one intensity to every cell in the section. |
| Predominantly nuclear staining replaces the expected cytoplasmic pattern in a positive IHC tissue. | Treat this as an IHC localisation mismatch and check morphology, detection background and antibody specificity (HPA tissue IHC: cytoplasmic profile). Nuclear signal alone is not proof of artefact: HPA reports approved nucleoplasmic localisation in ICC-IF (HPA subcellular: Nucleoplasm approved). |
| Strong signal appears in a cell population reported as unstained, such as pancreatic exocrine glandular cells. | Investigate antibody cross-reactivity or endogenous chromogenic detection activity before calling it KANK2 (HPA tissue IHC: pancreas, Not detected; standard IHC practice). A tissue-level result does not validate every unexpected cell-level signal. |
| Colour spreads across the section without clear cell boundaries or a reproducible intracellular pattern. | This is background rather than a convincing KANK2 pattern; inspect the no-primary control and review blocking, washes and detection conditions (standard IHC practice). HPA's reported pattern is cellular and cytoplasmic (HPA tissue IHC: cytoplasmic profile). |
| No staining appears in cervical or esophageal squamous cells when the run is otherwise readable. | A failed positive control is possible because both populations are reported High (HPA tissue IHC: cervix and esophagus). Review tissue identity, antibody application and the run controls before treating the test section as KANK2-negative (standard IHC practice). |
| Which compartment should I use for IHC scoring? | Use the cytoplasmic tissue-IHC profile for paraffin sections (HPA tissue IHC: cytoplasmic profile). UniProt also lists mitochondria, but the supplied tissue-IHC record does not resolve a mitochondrial pattern (UniProt Q63ZY3: subcellular location; HPA tissue IHC: profile). |
| What if I compare the separate IF/ICC guide? | HPA ICC-IF reports mainly nucleoplasm, with additional cytosol (HPA subcellular: Nucleoplasm approved; Cytosol supported). That assay-specific observation merits comparison, not automatic transfer into an IHC scoring rule; HPA015643 is IHC Approved and ICC Uncertain (HPA antibodies). |
| How firm is tissue selection? | High staining is reported in three named cell populations, while pancreatic exocrine, stomach glandular and bladder urothelial cells are Not detected (HPA tissue IHC). HPA also reports low tissue RNA specificity and low staining–RNA consistency, so these are comparison tissues, not absolute biological controls (HPA tissue IHC: reliability; RNA specificity). |
| Do protein features predict a different slide pattern? | UniProt records three isoforms, no signal peptide or propeptide, and no transmembrane segment (UniProt Q63ZY3: isoforms; processing; topology). Those annotations do not establish which isoform an antibody detects or predict fixation sensitivity; the supplied evidence gives neither an epitope map nor a target-specific fixation effect. |
| Situation | Likely cause | Next action |
|---|---|---|
| Positive comparison tissue is blank. | The expected High cell population may be absent from the examined area, or the IHC run may have failed (HPA tissue IHC: cervix, esophagus and endometrium High; standard IHC practice). | Confirm the named cells on the counterstain, then check the antibody and detection controls and repeat alongside a known-positive section (standard IHC practice). |
| Colour is diffuse or covers tissue and empty spaces. | Nonspecific binding or detection background can obscure the reported cytoplasmic pattern (standard IHC practice; HPA tissue IHC: cytoplasmic profile). | Compare a no-primary control; review blocking, washing and detection exposure, then score only discrete cellular signal (standard IHC practice). |
| Nuclei dominate the paraffin-section stain. | The result differs from HPA tissue IHC, although ICC-IF separately reports nucleoplasmic KANK2 (HPA tissue IHC: cytoplasmic profile; HPA subcellular: Nucleoplasm approved). | Check the no-primary control and repeat IHC in a reported high-staining tissue before interpreting the compartment (standard IHC practice; HPA tissue IHC: High). |
| Pancreatic exocrine cells stain strongly. | This conflicts with their Not detected HPA IHC result; cross-reactivity or endogenous detection activity is possible (HPA tissue IHC: pancreas; standard IHC practice). | Check detection-only and no-primary controls, then compare staining in a reported high-staining cell population (standard IHC practice; HPA tissue IHC: High). |
| A low-staining tissue seems negative. | A faint signal may be hard to separate from background in cells HPA rates Low (HPA tissue IHC: cerebellar granular-layer cells, caudate glia and others Low). | Use a reported High cell population to assess run performance; avoid treating a Low tissue alone as a failed assay (HPA tissue IHC: High and Low; standard IHC practice). |
| Staining varies between sections despite readable controls. | Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation. | Compare matched cell populations and run controls, record the variation, and avoid inferring a target-specific fixation effect from these data (standard IHC practice; HPA tissue IHC: reliability). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Cervix | Squamous epithelial cells | High | Protein (IHC) | HPA → |
| Endometrium | Cells in endometrial stroma | High | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | High | Protein (IHC) | HPA → |
| Adipose tissue | Adipocytes | Medium | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
Troubleshoot KANK2 chromogenic IHC in paraffin sections by checking retrieval, compartment, cell identity and staining controls before interpreting intensity.
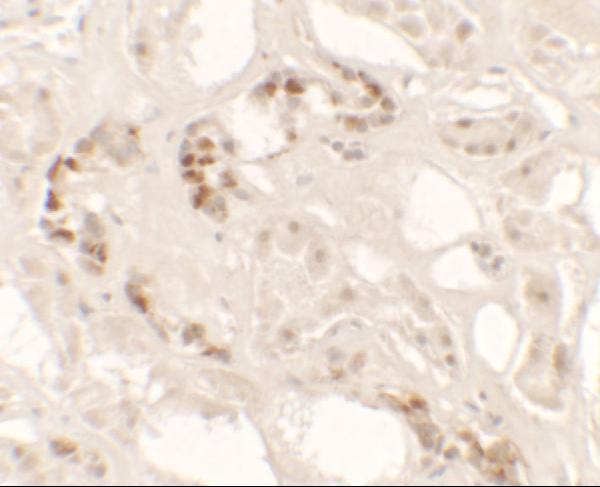
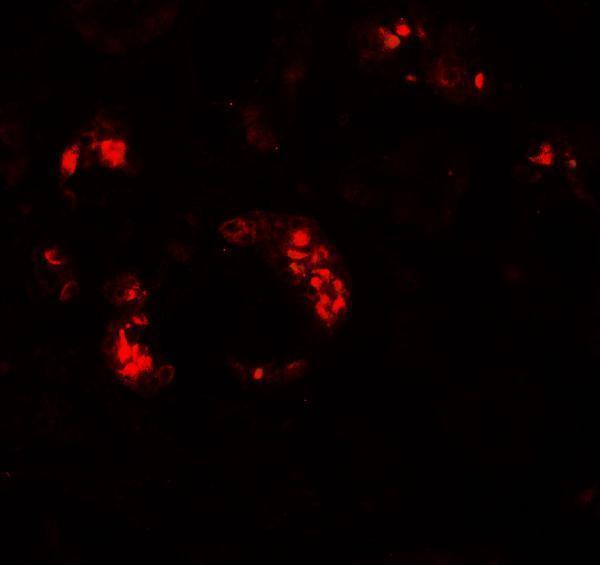
A07999-1 has IHC-P and IF applications (catalog: applications), with images from human kidney tissue (catalog: IHC and IF image captions). Human, mouse, and rat are listed as reactive (catalog: reactivity).
A07999-1 will render with an IHC image of human kidney tissue stained at 2.5 μg/ml (catalog: IHC image caption). Its IF image also shows human kidney tissue, stained at 20 μg/ml (catalog: IF image caption).
Which to pick: For paraffin-section tissue IHC, choose A07999-1 (catalog: IHC-P application); its human kidney IHC caption does not report the fixative (catalog: IHC image caption). For IF, A07999-1 has a human kidney image (catalog: IF image caption); ICC validation is unreported (catalog: applications and image captions). Human, mouse, and rat reactivity is listed for A07999-1, but its IHC and IF images document human tissue only (catalog: reactivity and image captions).