LAPTM5 / Lysosomal-associated transmembrane protein 5 · IHC design guide

Design Immunohistochemistry for LAPTM5

Plan LAPTM5 IHC-P around granular cytoplasmic staining in tissue (HPA tissue IHC). This guide covers control selection and the catalog antibody's 1:50–1:100 starting dilution (datasheet).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for LAPTM5 (IHC for LAPTM5): expected localisation Granular cytoplasm (HPA tissue IHC); lysosome membrane (UniProt), antibody A09673, validated IHC image, and IHC protocol steps
Printable LAPTM5 IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); lysosome membrane (UniProt), antibody A09673, controls and protocol steps. Open the full LAPTM5 IHC guide →

LAPTM5 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); lysosome membrane (UniProt)
Staining pattern Granular cytoplasm in glandular cells and hepatocytes (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep formalin fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Glandular cells outside immune tissues can stain strongly (HPA tissue IHC)
Regulation Adult hematopoietic tissue enrichment (UniProt)
Isoform / epitope No isoforms or processing annotated; epitope side unresolved (UniProt)
Section 1

Recommended LAPTM5 IHC & IF Protocols

The catalog antibody protocol (datasheet) is followed by three published paraffin-section IHC protocols for LAPTM5 (PMC13066990; PMC12750714; PMC2746316).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleFFPE human lymph node tissue (datasheet A09673)
FixationImage formalin-fixed; duration unreported (datasheet A09673); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-LAPTM5, 1:50-1:100 (datasheet A09673)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultLAPTM5-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Granular cytoplasmic expression in several different tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page retrieval rule); a published LAPTM5 protocol also uses boiling citrate pH 6.0 (PMC2746316).
Section 2

What Is the Expected LAPTM5 Staining Pattern?

LAPTM5 is annotated at the lysosome membrane with 5 transmembrane segments (UniProt Q13571 topology). In paraffin sections, expect granular cytoplasmic staining where protein is detected; HPA reports high staining in several glandular cell populations and hepatocytes (HPA: tissue IHC). UniProt also describes preferential expression in hematopoietic tissues (UniProt Q13571 tissue specificity). The HPA tissue pattern is Approved, with external verification pending (HPA: tissue IHC reliability).

What am I looking at on my slide?
Discrete cytoplasmic granules in glandular cells or hepatocytes, with clear nuclei.This matches HPA's granular cytoplasmic profile and its high IHC staining in several glandular tissues and liver hepatocytes (HPA: tissue IHC). The pattern is compatible with a lysosome-membrane protein, though chromogenic granules alone cannot identify individual organelles (UniProt Q13571 subcellular location; general IHC practice).
Predominantly nuclear staining or a smooth cell-surface rim replaces cytoplasmic granules.Treat this as a compartment mismatch and investigate artefact or nonspecific binding (HPA: granular cytoplasmic tissue profile; UniProt Q13571 lysosome membrane; general IHC practice). Do not score the unexpected compartment as LAPTM5 solely because the tissue contains cells that HPA reports as positive (HPA: tissue IHC).
Strong signal appears in adipocytes, respiratory epithelium, myocytes or fibroblasts.HPA reports those specified cell populations as not detected in its sampled tissues (HPA: tissue IHC). Review cell identity, nearby stained cells, antibody cross-reactivity and endogenous detection activity before calling them positive (general IHC practice); an HPA negative observation is not proof that every specimen will be negative.
A uniform tint covers cells, stroma and empty areas, obscuring granules.This does not reproduce HPA's granular cytoplasmic profile (HPA: tissue IHC). Compare a reagent control and review blocking, washes, antibody concentration and chromogen development (general IHC practice). Interpret cell-specific staining only after the background permits a clear comparison with adjacent unstained structures.
No signal appears in a section selected for HPA high staining.First verify that the expected cell population is present: HPA identifies high staining in liver hepatocytes and glandular cells in several named tissues (HPA: tissue IHC). If present, review antibody and detection controls, retrieval conditions and section handling (general IHC practice); the missing signal alone cannot establish absent LAPTM5.
💡Expected LAPTM5 appearanceCall a convincing positive granular cytoplasmic staining in an HPA high cell population, such as liver hepatocytes or listed glandular cells; broad nuclear staining or uniform haze is a suspect result (HPA: tissue IHC; general IHC practice).
How each factor affects the staining
Topology and compartmentUniProt places LAPTM5 at the lysosome membrane and annotates 5 transmembrane segments (UniProt Q13571 topology and subcellular location). Use that annotation to assess compartment plausibility; it does not identify the catalog antibody's epitope or establish an antigen-retrieval condition.
Choice of tissue and cell populationHPA records high IHC staining in liver hepatocytes and multiple glandular cell populations, but low staining in spleen red-pulp cells and tonsil non-germinal-center cells (HPA: tissue IHC). UniProt describes high expression in lymphoid and myeloid tissues (UniProt Q13571 tissue specificity); score the specified cells rather than assigning one intensity to an entire organ.
Strength of IHC evidenceThe tissue profile is Approved with external verification pending, and antibody HPA051293 is Approved for IHC (HPA: tissue IHC reliability; HPA: antibody validation). Those labels support using the observed pattern as a reference while keeping unexpected staining provisional; they do not establish independent confirmation for this section.
IF/ICC Q: Should the paraffin IHC pattern be applied to IF/ICC?A: Use the separate IF/ICC guide for that application. HPA reports approved cytosolic localization in ICC-IF images but rates HPA051293 ICC as Uncertain (HPA: subcellular ICC-IF; HPA: antibody validation). That observation needs its own interpretation alongside UniProt's lysosome-membrane annotation (UniProt Q13571 subcellular location).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
An expected high-staining cell population is blank.The relevant cells may be absent, or the IHC workflow may have failed (HPA: tissue IHC; general IHC practice).Confirm cell identity and run a known-positive section with the same detection workflow; then review retrieval and reagent performance (general IHC practice). No LAPTM5-specific fixation or retrieval sensitivity is established by these sources.
Staining is cytoplasmic but broadly diffuse.It diverges from HPA's granular tissue-IHC profile, although HPA describes cytosolic localization in ICC-IF (HPA: tissue IHC; HPA: subcellular ICC-IF).Assess granules against a comparable positive section and reagent control; check antibody concentration and washes before scoring diffuse color as specific (general IHC practice).
Nuclei dominate the stain.Nuclear localization conflicts with the HPA tissue profile and UniProt lysosome-membrane annotation (HPA: tissue IHC; UniProt Q13571 subcellular location).Inspect the negative reagent control and detection background, then reassess the primary antibody conditions (general IHC practice). Record the nuclear result separately from expected LAPTM5 staining.
A reportedly negative cell population stains strongly.Cross-reactivity, endogenous detection activity or cell misidentification are possible (general IHC practice); HPA reports no detection in the specified comparison cells (HPA: tissue IHC).Verify the cell type and compare reagent controls and adjacent structures (general IHC practice). Avoid treating an HPA observation from one tissue as a universal negative rule.
Color extends across stroma or section edges.A broad deposit may reflect background or uneven reagent exposure rather than HPA's cell-associated granules (general IHC practice; HPA: tissue IHC).Compare a control section, inspect wash and blocking steps, and limit scoring to discrete cell-associated signal (general IHC practice).
Spleen or tonsil looks weaker than a glandular comparison section.HPA lists low staining in spleen red-pulp and tonsil non-germinal-center cells while listing high staining in several glandular cell populations (HPA: tissue IHC).Compare the named cell populations at equivalent detection settings and preserve their recorded intensity categories (general IHC practice; HPA: tissue IHC).

Sample controls for LAPTM5 IHC & IF

🧪Run appendix first: its glandular cells must stain (HPA: High in appendix glandular cells). Use adipose tissue as the negative tissue, where adipocytes are not detected (HPA: Not detected in adipocytes); on the appendix slide, assess non-glandular cells for background, but do not assume leukocytes are negative (UniProt Q13571: preferential expression in hematopoietic tissues).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show LAPTM5 in Rh30, U2OS, with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and an isotype control matched to the primary antibody’s host and subclass for a monoclonal antibody, or host-matched normal IgG for a polyclonal antibody. Use knockout tissue or cells as a biological negative, or a peptide-block control if the immunizing peptide is available; quench endogenous peroxidase before chromogenic detection, particularly in leukocyte-rich areas (UniProt Q13571: high expression in lymphoid and myeloid tissues).
⚠️Feasibility: The selected product caption documents formalin-fixed, paraffin-embedded human lymph node stained with peroxidase and DAB (A09673 tissue-IHC caption), but reports no fixation duration or target-specific fixation effect. An antigen-retrieval requirement or condition is unreported, so optimize retrieval against the positive and negative controls. Neither frozen sections nor IF can be judged easier from the supplied evidence; immune cells within the appendix may complicate interpretation of glandular staining (UniProt Q13571: high expression in lymphoid and myeloid tissues).

HPA tissue IHC evidence for LAPTM5

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Placenta Decidual cells Not detected Protein (IHC) HPA →
Section 3

Advanced LAPTM5 IHC Tips

For LAPTM5 chromogenic IHC, interpret staining in light of its lysosomal membrane annotation and the tissue and cell patterns reported in the supplied evidence.

How should I retrieve LAPTM5 in paraffin sections with weak staining?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 min (page retrieval rule: cytoplasmic / membrane antigen). Because LAPTM5 has 5 transmembrane segments (UniProt Q13571 topology), compare retrieved and unretrieved serial sections to see whether retrieval improves the expected granular cytoplasmic pattern (HPA tissue IHC profile). Let sections cool in retrieval buffer before proceeding, and keep antibody concentration and detection conditions identical across the comparison (standard IHC practice). If staining remains weak, adjust heating duration on replicate sections before trying another buffer, while checking that background and tissue morphology remain acceptable (standard IHC practice).
Does formalin fixation alter LAPTM5 staining in paraffin sections?
Target-specific sensitivity to fixation duration is unknown from the supplied evidence, so do not assign a LAPTM5-specific fixation limit (supplied fixation evidence). An IHC image of formalin-fixed, paraffin-embedded human lymph node with antibody A09673 establishes use under those conditions, but gives no fixation comparison (A09673 tissue-IHC caption). When staining varies between specimens, compare sections with documented fixation histories using the same citrate pH 6.0 retrieval and detection conditions (page retrieval rule; standard IHC practice). Evaluate whether differences persist in morphologically intact areas and in comparable cell populations before attributing them to fixation (standard IHC practice; UniProt Q13571 tissue specificity).
Where should convincing LAPTM5 staining appear in tissue?
Look for granular cytoplasmic staining in appropriately identified cells, as reported for tissue IHC (HPA tissue IHC profile). This pattern is consistent with LAPTM5's lysosome membrane annotation and 5 transmembrane segments, although chromogenic IHC alone cannot prove organelle identity (UniProt Q13571 subcellular annotation and topology; standard IHC interpretation). A separate cell imaging record calls the main location cytosolic, so resolve an apparently diffuse signal with morphology, controls and, if needed, a lysosomal marker in a separate assay (HPA subcellular summary; standard IHC practice). Treat isolated nuclear or uniform surface staining cautiously because neither location is the supplied tissue pattern (HPA tissue IHC profile; UniProt Q13571 subcellular annotation).
How does epitope placement affect interpretation of LAPTM5 IHC?
The selected antibody is described as N-terminal, but its precise recognized residues are not supplied (A09673 tissue-IHC caption). LAPTM5 is annotated as a 262-residue chain with 5 transmembrane segments, 0 annotated isoforms and a phosphotyrosine at residue 259 (UniProt Q13571 sequence, topology, isoforms and modified residues). Do not infer that staining distinguishes an isoform, detects phosphorylation, or reports the accessibility of a particular membrane-facing segment from this caption (A09673 tissue-IHC caption; UniProt Q13571 annotations). If staining differs between preparations, compare retrieval and antibody controls first; establish epitope sidedness experimentally before interpreting that difference as membrane topology (standard IHC practice).
How can IF help assess ambiguous LAPTM5 IHC staining?
Use IF on an adjacent preparation to compare LAPTM5 with a marker for the cell population being assessed, such as a validated marker of a lymphoid or myeloid population (UniProt Q13571 tissue specificity; standard IF practice). Include a lysosomal marker when testing whether puncta match the lysosome membrane annotation, while recognizing that proximity in images does not establish direct binding (UniProt Q13571 subcellular annotation; standard IF interpretation). Choose fluorophores after inspecting the tissue's autofluorescence and include single-channel controls for multiplex imaging (standard IF practice). Because the N-terminal antibody's exact epitope and membrane sidedness are unspecified, validate permeabilisation empirically for epitope access instead of assuming which side to expose (A09673 tissue-IHC caption; UniProt Q13571 topology).
What explains widespread brown background in LAPTM5 IHC?
First compare a no-primary control with the stained section to identify signal from detection reagents or endogenous peroxidase (standard chromogenic IHC practice). Use an appropriate peroxidase block before DAB development, then assess whether background tracks red blood cells, damaged tissue or section edges (standard chromogenic IHC practice). Review primary antibody concentration, blocking and wash conditions without calling diffuse brown deposition LAPTM5-positive, because the supplied tissue profile describes granular cytoplasmic expression (HPA tissue IHC profile; standard IHC practice). Preserve the same retrieval and development conditions across controls and test sections so that a change in background can be assigned to the step varied (standard IHC practice).
How should I quantify LAPTM5 staining across tissue samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue region before scoring, because LAPTM5 is preferentially expressed in hematopoietic tissues and HPA reports cell-specific staining differences (UniProt Q13571 tissue specificity; HPA tissue IHC). Record the percentage of positive cells and staining intensity, or calculate an H-score; for infiltrating populations, report positive-cell density per mm² of viable tissue (standard IHC quantification practice). Apply the same threshold and acquisition or scoring conditions to every sample, and exclude necrotic or folded regions (standard IHC practice). Normalise counts to the number of eligible cells or viable tissue area, and report the denominator so changing cell composition is distinguishable from changing staining (standard IHC quantification practice).
How can I distinguish genuine LAPTM5 positivity from artefact?
Give greatest weight to reproducible granular cytoplasmic staining in morphologically identified cells, consistent with the tissue IHC profile and lysosome membrane annotation (HPA tissue IHC profile; UniProt Q13571 subcellular annotation). Check the claimed cell population against tissue context: HPA reports high hepatocyte staining in liver but no detected staining in adipocytes of adipose tissue, so neither all epithelial cells nor all stromal cells should be assumed positive (HPA tissue IHC positive and negative lists). Discount staining confined to cut edges, folds or necrotic areas, and compare no-primary controls for endogenous enzyme signal (standard chromogenic IHC practice). Confirm uncertain calls with an independent antibody or an orthogonal assay before assigning biological meaning (standard IHC validation practice).
Boster reagents

Best LAPTM5 / Lysosomal-associated transmembrane protein 5 IHC Antibodies

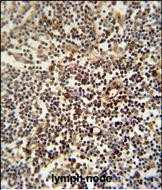
The IHC-validated antibody A09673 has real chromogenic IHC data from formalin-fixed, paraffin-embedded human lymph node (catalog image caption); no IF image is provided (catalog IF image list).

Real IHC data LAPTM5 antibody (N-term) immunohistochemistry analysis in formalin fixed and paraffin embedded human lymph node followed by peroxidase conjugation of the secondary antibody and DAB staining. This data demonstrates the use of the LAPTM5 antibody (N-term) for immunohistochemistry. Clinical relevance has not been evaluated.
Anti-LAPTM5 Antibody (N-term)
Cat # A09673

A09673 is listed for human IHC-P (catalog applications and reactivity). Its image shows DAB staining of formalin-fixed, paraffin-embedded human lymph node (catalog image caption).

Which to pick: Choose A09673 for human tissue IHC: it is a rabbit polyclonal antibody listed for IHC-P at 1:50–1:100 (catalog host, dilution record, applications, and reactivity), with an image from formalin-fixed, paraffin-embedded human lymph node (catalog image caption). No SKU here is validated for IF/ICC or another species (catalog applications, reactivity, and IF image list).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q13571 (LAPM5_HUMAN, Lysosomal-associated transmembrane protein 5).
  2. Human Protein Atlas. LAPTM5 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. LAPTM5 subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. LAPTM5 antibody validation summary (1 antibodies).
  5. LAPTM5-dependent lipophagy enhances ferroptosis sensitivity in glioma cells. Translational cancer research 2026 — PMC13066990.
  6. LAPTM5 drives omental metastasis in high-grade serous ovarian cancer via TGF-β/Smad-mediated epithelial plasticity. Journal of translational medicine 2025 — PMC12750714.
  7. Lysosomal-associated protein multispanning transmembrane 5 gene (LAPTM5) is associated with spontaneous regression of neuroblastomas. PloS one 2009 — PMC2746316.
  8. Exploration of efferocytosis-related genes as potential therapeutic targets in endometrial cancer. Translational cancer research 2025 — PMC12611400.
  9. PubMed PMID:8661146 — UniProt-cited evidence.
  10. PubMed PMID:7788527 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.