This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan LIMA1 chromogenic IHC-P around the membranous pattern reported in most tissues (HPA tissue IHC). Start with 2 μg/mL in paraffin sections (datasheet A05231-1), and compare breast glandular cells with heart cardiomyocytes (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Plasma membrane in most tissues (HPA tissue IHC) | |
| Staining pattern | Membranous staining in most tissues (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A05231-1) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Caudate+4 more · see all |
| Fixation | Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Antibody staining and RNA show medium consistency (HPA tissue IHC) | |
| Regulation | Intensity regulation not established (UniProt) | |
| Isoform / epitope | 5 isoforms; check epitope coverage; no transmembrane segment (UniProt) |
The catalog antibody protocol is complemented by published LIMA1 IHC methods for head and neck cancer tissue microarrays and liver sections (PMC12340046; PMC11140962).
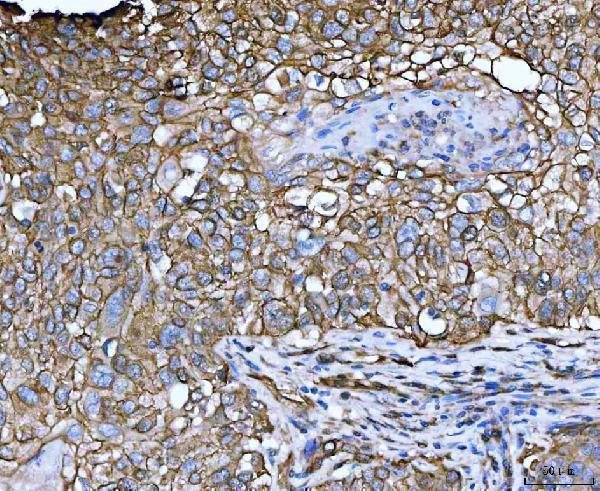
| Sample | Paraffin-embedded human lung squamous cell carcinoma tissue; fixative not specified (datasheet A05231-1) |
| Fixation | Image fixative and duration unreported (datasheet A05231-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A05231-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A05231-1) |
| Primary antibody | Rabbit anti-LIMA1, 2-5 μg/ml (datasheet A05231-1) |
| Primary incubation | Overnight at 4 °C (datasheet A05231-1) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A05231-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | LIMA1-positive staining in endocrine cells of appendix (HPA tissue IHC: High). HPA tissue profile: Plasma membrane expression in most tissues. No signal in the no-primary control. |
In paraffin-section IHC, expect LIMA1 mainly along the plasma membrane, with possible cytoskeletal staining (HPA: plasma membrane expression in most tissues; UniProt Q9UHB6: cytoskeleton and cell junction localization). Breast and cervical glandular cells and intestinal endocrine cells are documented strong examples (HPA: High in these cells). HPA rates its tissue IHC evidence Enhanced, with medium consistency between staining and RNA expression (HPA: reliability summary).
| Membrane-associated staining in breast or cervical glandular cells, or in appendix, colon or duodenal endocrine cells. | This fits documented High staining in those specific cell populations (HPA: tissue IHC). Judge the labelled cells, not the organ as a whole; an unstained neighbouring cell type does not by itself contradict the reference pattern (HPA: cell-specific tissue entries). |
| Staining follows cell borders, with some cytoplasmic or filament-associated signal. | A membrane-dominant pattern matches tissue IHC (HPA: plasma membrane expression in most tissues). Cytoplasmic and actin-associated localization is also plausible (UniProt Q9UHB6: cytoplasm and cytoskeleton; HPA: ICC-IF actin filaments supported). Do not require every positive cell to show an exclusively membranous outline. |
| Strong, predominantly nuclear staining replaces the expected membrane-associated pattern. | Treat this as a possible artefact or off-target signal before scoring it as LIMA1: the supplied localizations are membrane, cytoplasm, cytoskeleton and adhesions, with no nuclear location listed (UniProt Q9UHB6: subcellular location; HPA: subcellular summary). Review controls and staining distribution (standard IHC practice). |
| Strong signal appears in a cell population listed as Not detected, such as cardiomyocytes or ovarian stromal cells. | Check for cross-reactivity or endogenous detection activity (standard IHC practice). The HPA entries concern Not detected staining in those named cell types, not every cell in heart or ovary (HPA: tissue IHC). Compare with an appropriate control before interpreting the unexpected signal. |
| Diffuse color covers the section, or a documented positive population has no discernible signal. | Diffuse color makes compartment and cell-type scoring unreliable; absent signal in a documented High population leaves assay performance unresolved (standard IHC practice; HPA: tissue IHC). Compare positive and negative controls, then assess background and detection before concluding that the specimen lacks LIMA1. |
| Cell population chosen for interpretation | Use a documented High population, such as breast glandular cells or duodenal endocrine cells, to assess whether the assay can reveal the expected pattern (HPA: tissue IHC). HPA also lists Not detected cardiomyocytes and ovarian stromal cells; those labels do not describe whole-organ expression (HPA: tissue IHC). |
| Membrane association and topology | A border-associated signal is consistent with the tissue profile, but LIMA1 has no transmembrane segment (HPA: plasma membrane expression in most tissues; UniProt Q9UHB6: topology). Interpret the pattern as localization, not proof that the protein spans the membrane; cytoskeletal and focal-adhesion locations are also reported (UniProt Q9UHB6: subcellular location). |
| Isoforms and antibody validation | UniProt lists 5 isoforms, including Alpha and Beta, so an isoform-specific interpretation requires epitope information that is not supplied here (UniProt Q9UHB6: isoforms). HPA reports Enhanced IHC validation for HPA023871 and HPA052645; that summary does not establish how an unspecified catalog antibody detects each isoform (HPA: antibody validation). |
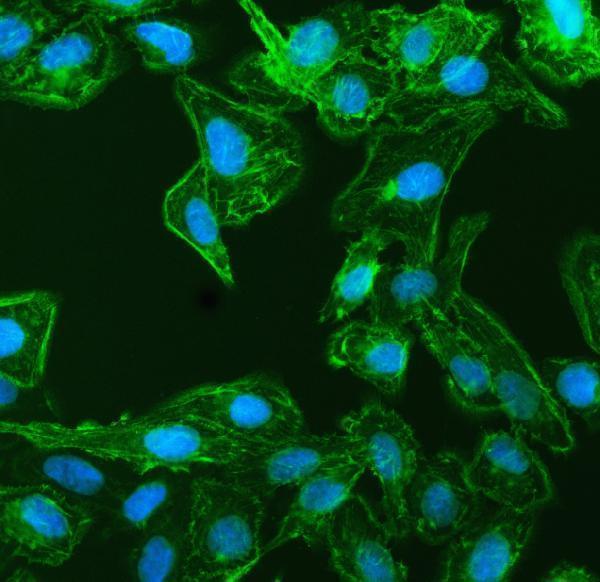
| IF/ICC Q&A: Should its signal match the IHC slide exactly? | No exact match is established: HPA ICC-IF places LIMA1 mainly at actin filaments (supported) and plasma membrane (uncertain), with supported focal-adhesion and cytosol locations (HPA: subcellular summary). Use that as localization context for this IHC guide, not as an IF/ICC protocol or an equivalence claim. |
| Situation | Likely cause | Next action |
|---|---|---|
| No stain in a breast glandular-cell or duodenal endocrine-cell positive reference. | The expected High population is not visible, leaving tissue selection, staining or detection as possibilities (HPA: tissue IHC; standard IHC practice). HPA does not supply a LIMA1-specific fixation or retrieval effect. | Confirm the reference contains the named cells, then check the primary-antibody, detection and counterstain steps with controls (standard IHC practice). If retrieval is adjusted, treat it as general assay optimization, not a demonstrated LIMA1-specific requirement. |
| Uniform brown haze obscures cell borders. | Background from blocking, washing or detection can prevent reliable localization scoring (standard chromogenic IHC practice). The supplied HPA pattern is membrane-associated rather than section-wide (HPA: tissue IHC profile). | Inspect the no-primary control, review blocking and washes, and adjust detection conditions according to the assay controls (standard IHC practice). Score LIMA1 only after cell boundaries and the expected positive population are distinguishable. |
| Nuclei dominate the stain while expected cell borders remain faint. | The compartment conflicts with the reported membrane and cytoskeletal locations (HPA: tissue IHC and subcellular summary; UniProt Q9UHB6: subcellular location). This raises concern for nonspecific signal rather than confirming nuclear LIMA1. | Compare the no-primary control and a documented positive cell population; review staining and detection conditions before assigning positivity (standard IHC practice; HPA: High in breast glandular cells). |
| Cardiomyocytes or ovarian stromal cells stain strongly. | Those specific populations are Not detected in the HPA tissue entries (HPA: tissue IHC). Cross-reactivity or endogenous detection activity is possible (standard IHC practice), although other cells in the same organ cannot be judged from those entries. | Identify the stained cell type, compare an appropriate negative control, and check endogenous-activity blocking where relevant to the detection chemistry (standard IHC practice). Do not score the whole organ as discordant from one cell-type observation. |
| Cytoplasmic staining is present without a crisp membrane outline. | LIMA1 has reported cytoplasmic and cytoskeletal locations, so this is not automatically false (UniProt Q9UHB6: subcellular location). Tissue IHC nevertheless describes plasma membrane expression in most tissues (HPA: tissue profile). | Check whether staining follows identifiable cells or structures and compare it with a documented High reference (HPA: tissue IHC; standard IHC practice). If signal remains diffuse, record localization as uncertain rather than forcing a membrane score. |
| Two antibodies give different-looking IHC patterns. | HPA reports Enhanced IHC validation for HPA023871 and HPA052645, but the supplied record does not map their epitopes to LIMA1's 5 isoforms (HPA: antibody validation; UniProt Q9UHB6: isoforms). | Compare each antibody's staining in the same documented positive cell population and against its controls (HPA: tissue IHC; standard IHC practice). Record the discordance; do not attribute it to an isoform or processing event without supporting epitope evidence. |
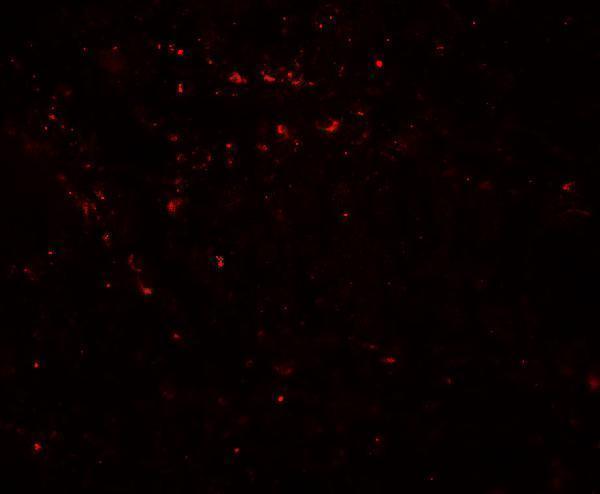


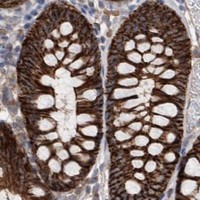
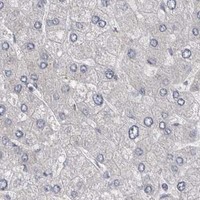


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Endocrine cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Cervix | Glandular cells | High | Protein (IHC) | HPA → |
| Colon | Endocrine cells | High | Protein (IHC) | HPA → |
| Duodenum | Endocrine cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Cerebral cortex | Endothelial cells | Not detected | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Not detected | Protein (IHC) | HPA → |
| Hippocampus | Glial cells | Not detected | Protein (IHC) | HPA → |
| Liver | Cholangiocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot chromogenic LIMA1 IHC by checking retrieval, compartment, cell identity and controls before comparing staining across sections.
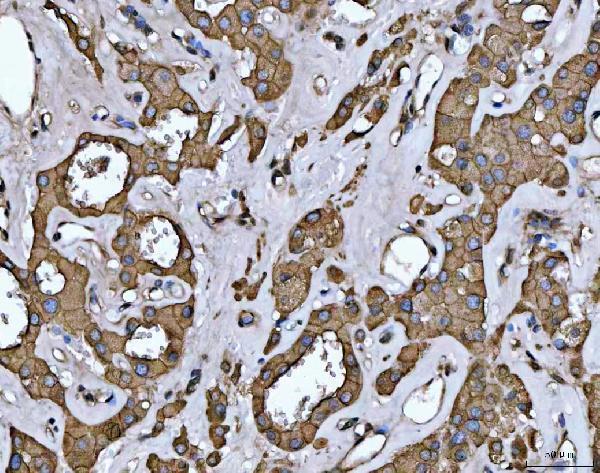
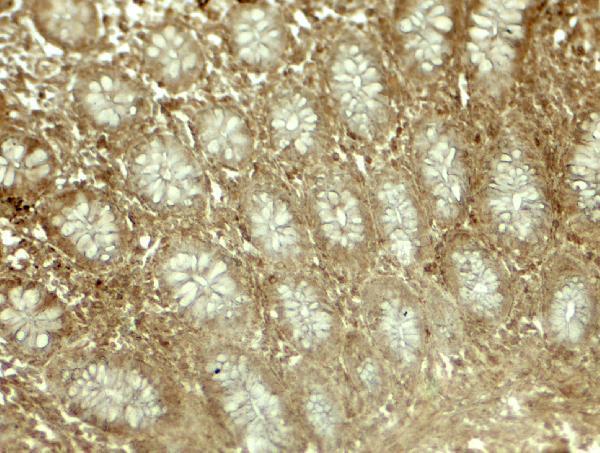
Two human-reactive anti-LIMA1 antibodies have IHC images from lung squamous cell carcinoma and colon tissue, respectively; both also have IF data (catalog: A05231-1 and A05231 image captions).
A05231-1 has IHC images from paraffin sections of human lung squamous cell carcinoma and kidney oncocytoma, plus IF data from U20S cells (catalog: A05231-1 image captions). A05231 has IHC and IF images from human colon tissue and lists IHC-P and IF applications (catalog: A05231 image captions and applications).
Which to pick: For tissue IHC, choose A05231-1 when an explicitly documented paraffin-section workflow is useful: its lung image caption specifies EDTA retrieval at pH 8.0 and 2 μg/mL primary antibody (catalog: A05231-1 IHC caption). For IF/ICC, A05231-1 has a cell-based IF example at 5 μg/mL, while A05231 has a colon-tissue IF example at 20 μg/mL (catalog: respective IF captions). Neither has documented cross-species reactivity; both list human only, and the fixative is unreported in their IHC captions (catalog: reactivity and IHC captions).