This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan MC4R paraffin IHC with the catalog antibody and score cytoplasmic and membranous staining (HPA tissue IHC; datasheet A00619-2). Interpret positive staining cautiously: HPA rates its tissue IHC evidence uncertain because staining and RNA expression show very low consistency (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic and membranous tissue staining (HPA tissue IHC) | |
| Staining pattern | Most tissues show cytoplasmic and membranous staining (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A00619-2) | |
| Positive control | Bone marrow+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Poor staining–RNA concordance; verify specificity (HPA tissue IHC) | |
| Regulation | Expression regulation is not specified (UniProt) | |
| Isoform / epitope | No annotated isoforms; epitope side matters across 7 transmembrane segments (UniProt) |
The catalog antibody has an IHC-P protocol; the published protocol below uses fluorescent staining of MC4R-GFP mouse brain sections (PMC3652326).
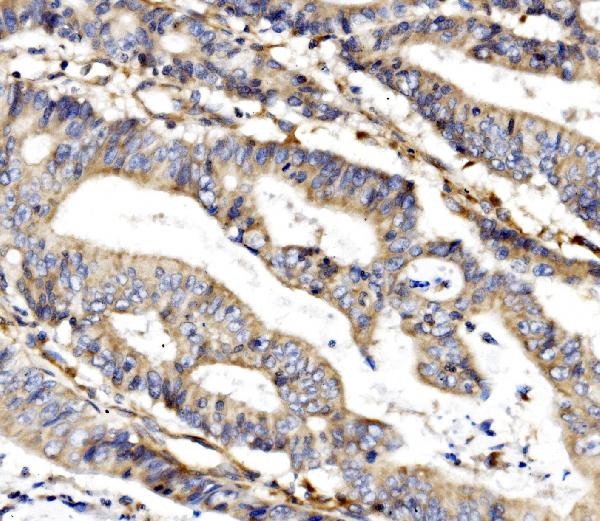
| Sample | Paraffin-embedded human rectal cancer tissue; fixative not specified (datasheet A00619-2) |
| Fixation | Image fixative and duration unreported (datasheet A00619-2); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A00619-2); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A00619-2) |
| Primary antibody | Rabbit anti-MC4R, 0.5-1μg/ml (datasheet A00619-2) |
| Primary incubation | Overnight at 4 °C (datasheet A00619-2) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet A00619-2) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | MC4R-positive staining in hematopoietic cells of bone marrow (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and membranous expression in most tissues. No signal in the no-primary control. |
MC4R is a 7-transmembrane receptor assigned to the cell membrane and cilium membrane (UniProt P32245 topology and subcellular location). For paraffin-section IHC, assess membranous staining in HPA-reported cells such as placental trophoblasts and kidney tubular cells; HPA also describes cytoplasmic staining (HPA tissue IHC: High in both cell types; cytoplasmic and membranous profile). Treat the pattern cautiously: tissue IHC reliability is Uncertain, with very low agreement between antibody staining and RNA expression (HPA tissue IHC).
| Cell outlines stain in placental trophoblasts or kidney tubular cells, with some cytoplasmic signal. | Membrane localisation fits receptor topology (UniProt P32245 topology). These cells have High HPA staining, and HPA describes both membranous and cytoplasmic signal (HPA tissue IHC). Reproducible cell-associated staining is encouraging, but the HPA reliability rating is Uncertain (HPA tissue IHC). |
| Strong nuclear staining dominates while cell outlines are indistinct. | Nuclear dominance conflicts with the annotated cell and cilium membrane locations (UniProt P32245 subcellular location). Review the negative control and detection background before calling it MC4R; the available HPA tissue pattern has Uncertain reliability (HPA tissue IHC; general IHC practice). |
| Adipocytes or prostate glandular cells stain as strongly as the selected positive cells. | HPA lists those cell types as Not detected, while its tissue staining overall is Uncertain (HPA tissue IHC). Compare staining with a negative control and assess cross-reactivity or endogenous detection activity; staining alone cannot identify which cause applies (general IHC practice). |
| Color spreads across stroma, lumens, or the whole section without clear cell boundaries. | A diffuse field is difficult to assign to the reported membranous and cytoplasmic cell-associated profile (HPA tissue IHC). Check control slides for background from blocking, secondary detection, or chromogen development before scoring cells (general IHC practice). |
| No signal appears in a placental trophoblast or kidney tubular cell section. | Both are HPA High examples, so absence warrants a run-level check, although they are not independently verified positive controls here (HPA tissue IHC: High; reliability Uncertain). Check section quality, primary incubation, detection reagents, and counterstain, then compare a control processed in the same run (general IHC practice). |
| Compartment and epitope orientation | MC4R has 7 membrane spans and annotated extracellular and cytoplasmic regions (UniProt P32245 topology). Interpret a membrane-associated pattern in that context. The supplied sources do not locate this antibody's epitope, so they do not establish which side of the receptor its stain should favor. |
| Tissue selection | HPA reports High staining in placental trophoblasts, kidney tubular cells, small-intestinal glandular cells, and several other cell groups (HPA tissue IHC). Use a named cell population when judging a section; the High label describes reported staining, while the overall tissue profile remains Uncertain (HPA tissue IHC). |
| Negative comparison | Adipocytes, prostate glandular cells, and liver cholangiocytes are listed as Not detected (HPA tissue IHC). They can help flag broadly distributed signal, but an unstained cell is not proof of antibody specificity, particularly given the HPA Uncertain tissue reliability (HPA tissue IHC; general IHC practice). |
| Protein processing and glycosylation | UniProt lists one 332-aa chain, no signal peptide or propeptide, and three glycosylation sites at residues 3, 17, and 26 (UniProt P32245 processing and glycosylation). These annotations do not establish antibody epitope recognition or a target-specific antigen-retrieval effect. |
| Antigen retrieval in paraffin sections | Retrieval is a general IHC workflow variable; judge any change against a matched control and tissue morphology (general IHC practice). Neither source supplied here reports MC4R-specific fixation sensitivity or a retrieval condition, so a stronger signal after retrieval alone does not verify identity. |
| IF/ICC Q&A: should the same appearance be expected? | Membrane localisation remains the biological expectation (UniProt P32245 subcellular location). HPA's ICC-IF summary says Membrane, but gives no main-location assignment or cell-line images; its listed antibody has no ICC status (HPA subcellular; HPA antibodies). Assess IF/ICC on its own guide page. |
| Situation | Likely cause | Next action |
|---|---|---|
| A suspected positive section is blank. | The HPA High designation is an uncertain staining observation, or the IHC run may have failed (HPA tissue IHC: High; reliability Uncertain; general IHC practice). | Verify the named cell population, section integrity, primary incubation, and detection with a same-run control; review retrieval as a general workflow variable, without assuming MC4R-specific fixation sensitivity (general IHC practice). |
| Nuclei stain more strongly than cell edges. | That distribution disagrees with the annotated membrane locations (UniProt P32245 subcellular location); nonspecific nuclear color is a possible technical cause (general IHC practice). | Compare a negative control and inspect chromogen development and counterstain; score membrane and cell-associated signal separately (general IHC practice). |
| Adipocytes or other HPA Not detected cells stain. | Broad staining may reflect cross-reactivity or endogenous detection activity; HPA itself rates its tissue profile Uncertain (HPA tissue IHC; general IHC practice). | Check a negative control, examine where color sits within each cell, and compare the suspect population with HPA High cells on the same run (HPA tissue IHC; general IHC practice). |
| The entire section looks hazy. | Diffuse color can arise from insufficient blocking, secondary detection background, or extended chromogen development (general IHC practice). | Inspect negative controls and reduce the background-producing step identified there; interpret only resolvable cell-associated staining (general IHC practice). |
| Only cytoplasmic staining is visible. | HPA does report cytoplasmic as well as membranous staining, but membrane localisation is annotated by UniProt and the HPA profile is Uncertain (HPA tissue IHC; UniProt P32245 subcellular location). | Record the compartment explicitly, compare cell outlines and controls, and avoid calling cytoplasmic-only signal confirmed MC4R from these sources alone (general IHC practice; HPA tissue IHC: reliability Uncertain). |
| Staining differs between sections or runs. | Technical variation is possible (general IHC practice), and the HPA tissue result has very low antibody-staining versus RNA-expression consistency (HPA tissue IHC). | Compare the same named cell type using matched controls and consistent scoring; report the observed compartment and the HPA Uncertain reliability alongside any result (HPA tissue IHC; general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Very low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Kidney | Cells in tubules | High | Protein (IHC) | HPA → |
| Nasopharynx | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Pancreas | Exocrine glandular cells | High | Protein (IHC) | HPA → |
| Placenta | Trophoblastic cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Fallopian tube | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Hippocampus | Glial cells | Not detected | Protein (IHC) | HPA → |
| Liver | Cholangiocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot MC4R chromogenic IHC in paraffin sections by checking retrieval, cellular localisation, controls and scoring before interpreting staining.
Both anti-MC4R antibodies have human tissue IHC and human cell IF images (catalog image captions); both list human, mouse and rat reactivity (catalog reactivity).
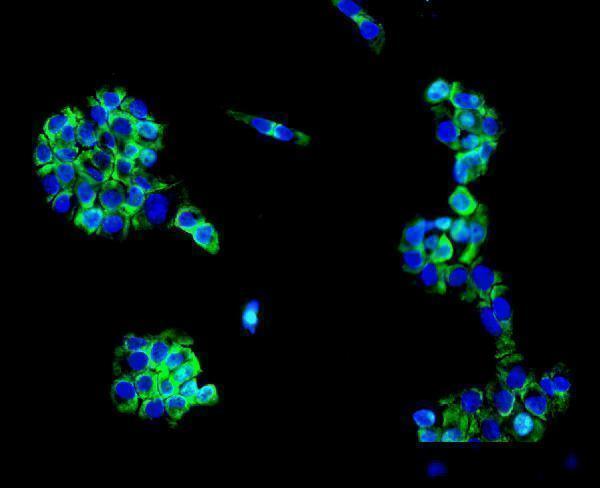
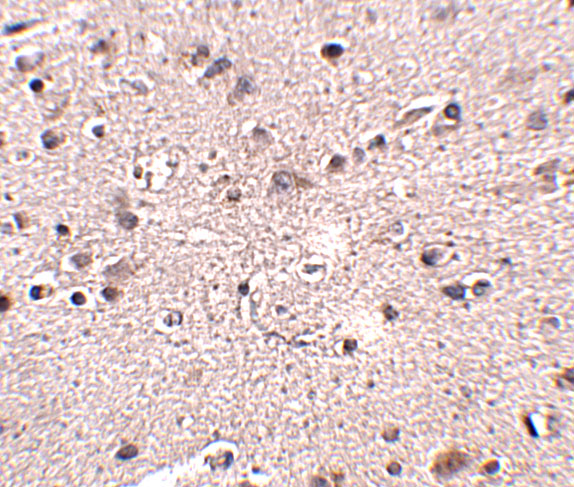
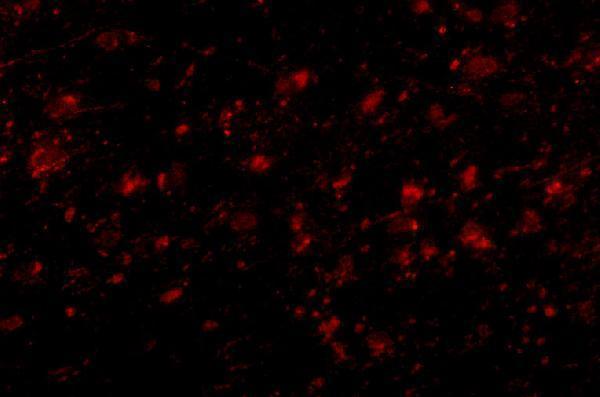
A00619-2 shows IHC in a human rectal cancer paraffin section and IF/ICC in A431 cells (A00619-2 image captions; catalog applications: IF, ICC). A00619 shows IHC in human brain tissue and IF in human brain cells (A00619 image captions; catalog applications: IHC-P, IF).
Which to pick: Choose A00619-2 for paraffin-section IHC or A431 cell IF/ICC, matching its images (A00619-2 image captions); its IHC caption does not report the fixative (A00619-2 IHC caption). Choose A00619 for human brain tissue IHC-P or human brain cell IF, matching its images (A00619 image captions); its IHC caption also does not report the fixative (A00619 IHC caption). For cross-species work, both list human, mouse and rat reactivity, but their IHC and IF images show human samples only (catalog reactivity; image captions); clonality is unreported for both (catalog clone fields).