MFN2 / Mitofusin-2 · IHC design guide

Design Immunohistochemistry for MFN2

Plan chromogenic MFN2 IHC in paraffin sections using mainly cytoplasmic tissue staining as a benchmark (HPA tissue IHC). Kidney tubule cells show high staining, but HPA rates tissue staining reliability as uncertain because it has low consistency with RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for MFN2 (IHC for MFN2): expected localisation Mainly cytoplasmic (HPA tissue IHC); outer mitochondrial membrane (UniProt), antibody A00461, validated IHC image, and IHC protocol steps
Printable MFN2 IHC protocol sheet — expected localisation Mainly cytoplasmic (HPA tissue IHC); outer mitochondrial membrane (UniProt), antibody A00461, controls and protocol steps. Open the full MFN2 IHC guide →

MFN2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Mainly cytoplasmic (HPA tissue IHC); outer mitochondrial membrane (UniProt)
Staining pattern Mainly cytoplasmic staining in most tissues (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Cerebellum+4 more · see all
Negative control ⓘ Liver+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining has low consistency with RNA expression (HPA tissue IHC)
Regulation Low broadly; high in heart and kidney (UniProt)
Isoform / epitope 2 isoforms; epitope coverage needs sequence review (UniProt)
Section 1

Recommended MFN2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is followed by three published MFN2 tissue-staining protocols (PMC6038474; PMC4892862; PMC6676712).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A00461); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-MFN2, 5 μg/mL (datasheet A00461)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMFN2-positive staining in purkinje cells of cerebellum (HPA tissue IHC: High). HPA tissue profile: Mainly cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page antigen retrieval); adjust using the published conditions if needed (PMC4892862; PMC6676712).
Section 2

What Is the Expected MFN2 Staining Pattern?

MFN2 is an outer mitochondrial membrane protein with cytoplasmic-facing regions (UniProt O95140 topology). In paraffin sections, expect mainly cytoplasmic staining, particularly in kidney tubule cells, intestinal glandular cells and neurons reported as high by HPA (HPA: tissue IHC). Interpret the pattern cautiously: HPA rates its tissue IHC reliability Uncertain because antibody staining and RNA expression show low consistency (HPA: reliability).

What am I looking at on my slide?
Cytoplasmic staining in kidney tubule cells, intestinal glandular cells or neurons.This fits HPA's mainly cytoplasmic tissue pattern and its high staining calls for these cell types (HPA: tissue IHC). MFN2's outer mitochondrial membrane location supports an intracellular pattern (UniProt O95140: subcellular location). Chromogenic IHC alone does not establish mitochondrial colocalization.
Predominantly nuclear, luminal or acellular staining.These compartments do not fit MFN2's outer mitochondrial membrane location or HPA's mainly cytoplasmic IHC pattern (UniProt O95140: subcellular location; HPA: tissue IHC). Treat the signal as suspect and compare it with a negative detection control before assigning MFN2 expression (general IHC practice).
Strong staining in cholangiocytes, ovarian stromal cells or parathyroid glandular cells.HPA reports MFN2 as not detected in these specific cell populations (HPA: tissue IHC). Unexpected signal may reflect cross-reactivity or endogenous detection activity; it does not establish expression without independent support (general IHC practice). Do not extend those cell-level observations to every cell in the corresponding tissue.
Uniform haze across cells and extracellular areas.This obscures the cell-specific, mainly cytoplasmic pattern reported by HPA (HPA: tissue IHC). Excess detection background or nonspecific antibody binding are general IHC possibilities; inspect a negative detection control and optimize blocking, washing or antibody concentration as appropriate (general IHC practice).
No signal in kidney tubules or another HPA high-staining cell population.A blank result conflicts with HPA's high staining observations for that population, though HPA rates tissue IHC reliability Uncertain (HPA: tissue IHC; HPA: reliability). Check tissue preservation, retrieval and detection with suitable controls before concluding that MFN2 is absent (general IHC practice).
💡Expected MFN2 appearanceCall a positive result when the relevant cells show clear, mainly cytoplasmic staining—potentially high in kidney tubules, intestinal glandular cells or neurons—while nuclear or acellular signal counts as suspect background (HPA: tissue IHC; UniProt O95140: subcellular location).
How each factor affects the staining
Location and topologyMFN2 sits in the outer mitochondrial membrane, with regions 1–604 and 648–757 facing the cytoplasm (UniProt O95140 topology). HPA describes tissue IHC as mainly cytoplasmic, so score cellular distribution before inferring finer organelle detail (HPA: tissue IHC).
Choice of comparison cellsHPA reports high staining in kidney tubules and Purkinje cells, but no detection in cholangiocytes (HPA: tissue IHC). Compare the named cell populations, rather than treating an entire kidney, cerebellum or liver section as uniformly positive or negative.
Strength of tissue evidenceHPA labels tissue IHC reliability Uncertain because staining has low consistency with RNA expression; its listed IHC antibody HPA030554 is also Uncertain (HPA: reliability; HPA: antibodies). Treat the listed intensities as reference observations, not definitive proof of antibody specificity.
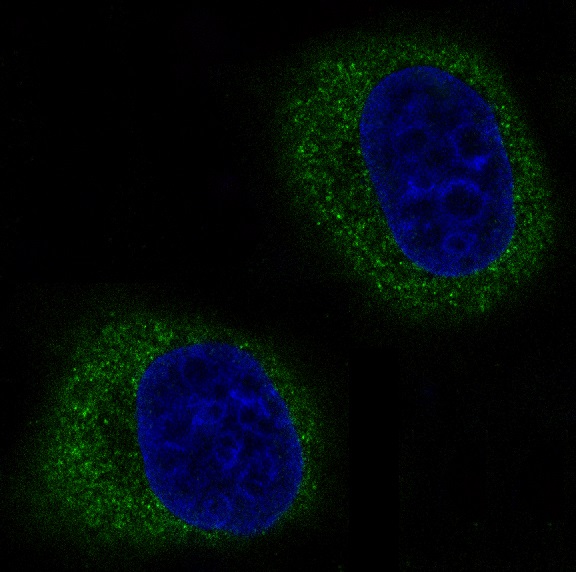
IF/ICC Q&AWhat should IF/ICC show? HPA supports mitochondrial localization in its ICC-IF data, including U2OS images, and lists CAB079902 as ICC Supported (HPA: subcellular; HPA: antibodies). That evidence informs localization but does not validate a paraffin IHC result.
Epitope and isoform scopeUniProt lists 2 MFN2 isoforms and an intact 1–757 chain without a signal peptide or propeptide (UniProt O95140: isoforms; processing). The supplied sources do not map this IHC antibody's epitope, so isoform coverage and any epitope-specific retrieval response remain unknown.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Kidney tubules are blank while a general detection control works.Retrieval conditions, antibody concentration or tissue quality may limit staining (general IHC practice); HPA reports high kidney tubule staining but uncertain overall tissue IHC reliability (HPA: tissue IHC; reliability).Verify tubule identity and tissue integrity, then optimize retrieval and antibody concentration within the assay's validated range (general IHC practice). Record the discrepancy rather than treating HPA's observation as a guaranteed outcome.
Every compartment appears brown.Diffuse chromogen deposition or nonspecific binding can obscure the expected mainly cytoplasmic pattern (general IHC practice; HPA: tissue IHC).Review the negative detection control, blocking, washes and development time; adjust the step responsible for background before scoring cells (general IHC practice).
Cholangiocytes stain strongly.This differs from HPA's not-detected call for cholangiocytes and may reflect cross-reactivity or endogenous detection activity (HPA: tissue IHC; general IHC practice).Check a control omitting primary antibody and assess endogenous enzyme activity where relevant; seek independent specificity evidence before calling cholangiocytes positive (general IHC practice).
Signal looks nuclear rather than cytoplasmic.A mainly nuclear pattern conflicts with HPA tissue IHC and MFN2's outer mitochondrial membrane location (HPA: tissue IHC; UniProt O95140: subcellular location).Check section morphology and negative controls, then reassess staining specificity; do not score nuclear signal as the expected MFN2 pattern (general IHC practice).
A high-staining cell population varies across sections.Technical variation or biological variation may affect staining (general IHC practice); HPA's tissue IHC reliability is Uncertain (HPA: reliability).Compare equivalent cell populations under matched processing and detection conditions, using controls on each run before assigning a biological difference (general IHC practice).
IHC looks diffuse while IF/ICC appears mitochondrial.HPA reports mainly cytoplasmic tissue IHC and supported mitochondrial ICC-IF localization; the assays report patterns at different levels of detail (HPA: tissue IHC; HPA: subcellular).Judge the paraffin IHC result against cell-specific cytoplasmic distribution and IHC controls; use the IF/ICC guide for organelle-level localization assessment (general IHC practice).

Sample controls for MFN2 IHC & IF

🧪Run kidney first: tubular cells should stain (HPA: High in kidney cells in tubules). Use liver cholangiocytes as a negative tissue (HPA: Not detected in liver cholangiocytes); on the kidney slide, cells without a discernible cytoplasmic mitochondrial pattern can serve as internal background references, but the supplied HPA rows do not establish a negative kidney cell population.
Positive control tissue: Cerebellum (Purkinje cells, HPA High)
Negative control tissue: Liver (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show MFN2 in U2OS, with annotated localisation: Mitochondria (supported) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control and an isotype control matched to the primary antibody’s host species and antibody class; assess biological specificity with MFN2 knockout material or an immunizing-peptide block when available (standard IHC practice). For chromogenic kidney IHC, quench endogenous peroxidase and check background in the controls (standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A00461 rat-brain IHC caption leaves the fixative unreported (caption: A00461). Optimize antigen retrieval empirically for paraffin sections because the supplied evidence does not establish an MFN2-specific retrieval dependency (standard IHC practice). IF/ICC may make the mitochondrial pattern easier to assess (HPA subcellular: mitochondria supported); kidney background from endogenous peroxidase can complicate chromogenic interpretation (standard IHC practice).

HPA tissue IHC evidence for MFN2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebellum Purkinje cells High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Kidney Cells in tubules High Protein (IHC) HPA →
Lymph node Non-germinal center cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Parathyroid gland Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced MFN2 IHC Tips

Troubleshoot MFN2 staining in paraffin sections by checking retrieval, compartment, cell type and controls before comparing chromogenic signal across samples.

Which retrieval conditions should I try first for weak MFN2 staining in paraffin sections?
For MFN2 IHC on paraffin sections, start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 min (page retrieval rule: cytoplasmic/membrane antigen). Cool and process matched sections consistently, because retrieval differences can change chromogenic intensity independently of antigen abundance (standard IHC practice). If staining remains weak, compare EDTA buffer at pH 9.0 as a fallback on matched sections (standard IHC practice). Include a positive tissue section and a no-primary control in each comparison so increased signal is distinguishable from increased background (standard IHC practice). Assess cytoplasmic staining in the expected cells, since MFN2 resides on the mitochondrial outer membrane (UniProt O95140 localization; HPA tissue IHC profile).
How should I handle fixation when MFN2 staining varies between paraffin samples?
MFN2-specific sensitivity to fixative type or fixation duration is unknown from the supplied evidence (evidence payload: no target-specific fixation comparison). The catalog antibody’s rat brain IHC caption reports 5 µg/mL but does not state the fixative (A00461 tissue-IHC caption). Record each sample’s fixative, time before fixation and fixation duration, then compare sections processed in the same way (standard IHC practice). Keep section thickness, retrieval and detection conditions matched while testing fixation effects, so those variables do not confound the comparison (standard IHC practice). Use a concurrently processed positive tissue control to detect a staining run that has failed (standard IHC practice).
What MFN2 staining pattern should count as plausible in tissue IHC?
Expect predominantly cytoplasmic chromogenic staining in relevant cells; MFN2 is an outer mitochondrial membrane protein, and the tissue IHC profile describes mainly cytoplasmic expression (UniProt O95140 localization; HPA tissue IHC profile). Bright, exclusively nuclear signal is therefore a reason to investigate specificity and counterstain overlap (UniProt O95140 localization; standard IHC practice). Evaluate the signal within identified cell types: Purkinje cells and kidney tubule cells have high reported staining (HPA tissue IHC: High in Purkinje cells; High in kidney tubule cells). Compare the staining with adjacent morphology and a no-primary control before accepting faint diffuse color as positive (standard IHC practice). Tissue IHC patterns carry uncertainty because antibody staining and RNA expression show low consistency (HPA tissue IHC: Uncertain).
Could isoforms or epitope location explain an unexpected MFN2 IHC pattern?
MFN2 has 2 reported isoforms, but the supplied evidence does not map the catalog antibody’s epitope to either one (UniProt O95140 isoforms; evidence payload). Most of the protein faces the cytoplasm: residues 1–604 and 648–757 are cytoplasmic, while transmembrane segments occupy 605–625 and 627–647 (UniProt O95140 topology). PINK1-associated phosphorylation is reported at residues 111 and 442; its effect on this antibody’s IHC staining is unknown (UniProt O95140 modified residues; evidence payload). Check the antibody’s documented immunogen or epitope before assigning an isoform-specific result (standard IHC practice). If epitope information remains unavailable, report the chromogenic signal as MFN2 immunoreactivity without attributing it to one isoform (standard IHC practice).
How can IF help assess an ambiguous MFN2 chromogenic pattern?
Use IF as a separate localization check when chromogenic MFN2 staining is difficult to assign to cells (standard IHC/IF practice). Multiplex MFN2 with a marker for the expected cell type, such as a neuronal marker when evaluating reported cortical neuronal staining (HPA tissue IHC: High in cerebral cortex neuronal cells; standard IF practice). Choose a fluorophore channel with low tissue autofluorescence and include single-label controls to assess bleed-through (standard IF practice). Select permeabilisation according to the documented antibody epitope: MFN2’s long terminal regions face the cytoplasm, while its short intervening region faces the mitochondrial intermembrane space (UniProt O95140 topology). Interpret apparent mitochondrial overlap alongside controls, because mitochondrial localization is supported but IF and chromogenic IHC have different detection readouts (HPA subcellular: mitochondria supported; standard IHC/IF practice).
What should I check when MFN2 DAB staining appears diffuse or excessive?
First inspect the no-primary control for secondary-reagent binding and endogenous peroxidase signal, then check the primary-antibody dilution and blocking conditions (standard chromogenic IHC practice). A peroxidase block before DAB development is a general chromogenic workflow step, not evidence specific to MFN2 (standard chromogenic IHC practice). The catalog rat brain IHC caption uses 5 µg/mL; it does not establish an optimal concentration for every paraffin preparation (A00461 tissue-IHC caption). Shorten DAB development or reduce primary concentration in matched test sections if color obscures cell boundaries (standard chromogenic IHC practice). Judge whether the remaining signal is cytoplasmic in plausible cells, while accounting for the uncertain tissue staining profile (UniProt O95140 localization; HPA tissue IHC: Uncertain).
How should I quantify MFN2 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the anatomical region and cell population before scoring, then apply the same selection rule to every section (standard IHC quantification practice). An H-score combines the percentage of cells at each staining intensity; report the scoring scale and exclude nonviable regions consistently (standard IHC quantification practice). Alternatively, report the percentage of positive cells or positive-cell density per mm², with the positivity threshold set from controls (standard IHC quantification practice). Normalize cell counts to viable tissue area or the number of eligible cells, and match staining runs or use a shared reference section (standard IHC quantification practice). Stratify by cell type because MFN2 staining differs across reported tissue compartments (HPA tissue IHC: cell-specific staining profile).
When should a strong MFN2 IHC signal be treated as suspect?
Question staining that is confined to nuclei or extracellular material, because MFN2 is assigned to the mitochondrial outer membrane (UniProt O95140 localization). Check whether the signal occurs in the expected cells; high staining is reported in Purkinje cells, whereas liver cholangiocytes are reported as not detected (HPA tissue IHC: High in Purkinje cells; Not detected in liver cholangiocytes). Edge staining and color concentrated in necrotic regions can reflect processing artefact, so compare intact interior tissue (standard IHC practice). Signal in the no-primary control warrants checking endogenous peroxidase and detection reagents before calling a positive result (standard chromogenic IHC practice). Treat tissue-level conclusions cautiously because the reference IHC profile has low agreement with RNA expression (HPA tissue IHC: Uncertain).
Boster reagents

Best MFN2 / Mitofusin-2 IHC Antibodies

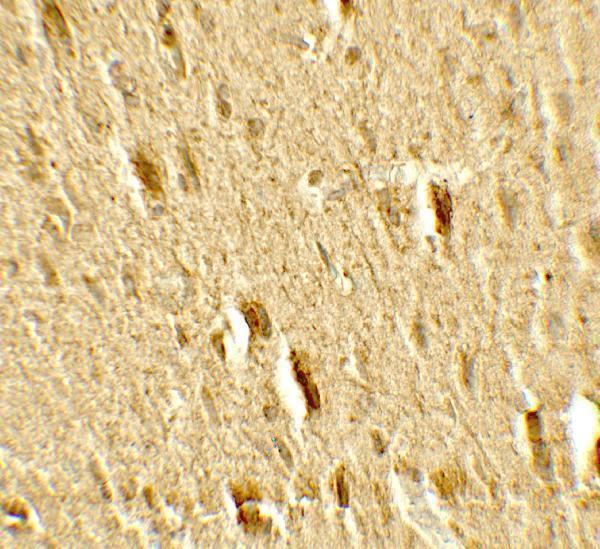
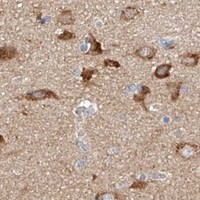
Catalog antibodies A00461 and M00461 have IHC and IF images from rodent tissue, human tissue, or cultured cells (catalog image captions); both list human, mouse, and rat reactivity (catalog applications and reactivity).

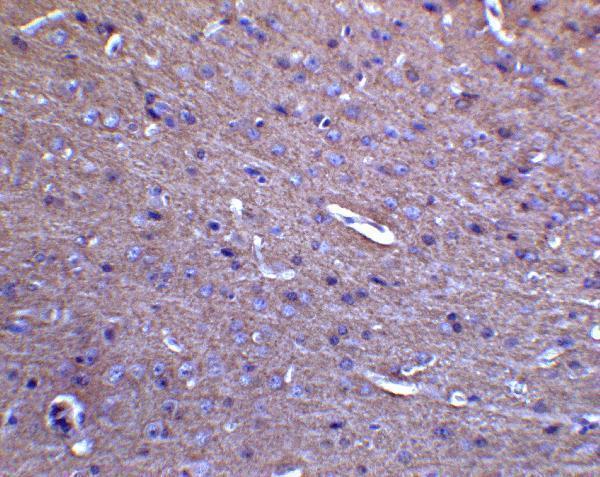
Real IHC data Immunohistochemistry of MFN2 in rat brain tissue with MFN2 antibody at 5 μg/mL.
Anti-Mitofusin-2 MFN2 Antibody
Cat # A00461
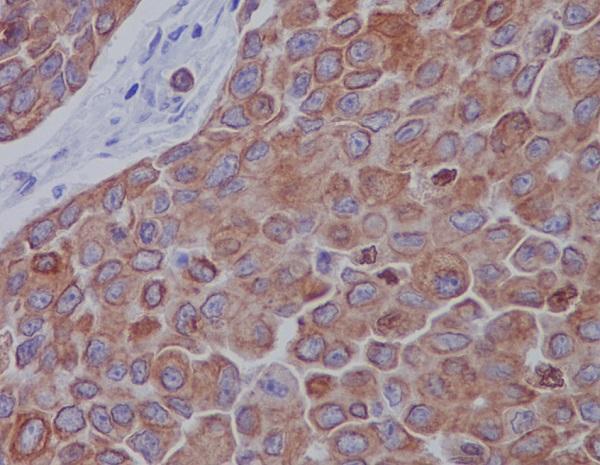
Real IHC data Immunohistochemical analysis of paraffin-embedded human breast carcinoma, using Mitofusin 2 Antibody.
Anti-Mitofusin 2 MFN2 Rabbit Monoclonal Antibody
Cat # M00461

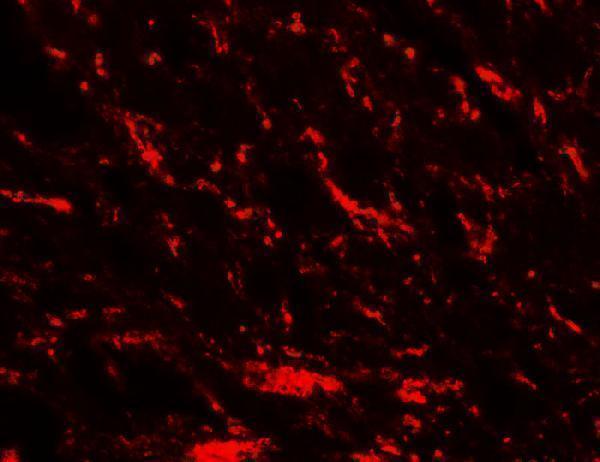
A00461 has IHC images of rat and mouse brain and IF images of rat and mouse brain (catalog image captions). M00461 has an IHC image of paraffin-embedded human breast carcinoma and an IF image of HeLa cells (catalog image captions).

Which to pick: For tissue IHC, choose A00461 for rat or mouse brain (A00461 IHC captions), or M00461 for paraffin-embedded human breast carcinoma; the M00461 caption does not report a fixative (M00461 IHC caption). For IF/ICC in cultured cells, M00461 lists both applications and shows HeLa cell IF (catalog applications; M00461 IF caption). For cross-species tissue work, A00461 has IHC images in two species and lists human, mouse, and rat reactivity; verify performance in human tissue separately (A00461 IHC captions; catalog reactivity).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O95140 (MFN2_HUMAN, Mitofusin-2).
  2. Human Protein Atlas. MFN2 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. MFN2 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. MFN2 antibody validation summary (2 antibodies).
  5. Mitofusin2 Induces Cell Autophagy of Pancreatic Cancer through Inhibiting the PI3K/Akt/mTOR Signaling Pathway. Oxidative medicine and cellular longevity 2018 — PMC6038474.
  6. Prognostic impact of mitofusin 2 expression in colon cancer. Translational cancer research 2022 — PMC9641083.
  7. The evaluative value of Sema3C and MFN2 co-expression detected by immunohistochemistry for prognosis in hepatocellular carcinoma patients after hepatectomy. OncoTargets and therapy 2016 — PMC4892862.
  8. Mitofusin 2 inhibits bladder cancer cell proliferation and invasion via the Wnt/β-catenin pathway. Oncology letters 2019 — PMC6676712.
  9. PubMed PMID:12598526 — UniProt-cited evidence.
  10. PubMed PMID:15322553 — UniProt-cited evidence.
  11. PubMed PMID:9039502 — UniProt-cited evidence.