MPC2 / Mitochondrial pyruvate carrier 2 · IHC design guide

Design Immunohistochemistry for MPC2

Plan chromogenic IHC on paraffin sections with the catalog antibody at 1:100–1:300 (datasheet: A30577). Interpret cytoplasmic staining (HPA tissue IHC) alongside MPC2’s inner mitochondrial membrane location (UniProt), while accounting for uncertain staining reliability (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for MPC2 (IHC for MPC2): expected localisation Cytoplasmic tissue signal (HPA tissue IHC); inner mitochondrial membrane (UniProt), antibody A30577, validated IHC image, and IHC protocol steps
Printable MPC2 IHC protocol sheet — expected localisation Cytoplasmic tissue signal (HPA tissue IHC); inner mitochondrial membrane (UniProt), antibody A30577, controls and protocol steps. Open the full MPC2 IHC guide →

MPC2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue signal (HPA tissue IHC); inner mitochondrial membrane (UniProt)
Staining pattern Cytoplasmic staining in most tissues, including glandular cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A30577)
Caveat Staining and RNA show low consistency; reliability is uncertain (HPA tissue IHC)
Regulation Low tissue specificity in RNA data (HPA tissue RNA)
Isoform / epitope No isoforms or processing; matrix versus intermembrane epitope location matters (UniProt)
Section 1

Recommended MPC2 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with five published MPC2 paraffin-section workflows (PMC5112705; PMC10804966; PMC11380453; PMC7362444).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung carcinoma tissue; fixative not specified (datasheet A30577)
FixationImage fixative and duration unreported (datasheet A30577); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-MPC2, 1:100 - 1:300 (datasheet A30577)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMPC2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page retrieval rule); compare the shorter published conditions if needed (PMC5112705; PMC7362444).
Section 2

What Is the Expected MPC2 Staining Pattern?

MPC2 is an inner mitochondrial membrane protein with three transmembrane segments (UniProt O95563 topology). In paraffin IHC, expect cytoplasmic staining in cells reported as positive, including colon glandular cells and cerebral cortex neurons (HPA tissue IHC). HPA describes cytoplasmic expression in most tissues but rates its tissue staining evidence Uncertain because antibody staining and RNA expression show low consistency (HPA tissue IHC).

What am I looking at on my slide?
Granular cytoplasmic signal in colon glandular cells.This fits the reported Medium staining in these cells (HPA tissue IHC) and the mitochondrial location (UniProt O95563). Chromogenic IHC cannot establish inner membrane localization from the pattern alone (general IHC practice).
Predominantly nuclear or cell surface staining.That compartment conflicts with MPC2's inner mitochondrial membrane location (UniProt O95563). Check the counterstain and tissue morphology, then compare with a control before interpreting the signal as MPC2 (general IHC practice).
Strong staining in adipocytes or bone marrow hematopoietic cells.Both are reported Not detected (HPA tissue IHC). Treat unexpected staining as a specificity question; cross-reactivity or endogenous chromogenic activity are possibilities (general IHC practice), especially given the Uncertain tissue IHC reliability (HPA tissue IHC).
Uniform color across cells, stroma, and blank areas.A distribution unrelated to cell boundaries is more consistent with background than a cellular MPC2 pattern (general IHC practice). HPA describes cytoplasmic tissue staining (HPA tissue IHC); inspect the no-primary control before scoring.
No signal in colon glandular cells or cerebral cortex neurons.Both are reported Medium (HPA tissue IHC), so inspect section quality and the staining run (general IHC practice). A single negative section cannot establish absence of MPC2 because HPA rates tissue IHC reliability Uncertain (HPA tissue IHC).
💡Expected MPC2 appearanceCall a result compatible when staining is predominantly granular cytoplasmic in reported Medium cell populations, such as colon glandular cells (HPA tissue IHC; UniProt O95563 location); isolated nuclear, cell surface, or tissue-wide color warrants investigation (general IHC practice).
How each factor affects the staining
Subcellular locationMPC2 spans the inner mitochondrial membrane three times (UniProt O95563 topology). In tissue IHC, interpret an apparent cytoplasmic pattern alongside morphology; a chromogenic signal does not resolve individual membrane faces (general IHC practice).
Cell and tissue contextHPA reports Medium staining in several glandular and neuronal populations, Low in lung alveolar cells, and Not detected in adipocytes (HPA tissue IHC). Choose comparison regions with those reported levels, while treating them as observations rather than definitive biological controls.
Evidence strengthHPA calls tissue IHC reliability Uncertain because antibody staining and RNA expression have low consistency; HPA056091 is also marked IHC Uncertain (HPA tissue IHC; HPA antibodies). Interpret an isolated positive or negative conservatively.
Protein architectureUniProt lists one 127-residue chain, no annotated isoforms, and no glycosylation sites or modified residues (UniProt O95563). Those annotations do not identify the catalog antibody's epitope or establish antigen retrieval behavior.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known Medium population appears blank.A failed staining run or weak detection is possible (general IHC practice); HPA's Medium call is observational and its reliability is Uncertain (HPA tissue IHC).Check a known staining control, section integrity, primary antibody application, and detection reagents; repeat with the same scoring criteria (general IHC practice).
Signal is diffuse across the section.Background from insufficient blocking, washing, or detection chemistry can obscure cell boundaries (general IHC practice).Review the no-primary control and reagent controls, then adjust blocking or washes according to the assay controls (general IHC practice).
Color appears in an HPA Not detected population.Cross-reactivity or endogenous enzyme activity is possible in chromogenic IHC (general IHC practice); an HPA Not detected call is not proof of biological absence (HPA tissue IHC).Compare the no-primary and detection controls with a reported Medium region on the same run before assigning the signal to MPC2 (general IHC practice; HPA tissue IHC).
Only nuclei or cell borders stain.That pattern conflicts with the inner mitochondrial membrane assignment (UniProt O95563 topology); counterstain or nonspecific labeling may confuse localization (general IHC practice).Review morphology and controls, then repeat the IHC with verified primary and detection settings before scoring MPC2 (general IHC practice).
Staining varies between otherwise comparable sections.Section quality or run conditions can alter IHC appearance (general IHC practice). HPA's tissue evidence is Uncertain, so its reported intensity is a guide rather than a fixed threshold (HPA tissue IHC).Compare sections processed together, verify controls, and score the same cell population with consistent criteria (general IHC practice).
Can IF/ICC settle an ambiguous IHC compartment?HPA lists a Membrane summary but no main location or ICC-IF cell-line images for MPC2 (HPA subcellular).Treat that summary as insufficient to confirm mitochondrial localization by IF/ICC; interpret this paraffin IHC result against controls and the UniProt inner membrane annotation (HPA subcellular; UniProt O95563).

Sample controls for MPC2 IHC & IF

🧪Run adrenal gland first: its glandular cells should stain at the HPA Medium level (HPA: adrenal gland, glandular cells). Use cervix glandular cells as the negative tissue (HPA: cervix, glandular cells, Not detected); on the adrenal slide, any unstained neighboring cells should show only background chromogen, but their MPC2-negative status needs separate validation.
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for MPC2; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include no-primary (secondary-only) and host- and clonality-matched isotype controls, plus MPC2 knockout tissue if available or a peptide-block control (selected A30577 tissue-IHC caption: peptide block). Quench endogenous peroxidase for chromogenic detection and check the adrenal slide for residual background (standard IHC practice).
⚠️Feasibility: No target-specific fixation window, fixation effect, or retrieval requirement is reported in the supplied evidence; compare antigen retrieval conditions empirically (standard IHC practice). The selected A30577 paraffin-section caption leaves the fixative unreported (selected tissue-IHC caption). Frozen sections and IF/ICC cannot be judged easier from these data: HPA supplies no ICC-IF images (HPA subcellular entry), and tissue-specific artefacts are unreported.

HPA tissue IHC evidence for MPC2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Caudate Neuronal cells Medium Protein (IHC) HPA →
Cerebellum Purkinje cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Lymph node Germinal center cells Not detected Protein (IHC) HPA →
Nasopharynx Respiratory epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced MPC2 IHC Tips

Troubleshoot MPC2 chromogenic IHC in paraffin sections using its inner mitochondrial membrane topology, the selected antibody image, and cautious interpretation of tissue staining.

Which retrieval conditions should I try first for MPC2 in paraffin sections?
Start with citrate pH 6.0 heat-induced antigen retrieval at 95–98 °C for 20 min (page retrieval setting). Allow sections to cool in retrieval buffer, then process matched sections together so heating differences do not masquerade as expression differences (standard IHC practice). MPC2 has 3 transmembrane segments in the mitochondrial inner membrane, but the antibody epitope is unspecified, so topology alone cannot establish retrieval sensitivity (UniProt O95563 topology; antibody information supplied). If staining is weak, compare a modestly adjusted heating time on adjacent sections while retaining citrate pH 6.0 and identical detection conditions (standard IHC practice).
How can I troubleshoot weak staining when fixation history differs between blocks?
Target-specific fixation sensitivity for MPC2 is unknown; the selected antibody caption identifies paraffin-embedded human lung carcinoma but does not state its fixative (A30577 tissue-IHC caption). Record each block’s documented fixative and fixation duration, and compare sections of similar thickness within the same staining run (standard IHC practice). Where collection is prospective, use a consistent 10% neutral buffered formalin workflow and record the elapsed fixation time rather than assigning an MPC2-specific optimum (standard IHC practice). Include a section with established staining in every run, and assess morphology alongside signal before attributing differences between blocks to antigen loss (standard IHC practice).
What staining pattern is plausible for MPC2, and which patterns warrant investigation?
Expect signal within the cytoplasmic compartment because MPC2 resides in the mitochondrial inner membrane; chromogenic resolution may present mitochondrial staining as cytoplasmic granularity (UniProt O95563 subcellular location; standard IHC practice). HPA describes cytoplasmic expression in most tissues, but labels its tissue-IHC reliability uncertain because staining and RNA expression have low consistency (HPA tissue IHC). A crisp plasma membrane rim or predominantly nuclear staining conflicts with the annotated compartment and deserves control review (UniProt O95563 subcellular location). Compare suspected signal with a matched negative control and inspect preserved cells away from section edges before assigning localisation (standard IHC practice).
Could MPC2 isoforms or membrane orientation explain inconsistent IHC staining?
No MPC2 isoforms, glycosylation sites, or modified residues are annotated in the supplied record, so those features do not establish an explanation for variable staining (UniProt O95563 record). Its 3 transmembrane segments span residues 40–61, 70–90, and 94–115, with termini annotated on different sides of the inner membrane (UniProt O95563 topology). The catalog antibody’s recognized residues are unspecified, so map its immunogen before predicting whether fixation or retrieval exposes its epitope (antibody information supplied; standard IHC practice). The selected image includes synthesized-peptide blocking, which supports evaluation of that image but does not establish the epitope sequence or tissue-wide specificity (A30577 tissue-IHC caption).
How should I assess MPC2 by IF alongside this chromogenic IHC guide?
Treat IF/ICC as a separate application: the selected evidence is a paraffin-section IHC image, and the supplied HPA subcellular entry lists no ICC/IF images (A30577 tissue-IHC caption; HPA subcellular). For tissue IF multiplexing, a respiratory epithelial cell marker can identify bronchial cells where HPA reports medium MPC2 staining (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores and place the weaker signal in a longer-wavelength channel after checking tissue autofluorescence (standard IF practice). Optimise permeabilisation against the mapped antibody epitope: residues 1–39 face the matrix, whereas 116–127 face the intermembrane space, and the recognized epitope is unspecified (UniProt O95563 topology; antibody information supplied).
What should I check when MPC2 DAB staining appears diffuse or widespread?
Check the no-primary control, tissue morphology, and staining at cut edges before interpreting diffuse brown signal as MPC2 (standard IHC practice). Quench endogenous peroxidase before horseradish peroxidase detection, and keep DAB development time consistent across comparison sections (standard chromogenic IHC practice). Titrate the IHC-validated antibody and review blocking and wash conditions if both test and control sections show background (standard IHC practice). MPC2 is annotated in the mitochondrial inner membrane, while HPA reports cytoplasmic staining with uncertain tissue-IHC reliability, so widespread color alone is insufficient evidence of specific expression (UniProt O95563 subcellular location; HPA tissue IHC).
How should I score MPC2 IHC across samples with different cell densities? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and viable tissue region before scoring, and apply the same threshold and illumination settings to every image (standard IHC image analysis practice). For cellular staining, report an H-score from 0–300, combining the percentage of cells at each intensity with their intensity grade (standard IHC scoring practice). Also report the percentage of positive cells; if counting stained cells by area, express density per mm² of viable tissue (standard IHC scoring practice). Normalise cell-level comparisons to the number of evaluable target cells, record excluded necrosis and edges, and interpret small differences cautiously given HPA’s uncertain tissue-IHC reliability (standard IHC practice; HPA tissue IHC).
How can I distinguish genuine MPC2 staining from artefact in a positive section?
A plausible positive is staining within intact cell cytoplasm, consistent with MPC2’s mitochondrial inner membrane location, rather than isolated nuclear or sharp plasma membrane signal (UniProt O95563 subcellular location; standard IHC interpretation). Confirm the cell type against morphology and an adjacent section; HPA reports medium staining in bronchial respiratory epithelial cells but low staining in lung alveolar cells (HPA tissue IHC; standard IHC practice). Discount staining concentrated at section edges, in necrotic regions, or in a no-primary control after checking endogenous enzyme activity (standard chromogenic IHC practice). Peptide blocking appears in the selected antibody image, yet HPA rates tissue-IHC reliability uncertain, so one positive image cannot establish universal specificity (A30577 tissue-IHC caption; HPA tissue IHC).
Boster reagents

Best MPC2 / Mitochondrial pyruvate carrier 2 IHC Antibodies

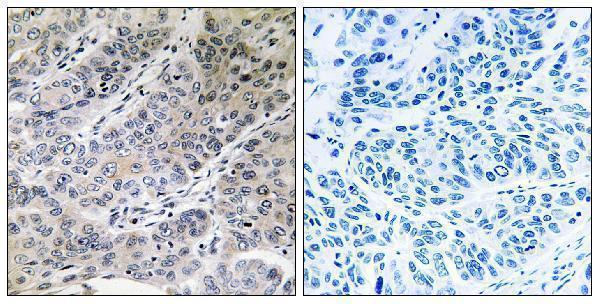
The catalog antibody A30577 lists IHC and IF applications and Human, Mouse, and Rat reactivity; its figure shows IHC on paraffin-embedded human lung carcinoma tissue (catalog applications/reactivity; A30577 IHC caption).

Real IHC data Immunohistochemistry analysis of paraffin-embedded human lung carcinoma tissue, using BRP44 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-BRP44 MPC2 Antibody
Cat # A30577

A30577 will render with an IHC figure of paraffin-embedded human lung carcinoma tissue and a peptide-blocked comparison (A30577 IHC caption). It also lists IF and ICC applications and Human, Mouse, and Rat reactivity, but supplies no IF figure (A30577 catalog applications/reactivity; IF image alts).

Which to pick: For tissue IHC, choose A30577: its own figure shows paraffin-embedded human lung carcinoma tissue, with the fixative unreported (A30577 IHC caption). For IF/ICC or work across Human, Mouse, and Rat, A30577 is the listed option because it is polyclonal and lists those applications and species; the supplied figure documents IHC only (A30577 dilution_raw; catalog applications/reactivity; IHC caption; IF image alts).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O95563 (MPC2_HUMAN, Mitochondrial pyruvate carrier 2).
  2. Human Protein Atlas. MPC2 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. MPC2 subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. MPC2 antibody validation summary (1 antibodies).
  5. MPC1 and MPC2 expressions are associated with favorable clinical outcomes in prostate cancer. BMC cancer 2016 — PMC5112705.
  6. Association of Mitochondrial Pyruvate Carrier with the Clinical and Histological Features in Lupus Nephritis. International journal of nephrology and renovascular disease 2024 — PMC10804966.
  7. Mitochondrial pyruvate carrier 2 mitigates acute kidney injury via sustaining mitochondrial metabolism. International journal of biological sciences 2024 — PMC11380453.
  8. Mitochondrial pyruvate carrier: a potential target for diabetic nephropathy. BMC nephrology 2020 — PMC7362444.
  9. PubMed PMID:11230166 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:16710414 — UniProt-cited evidence.