MT-CO2 / Cytochrome c oxidase subunit 2 · IHC design guide

Design Immunohistochemistry for MT-CO2

Plan chromogenic IHC in paraffin sections with the catalog antibody at 2–5 μg/ml (datasheet A03631-1). Interpret granular cytoplasmic staining (HPA tissue IHC) in light of MT-CO2's inner mitochondrial membrane location (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for MT-CO2 (IHC for MT-CO2): expected localisation IHC: granular cytoplasm (HPA tissue IHC); inner mitochondrial membrane (UniProt), antibody A03631-1, validated IHC image, and IHC protocol steps
Printable MT-CO2 IHC protocol sheet — expected localisation IHC: granular cytoplasm (HPA tissue IHC); inner mitochondrial membrane (UniProt), antibody A03631-1, controls and protocol steps. Open the full MT-CO2 IHC guide →

MT-CO2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation IHC: granular cytoplasm (HPA tissue IHC); inner mitochondrial membrane (UniProt)
Staining pattern Widespread granular cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A03631-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A03631-1)
Caveat Adipocytes show low staining (HPA tissue IHC)
Regulation No specific regulator annotated (UniProt)
Isoform / epitope No isoforms; inner-membrane topology, no extracellular domain (UniProt)
Section 1

Recommended MT-CO2 IHC & IF Protocols

The catalog antibody has an IHC-P protocol (datasheet: A03631-1). The published protocols below stained MT-CO2 in lung adenocarcinoma and ovarian carcinoma tissue microarrays (PMC11695821; PMC4170973).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colorectal cancer tissue; fixative not specified (datasheet A03631-1)
FixationImage fixative and duration unreported (datasheet A03631-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A03631-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03631-1)
Primary antibodyRabbit anti-MT-CO2, 2-5 μg/ml (datasheet A03631-1)
Primary incubationOvernight at 4 °C (datasheet A03631-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A03631-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMT-CO2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression with a granular pattern. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet: A03631-1). If staining is weak, compare the published citrate pH 6.0 and Tris-EDTA pH 9.0 conditions (PMC11695821; PMC4170973).
Section 2

What Is the Expected MT-CO2 Staining Pattern?

MT-CO2 resides in the mitochondrial inner membrane, with two membrane-spanning segments and a large intermembrane-space region (UniProt P00403 topology). In paraffin-section IHC, expect granular cytoplasmic staining across many cell types (HPA tissue IHC: ubiquitous cytoplasmic granular profile). HPA rates the tissue pattern Enhanced, citing high consistency between antibody staining and RNA expression; that rating does not define a universal staining intensity for every cell (HPA tissue IHC: reliability).

What am I looking at on my slide?
Granular cytoplasmic signal in glandular, epithelial, neuronal, or hematopoietic cells.This fits the reported tissue pattern (HPA tissue IHC: ubiquitous cytoplasmic granular profile). HPA reports High staining in adrenal and breast glandular cells, bronchial respiratory epithelial cells, cerebral-cortex neurons, and bone-marrow hematopoietic cells (HPA tissue IHC). Read intensity against the cell type in the section.
Predominantly nuclear, surface-rim, or extracellular chromogen, with little granular cytoplasmic signal.That distribution conflicts with the expected mitochondrial compartment (UniProt P00403: inner-membrane localisation; HPA tissue IHC: granular cytoplasmic profile). Treat it as suspect staining and compare with a known-positive section and staining controls before assigning biological meaning (general IHC practice).
Strong staining only in adipocytes while expected positive cells on the same run lack signal.HPA lists adipocytes as Low and reports High staining in several other cell types (HPA tissue IHC). An inverted pattern raises concern for cross-reactivity or endogenous detection activity; it does not establish either cause by itself (general IHC practice). HPA supplies no negative tissue here.
Diffuse brown haze obscures cell boundaries and the granular pattern.The slide cannot be scored confidently for the reported cytoplasmic granules (HPA tissue IHC: profile). Non-specific antibody binding, inadequate washing, or endogenous chromogenic activity are general IHC possibilities; assess controls and tissue morphology before changing the interpretation (general IHC practice).
No signal in a section containing a cell type reported as High.This is an unexpected run result, not evidence that MT-CO2 is absent from that specimen. HPA reports High staining in, for example, adrenal glandular cells and bronchial respiratory epithelial cells (HPA tissue IHC). Confirm that the expected cells are present, then check the antibody and detection controls (general IHC practice).
💡Expected MT-CO2 appearanceCall a positive result when distinct cytoplasmic granules appear in expected cells, with stronger staining plausible in HPA High cell types (HPA tissue IHC); predominantly nuclear, extracellular, or uniform diffuse staining fails that pattern (UniProt P00403 localisation; HPA tissue IHC: profile).
How each factor affects the staining
Cell type chosen for a positive referenceChoose a reported High population, such as adrenal glandular cells or bronchial respiratory epithelial cells, and verify that those cells appear in the section (HPA tissue IHC). Adipocytes are listed Low, so weak adipocyte signal alone is a poor failure criterion (HPA tissue IHC).
Epitope location and accessMT-CO2 spans the inner mitochondrial membrane twice; residues 88–227 face the intermembrane space (UniProt P00403 topology). The supplied record does not locate the catalog antibody's epitope, so topology cannot establish which retrieval or permeabilisation condition it needs.
Antibody evidenceThree listed antibodies have Enhanced IHC status: HPA051505, HPA054758, and CAB016243 (HPA antibodies). This supports the reported tissue pattern, but it does not establish that a different catalog antibody will produce identical intensity or that every stained compartment is specific.
Chromogenic detectionFor a peroxidase-based IHC system, endogenous enzyme activity can mimic positive chromogen; use appropriate detection controls and blocking according to that system (general IHC practice). The supplied HPA and UniProt records do not identify an MT-CO2-specific endogenous activity problem.
IF/ICC: what localisation should be expected?UniProt places MT-CO2 in the mitochondrial inner membrane (UniProt P00403 localisation). HPA's subcellular entry says Membrane but supplies no main location or ICC/IF image-bearing cell line (HPA subcellular). Thus this record supports a mitochondrial expectation, not an image-validated IF pattern or IF protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive reference tissue has no chromogen.The expected cells may be absent from the section, or an IHC run step may have failed; the record does not identify a target-specific failure mechanism.Verify the cell population and morphology, then check antibody application and detection with run controls (general IHC practice). Use a reported High population as the reference (HPA tissue IHC).
Signal is nuclear or extracellular instead of granular cytoplasmic.The location conflicts with mitochondrial inner-membrane localisation (UniProt P00403) and the reported tissue pattern (HPA tissue IHC).Compare with a known-positive section and an appropriate negative control; withhold a positive call until the granular cytoplasmic pattern is resolved (general IHC practice).
Brown staining appears broadly, including where antibody-dependent signal is uncertain.Endogenous detection activity or non-specific background may contribute in chromogenic IHC (general IHC practice).Review a control omitting primary antibody and the detection system's blocking and washing steps; assess whether discrete cytoplasmic granules remain (general IHC practice; HPA tissue IHC: profile).
Adipocytes look stronger than nearby expected positive cells.That ordering is unexpected because HPA lists adipocytes Low and several other cell types High (HPA tissue IHC); staining alone cannot distinguish cross-reactivity from detection artefact.Check the cell identities, compare the run controls, and avoid treating adipocytes as a confirmed negative reference (general IHC practice; HPA tissue IHC: no negative entries).
Granules are visible but the section is too dark to judge their distribution.Excess chromogen or background can obscure subcellular detail in IHC (general IHC practice).Review detection development and counterstain on a controlled repeat, then score the cellular pattern alongside intensity (general IHC practice; HPA tissue IHC: granular profile).
A different antibody gives a different tissue pattern.HPA's Enhanced rating describes its listed IHC antibodies and reported pattern; it does not validate every antibody or establish an epitope for the catalog antibody (HPA antibodies).Compare cell-level staining against the HPA pattern and a known-positive reference, and review the catalog antibody's IHC validation before interpreting a discordant result (general IHC practice; HPA tissue IHC).

Sample controls for MT-CO2 IHC & IF

🧪Run adrenal gland first and assess its glandular cells for staining (HPA: High in adrenal glandular cells). HPA detects MT-CO2 in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and treat cells on the positive slide that lack granular cytoplasmic staining as a background reference rather than confirmed target-negative cells (HPA: detected in all 45 tissues; UniProt P00403: mitochondrial inner membrane).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: MT-CO2 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for MT-CO2; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include a secondary-only slide and a concentration-matched rabbit IgG isotype control, alongside MT-CO2 knockout material as a biological specificity control (caption: rabbit primary; standard IHC practice). Block endogenous peroxidase and assess pigment-related background in the positive tissue before interpreting DAB staining (caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A03631-1 tissue-IHC caption does not state a fixative (caption: fixative unreported). The reported paraffin-section procedure uses heat retrieval in EDTA, pH 8.0; retrieval is therefore documented for that procedure, but its necessity across preparations is unreported (caption: EDTA heat retrieval). The supplied evidence does not establish whether frozen sections or IF are easier; IF would require access to an inner-membrane target, with permeabilization optimized for the specimen (UniProt P00403: mitochondrial inner membrane; standard IF practice).

HPA tissue IHC evidence for MT-CO2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Endocrine cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: MT-CO2 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced MT-CO2 IHC Tips

Troubleshoot chromogenic MT-CO2 staining in paraffin sections using the catalog antibody’s tissue IHC evidence and the expected mitochondrial pattern (datasheet A03631-1; UniProt P00403 topology).

Which retrieval conditions should I use when MT-CO2 staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A03631-1). The documented paraffin-section example then used 10% goat serum and 2 μg/ml primary antibody overnight at 4°C (datasheet A03631-1). If staining is weak, check heating consistency and compare retrieval durations on adjacent sections before changing the buffer (standard IHC practice). Judge improvement by stronger granular cytoplasmic staining without a comparable rise in diffuse background (HPA tissue IHC profile; standard IHC practice). Record the heating method and duration for each section so changes in staining can be attributed to retrieval (standard IHC practice).
Could fixation explain weak or uneven MT-CO2 staining?
The selected paraffin-section caption does not report a fixative, so target-specific fixation sensitivity is unknown (datasheet A03631-1 caption). Record the fixative and fixation duration for each specimen, then compare sections processed together with the same EDTA pH 8.0 retrieval (standard IHC practice; datasheet A03631-1). Uneven fixation can complicate tissue staining, but the supplied evidence does not establish a particular effect on MT-CO2 (standard IHC practice; datasheet A03631-1 caption). Include a consistently processed comparison section when assessing a suspected fixation effect (standard IHC practice). Interpret any difference alongside section quality and the expected granular cytoplasmic pattern (standard IHC practice; HPA tissue IHC profile).
Where should MT-CO2 appear in chromogenic tissue sections?
Expect a granular cytoplasmic IHC pattern, consistent with a protein of the mitochondrial inner membrane (HPA tissue IHC profile; UniProt P00403 subcellular location). MT-CO2 has 2 transmembrane segments, at residues 15–45 and 60–87, so section-level DAB staining should be assessed as a cellular pattern rather than a resolved membrane outline (UniProt P00403 topology; standard IHC practice). Compare staining within intact cells against adjacent tissue background and the counterstain (standard IHC practice). Predominantly nuclear staining would conflict with the reported location and warrants a specificity check (UniProt P00403 subcellular location; standard IHC practice). HPA reports ubiquitous cytoplasmic expression, with intensity varying across sampled cell types (HPA tissue IHC profile).
How does epitope location affect staining of MT-CO2?
The record describes one 227-residue chain and no annotated isoforms, glycosylation sites or modified residues (UniProt P00403 processing and annotations). Its 2 membrane-spanning segments separate short intermembrane and matrix regions from a longer intermembrane region at residues 88–227 (UniProt P00403 topology). Check the antibody’s stated immunogen or epitope before attributing weak staining to a particular membrane-facing region (standard IHC practice; UniProt P00403 topology). If the epitope is undisclosed, test retrieval changes on matched sections and score both signal and background (standard IHC practice). Do not explain staining differences by an alternative MT-CO2 isoform without independent evidence (UniProt P00403 isoform annotation).
How should I plan MT-CO2 immunofluorescence alongside this IHC guide?
Use the separate IF/ICC guide for fluorescence validation; the selected antibody evidence here documents paraffin-section chromogenic IHC (datasheet A03631-1 caption). For multiplexing, pair MT-CO2 with a marker identifying the cell population being compared, and assess each channel separately before merging images (standard IF practice). Choose fluorophores after inspecting tissue autofluorescence; a spectrally separated far-red channel can help when shorter-wavelength background is strong (standard IF practice). MT-CO2 spans the inner mitochondrial membrane, with residues 88–227 facing the intermembrane space (UniProt P00403 topology). Confirm the antibody’s epitope before optimizing permeabilisation for access to its membrane-facing side (standard IF practice; UniProt P00403 topology).
What should I change when DAB background obscures mitochondrial staining?
First compare a no-primary control with the stained section to identify signal arising from the detection workflow (standard IHC practice). In the documented example, 2 μg/ml primary antibody followed 10% goat serum blocking, and detection used a peroxidase secondary with DAB (datasheet A03631-1). If background persists, check the general peroxidase-blocking step and antibody concentration on matched sections (standard IHC practice). Distinguish diffuse DAB deposition or staining at section edges from the reported granular cytoplasmic pattern (HPA tissue IHC profile; standard IHC practice). Keep chromogen development and imaging conditions comparable across controls and test sections (standard IHC practice).
How can I quantify MT-CO2 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and region before scoring, then report the percentage of positive cells and an H-score for staining intensity (standard IHC practice). Where cell boundaries cannot be scored reliably, measure positive area or cell density per mm² of viable tissue using a fixed threshold (standard IHC practice). Normalise area-based measurements to viable tissue area and compare equivalent cell populations, since HPA describes widespread granular cytoplasmic expression (standard IHC practice; HPA tissue IHC profile). Apply the same retrieval, DAB development, counterstain and imaging settings to comparison sections (standard IHC practice). Exclude folds, edges and necrotic regions using a prespecified rule (standard IHC practice).
How do I separate genuine MT-CO2 staining from artefact?
Give greatest weight to granular cytoplasmic staining in intact cells, matching the reported tissue pattern and mitochondrial inner-membrane location (HPA tissue IHC profile; UniProt P00403 subcellular location). HPA reports high staining in several cell populations, including adrenal glandular cells, while adipocytes are listed as low; interpret intensity within the cell type being examined (HPA tissue IHC data). Treat dominant nuclear staining, edge-only signal and staining in necrotic areas as reasons to investigate artefact (UniProt P00403 subcellular location; standard IHC practice). Compare the no-primary control to assess endogenous peroxidase or detection-related DAB signal (standard IHC practice). A brown deposit alone does not establish MT-CO2 localisation without the expected cellular pattern and appropriate controls (standard IHC practice; HPA tissue IHC profile).
Boster reagents

Best MT-CO2 / Cytochrome c oxidase subunit 2 IHC Antibodies

Catalog images show human, mouse, and rat MT-CO2 IHC (A03631-1, M03631, M03631-2 image captions). Human IF/ICC is application-listed, with no IF figure supplied (catalog applications; IF image alts).

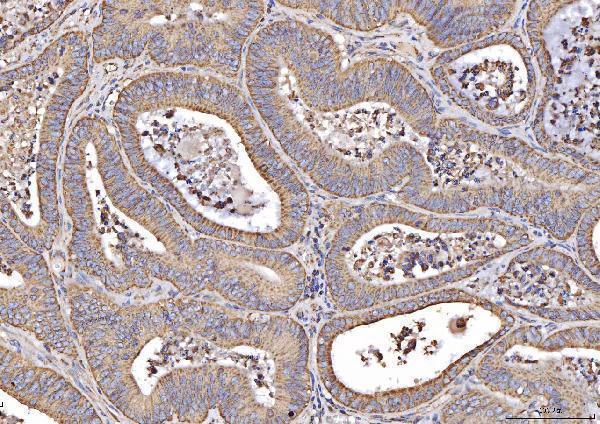
Real IHC data IHC analysis of MT-CO2 using anti-MT-CO2 antibody (A03631-1). MT-CO2 was detected in a paraffin-embedded section of human colorectal cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-MT-CO2 Antibody (A03631-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-MT-CO2 Antibody ®
Cat # A03631-1
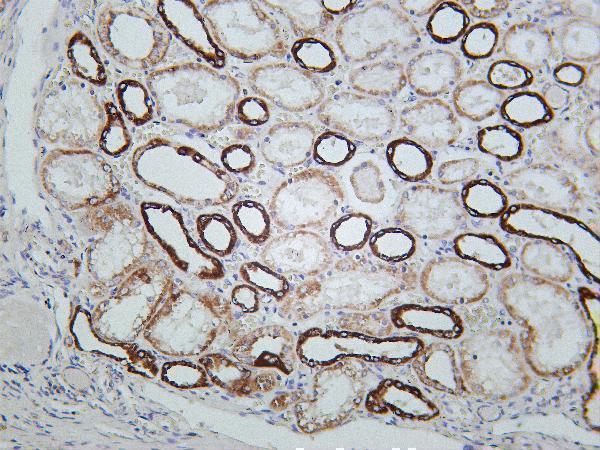
Real IHC data Human kidney was stained with Anti-MTCO2 rabbit antibody
Anti-MTCO2 Rabbit Monoclonal Antibody
Cat # M03631-2
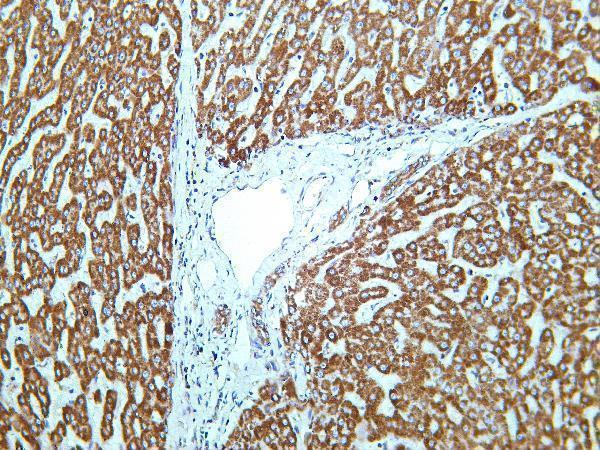
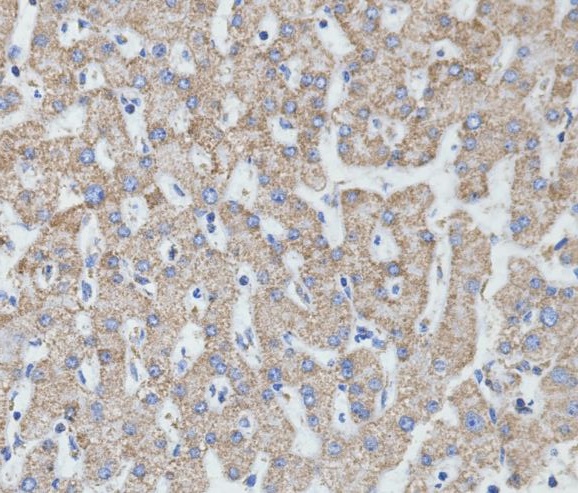
Real IHC data Immunohistochemical analysis of paraffin-embedded human liver, using MTCO2 Antibody.
Anti-MTCO2 Rabbit Monoclonal Antibody
Cat # M03631

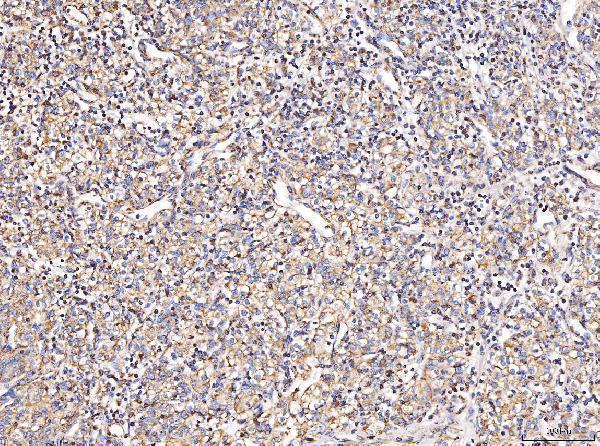
A03631-1 shows paraffin-section IHC in human colorectal cancer and glioma, mouse brain, and rat brain; M03631 shows paraffin-section human liver IHC (respective image captions). M03631-2 shows human kidney and liver IHC and lists human IF, with no IF image supplied (M03631-2 image captions; applications; IF image alts).

Which to pick: For human tissue IHC, M03631 is a rabbit monoclonal shown on paraffin-section liver, while M03631-2 is a recombinant rabbit monoclonal shown on kidney and liver with processing unreported (respective catalog entries; image captions). For human IF/ICC, choose M03631 when both applications are needed; M03631-2 lists IF only (respective application lists). For cross-species paraffin-section IHC, choose A03631-1, which lists human, mouse, and rat reactivity and shows each in IHC images; fixative is unreported in all three SKUs’ image captions (A03631-1 catalog; respective image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P00403 (COX2_HUMAN, Cytochrome c oxidase subunit 2).
  2. Human Protein Atlas. MT-CO2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. MT-CO2 subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. MT-CO2 antibody validation summary (3 antibodies).
  5. Mitochondrial-cytochrome c oxidase II promotes glutaminolysis to sustain tumor cell survival upon glucose deprivation. Nature communications 2025 — PMC11695821.
  6. Expression of mitochondrial regulators PGC1α and TFAM as putative markers of subtype and chemoresistance in epithelial ovarian carcinoma. PloS one 2014 — PMC4170973.
  7. Non-canonical dihydrolipoyl transacetylase promotes chemotherapy resistance via mitochondrial tetrahydrofolate signaling. Nature communications 2025 — PMC12508156.
  8. PubMed PMID:7219534 — UniProt-cited evidence.
  9. PubMed PMID:2550900 — UniProt-cited evidence.
  10. PubMed PMID:226894 — UniProt-cited evidence.