MYH6 / Myosin-6 · IHC design guide

Design Immunohistochemistry for MYH6

Plan MYH6 paraffin-section IHC around high cytoplasmic staining in cardiomyocytes and medium staining in skeletal myocytes (HPA tissue IHC). This guide covers fixation consistency, chromogenic controls and interpretation of the expected myofibrillar signal (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for MYH6 (IHC for MYH6): expected localisation Cytoplasmic staining observed; thick filaments expected (HPA tissue IHC; UniProt), antibody A02808-2, validated IHC image, and IHC protocol steps
Printable MYH6 IHC protocol sheet — expected localisation Cytoplasmic staining observed; thick filaments expected (HPA tissue IHC; UniProt), antibody A02808-2, controls and protocol steps. Open the full MYH6 IHC guide →

MYH6 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining observed; thick filaments expected (HPA tissue IHC; UniProt)
Staining pattern High cardiomyocyte and medium skeletal myocyte cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02808-2)
Positive control ⓘ Heart muscle+1 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Cardiac endogenous peroxidase can add DAB background (standard IHC practice)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope No annotated isoforms; one full-length chain (UniProt)
Section 1

Recommended MYH6 IHC & IF Protocols

The catalog antibody’s paraffin IHC protocol (datasheet: A02808-2) is accompanied by published prostate, heart, and mouse skeletal muscle protocols (PMC11344859; PMC8962334; PMC6083496).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human skeletal muscle tissue; fixative not specified (datasheet A02808-2)
FixationImage fixative and duration unreported (datasheet A02808-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02808-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02808-2)
Primary antibodyRabbit anti-MYH6, 2 μg/ml (datasheet A02808-2)
Primary incubationOvernight at 4 °C (datasheet A02808-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A02808-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMYH6-positive staining in cardiomyocytes of heart muscle (HPA tissue IHC: High). HPA tissue profile: Selective cytoplasmic expression in heart and skeletal muscle. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet: A02808-2). For optimization, compare published citrate retrieval at pH 6 (PMC11344859) and 9.0 (PMC6083496).
Section 2

What Is the Expected MYH6 Staining Pattern?

MYH6 should stain the cytoplasm of cardiomyocytes strongly and skeletal myocytes at a medium level in tissue IHC (HPA tissue IHC: heart High; skeletal muscle Medium). Its expected location is the myofibril thick filament, with no transmembrane segment (UniProt P13533). HPA rates the tissue pattern Enhanced because antibody staining is highly consistent with RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Strong cytoplasmic staining in cardiomyocytes, with myofibrillar detail where preserved.This fits the heart pattern (HPA tissue IHC: cardiomyocytes High) and the thick filament location (UniProt P13533). Compare staining with tissue structure and controls before scoring; HPA levels describe observed staining, not a required intensity for every section.
Predominantly nuclear, surface, or extracellular staining in otherwise intact cardiomyocytes.These compartments conflict with the annotated cytoplasmic myofibril location and absence of a transmembrane segment (UniProt P13533). Consider nonspecific staining or a detection artefact; compartment alone cannot identify its cause (general IHC practice).
Prominent staining in adipocytes or respiratory epithelial cells.HPA reports MYH6 as Not detected in these cells (HPA tissue IHC: adipose tissue; bronchus). Check cross-reactivity or endogenous detection activity with controls before assigning the signal to MYH6 (general IHC practice).
Widespread diffuse color across cells and surrounding tissue, obscuring myocyte boundaries.This does not resemble selective cytoplasmic muscle staining (HPA tissue IHC). It may reflect background from detection reagents, inadequate blocking, or overly concentrated antibody; a no-primary control helps separate these possibilities (general IHC practice).
No convincing cardiomyocyte signal in a heart muscle section.Heart cardiomyocytes are High in the HPA tissue IHC record. First confirm tissue identity and preservation, then check antibody application, retrieval, and detection controls (general IHC practice). A negative run alone cannot overturn the reference pattern.
💡Expected MYH6 appearanceCall a section positive when cardiomyocytes show strong cytoplasmic, preferably myofibrillar staining (HPA tissue IHC: High; UniProt P13533); dominant nuclear or nonmuscle staining is suspect (UniProt P13533; HPA tissue IHC).
How each factor affects the staining
Tissue and cell selectionHeart cardiomyocytes provide the strongest listed positive reference; skeletal myocytes are Medium (HPA tissue IHC). Adipocytes and respiratory epithelial cells are listed as Not detected (HPA tissue IHC). Use matched controls to judge a run (general IHC practice).
Compartment and protein organizationMYH6 is cytoplasmic in myofibril thick filaments and has no transmembrane segment (UniProt P13533). Interpret a convincing signal within myocytes in that context; nuclear, cell surface, or extracellular color needs investigation (general IHC practice).
Strength of HPA validationThe tissue profile is Enhanced for antibody and RNA consistency (HPA tissue IHC). Three listed antibodies are IHC Enhanced, while two are IHC Supported (HPA antibodies). These labels support the reported pattern but do not validate every antibody or individual slide.
Antigen retrievalTarget-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.
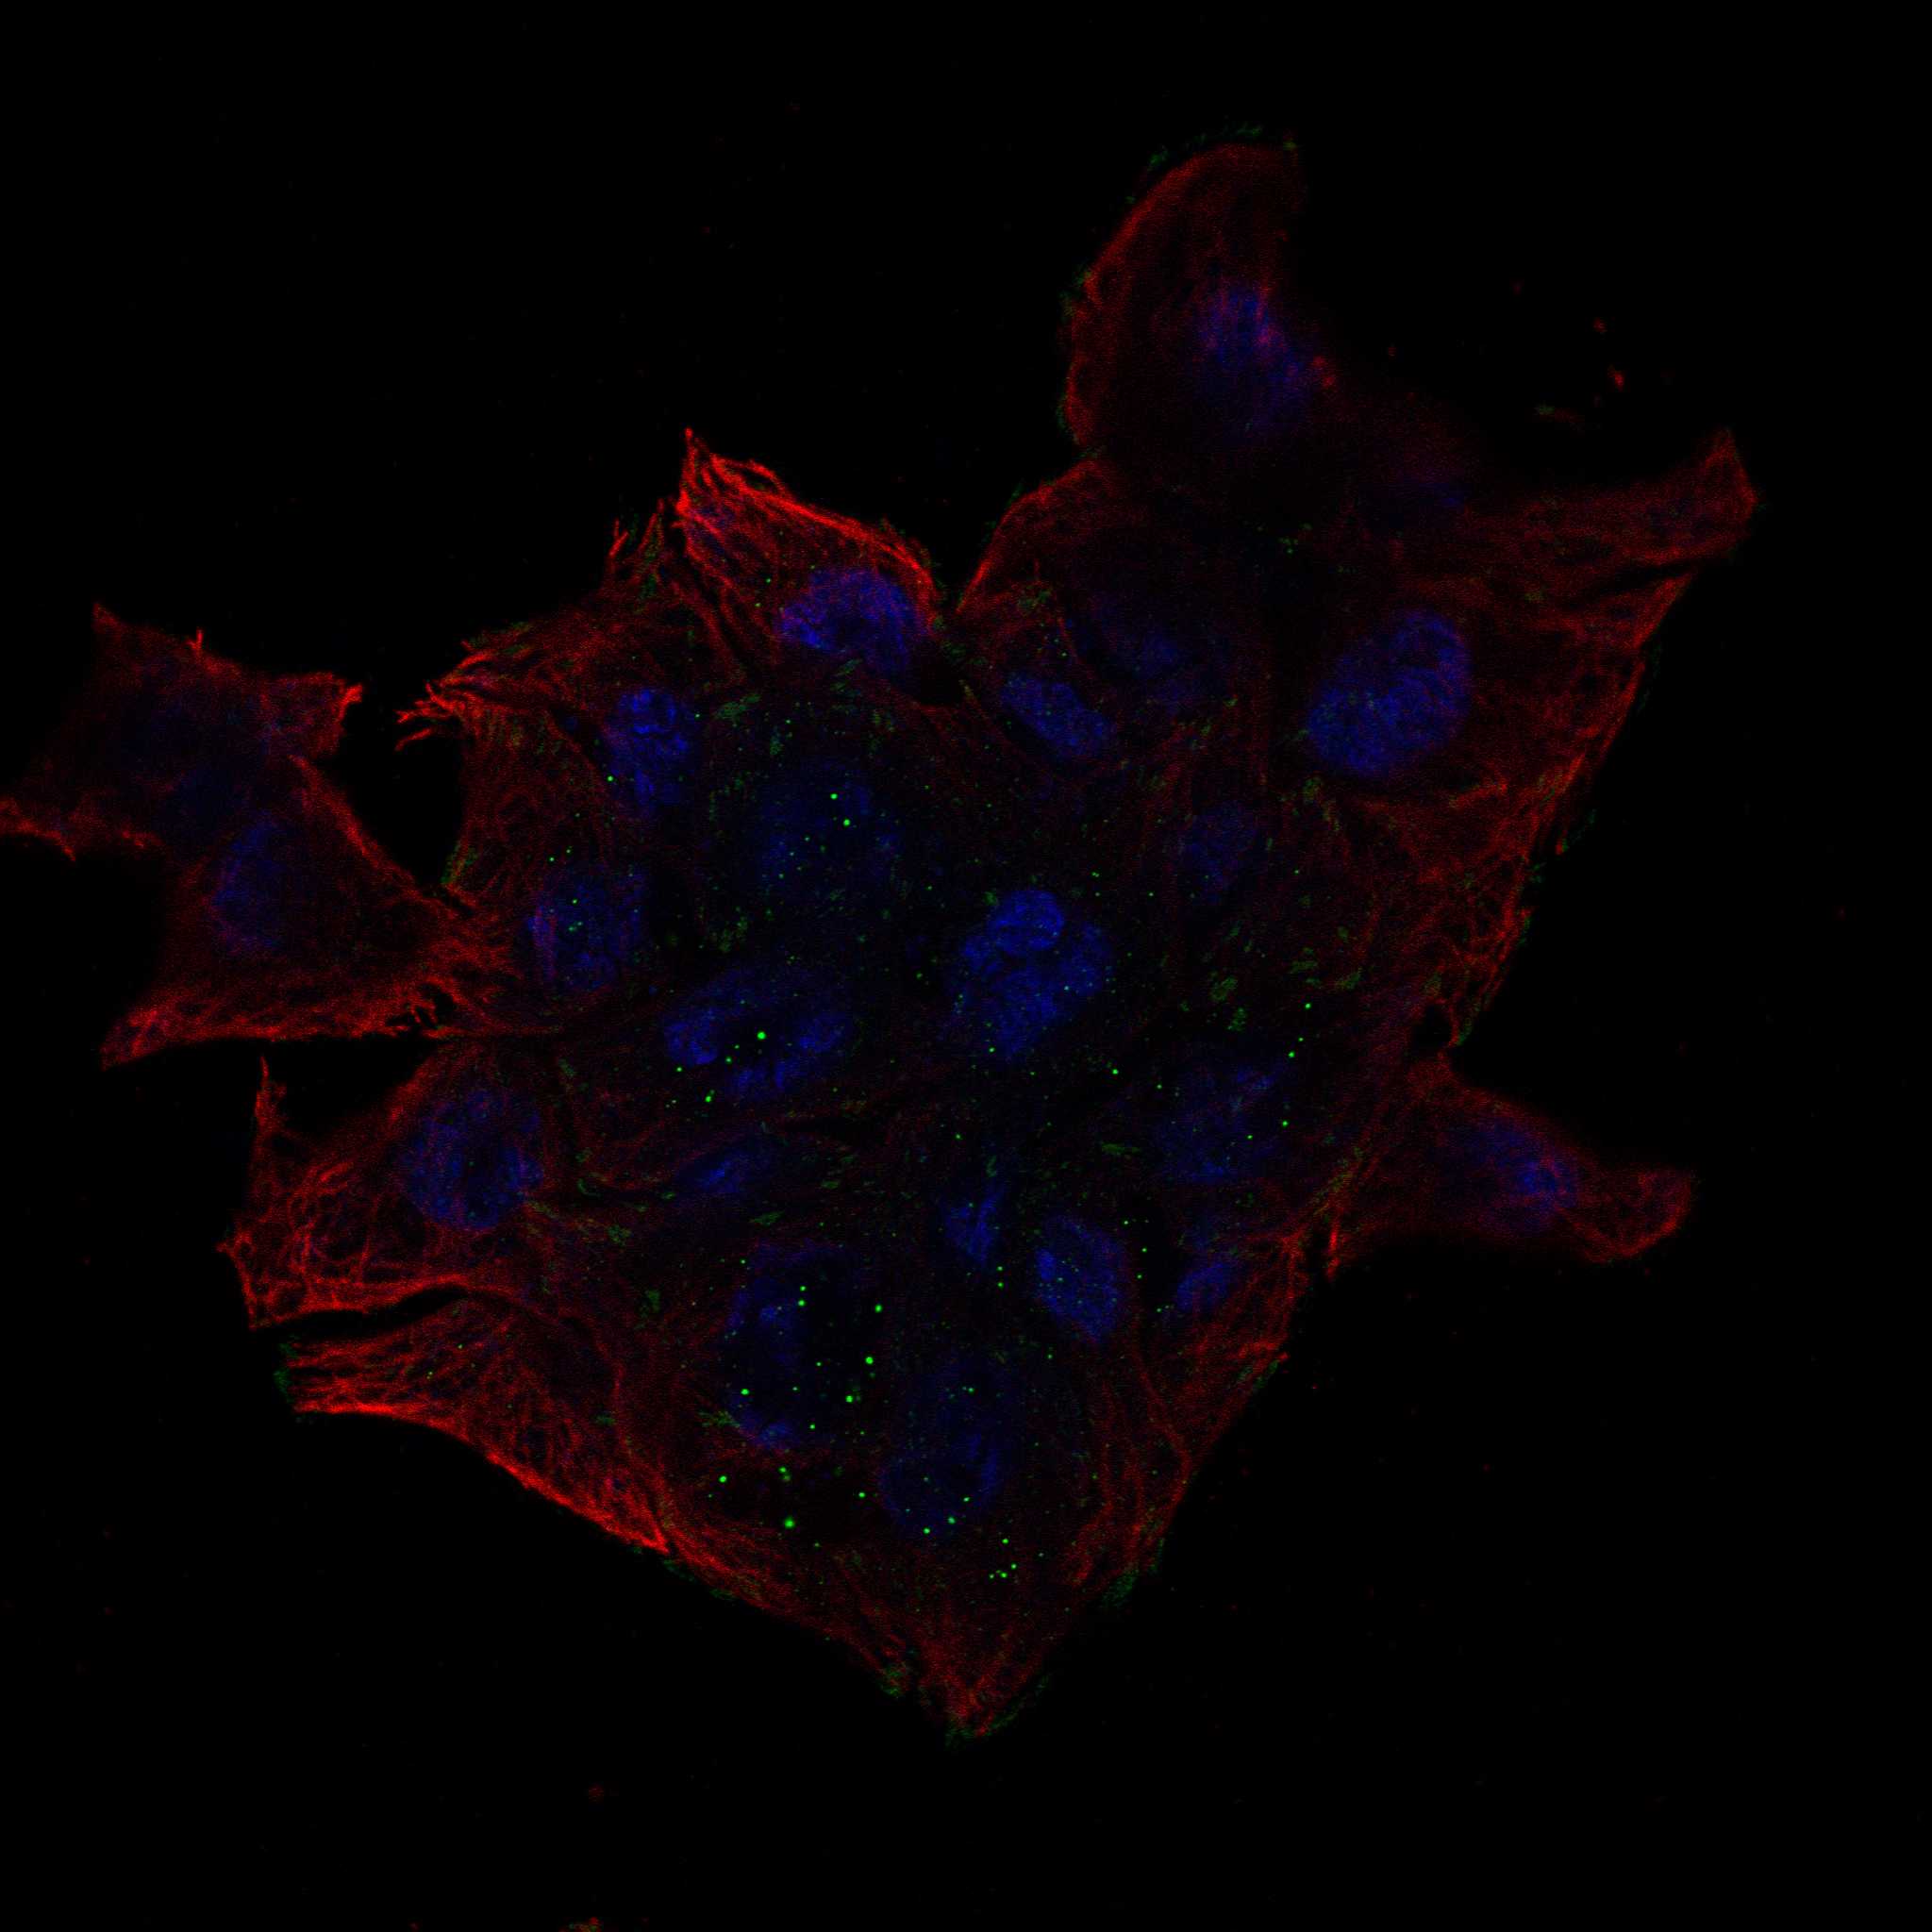
IF/ICC Q&A: Should focal adhesion staining be expected?Treat it as uncertain: HPA lists focal adhesion sites with a warning that the observation uses antibodies targeting proteins from multiple genes (HPA subcellular ICC-IF). The listed ICC-IF image cell lines do not establish MYH6-positive controls for this IHC guide.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Heart control is blank or much weaker than expected.The result conflicts with High cardiomyocyte staining (HPA tissue IHC); tissue, antibody, retrieval, or detection problems remain possible (general IHC practice).Confirm the heart section contains preserved cardiomyocytes, then review the antibody's IHC-P instructions and run detection controls (general IHC practice). Do not infer MYH6-specific fixation sensitivity from this failure.
Signal is confined to nuclei or cell outlines.That distribution conflicts with cytoplasmic myofibril localization and no transmembrane segment (UniProt P13533).Inspect tissue morphology and a no-primary control; reassess antibody specificity and detection background before scoring the signal as MYH6 (general IHC practice).
Adipocytes or bronchial respiratory epithelial cells stain strongly.HPA lists those cell types as Not detected (HPA tissue IHC: adipose tissue; bronchus); cross-reactivity or endogenous activity is possible (general IHC practice).Compare with a heart positive control and no-primary control. If peroxidase detection is used, verify endogenous peroxidase blocking (general IHC practice).
Color covers the section diffusely and hides muscle architecture.Diffuse color differs from selective muscle cytoplasmic staining (HPA tissue IHC); reagent background or excess antibody is possible (general IHC practice).Check the no-primary control, blocking, washes, and the antibody's recommended working concentration (general IHC practice). Adjust only against a positive heart control.
Skeletal muscle is weaker than heart muscle.That ordering is compatible with the reported Medium skeletal myocyte and High cardiomyocyte levels (HPA tissue IHC).Score the two tissues in their own context and check controls before treating the difference as assay failure (general IHC practice). Avoid assuming HPA levels predict identical staining in every section.
An ICC-IF image suggests focal adhesion staining.The HPA focal adhesion assignment is uncertain and carries a multiple-gene antibody warning (HPA subcellular ICC-IF).Do not transfer that assignment to paraffin IHC. Judge IHC against cardiomyocyte cytoplasmic staining and the myofibril annotation (HPA tissue IHC; UniProt P13533).

Sample controls for MYH6 IHC & IF

🧪Run heart muscle first: cardiomyocytes should stain (HPA: High in cardiomyocytes). Use adipose tissue as the negative tissue (HPA: Not detected in adipocytes); on the heart slide, assess non-cardiomyocyte elements as internal negatives for the expected myofibrillar staining (UniProt P13533: myofibril, thick filaments).
Positive control tissue: Heart muscle (Cardiomyocytes, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show MYH6 in OE19, SuSa, U2OS, with annotated localisation: Focal adhesion sites (uncertain) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) slide and a matched nonimmune rabbit IgG isotype control, since the catalog antibody is rabbit-derived (selected-SKU IHC caption). Use MYH6-knockout tissue as a biological specificity control if available; quench endogenous peroxidase and check for endogenous biotin when using the caption’s biotin–SABC/DAB detection (selected-SKU IHC caption; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU paraffin-section caption does not state the fixative (selected-SKU IHC caption). The reported IHC workflow uses heat retrieval in EDTA at pH 8.0 and 2 μg/ml primary antibody overnight at 4°C; the supplied evidence does not establish whether retrieval is essential or frozen sections or IF are easier (selected-SKU IHC caption). Check for endogenous biotin signal in heart muscle when using biotin-based detection (selected-SKU IHC caption; standard IHC practice).

HPA tissue IHC evidence for MYH6

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes High Protein (IHC) HPA →
Skeletal muscle Myocytes Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced MYH6 IHC Tips

Troubleshoot chromogenic MYH6 staining in paraffin sections by checking retrieval, myofibrillar localisation and cell type before comparing signal intensity (UniProt P13533; HPA tissue IHC).

Which retrieval conditions should I try first for weak MYH6 staining?
Start with heat mediated retrieval in EDTA buffer at pH 8.0 for paraffin sections (datasheet A02808-2). The selected image used this retrieval before overnight incubation at 4°C with 2 μg/ml primary antibody, so keep those conditions together while establishing a baseline (datasheet A02808-2). If staining remains weak, adjust heating duration in small increments using adjacent sections and compare signal with tissue preservation (standard IHC practice). Use heart muscle as a positive reference because cardiomyocytes show high expression, and check whether any gain preserves the expected myofibrillar pattern (HPA tissue IHC; UniProt P13533).
How should I assess whether fixation caused weak or uneven MYH6 staining?
The selected paraffin section caption does not state a fixative, and target specific MYH6 sensitivity to fixation is unknown (datasheet A02808-2). Record each specimen’s fixative and fixation duration, then compare adjacent sections processed with the same EDTA pH 8.0 retrieval and 2 μg/ml primary antibody conditions (datasheet A02808-2; standard IHC practice). Include a heart muscle control in each run because cardiomyocytes show high MYH6 expression (HPA tissue IHC). If control staining is consistent while specimens vary, assess preservation and processing history before assigning the difference to MYH6 abundance (standard IHC practice).
Where should convincing MYH6 signal appear in a chromogenic section?
Look for cytoplasmic staining associated with myofibrils: MYH6 resides in their thick filaments and has no transmembrane segment (UniProt P13533). In tissue, cardiomyocytes show high expression and skeletal muscle myocytes show medium expression, providing cell type references for section review (HPA tissue IHC). Compare DAB distribution with fibre morphology and a counterstain, and assess multiple intact fields before scoring a specimen (standard IHC practice). Treat predominantly nuclear or membrane outlining signal as a reason to recheck specificity and detection controls, since those patterns do not match the annotated myofibrillar location (UniProt P13533; standard IHC practice).
Can epitope accessibility or related myosins explain discordant MYH6 staining?
The supplied MYH6 record lists 0 isoforms and places its motor domain at residues 85–780, but it does not identify this antibody’s epitope (UniProt P13533; datasheet A02808-2). Consequently, staining alone cannot establish which sequence region the antibody recognizes or exclude recognition of a related myosin (standard IHC interpretation). Compare the antibody’s documented immunogen or epitope information, if available, with related sequences before making a specificity claim (standard antibody validation practice). Keep EDTA at pH 8.0 constant during that comparison, and confirm that signal follows expected cells and myofibrils (datasheet A02808-2; HPA tissue IHC; UniProt P13533).
How can IF help evaluate ambiguous MYH6 IHC staining?
Use IF as a separate validation experiment and multiplex MYH6 with a marker that identifies cardiomyocytes or skeletal muscle myocytes, the expected positive cell types (HPA tissue IHC; standard IF practice). Choose a far red fluorophore when tissue autofluorescence compromises shorter wavelength channels, and examine unstained tissue in each channel before interpreting overlap (standard IF practice). MYH6 has no transmembrane segment and localises to cytoplasmic myofibrillar thick filaments, so include a mild permeabilisation step to reach that intracellular compartment (UniProt P13533; standard IF practice). Optimise IF fixation independently; the selected paraffin IHC caption reports no fixative and supplies no IF fixation evidence (datasheet A02808-2).
What should I check when DAB staining obscures MYH6 positive fibres?
First compare a no primary control with the stained section to identify signal generated by secondary reagents or chromogen development (standard IHC practice). The selected assay uses a biotinylated secondary, streptavidin–biotin complex and DAB, so include a detection only control when background is widespread (datasheet A02808-2; standard IHC practice). Apply a peroxidase block and assess endogenous biotin interference as general chromogenic workflow checks, then titrate detection and washing while holding retrieval at EDTA pH 8.0 (standard IHC practice; datasheet A02808-2). Judge improvements against intact cardiomyocyte or myocyte cytoplasmic staining, rather than a lower background level alone (HPA tissue IHC; standard IHC practice).
How should I score and normalise MYH6 staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scoring population before analysis: cardiomyocytes or skeletal muscle myocytes, which show high and medium MYH6 expression respectively (HPA tissue IHC). For chromogenic sections, record the percentage of positive target cells and an intensity based H-score, or measure positive area per mm² of viable target tissue when fibre boundaries are difficult to separate (standard IHC quantification practice). Normalise to the number or area of eligible cells or viable tissue, and use identical DAB development and imaging settings across compared sections (standard IHC practice). Exclude folds, edges and damaged areas consistently, and report those exclusions alongside the scoring threshold (standard IHC quantification practice).
How do I distinguish true MYH6 staining from a misleading positive?
A credible positive follows cardiomyocyte or skeletal muscle myocyte cytoplasm and myofibrils, consistent with the tissue profile and thick filament annotation (HPA tissue IHC; UniProt P13533). Reconsider signal confined to nuclei, section edges or necrotic regions, and inspect a no primary control for nonspecific detection or endogenous enzyme activity (UniProt P13533; standard IHC practice). The selected chromogenic method uses DAB with a streptavidin–biotin detection system, so check whether apparent positives persist when primary antibody is omitted (datasheet A02808-2; standard IHC practice). Resolve discordant staining with intact morphology, an appropriate positive control and independently validated specificity evidence before calling a biological change (standard IHC practice).
Boster reagents

Best MYH6 / Myosin-6 IHC Antibodies

IHC-validated anti-MYH6 antibodies have paraffin-section images from human skeletal muscle, mouse smooth muscle, and mouse and rat cardiac tissue (catalog IHC image captions).

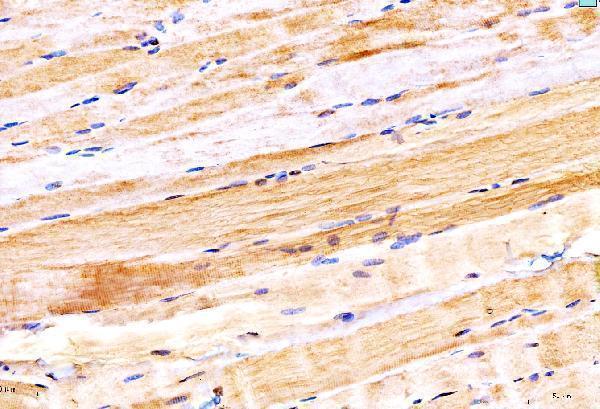
Real IHC data IHC analysis of MYH6 using anti-MYH6 antibody (A02808-2). MYH6 was detected in a paraffin-embedded section of human skeletal muscle tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-MYH6 Antibody (A02808-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-MYH6 Antibody ®
Cat # A02808-2
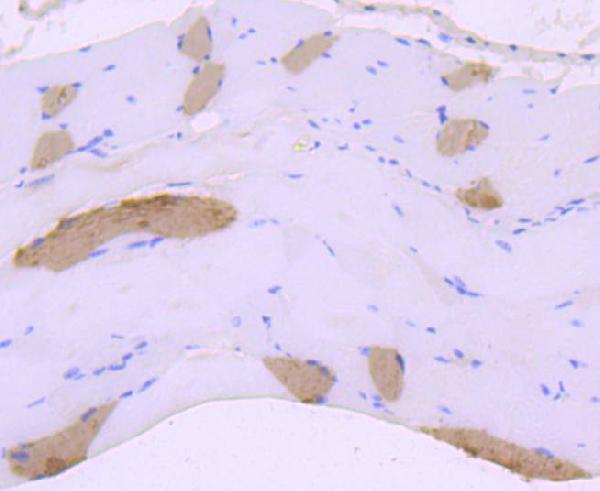
Real IHC data Immunohistochemical analysis of paraffin-embedded mouse smooth muscle tissue using anti-Myosin heavy chain antibody. Counter stained with hematoxylin.
Anti-Myosin-6 MYH6 Antibody
Cat # A02808-1

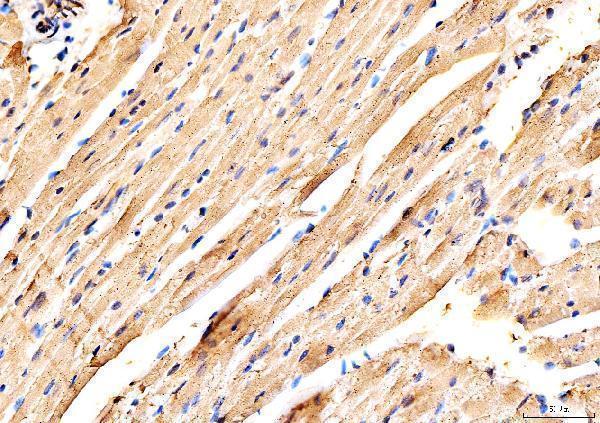
A02808-2 has IHC images from paraffin sections of human skeletal muscle and mouse and rat cardiac tissue (A02808-2 image captions). A02808-1 has an IHC image from paraffin-embedded mouse smooth muscle (A02808-1 image caption).

Which to pick: Choose A02808-2 for cross-species tissue IHC: its own paraffin-section captions show human, mouse, and rat samples (A02808-2 image captions). A02808-1 is an option for mouse smooth muscle IHC, with a listed dilution of 1:50–1:200 (A02808-1 image caption; catalog IHC dilution); neither caption reports the fixative (catalog IHC image captions). For IF/ICC, neither SKU has a listed IF application or IF image, so there is no IF-validated choice here (catalog applications; catalog IF image alts).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P13533 (MYH6_HUMAN, Myosin-6).
  2. Human Protein Atlas. MYH6 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. MYH6 subcellular location (ICC-IF): Localized to the focal adhesion sites. Caution: Based on antibodies targeting proteins from multiple genes..
  4. Human Protein Atlas. MYH6 antibody validation summary (5 antibodies).
  5. MYH6 suppresses tumor progression by downregulating KIT expression in human prostate cancer. Scientific reports 2024 — PMC11344859.
  6. Nr2f1a and Isl1 repress acquisition of epicardial identity in venous atrial cardiomyocytes. Development (Cambridge, England) 2026 — PMC13286355.
  7. Cellular Phenotypic Transformation in Heart Failure Caused by Coronary Heart Disease and Dilated Cardiomyopathy: Delineating at Single-Cell Level. Biomedicines 2022 — PMC8962334.
  8. Skeletal muscle in aged mice reveals extensive transformation of muscle gene expression. BMC genetics 2018 — PMC6083496.
  9. PubMed PMID:1776652 — UniProt-cited evidence.
  10. PubMed PMID:8307559 — UniProt-cited evidence.
  11. PubMed PMID:12508121 — UniProt-cited evidence.