NDEL1 / Nuclear distribution protein nudE-like 1 · IHC design guide

Design Immunohistochemistry for NDEL1

Plan NDEL1 paraffin IHC around cytoplasmic staining and strong signal in colon glandular cells (HPA tissue IHC). Start the IHC-validated antibody at 2–5 μg/mL (datasheet A02478-2), and use controls when interpreting staining because antibody staining and RNA show low consistency (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for NDEL1 (IHC for NDEL1): expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC), antibody A02478-2, validated IHC image, and IHC protocol steps
Printable NDEL1 IHC protocol sheet — expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC), antibody A02478-2, controls and protocol steps. Open the full NDEL1 IHC guide →

NDEL1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC)
Staining pattern Cytoplasmic; high in intestinal glandular cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02478-2)
Positive control ⓘ Colon+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Antibody staining and RNA show low consistency (HPA tissue IHC)
Regulation Intensity varies by cell type (HPA tissue IHC)
Isoform / epitope 3 isoforms; check epitope coverage (UniProt)
Section 1

Recommended NDEL1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by published NDEL1 chromogenic IHC methods for mouse brain sections and sections of unspecified origin (PMC5363720; PMC7796549; PMC4048543).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human endometrial cancer tissue; fixative not specified (datasheet A02478-2)
FixationImage fixative and duration unreported (datasheet A02478-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02478-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02478-2)
Primary antibodyRabbit anti-NDEL1, 2-5μg/ml (datasheet A02478-2)
Primary incubationOvernight at 4 °C (datasheet A02478-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A02478-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultNDEL1-positive staining in glandular cells of colon (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA at pH 8.0 for the catalog antibody (datasheet A02478-2); sodium citrate at pH 6.0 is reported for mouse brain sections (PMC4048543).
Section 2

What Is the Expected NDEL1 Staining Pattern?

NDEL1 is associated with the cytoskeleton, centrosome and mitotic spindle, with kinetochore localisation in dividing cells (UniProt Q9GZM8: subcellular location). On tissue IHC, expect predominantly cytoplasmic staining in many tissues, especially glandular cells of the colon, duodenum, rectum and small intestine (HPA: tissue IHC). HPA rates its tissue profile Approved but reports low consistency between antibody staining and RNA expression (HPA: reliability description). NDEL1 has no transmembrane segment (UniProt Q9GZM8: topology).

What am I looking at on my slide?
Clear cytoplasmic chromogen in intestinal glandular cells, with stronger staining than adjacent background.This fits the observed pattern: glandular cells stain High in colon, duodenum, rectum and small intestine (HPA: tissue IHC). Score the cells and compartment actually stained; a positive section does not imply that every cell should be equally intense (HPA: cell-specific tissue IHC levels).
Predominantly nuclear or membranous staining, with little convincing cytoplasmic signal.That distribution does not fit HPA’s predominantly cytoplasmic tissue profile or UniProt’s cytoskeletal localisation and lack of a transmembrane segment (HPA: tissue IHC; UniProt Q9GZM8: subcellular location and topology). Check morphology and controls before assigning the signal to NDEL1; compartment alone cannot identify the source of an artefact.
Strong staining in a cell population recorded as Not detected, such as adipocytes or alveolar cells.This conflicts with those HPA observations (HPA: adipocytes and alveolar cells Not detected). Consider cross-reactivity or endogenous detection activity, and compare a no-primary control (general IHC practice). HPA’s Approved rating has low staining–RNA consistency, so a single unexpected positive result needs corroboration (HPA: reliability description).
Weak, diffuse colour extends across cells, stroma and empty areas without a readable cell boundary.Treat this as background until a cell-specific cytoplasmic pattern can be distinguished (HPA: cytoplasmic expression in most tissues). Review the no-primary control, blocking, washes and chromogen development (general IHC practice). Diffuse colour by itself cannot establish NDEL1 localisation.
No signal in glandular cells of a colon, duodenum, rectum or small-intestine section.These are High-staining cell populations in the HPA tissue record, so an entirely blank result warrants an assay check (HPA: tissue IHC). Confirm that the section contains intact glandular cells, then review retrieval, antibody incubation and detection with the assay controls (general IHC practice). A blank slide alone does not show biological absence.
💡Expected NDEL1 appearanceCall the IHC result positive when distinct cytoplasmic staining is visible in intestinal glandular cells at a clearly readable intensity (HPA: High in colon, duodenum, rectum and small intestine); isolated nuclear or membranous colour, or uniform colour outside cells, does not match the expected pattern (HPA: cytoplasmic tissue profile; UniProt Q9GZM8: topology).
How each factor affects the staining
Tissue and cell selectionUse HPA’s cell-level observations to interpret the slide: intestinal glandular cells are High, whereas adipocytes and alveolar cells are Not detected (HPA: tissue IHC). These observations guide comparison, but HPA reports low consistency between staining and RNA data (HPA: reliability description).
Antibody evidenceThe listed HPA antibody, HPA017916, is rated Approved for IHC; its supplied record does not say Enhanced (HPA: antibody validation). Treat agreement with the expected tissue pattern as supportive, while investigating unexpected staining with controls rather than assuming independent antibody confirmation.
Isoforms and epitopeUniProt lists three NDEL1 isoforms, but the supplied evidence gives no antibody epitope or isoform-specific staining result (UniProt Q9GZM8: isoforms; HPA: supplied antibody record). Do not infer that a tissue difference reflects a particular isoform; establish antibody recognition separately if that distinction matters.
IF/ICC Q&A: what pattern is established?UniProt places NDEL1 at cytoskeletal and centrosomal sites, including the mitotic spindle (UniProt Q9GZM8: subcellular location). HPA supplies no main ICC-IF location or cell-line images, and the listed antibody has no ICC status (HPA: subcellular and antibody records). These data do not establish an observed IF pattern.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Intestinal glandular cells are blank.A failed assay step is possible when a cell population reported High is unstained (HPA: intestinal glandular cells High); the image alone cannot identify which step failed.Confirm glandular morphology and assess retrieval, primary incubation and detection against appropriate assay controls (general IHC practice). Record the blank result as inconclusive until the controls work.
Staining appears mainly nuclear.The dominant compartment differs from HPA’s cytoplasmic tissue profile and UniProt’s cytoskeletal localisation (HPA: tissue IHC; UniProt Q9GZM8: subcellular location).Check whether cytoplasmic staining is also present, inspect the no-primary control and compare another expected-positive section (general IHC practice; HPA: intestinal glandular cells High).
Colour covers the section without a cell-specific pattern.Background from nonspecific binding or detection may obscure localisation (general IHC practice); broad colour alone does not match HPA’s interpretable cytoplasmic expression.Inspect a no-primary control, review blocking and washes, and stop chromogen development before background hides cell boundaries (general IHC practice). Reassess only clearly localised signal.
Adipocytes or alveolar cells stain strongly.Those cells are listed as Not detected in the supplied HPA observations; cross-reactivity or endogenous detection activity is possible (HPA: tissue IHC; general IHC practice).Compare the no-primary control and a High-staining intestinal glandular population (general IHC practice; HPA: tissue IHC). Treat a conflicting stain cautiously because HPA reports low staining–RNA consistency (HPA: reliability description).
Only a few cells show intense focal colour.A focal signal needs cell and compartment identification: UniProt includes centrosome, spindle and kinetochore localisation, while HPA describes predominantly cytoplasmic tissue staining (UniProt Q9GZM8: subcellular location; HPA: tissue IHC).Check cell morphology and whether the signal tracks the expected compartment; compare neighbouring cells and a no-primary control (general IHC practice). Do not score isolated deposits as positive cells.
Two tissues yield different staining intensities.HPA reports cell-specific levels ranging from High intestinal glandular staining to Low hippocampal neuronal staining and Not detected adipocytes (HPA: tissue IHC).Compare the named cell populations within each section, using the same scoring criteria (general IHC practice). Interpret differences with HPA’s reported low staining–RNA consistency in mind (HPA: reliability description).

Sample controls for NDEL1 IHC & IF

🧪Run colon first: glandular cells should show strong staining (HPA: High in colon glandular cells); use adipose tissue as a negative comparator, where adipocytes are not detected (HPA: Not detected in adipocytes). On the colon slide, nonglandular cells that remain pale relative to the glands can serve as internal background comparators, but these HPA rows do not establish that they lack NDEL1 (HPA: High in colon glandular cells).
Positive control tissue: Colon (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for NDEL1; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary (secondary-only) control, a matched rabbit IgG isotype control, and an NDEL1 knockout sample if available (caption: rabbit anti-NDEL1; standard IHC control practice). For colon sections developed with SABC/DAB, quench endogenous peroxidase and block endogenous biotin to assess background (caption: SABC/DAB; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A02478-2 paraffin-section caption does not state a fixative (caption: fixative not stated). Heat-mediated retrieval in EDTA at pH 8.0 was used, but whether staining depends on retrieval is unreported (caption: EDTA pH 8.0). Frozen-section and IF performance are unreported in the supplied application evidence; endogenous biotin is a potential background source in intestinal tissue when using SABC detection (caption: SABC; standard IHC practice).

HPA tissue IHC evidence for NDEL1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Rectum Glandular cells High Protein (IHC) HPA →
Small intestine Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Fallopian tube Glandular cells Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Section 3

Advanced NDEL1 IHC Tips

Troubleshoot NDEL1 chromogenic IHC in paraffin sections by checking retrieval, tissue handling, staining pattern and controls before interpreting signal.

Which retrieval conditions should I try first for NDEL1 paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 for NDEL1 paraffin sections (datasheet A02478-2). Run a timed retrieval series on adjacent sections, keeping antibody concentration and detection conditions constant so changes in staining can be attributed to retrieval (standard IHC practice). The product image used 2 μg/ml primary antibody overnight at 4°C, providing a starting point when reproducing that workflow (datasheet A02478-2). If staining remains weak, compare retrieval durations before considering another buffer as a fallback, and assess tissue morphology alongside signal (standard IHC practice). Include a section processed without primary antibody to distinguish improved staining from detection background (standard IHC practice).
Could fixation explain weak or uneven NDEL1 staining?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not state a fixative (datasheet A02478-2). Record fixative, fixation duration, block age and section thickness for each specimen, then compare matched sections under the same retrieval and detection conditions (standard IHC practice). If weak staining tracks with processing batches, test adjacent sections using a controlled retrieval-time series while checking whether morphology remains interpretable (standard IHC practice). Avoid assigning a particular fixation effect to NDEL1 from its tissue distribution or cellular location; neither establishes fixation sensitivity (HPA tissue IHC; UniProt Q9GZM8 subcellular location). Use an independently characterized control section in each run to identify broader processing failures (standard IHC practice).
Where should convincing NDEL1 chromogenic signal appear?
Expect predominantly cytoplasmic staining across many tissues, with possible enrichment near centrosomes or the spindle in suitable cells (HPA tissue IHC: cytoplasmic expression; UniProt Q9GZM8 subcellular location). NDEL1 is also reported at kinetochores and alongside assembled neurofilaments in axonal processes, so examine cellular context before calling a focal pattern nonspecific (UniProt Q9GZM8 subcellular location). High glandular-cell staining in colon, duodenum, rectum and small intestine offers reference patterns for comparing cytoplasmic signal (HPA tissue IHC: High in glandular cells). Review the hematoxylin counterstain and adjacent morphology to assign signal to cells rather than luminal material (standard IHC practice). Diffuse nuclear-only staining warrants scrutiny against controls and expected localisation (UniProt Q9GZM8 subcellular location; standard IHC practice).
Can this stain distinguish NDEL1 isoforms or phosphorylation states?
NDEL1 has 3 annotated isoforms, but the supplied caption does not identify the antibody epitope or demonstrate isoform selectivity (UniProt Q9GZM8 isoforms; datasheet A02478-2). Several modified residues are annotated, including phosphorylation at positions 215, 219, 231, 242 and 245 (UniProt Q9GZM8 modified residues). Therefore, score this stain as NDEL1 immunoreactivity without assigning an isoform or phosphorylation state from intensity alone (UniProt Q9GZM8 isoforms and modified residues; standard IHC interpretation). If that distinction matters, obtain the epitope sequence and validate specificity using appropriate orthogonal controls (standard antibody-validation practice). Keep retrieval and detection settings consistent across compared sections because either can alter apparent intensity (standard IHC practice).
How should I follow up an IHC pattern with multiplex IF?
For a follow-up IF experiment, pair NDEL1 with a marker of the cell population under study and use the chromogenic section to guide which cells to inspect (standard multiplex IF practice). Choose fluorophores whose emission is well separated from measured tissue autofluorescence, and include single-label and no-primary controls before interpreting overlap (standard multiplex IF practice). NDEL1 is reported in cytoskeletal and centrosomal compartments and has no annotated transmembrane segment, so assess access to an intracellular epitope with a controlled permeabilisation series (UniProt Q9GZM8 subcellular location and topology; standard IF practice). The paraffin IHC caption does not establish IF performance, fixation conditions or an IF antibody dilution (datasheet A02478-2). Confirm the IF pattern independently before treating colocalisation as evidence of physical interaction (standard IF interpretation).
What should I check when DAB staining appears widespread?
First compare the stained section with a no-primary control and inspect whether pigment follows tissue edges, damaged regions or the expected cellular pattern (standard IHC practice). The selected workflow used a biotinylated secondary, streptavidin–biotin complex and DAB, so evaluate secondary-reagent background and endogenous biotin when background persists (datasheet A02478-2; standard IHC practice). Apply an endogenous peroxidase block and keep DAB development consistent across slides; these are general chromogenic IHC controls, not NDEL1-specific requirements (standard IHC practice). The caption used 10% goat serum for blocking and 2 μg/ml primary antibody, useful reference conditions when reproducing that image (datasheet A02478-2). Titrate primary antibody against a control tissue while preserving visible cell boundaries (standard IHC practice).
How can I quantify NDEL1 IHC across specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the compartment and cell population before scoring, because NDEL1 is reported mainly as cytoplasmic tissue staining with context-dependent cytoskeletal localisation (HPA tissue IHC; UniProt Q9GZM8 subcellular location). For a defined cell population, record the percentage of positive cells and an H-score based on staining intensity; use density per mm² when counting discrete positive cells in tissue areas (standard IHC scoring practice). Normalise cell counts to viable tissue area and report the number of eligible cells, excluding folds and necrotic regions (standard IHC quantification practice). Hold section thickness, retrieval, antibody incubation and DAB development constant across batches, with a reference section for comparison (standard IHC practice). Report cell-type-specific results because whole-section averages can obscure differences in tissue composition (standard IHC quantification practice).
How do I separate true NDEL1 staining from artefact?
Give greatest weight to reproducible cytoplasmic signal in identifiable cells; NDEL1 is reported in cytoskeletal compartments, and HPA describes cytoplasmic expression in most tissues (UniProt Q9GZM8 subcellular location; HPA tissue IHC). High staining in glandular cells of colon, duodenum, rectum and small intestine provides a documented reference, while an unexpected cell pattern needs independent checking (HPA tissue IHC: High in glandular cells). Inspect nuclear-only signal, edge staining, necrosis and DAB deposition that also appears in no-primary controls before calling a section positive (UniProt Q9GZM8 subcellular location; standard IHC practice). Rule out endogenous peroxidase activity with appropriate controls when diffuse brown signal persists (standard IHC practice). Interpret intensity cautiously because the HPA assessment reports low agreement between antibody staining and RNA expression (HPA tissue IHC: Approved, low consistency).
Boster reagents

Best NDEL1 / Nuclear distribution protein nudE-like 1 IHC Antibodies

NDEL1 antibodies have human paraffin-section IHC images and human Jurkat-cell ICC/IF images; catalog reactivity also includes mouse and rat for selected antibodies (catalog image captions; catalog reactivity).

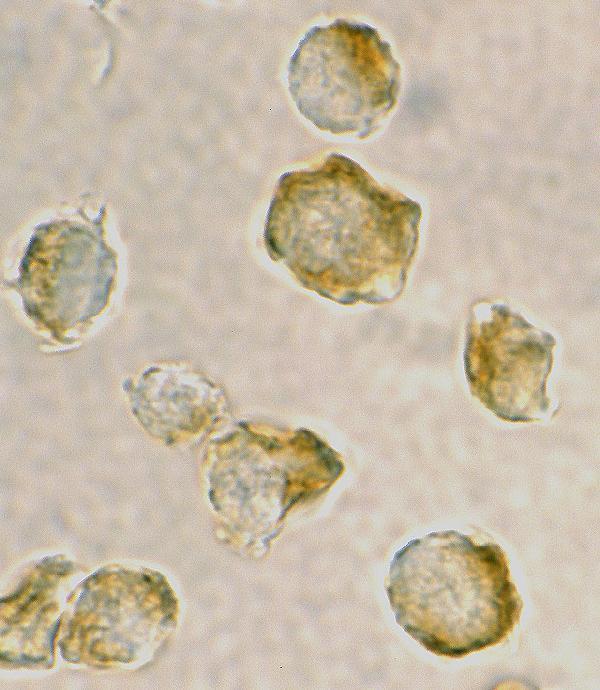
Real IHC data IHC analysis of NDEL1 using anti-NDEL1 antibody (A02478-2). NDEL1 was detected in a paraffin-embedded section of human endometrial cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-NDEL1 Antibody (A02478-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-NDEL1 Antibody ®
Cat # A02478-2
Real IF data Immunocytochemistry of Nudel in Jurkat cells with Nudel antibody at 2 μg/mL.
Anti-Nudel NDEL1 Antibody
Cat # A02478

A02478-2 will render with human paraffin-section IHC data from endometrial cancer tissue (A02478-2 IHC image caption). A02478 will render with Jurkat-cell ICC data; its catalog also lists IF and human/mouse reactivity (A02478 image caption; catalog applications and reactivity).

Which to pick: Choose A02478-2 for human paraffin-section IHC: its image caption documents EDTA retrieval at pH 8.0 and 2 μg/mL primary antibody, but does not report the fixative (A02478-2 IHC image caption). Choose A02478 for human-cell IF/ICC; it lists mouse reactivity too, although the supplied images show Jurkat cells (A02478 IF/ICC image captions; catalog reactivity). For mouse or rat tissue IHC, M02478-2 is the catalog-listed rabbit monoclonal option, with IHC in its application list and human/mouse/rat reactivity; no IHC image or fixation method is supplied for it (M02478-2 catalog entry).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9GZM8 (NDEL1_HUMAN, Nuclear distribution protein nudE-like 1).
  2. Human Protein Atlas. NDEL1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. NDEL1 subcellular location (ICC-IF): Highest expression in BJ [Human fibroblast]: 82.8 nTPM.
  4. Human Protein Atlas. NDEL1 antibody validation summary (1 antibodies).
  5. Status epilepticus stimulates NDEL1 expression via the CREB/CRE pathway in the adult mouse brain. Neuroscience 2016 — PMC5363720.
  6. Expression and function of Ndel1 during the differentiation of neural stem cells induced by hippocampal exosomesticle. Stem cell research & therapy 2021 — PMC7796549.
  7. Sequential phosphorylation of NDEL1 by the DYRK2-GSK3β complex is critical for neuronal morphogenesis. eLife 2019 — PMC6927744.
  8. The expression and roles of Nde1 and Ndel1 in the adult mammalian central nervous system. Neuroscience 2014 — PMC4048543.
  9. PubMed PMID:11163260 — UniProt-cited evidence.
  10. PubMed PMID:12556484 — UniProt-cited evidence.
  11. PubMed PMID:15728732 — UniProt-cited evidence.