NDUFB8 / NADH dehydrogenase [ubiquinone] 1 beta subcomplex subunit 8, mitochondrial · IHC design guide

Design Immunohistochemistry for NDUFB8

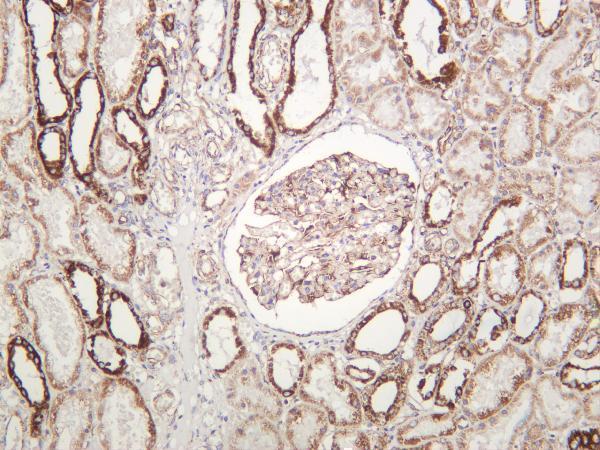
NDUFB8 shows granular cytoplasmic staining in tissue IHC, consistent with its mitochondrial location (HPA tissue IHC; UniProt). Plan paraffin IHC with 2–5 μg/ml catalog antibody and use cardiomyocytes or kidney tubules as positive controls (datasheet A07936-1; HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for NDUFB8 (IHC for NDUFB8): expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial inner membrane (UniProt), antibody A07936-1, validated IHC image, and IHC protocol steps
Printable NDUFB8 IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial inner membrane (UniProt), antibody A07936-1, controls and protocol steps. Open the full NDUFB8 IHC guide →

NDUFB8 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial inner membrane (UniProt)
Staining pattern Ubiquitous granular cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A07936-1)
Positive control ⓘ Bone marrow+4 more · see all
Negative control ⓘ Adipose tissue+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific)
Caveat Bone marrow cells may show endogenous peroxidase (HPA tissue IHC; standard IHC practice)
Regulation Low tissue specificity (HPA tissue RNA)
Isoform / epitope 3 isoforms; epitope map unreported (UniProt)
Section 1

Recommended NDUFB8 IHC & IF Protocols

This section pairs the catalog antibody’s IHC-P protocol with one published NDUFB8 IHC protocol (datasheet A07936-1; PMC10868282).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human laryngeal squamous cell carcinoma tissue; fixative not specified (datasheet A07936-1)
FixationImage fixative and duration unreported (datasheet A07936-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A07936-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A07936-1)
Primary antibodyRabbit anti-NDUFB8, 2-5 μg/ml (datasheet A07936-1)
Primary incubationOvernight at 4 °C (datasheet A07936-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A07936-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultNDUFB8-positive staining in hematopoietic cells of bone marrow (HPA tissue IHC: High). HPA tissue profile: Ubiquitous granular cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet A07936-1); the published protocol reports retrieval without specifying its conditions (PMC10868282).
Section 2

What Is the Expected NDUFB8 Staining Pattern?

NDUFB8 is a Complex I subunit in the mitochondrial inner membrane, with a transmembrane segment at residues 133–153 (UniProt O95169 topology). In paraffin section IHC, expect granular cytoplasmic staining in many cell types, including cardiomyocytes and kidney tubular cells (HPA tissue IHC: High). HPA rates the tissue pattern Supported, with medium consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Granular cytoplasmic staining in cardiomyocytes, kidney tubular cells, or other HPA high groups (HPA tissue IHC: High).This fits the reported ubiquitous granular cytoplasmic profile (HPA tissue IHC) and mitochondrial inner membrane location (UniProt O95169). Read intensity within identified cell types; an HPA High designation does not set an intensity threshold for every section.
Predominantly nuclear, sharply surface restricted, or uniform cytoplasmic staining without granules.These patterns do not fit mitochondrial localization (UniProt O95169; HPA subcellular ICC/IF: mitochondria). Consider nonspecific binding, detection artifact, or a misread compartment; inspect a known positive area and the negative reagent control before assigning NDUFB8.
Strong staining in adipocytes or thyroid glandular cells alongside weak expected positive cells (HPA tissue IHC: Not detected in those cells).That discordance raises cross reactivity or endogenous detection activity as possibilities (general IHC interpretation). HPA also describes NDUFB8 expression as ubiquitous, so one discordant cell group is a prompt to check controls, not proof of antibody failure (HPA tissue IHC).
Diffuse color covers cells and surrounding tissue, obscuring cytoplasmic granules.The distribution prevents a confident compartment call against the reported granular profile (HPA tissue IHC). Check the negative reagent control, blocking, washes, and detection exposure as general IHC practice; diffuse color alone cannot establish NDUFB8 expression.
No staining in cardiomyocytes or kidney tubular cells expected to be High (HPA tissue IHC).Treat the run as unresolved until a positive control stains. As general IHC practice, check tissue preservation, retrieval and detection records, reagent performance, and counterstain visibility. HPA staining levels do not establish NDUFB8 specific fixation sensitivity.
💡Expected NDUFB8 appearanceCall positive when identifiable cells show cytoplasmic granules, especially HPA High cardiomyocytes or kidney tubular cells (HPA tissue IHC); nuclear staining or diffuse color without granules is suspect given mitochondrial localization (UniProt O95169; HPA subcellular ICC/IF).
How each factor affects the staining
Compartment and membrane topologyUniProt places NDUFB8 in the mitochondrial inner membrane and annotates one transmembrane segment at 133–153 (UniProt O95169). HPA describes tissue IHC as granular cytoplasmic (HPA tissue IHC). These facts guide localization scoring; they do not identify the catalog antibody's epitope.
Cell type and tissue contextHPA reports High staining in cardiomyocytes, kidney tubular cells, type II alveolar cells, and several other groups; adipocytes and thyroid glandular cells are Not detected (HPA tissue IHC). These are observed reference patterns, not guarantees for every specimen or processing run.
Strength of tissue IHC evidenceThe tissue profile is Supported with medium antibody to RNA consistency (HPA tissue IHC). HPA003886 is Supported for IHC, while the supplied record gives no IHC status for HPA065549 (HPA antibodies). Interpret unexpected staining with controls rather than treating all antibody images as equal IHC validation.
Isoforms and processed chainUniProt lists three isoforms and a chain spanning residues 29–186 (UniProt O95169). The supplied records give no isoform specific tissue pattern or antibody epitope, so IHC cannot assign a granular signal to one isoform from these facts.
IF/ICC cross-check: should it look mitochondrial?Yes: HPA reports mitochondrial ICC/IF localization and Enhanced ICC validation for both listed antibodies (HPA subcellular ICC/IF; HPA antibodies). That supports the compartment expectation, but ICC validation does not establish performance or a protocol for paraffin section IHC.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known positive tissue has no visible granules.A failed staining run or an unsuitable specimen is possible; HPA reports High cardiomyocyte and kidney tubular staining (HPA tissue IHC).Verify the positive control, reagent sequence, retrieval record, and detection step (general IHC practice). Do not infer a NDUFB8 specific fixation effect from HPA's tissue profile.
Nuclei dominate the stain.Nuclear dominance conflicts with mitochondrial localization (UniProt O95169; HPA subcellular ICC/IF). Nonspecific detection is possible.Compare the negative reagent control and review blocking and detection conditions (general IHC practice); score only interpretable cytoplasmic granules against the tissue context.
Color is diffuse across cells and extracellular space.Background obscures the granular cytoplasmic profile (HPA tissue IHC); excessive detection or incomplete washing can contribute (general IHC practice).Check the negative reagent control, washes, and detection exposure (general IHC practice). Reassess localization only after cell boundaries and granules can be distinguished.
Adipocytes or thyroid glandular cells stain strongly.HPA reports these cell groups as Not detected (HPA tissue IHC); cross reactivity or endogenous detection activity merits investigation (general IHC interpretation).Identify the stained cell type, inspect a negative reagent control, and compare a positive tissue in the same run (general IHC practice). Avoid calling the discordance NDUFB8 without supporting controls.
Only a few cells stain in a tissue expected to be positive.Cell composition and run quality can complicate interpretation (general IHC practice); HPA's High designation names specific cell groups, not every cell in a tissue (HPA tissue IHC).Locate the HPA named cell group, then compare its granularity with the positive control and the negative reagent control before scoring the specimen.
An IF/ICC image looks mitochondrial, but paraffin section IHC is ambiguous.HPA reports mitochondrial ICC/IF localization, while its supplied antibody statuses distinguish Enhanced ICC from Supported or unreported IHC (HPA subcellular ICC/IF; HPA antibodies).Judge the paraffin section by its own controls and granular cytoplasmic pattern (HPA tissue IHC; general IHC practice). Do not transfer an ICC validation rating to IHC.

Sample controls for NDUFB8 IHC & IF

🧪Run heart muscle first and look for staining in cardiomyocytes (HPA: High in cardiomyocytes). Use adipose tissue as the negative comparison, with adipocytes expected to show no detected signal (HPA: Not detected in adipocytes); on the heart slide, non-cardiomyocyte cells can provide a background comparison, but their NDUFB8 status is unreported (HPA: High in cardiomyocytes).
Positive control tissue: Bone marrow (Hematopoietic cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show NDUFB8 in A-431, U-251MG, U2OS, Sperm, with annotated localisation: Mitochondria (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and concentration-matched nonimmune rabbit IgG isotype control because the catalog primary is rabbit-derived (selected-SKU caption: rabbit anti-NDUFB8); use NDUFB8 knockout material as a biological negative if available (standard IHC practice). Block endogenous peroxidase and check the no-primary heart section for blood-associated DAB background (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU paraffin-section caption does not state a fixative (selected-SKU caption: fixative unreported). The caption uses heat retrieval in EDTA at pH 8.0, which is a starting condition rather than evidence that retrieval is required (selected-SKU caption: EDTA, pH 8.0). Paraffin IHC has a reported example; the supplied evidence does not establish whether frozen sections or IF are easier, and blood-associated peroxidase can complicate chromogenic interpretation in heart sections (selected-SKU caption: paraffin IHC; standard IHC practice).

HPA tissue IHC evidence for NDUFB8

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Cerebellum GLUC cells - cytoplasm/membrane High Protein (IHC) HPA →
Heart muscle Cardiomyocytes High Protein (IHC) HPA →
Kidney Cells in tubules High Protein (IHC) HPA →
Lung Alveolar cells type II High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Thyroid gland Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced NDUFB8 IHC Tips

Use compartment, cell type, and matched controls to troubleshoot NDUFB8 staining in chromogenic IHC; assess IF as a separate application.

Which retrieval conditions should I try first for weak NDUFB8 staining?
Start with heat-mediated retrieval in EDTA buffer at pH 8.0 for paraffin sections (datasheet A07936-1). The selected tissue image used this retrieval before overnight incubation at 4°C with 2 μg/ml primary antibody (caption A07936-1). If staining remains weak, vary heating duration on matched sections while holding antibody concentration, detection, and development constant; include a positive tissue control in each run (standard IHC practice; HPA: high in heart muscle cardiomyocytes). Record both signal and tissue damage, because excessive retrieval can impair morphology and make granular cytoplasmic staining harder to assess (standard IHC practice; HPA: ubiquitous granular cytoplasmic expression).
Could fixation explain inconsistent NDUFB8 staining between paraffin blocks?
The selected image identifies a paraffin-embedded section but does not state its fixative, so NDUFB8-specific fixation sensitivity is unknown (caption A07936-1). Compare sections with documented fixation histories using the same EDTA pH 8.0 retrieval, 2 μg/ml primary antibody, and overnight 4°C incubation used in that image (caption A07936-1). Keep section thickness, peroxidase blocking, and DAB development consistent so processing differences can be assessed against morphology and background (standard IHC practice). Include a matched positive control and record whether loss of granular cytoplasmic signal tracks with block history; the HPA staining pattern alone cannot establish a fixation effect (standard IHC practice; HPA: ubiquitous granular cytoplasmic expression).
What staining pattern fits NDUFB8, and when is localisation suspicious?
Expect fine, granular cytoplasmic staining consistent with mitochondrial distribution, rather than a diffuse nuclear signal (HPA: ubiquitous granular cytoplasmic expression; UniProt O95169: inner mitochondrial membrane). Examine high-resolution fields and compare granules with cell boundaries and tissue morphology, since a brown DAB deposit can obscure individual mitochondria in dense cytoplasm (standard IHC practice). A positive control can be heart muscle cardiomyocytes or kidney tubular cells, both reported as high by tissue IHC (HPA: high in cardiomyocytes and kidney tubular cells). If staining concentrates at section edges, in necrotic areas, or over nuclei, review retrieval, blocking, and detection controls before assigning it to NDUFB8 (standard IHC practice).
Can epitope placement explain loss of staining in some sections?
NDUFB8 has 3 annotated isoforms, a processed chain spanning residues 29–186, and one transmembrane segment at 133–153 (UniProt O95169). The supplied product evidence does not map the antibody epitope, so staining cannot be assigned to a particular isoform or membrane-facing region (datasheet A07936-1: epitope not supplied; UniProt O95169: topology). If a sample stains weakly, compare retrieval conditions on adjacent sections and assess preservation with a separate mitochondrial marker (standard IHC practice). Interpret a negative result cautiously until epitope recognition and section processing are checked, especially when a positive control retains granular cytoplasmic staining (standard IHC practice; HPA: ubiquitous granular cytoplasmic expression).
How should I assess NDUFB8 in a multiplex IF experiment?
Treat IF as a separate validation task: the selected antibody image documents paraffin-section chromogenic IHC, while HPA reports mitochondrial IF localisation (caption A07936-1; HPA subcellular: mitochondria). Pair NDUFB8 with a validated marker for the expected cell type, such as cardiomyocytes in heart muscle, and use distinct fluorophore channels with single-stain controls (HPA tissue IHC: high in cardiomyocytes; standard IF practice). Select fluorophores after checking tissue autofluorescence and exposure settings, then assess whether the NDUFB8 signal has a granular mitochondrial pattern (standard IF practice; HPA subcellular: mitochondria). Because the epitope's membrane-facing side is unspecified, optimise permeabilisation empirically with matched controls rather than assuming accessibility from the 133–153 transmembrane segment (UniProt O95169: topology; standard IF practice).
How can I reduce diffuse brown background without losing NDUFB8 signal?
First distinguish diffuse DAB haze from the granular cytoplasmic pattern reported for NDUFB8 (HPA: ubiquitous granular cytoplasmic expression). The selected paraffin-section example used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and a peroxidase-linked secondary for 30 minutes at 37°C (caption A07936-1). Run no-primary and secondary-only controls, block endogenous peroxidase, wash thoroughly, and shorten DAB development if background obscures cells (standard chromogenic IHC practice). If controls are clean but staining remains diffuse, titrate the primary antibody around the documented concentration on matched sections while retaining a positive tissue control (standard IHC practice; caption A07936-1).
How should I quantify NDUFB8 IHC across samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring: NDUFB8 is reported as granular cytoplasmic staining, with high signal in kidney tubular cells and cardiomyocytes (HPA: expression profile and tissue IHC). Score the percentage of positive cells and intensity with an H-score, or measure positive area per mm² within a defined region (standard IHC quantification practice). Normalise to viable target-cell area or cell count, and apply the same threshold, counterstain, and DAB development settings across sections (standard IHC quantification practice). Report controls and regional variability separately, because mixed cell populations and tissue damage can change an aggregate score without establishing a change in NDUFB8 per cell (standard IHC interpretation practice).
When is an apparent NDUFB8-positive result likely to be artefactual?
A convincing result shows granular cytoplasmic staining in viable cells, consistent with NDUFB8's mitochondrial inner-membrane location (HPA: expression profile; UniProt O95169: subcellular location). Compare cell identity with tissue context: HPA reports high staining in cardiomyocytes and kidney tubular cells but no detection in adipocytes and thyroid glandular cells (HPA tissue IHC). Nuclear-only signal, section-edge accentuation, necrotic deposits, or staining reproduced in a no-primary control warrants investigation before a positive call (standard IHC interpretation practice). Check endogenous peroxidase blocking and DAB development, then repeat with a matched positive control; HPA labels its tissue staining reliability “Supported” with medium agreement between staining and RNA data (standard IHC practice; HPA: reliability).
Boster reagents

Best NDUFB8 / NADH dehydrogenase [ubiquinone] 1 beta subcomplex subunit 8, mitochondrial IHC Antibodies

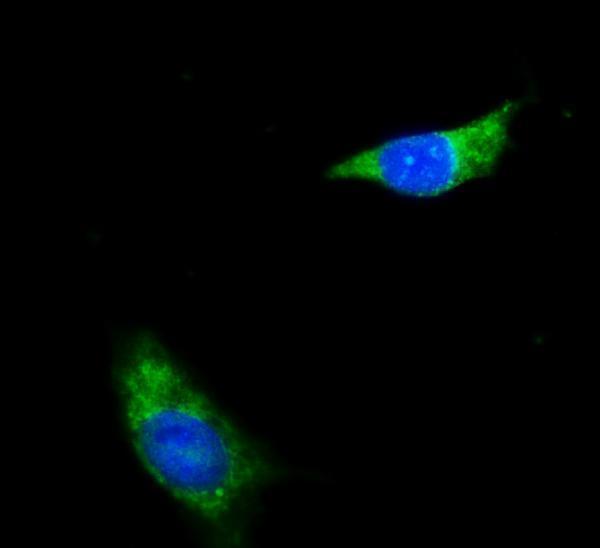
The catalog covers human and mouse tissue IHC images (catalog IHC captions) and IF in HepG2 cells (A07936-1 IF caption); both pictured antibodies list human, mouse, and rat reactivity (catalog applications/reactivity).

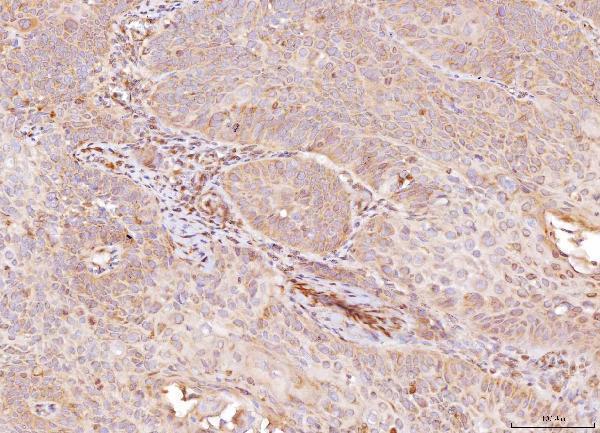
Real IHC data IHC analysis of NDUFB8 using anti-NDUFB8 antibody (A07936-1). NDUFB8 was detected in a paraffin-embedded section of human laryngeal squamous cell carcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-NDUFB8 Antibody (A07936-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-NDUFB8 Antibody ®
Cat # A07936-1
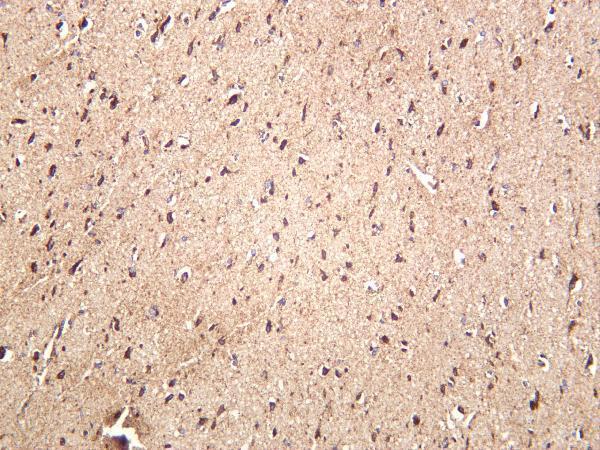
Real IHC data Human brain was stained with anti-NDUFB8 rabbit antibody
Anti-NDUFB8 Rabbit Monoclonal Antibody
Cat # M07936-2

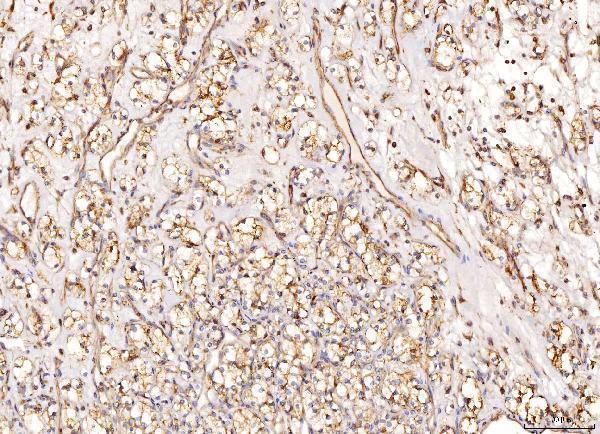
A07936-1 will render with its paraffin-section IHC image from human laryngeal squamous cell carcinoma; its separate IF image shows HepG2 cells (A07936-1 image captions). M07936-2 will render with its human brain IHC image; additional IHC captions show human kidney and mouse brain (M07936-2 IHC captions).

Which to pick: For paraffin-section IHC with documented retrieval conditions, choose A07936-1: its own caption specifies EDTA at pH 8.0 and 2 μg/ml primary antibody; the fixative is unreported (A07936-1 IHC caption). For IF/ICC, A07936-1 has a HepG2 IF image and lists both IF and ICC; M07936-2 lists IF but has no IF image in this payload (catalog applications and IF captions). For human or mouse tissue IHC, M07936-2 is a monoclonal option with images from both species; both SKUs list rat reactivity, but neither has a rat IHC image here (catalog descriptions, reactivity, and IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O95169 (NDUB8_HUMAN, NADH dehydrogenase [ubiquinone] 1 beta subcomplex subunit 8, mitochondrial).
  2. Human Protein Atlas. NDUFB8 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. NDUFB8 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. NDUFB8 antibody validation summary (2 antibodies).
  5. Targeting oxidative phosphorylation to increase the efficacy of immune-combination therapy in renal cell carcinoma. Journal for immunotherapy of cancer 2024 — PMC10868282.
  6. Expression pattern of mitochondrial respiratory chain enzymes in skeletal muscle of patients with mitochondrial myopathy associated with the homoplasmic m.14674T>C variant. Brain pathology (Zurich, Switzerland) 2022 — PMC9245933.
  7. Inhibition of mitochondrial respiration prevents BRAF-mutant melanoma brain metastasis. Acta neuropathologica communications 2019 — PMC6456988.
  8. Molecular Characterization and Clinical Relevance of Lysine Acetylation Regulators in Urological Cancers. Frontiers in oncology 2021 — PMC8202406.
  9. PubMed PMID:9878551 — UniProt-cited evidence.
  10. PubMed PMID:11042152 — UniProt-cited evidence.
  11. PubMed PMID:11230166 — UniProt-cited evidence.