NRAS / GTPase NRas · IHC design guide

Design Immunohistochemistry for NRAS

Plan chromogenic NRAS IHC in paraffin sections using colon glandular cells as a positive tissue reference (HPA tissue IHC). Assess cytoplasmic and membranous staining with appropriate controls, and interpret results cautiously because tissue staining reliability is uncertain (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for NRAS (IHC for NRAS): expected localisation Cytoplasmic and membranous tissue staining (HPA tissue IHC), antibody A00099-3, validated IHC image, and IHC protocol steps
Printable NRAS IHC protocol sheet — expected localisation Cytoplasmic and membranous tissue staining (HPA tissue IHC), antibody A00099-3, controls and protocol steps. Open the full NRAS IHC guide →

NRAS Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and membranous tissue staining (HPA tissue IHC)
Staining pattern Glandular cells show cytoplasmic and membranous staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A00099-3)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across samples (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A00099-3)
Caveat Staining may detect proteins from more than one gene (HPA tissue IHC)
Regulation Staining-linked regulation is unreported (UniProt)
Isoform / epitope No isoforms; processing removes residues 187–189 (UniProt)
Section 1

Recommended NRAS IHC & IF Protocols

The catalog antibody has an IHC-P protocol (datasheet A00099-3). The published options below use clone SP174 for NRAS Q61R staining (PMC7888553; PMC8458224; PMC5719500).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon cancer tissue; fixative not specified (datasheet A00099-3)
FixationImage fixative and duration unreported (datasheet A00099-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A00099-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A00099-3)
Primary antibodyRabbit anti-NRAS, 2-5 μg/ml (datasheet A00099-3)
Primary incubationOvernight at 4 °C (datasheet A00099-3)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A00099-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultNRAS-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and membranous expression in several tissues. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet A00099-3). The published SP174 retrieval conditions apply to Q61R staining (PMC7888553; PMC5719500).
Section 2

What Is the Expected NRAS Staining Pattern?

NRAS is a membrane-associated protein that shuttles between the plasma membrane and Golgi; it has no transmembrane segment (UniProt P01111 localization and topology). In paraffin-section IHC, expect cytoplasmic and membranous staining, particularly in glandular cells of appendix, colon, duodenum, gallbladder, rectum, salivary gland and small intestine (HPA: High). Interpret cautiously: HPA rates tissue IHC Uncertain because staining and RNA data have low consistency, and warns that antibodies may target proteins from more than one gene.

What am I looking at on my slide?
Glandular cells show clear membranous staining with cytoplasmic staining in an expected positive tissue.This matches the reported tissue pattern (HPA: cytoplasmic and membranous; High in listed glandular cells). A chromogenic section may not resolve plasma membrane from Golgi staining; UniProt describes shuttling between those sites (UniProt P01111 localization).
Strong staining is confined to nuclei, with little corresponding membrane or cytoplasmic signal.An isolated nuclear pattern does not match the supplied localization evidence (UniProt P01111 localization; HPA: cytoplasmic and membranous). Treat it as a suspect result and examine controls and antibody specificity before assigning it to NRAS.
Cells reported as unstained, such as adipocytes in adipose tissue, show convincing signal.This conflicts with that cell-specific reference observation (HPA: adipocytes in adipose tissue Not detected). Cross-reactivity or endogenous chromogenic activity is possible; staining alone cannot distinguish them, especially given HPA's antibody specificity caution.
Chromogen appears broadly across cells and spaces without recognizable cell boundaries.This is diffuse background rather than the reported cellular pattern (HPA: cytoplasmic and membranous). Review background controls and general IHC blocking, washing and detection steps (general IHC practice).
No signal appears in glandular cells of an expected positive section.Check the assay before calling the sample negative: several glandular tissues are reported High (HPA: tissue IHC). HPA's Uncertain reliability also means a single absent result should not be treated as definitive NRAS loss.
💡Expected NRAS appearanceA persuasive positive result is distinct cytoplasmic and membranous chromogenic staining in glandular cells of an HPA High tissue, while isolated nuclear signal or broad cell-independent color is suspect (HPA: tissue IHC; UniProt P01111 localization).
How each factor affects the staining
Compartment resolutionNRAS shuttles between plasma membrane and Golgi (UniProt P01111 localization). Interpret a membrane-associated or cytoplasmic pattern in section context; do not require a separately visible Golgi outline in chromogenic IHC (general IHC practice).
Tissue and cell choiceGlandular cells in appendix, colon, duodenum, gallbladder, rectum, salivary gland and small intestine are reported High; bone-marrow hematopoietic cells are Medium (HPA: tissue IHC). Compare the same cell type when selecting controls.
Antibody validationThe reported tissue IHC reliability is Uncertain, with low staining-to-RNA consistency and a warning about proteins from more than one gene (HPA: tissue IHC). The two listed IHC antibodies are also rated Uncertain (HPA: HPA049830, CAB010157).
Processing and epitope coverageUniProt lists a 1–186 NRAS chain and residues 187–189 as propeptide (UniProt P01111 processing). The supplied records give no antibody epitope, so they cannot establish whether processing affects this assay's staining.
Paraffin-section workflowAntigen retrieval and detection conditions should be checked against an expected positive section (general IHC practice). The supplied HPA and UniProt records provide no NRAS-specific fixation sensitivity or retrieval condition.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in an expected positive tissue.An assay step may have failed, or this specimen may differ from the reported pattern; HPA rates tissue IHC Uncertain (HPA: tissue IHC).Check section integrity, retrieval, primary-antibody use and detection with appropriate controls (general IHC practice). Reassess glandular cells specifically in an HPA High tissue (HPA: tissue IHC).
Widespread diffuse chromogen obscures cell boundaries.Background from blocking, washing or the detection system is possible (general IHC practice). The appearance does not match reported cellular staining (HPA: cytoplasmic and membranous).Inspect a control lacking primary antibody, then optimize blocking, washing and detection conditions (general IHC practice). Score NRAS only where cellular localization remains discernible (HPA: tissue IHC pattern).
Nuclei stain strongly while membranes and cytoplasm do not.This compartment is unsupported by the supplied NRAS localization records (UniProt P01111 localization; HPA: tissue IHC). Antibody or detection artefact is possible.Review control sections and antibody validation before interpreting the signal; compare with the expected membranous and cytoplasmic pattern (HPA: tissue IHC; general IHC practice).
Adipocytes or another reported Not detected cell population stains.The result conflicts with the cell-specific HPA observation and may reflect cross-reactivity or endogenous detection activity (HPA: Not detected; HPA: specificity caution; general IHC practice).Check a control lacking primary antibody for detection background, then compare staining in an HPA High glandular population; do not call unexpected staining NRAS-specific from appearance alone (HPA: tissue IHC).
A positive region looks weak or uneven across the section.Section handling or detection variation can produce uneven chromogen (general IHC practice); HPA's reported levels do not specify how every individual section will stain (HPA: tissue IHC).Check morphology and control staining across the slide, then repeat or optimize routine IHC steps if the control is uneven (general IHC practice). Interpret intensity within the identified cell population.
Can the IHC-P result be used as an ICC-IF protocol or readout?ICC-IF has separate localization evidence: plasma membrane Supported, additional cytosol Uncertain (HPA: subcellular ICC-IF). Tissue IHC reliability is Uncertain (HPA: tissue IHC).Use the separate IF/ICC guide for assay design; compare localization with the HPA ICC-IF evidence rather than transferring chromogenic IHC conditions or tissue intensity expectations (HPA: subcellular ICC-IF; HPA: tissue IHC).

Sample controls for NRAS IHC & IF

🧪Run colon first and expect staining in its glandular cells (HPA: High in colon glandular cells); use cervix glandular cells as the tissue negative (HPA: Not detected in cervix glandular cells). On the colon slide, use non-glandular cells with no specific DAB signal as an internal background comparison, but verify their NRAS status before calling them biological negatives (HPA: High is reported for colon glandular cells).
Positive control tissue: Appendix (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show NRAS in A-549, HEK293, U2OS, hTERT-RPE1 (serum starved), KOLF2.1J, with annotated localisation: Plasma membrane (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a rabbit IgG isotype control matched to the primary antibody’s clonality; and an NRAS knockout biological negative (catalog caption: rabbit anti-NRAS primary). Quench endogenous peroxidase and check colon gland lumens for trapped DAB precipitate (catalog caption: HRP/DAB detection in colon cancer tissue); block endogenous biotin if an avidin–biotin detection system is used (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A00099-3 tissue-IHC caption does not state a fixative (catalog caption: fixative not stated). Heat retrieval in EDTA at pH 8.0 was used for a paraffin-embedded colon cancer section, but retrieval dependency has not been established (catalog caption: EDTA pH 8.0); the supplied evidence does not establish that frozen sections or IF are easier. For IF/ICC, plasma membrane signal is supported and cytosolic signal is uncertain (HPA: subcellular localization); in colon IHC, inspect gland lumens for DAB precipitate before scoring cellular staining (standard IHC practice).

HPA tissue IHC evidence for NRAS

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →
Rectum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced NRAS IHC Tips

Troubleshoot NRAS staining in paraffin sections using the catalog antibody’s tissue IHC example, while checking compartment, background, and scoring against the available evidence.

Which retrieval condition should I use when NRAS staining is weak?
Start with heat mediated antigen retrieval in EDTA, pH 8.0, for paraffin sections (datasheet A00099-3). The selected tissue IHC example used that condition before overnight incubation at 4°C with 2 μg/ml primary antibody (datasheet A00099-3). If staining remains weak, compare a carefully controlled alternative retrieval condition on adjacent sections while keeping antibody concentration and detection constant (standard IHC practice). Include a no primary control and inspect tissue integrity, because excessive heating can make apparent gains in signal difficult to interpret (standard IHC practice). Record retrieval time and heating method for every run; the supplied caption does not report either value (datasheet A00099-3).
How should I troubleshoot variable NRAS staining after fixation?
The selected image shows a paraffin section, but its caption does not state the fixative or fixation duration (datasheet A00099-3). Target specific fixation sensitivity is therefore unknown; do not infer it from NRAS membrane association or tissue staining patterns (UniProt P01111; datasheet A00099-3). Compare sections with documented fixation histories using the same EDTA, pH 8.0 retrieval and 2 μg/ml primary antibody conditions (datasheet A00099-3; standard IHC practice). If fixation varies, assess morphology and background alongside NRAS signal rather than treating staining intensity alone as a measure of protein abundance (standard IHC practice). Keep processing and detection matched across comparison sections (standard IHC practice).
Where should convincing NRAS staining appear in a tissue section?
Expect a membranous component because NRAS shuttles between the plasma membrane and Golgi apparatus membranes (UniProt P01111). Its sequence has no transmembrane segment, so a crisp outline is helpful but should not be the sole acceptance criterion (UniProt P01111; standard IHC practice). Cytoplasmic and membranous tissue staining has been reported, although the tissue IHC evidence has uncertain reliability (HPA tissue IHC). Evaluate glandular cells in colon as an evidence based reference, while recognizing that the selected image is from human colon cancer tissue (HPA: High in colon glandular cells; datasheet A00099-3). At 2 μg/ml, check whether the pattern survives appropriate background controls (datasheet A00099-3; standard IHC practice).
Could epitope processing or Ras family cross reactivity explain my result?
The supplied record lists 0 NRAS isoforms and a mature GTPase chain spanning residues 1–186 (UniProt P01111). It also lists a short propeptide at residues 187–189 and modifications that could matter if an antibody recognizes a nearby epitope (UniProt P01111). The supplied caption does not identify the catalog antibody’s epitope, so these features cannot establish whether processing changes its staining (datasheet A00099-3; UniProt P01111). Review available antibody specificity information before assigning a weak or unexpected pattern to an NRAS variant (standard IHC practice). Treat apparent tissue distribution cautiously because the cited tissue IHC profile warns that its antibody targets protein from more than one gene (HPA tissue IHC).
How can I use IF to investigate an ambiguous chromogenic NRAS pattern?
Use IF as a separate check of compartment and cell identity, with a marker for the expected cell type in the same specimen (standard IF practice). For colon sections, a glandular cell marker is a reasonable pairing because glandular cells show high NRAS staining in the cited tissue profile (HPA: High in colon glandular cells). Select spectrally separated fluorophores and inspect an unstained section to avoid mistaking tissue autofluorescence for NRAS signal (standard IF practice). Because NRAS associates with the cytoplasmic face of plasma and Golgi membranes, choose permeabilisation based on the antibody epitope’s accessibility; that epitope is unreported here (UniProt P01111; datasheet A00099-3). Match exposure settings across controls before comparing localisation (standard IF practice).
What should I change when NRAS DAB staining is diffuse?
First inspect a no primary control and section morphology to separate detection background from plausible cytoplasmic or membranous NRAS staining (standard IHC practice; HPA tissue IHC). The selected example used 10% goat serum, 2 μg/ml primary antibody overnight at 4°C, and a peroxidase linked secondary for 30 minutes at 37°C (datasheet A00099-3). Apply a peroxidase block and titrate antibody or wash stringency if controls show diffuse DAB deposition (standard IHC practice). Check whether dark areas track folds, damaged edges, or necrosis rather than intact cells (standard IHC practice). Keep chromogen development comparable between runs so background changes remain interpretable (standard IHC practice).
How should I score NRAS across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population and compartment before comparing slides, since reported NRAS tissue staining is cytoplasmic and membranous (HPA tissue IHC). For chromogenic IHC, record the percentage of positive cells and an intensity based H-score, or report positive cell density per mm² when cell counts are appropriate (standard IHC practice). Normalize positive counts to all eligible cells of the same type, and use a consistent viable tissue area for density measurements (standard IHC practice). Exclude folds, necrosis, and edge deposits using preset rules (standard IHC practice). Interpret small differences cautiously because the cited tissue IHC profile has uncertain reliability and low staining to RNA consistency (HPA tissue IHC).
How can I distinguish true NRAS staining from artefact?
Give the strongest weight to staining in intact cells with a plausible membrane associated or cytoplasmic pattern, rather than isolated deposits (UniProt P01111; HPA tissue IHC; standard IHC practice). Colon glandular cells provide a documented positive context, but the selected cancer tissue image alone cannot establish specificity in every cell population (HPA: High in colon glandular cells; datasheet A00099-3). Treat dominant nuclear staining, section edge enhancement, and signal confined to necrosis as findings requiring control review (UniProt P01111; standard IHC practice). A no primary control can reveal endogenous peroxidase or detection related DAB signal (standard IHC practice). Confirm unexpected patterns independently because the cited tissue IHC evidence is rated uncertain and warns of recognition of more than one gene product (HPA tissue IHC).
Boster reagents

Best NRAS / GTPase NRas IHC Antibodies

The catalog shows human colon and colon cancer IHC images and a HeLa IF image; all three products list human, mouse, and rat reactivity (catalog image captions; reactivity).

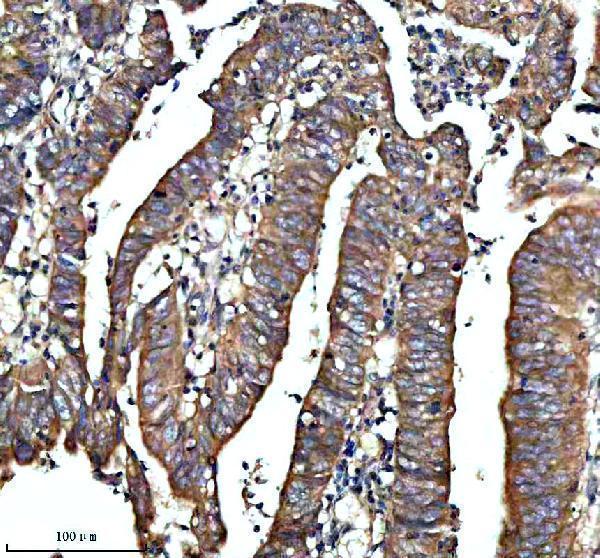
Real IHC data IHC analysis of NRAS using anti-NRAS antibody (A00099-3). NRAS was detected in a paraffin-embedded section of human colon cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-NRAS Antibody (A00099-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-NRAS Antibody ®
Cat # A00099-3
Real IHC data Human colon was stained with anti-Ras rabbit antibody
Anti-NRAS Rabbit Monoclonal Antibody
Cat # M00099-4
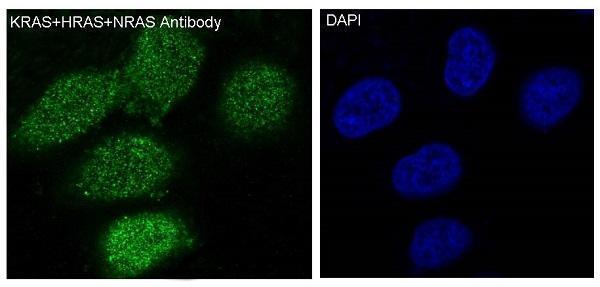
Real IF data Immunofluorescent analysis of Hela cells, using KRAS+HRAS+NRAS Antibody.
Anti-KRAS+HRAS+NRAS Rabbit Monoclonal Antibody
Cat # M00099-1

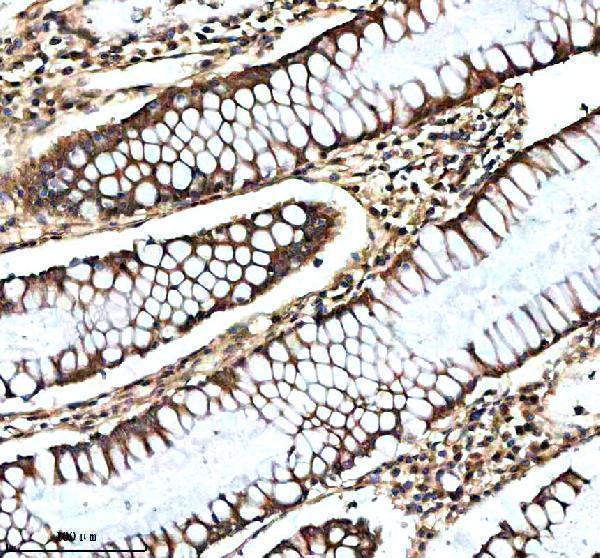
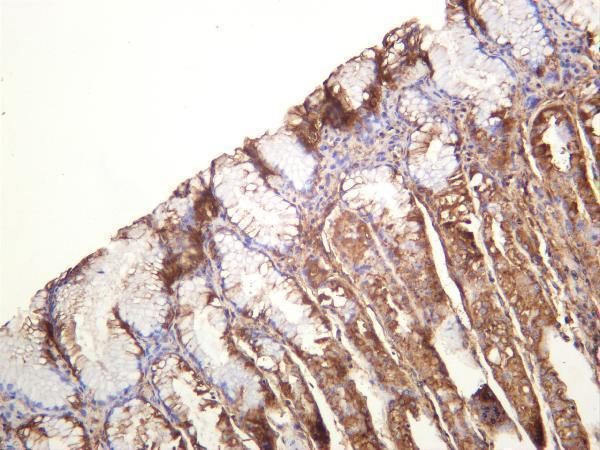
A00099-3 shows NRAS staining in paraffin-embedded human colon cancer, while M00099-4 shows staining in human colon (A00099-3 and M00099-4 image captions). M00099-1 shows IF staining in HeLa cells and lists IF/ICC applications; its antibody targets KRAS, HRAS, and NRAS (M00099-1 image caption; catalog applications and title).

Which to pick: For tissue IHC, choose A00099-3 when a documented paraffin-section procedure matters: its caption specifies EDTA retrieval at pH 8.0, 2 μg/ml antibody, and DAB detection; the fixative is unreported (A00099-3 image caption). M00099-4 offers a monoclonal IHC option with a human colon image, but its caption gives no processing details (M00099-4 catalog title and image caption). For IF/ICC, M00099-1 has a HeLa IF image but recognizes all three Ras isoforms; for cross-species planning, all three list human, mouse, and rat reactivity, while their supplied images document human samples only (M00099-1 catalog title and image caption; catalog reactivity and image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P01111 (RASN_HUMAN, GTPase NRas).
  2. Human Protein Atlas. NRAS tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. NRAS subcellular location (ICC-IF): Mainly localized to the plasma membrane. In addition localized to the cytosol..
  4. Human Protein Atlas. NRAS antibody validation summary (4 antibodies).
  5. SP174, NRAS Q61R Mutant-Specific Antibody, Cross-Reacts With KRAS Q61R Mutant Protein in Colorectal Carcinoma. Archives of pathology & laboratory medicine 2017 — PMC7888553.
  6. NRAS Q61R immunohistochemical staining in thyroid pathology: sensitivity, specificity and utility. Histopathology 2021 — PMC8458224.
  7. SP174 Antibody Lacks Specificity for NRAS Q61R and Cross-Reacts With HRAS and KRAS Q61R Mutant Proteins in Malignant Melanoma. Applied immunohistochemistry & molecular morphology : AIMM 2018 — PMC5719500.
  8. Mutation Status and Immunohistochemical Correlation of KRAS, NRAS, and BRAF in 260 Chinese Colorectal and Gastric Cancers. Frontiers in oncology 2018 — PMC6212577.
  9. PubMed PMID:6616621 — UniProt-cited evidence.
  10. PubMed PMID:2991860 — UniProt-cited evidence.
  11. PubMed PMID:6086315 — UniProt-cited evidence.