This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section OXSM IHC around granular cytoplasmic staining (HPA tissue IHC) and the protein’s mitochondrial location (UniProt). Start the IHC-validated antibody at 2–5 μg/ml (datasheet A12866-1), using adrenal glandular cells as a high-staining reference and skeletal myocytes as a low-staining reference (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Granular cytoplasm (HPA tissue IHC); mitochondrion (UniProt) | |
| Staining pattern | Granular cytoplasmic staining across tissues (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A12866-1) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A12866-1) | |
| Caveat | Skeletal myocytes show low staining (HPA tissue IHC) | |
| Regulation | Widely expressed (UniProt) | |
| Isoform / epitope | 2 isoforms; mature chain begins at residue 28 (UniProt) |
The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet A12866-1). Published OXSM IHC protocols cover glioma (PMC12474845) and colon cancer tissue microarrays (PMC12890678).
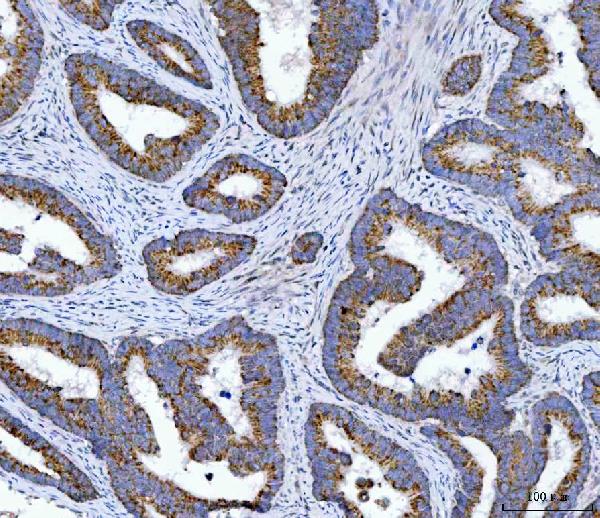
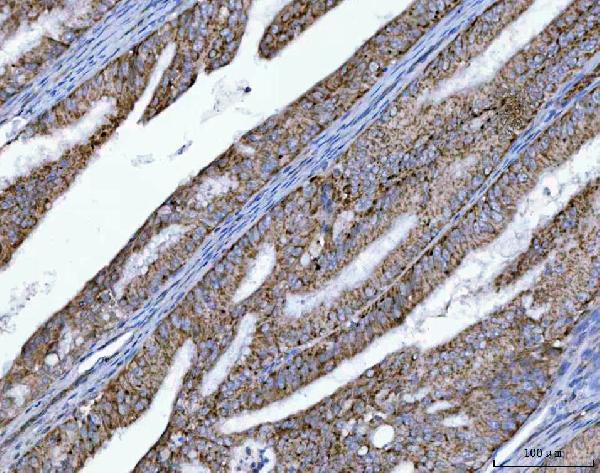
| Sample | Paraffin-embedded human Colorectal adenocarcinoma tissue; fixative not specified (datasheet A12866-1) |
| Fixation | Image fixative and duration unreported (datasheet A12866-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A12866-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A12866-1) |
| Primary antibody | Rabbit anti-OXSM, 2-5 μg/ml (datasheet A12866-1) |
| Primary incubation | Overnight at 4 °C (datasheet A12866-1) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A12866-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | OXSM-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression with a granular pattern in all tissues. No signal in the no-primary control. |
OXSM is a mitochondrial protein with no transmembrane segment (UniProt Q9NWU1 topology). In paraffin section IHC, expect granular cytoplasmic staining across many tissues, including glandular cells and cortical glial cells (HPA tissue IHC: Enhanced reliability; high staining in listed cells). HPA reports high consistency between antibody staining and RNA expression (HPA tissue IHC: Enhanced reliability).
| Granular cytoplasmic staining in colon or duodenal glandular cells. | This matches the reported high glandular staining and all-tissue granular profile (HPA tissue IHC). Assess intensity against the tissue's own cell types; broad expression means a positive result need not be confined to one gland (HPA tissue IHC: low tissue specificity). |
| Predominantly nuclear or sharply membranous staining, without a granular cytoplasmic component. | This does not fit mitochondrial localisation or the reported tissue pattern (UniProt Q9NWU1 subcellular location; HPA tissue IHC). Treat it as possible nonspecific staining or a detection artefact; review controls before scoring cells as OXSM-positive (general IHC practice). |
| Strong staining limited to smooth muscle cells, myocytes, adipocytes or marrow hematopoietic cells. | HPA reports low IHC staining in those cell groups (HPA tissue IHC). Strong isolated staining warrants a specificity check for cross-reactivity or endogenous detection activity (general IHC practice). Low HPA skeletal-muscle IHC staining should not be overridden by UniProt's higher tissue-expression statement (HPA tissue IHC; UniProt Q9NWU1 tissue specificity). |
| Uniform color across extracellular space, nuclei and cytoplasm, obscuring granules. | A field-wide haze cannot establish the reported granular cytoplasmic pattern (HPA tissue IHC). Check background with a no-primary control, then review blocking, washes and chromogen development as general IHC variables (general IHC practice). |
| No interpretable signal in colon glandular cells or cerebral-cortex glial cells. | Both are reported as high-staining cell populations (HPA tissue IHC). A negative result there calls for checking tissue quality, retrieval and detection controls before interpreting an experimental sample as OXSM-negative (general IHC practice); HPA supplies no OXSM-specific fixation-sensitivity claim. |
| Compartment and processing | OXSM is mitochondrial and lacks a transmembrane segment (UniProt Q9NWU1 topology). Its annotated chain spans residues 28–459 (UniProt Q9NWU1 processing). Use the granular cytoplasmic IHC pattern as the slide-level expectation (HPA tissue IHC); routine chromogenic IHC does not resolve individual mitochondria (general IHC practice). |
| Tissue and cell selection | HPA reports high staining in glandular cells of adrenal gland, appendix, breast, colon, duodenum and endometrium, and in cervical squamous cells and cortical glia (HPA tissue IHC). Smooth muscle cells, myocytes, adipocytes and marrow hematopoietic cells are listed as low (HPA tissue IHC). Compare the relevant cell population, rather than whole-section color (general IHC practice). |
| Antibody evidence | Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation. |
| Isoforms, modifications and retrieval | UniProt lists 2 isoforms and modified residues, including acetyllysine and succinyllysine annotations (UniProt Q9NWU1). The supplied records do not map an IHC epitope to either isoform or modification. If staining is weak, assess retrieval using assay controls (general IHC practice); no OXSM-specific retrieval or fixation effect is established here. |
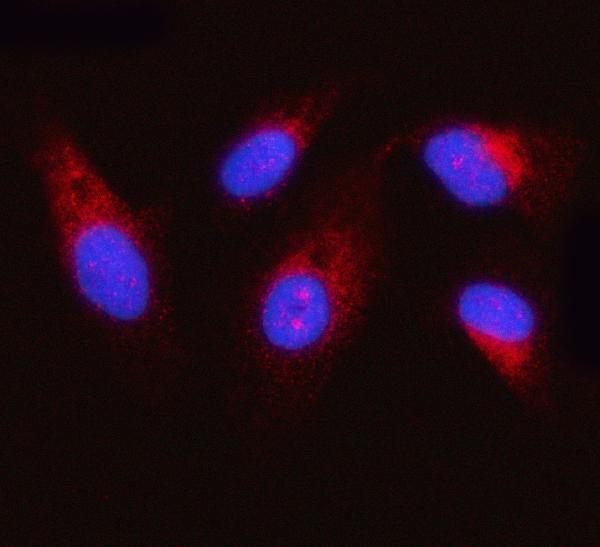
| IF/ICC Q: What localisation should a separate IF assay assess? | A: HPA reports mitochondria as supported and cytosol as uncertain, with ICC-IF images in A-431, U-251MG and U2OS (HPA subcellular). UniProt identifies mitochondria (UniProt Q9NWU1 subcellular location). This localisation evidence informs interpretation; the IF/ICC assay belongs to its own guide page. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected high-staining glandular cells show no signal. | An assay or tissue-control failure is possible; high staining is reported for several glandular populations (HPA tissue IHC). | Verify a known-positive section and detection controls, then assess retrieval and primary-antibody conditions as general IHC variables (general IHC practice). Do not infer an OXSM-specific fixation defect from this result. |
| Signal is mainly nuclear or follows the plasma membrane. | That distribution conflicts with mitochondrial localisation and granular cytoplasmic tissue staining (UniProt Q9NWU1; HPA tissue IHC). | Check a no-primary control and inspect whether the color tracks tissue edges or background; interpret compartment assignment only after those controls are acceptable (general IHC practice). |
| Strong color appears in cells HPA lists as low-staining. | The cell-type distribution may reflect cross-reactivity or endogenous detection activity (HPA tissue IHC; general IHC practice). | Compare adjacent expected-positive cells, include a no-primary control, and check endogenous enzyme blocking when using chromogenic enzyme detection (general IHC practice). |
| Diffuse color hides the granular pattern. | Background from incomplete blocking, washing or overdevelopment can obscure cellular detail (general IHC practice); it cannot confirm the HPA granular pattern (HPA tissue IHC). | Review the no-primary section, blocking and wash steps, and chromogen development time; score only cells whose cytoplasm remains interpretable (general IHC practice). |
| Skeletal-muscle myocytes stain weakly despite an expectation of abundant OXSM. | HPA lists low myocyte IHC staining, while UniProt describes higher skeletal-muscle expression (HPA tissue IHC; UniProt Q9NWU1 tissue specificity). These observations address different readouts. | Use the HPA myocyte staining level for slide interpretation and include an HPA high-staining cell population to check assay performance (HPA tissue IHC; general IHC practice). |
| The positive control stains unevenly across the section. | Uneven section handling or detection may affect apparent intensity (general IHC practice); the supplied sources provide no target-specific fixation-effect evidence. | Inspect section integrity and control uniformity, then repeat or adjust routine IHC handling if needed (general IHC practice). Avoid assigning regional loss specifically to OXSM biology without supporting evidence. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Cerebral cortex | Glial cells | High | Protein (IHC) | HPA → |
| Cervix | Squamous epithelial cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: OXSM is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot chromogenic OXSM staining in paraffin sections by checking retrieval, cellular pattern, controls and scoring before interpreting differences between samples.
A12866-1 has IHC images from human paraffin sections and an IF image from PC-3 cells (catalog image captions). Human and rat are listed as reactive species (catalog reactivity).
A12866-1 has IHC images from human paraffin sections of colorectal, endometrial, esophageal, and liver cancers (A12866-1 IHC captions). Its IF image shows PC-3 cells (A12866-1 IF caption).
Which to pick: Choose A12866-1 for paraffin-section IHC: its human tissue captions document EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody (A12866-1 IHC captions); the fixative is unreported (A12866-1 IHC captions). Choose the same SKU for IF/ICC in cells, supported by its PC-3 IF image and listed IF/ICC applications (A12866-1 IF caption; catalog applications). For rat samples, the catalog lists rat reactivity, while the supplied IHC and IF images show human tissue and PC-3 cells, respectively (catalog reactivity; A12866-1 image captions).