PAX2 / Paired box protein Pax-2 · IHC design guide

Design Immunohistochemistry for PAX2

Plan chromogenic PAX2 IHC in paraffin sections using the documented catalog antibody protocol (datasheet PB9734). Expect nuclear staining in epididymal glandular cells and compare with adrenal gland glandular cells, where staining was not detected (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PAX2 (IHC for PAX2): expected localisation Nuclear staining in epididymal glandular cells (HPA tissue IHC), antibody PB9734, validated IHC image, and IHC protocol steps
Printable PAX2 IHC protocol sheet — expected localisation Nuclear staining in epididymal glandular cells (HPA tissue IHC), antibody PB9734, controls and protocol steps. Open the full PAX2 IHC guide →

PAX2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in epididymal glandular cells (HPA tissue IHC)
Staining pattern High nuclear staining in epididymal glandular cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PB9734)
Positive control ⓘ Epididymis
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent across samples. (standard IHC practice; not target-specific)
Caveat Low staining in other tissues; medium staining–RNA consistency (HPA tissue IHC)
Regulation Expressed in primitive developmental cells (UniProt)
Isoform / epitope 4 splice isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended PAX2 IHC & IF Protocols

Start with the catalog antibody’s IHC-P protocol (datasheet: PB9734), then compare the published PAX2 staining conditions in three paraffin-section studies (PMC5621736; PMC2736318; PMC8860214).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human tonsil tissue; fixative not specified (datasheet PB9734)
FixationImage fixative and duration unreported (datasheet PB9734); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PB9734); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB9734)
Primary antibodyRabbit anti-PAX2, 0.5-1μg/ml (datasheet PB9734)
Primary incubationOvernight at 4 °C (datasheet PB9734)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet PB9734)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPAX2-positive staining in glandular cells of epididymis (HPA tissue IHC: High). HPA tissue profile: Distinct nuclear expression in epididymis. Low nuclear expression in a few other tissues. No signal in the no-primary control.
💡Decision noteTry heat-mediated EDTA pH 8.0 retrieval first for the catalog antibody (datasheet: PB9734); adjust retrieval using the published conditions if needed (PMC5621736; PMC2736318; PMC8860214).
Section 2

What Is the Expected PAX2 Staining Pattern?

PAX2 is a nuclear transcription factor with no transmembrane segment (UniProt Q02962: subcellular location, function, topology). In tissue IHC, expect the clearest staining in epididymal glandular-cell nuclei, with low nuclear expression in a few other tissues (HPA: tissue IHC). HPA rates the tissue profile Enhanced, while reporting medium consistency between antibody staining and RNA expression (HPA: reliability).

What am I looking at on my slide?
Distinct nuclear staining in epididymal glandular cells, with little staining outside their nuclei (HPA: High in epididymal glandular cells; nuclear profile).This matches the strongest supplied tissue result and PAX2's nuclear location (HPA: tissue IHC; UniProt Q02962: nucleus). Judge the signal by cell type and compartment together, rather than by stain intensity alone.
Predominantly cytoplasmic or membranous staining, especially where the nuclei remain unstained.Treat this as a localization mismatch needing investigation: PAX2 is nuclear and has no transmembrane segment (UniProt Q02962: location, topology). Check the section and controls before interpreting it as PAX2.
Strong signal in cells listed as not detected, such as adipocytes in adipose tissue (HPA: Not detected in adipocytes).That pattern conflicts with the supplied tissue profile (HPA: tissue IHC). Consider antibody cross-reactivity or endogenous chromogenic activity; compare with a no-primary control and the known-positive tissue on the same run (standard IHC practice).
Diffuse color across tissue, including extracellular areas and cells without a defined nuclear pattern.Diffuse deposition does not reproduce the distinct nuclear profile (HPA: tissue IHC). Review blocking, washing, detection background, and counterstain; a colored section alone does not establish cell-specific PAX2 staining (standard IHC practice).
No nuclear signal in epididymal glandular cells, even though tissue structure is preserved (HPA: High in epididymal glandular cells).The expected positive result is missing (HPA: tissue IHC). Check the antibody and detection controls, then review the run's retrieval and staining conditions (standard IHC practice); HPA provides no PAX2-specific fixation-sensitivity claim.
💡Expected PAX2 appearanceA convincing positive is distinct, strong nuclear staining in epididymal glandular cells (HPA: High; nuclear profile); isolated cytoplasmic color or broad staining of HPA-negative cells is suspect (UniProt Q02962: nucleus; HPA: tissue IHC).
How each factor affects the staining
Tissue and cell selectionEpididymal glandular cells provide the clearest supplied positive reference (HPA: High); kidney proximal tubules are listed as Low (HPA: tissue IHC). A faint kidney result therefore has less power to establish that an IHC run worked.
Subcellular location and topologyPAX2 is nuclear and has no transmembrane segment (UniProt Q02962: location, topology). Score staining within identified nuclei; membrane staining has no support as the expected PAX2 pattern in this record.
Antibody validation and tissue-profile limitsThree listed antibodies have Enhanced IHC status (HPA: HPA047704, HPA070751, CAB013024). The tissue profile still reports medium agreement with RNA (HPA: reliability); assess discordant cells against morphology and controls.
Isoforms and processingUniProt lists four PAX2 isoforms, one chain spanning residues 1–417, and no signal peptide or propeptide (UniProt Q02962: isoforms, processing). These entries alone do not predict antibody epitope coverage or a distinct IHC pattern.
IF/ICC Q&A: where should a verified signal appear?In the nucleoplasm (HPA: supported ICC-IF location), consistent with the nuclear assignment (UniProt Q02962: location). This localization answers the IF/ICC interpretation question; its workflow belongs to the separate IF/ICC guide.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The positive reference lacks nuclear stain in epididymal glandular cells (HPA: High).A failed detection step, unsuitable antibody conditions, or a staining-run problem is possible (standard IHC practice); this record does not identify a PAX2-specific fixation effect.Confirm tissue identity and inspect a same-run positive control, then review detection reagents and the antibody's IHC-P instructions (standard IHC practice).
Only weak signal appears in kidney proximal tubules.Low protein staining is reported there (HPA: Low in kidney proximal tubules), so faint nuclear color may fit the supplied profile.Compare nuclear localization and background with the epididymal reference (HPA: nuclear profile; High in epididymal glandular cells); avoid calling the run failed from kidney alone.
Cytoplasmic staining dominates while nuclei are pale.The compartment conflicts with PAX2's nuclear assignment (UniProt Q02962: subcellular location). Nonspecific antibody or detection signal is possible (standard IHC practice).Recheck morphology and counterstain, inspect the no-primary control, and score only convincing nuclear staining (standard IHC practice).
Strong color appears in adipocytes from adipose tissue.HPA reports PAX2 as not detected in these cells (HPA: adipose tissue). Cross-reactivity or endogenous detection activity may explain the color (standard IHC practice).Run a no-primary control and check blocking and detection background before assigning the signal to PAX2 (standard IHC practice).
The whole section has diffuse chromogen deposition.Background from the staining or detection workflow may obscure the distinct nuclear pattern (HPA: tissue IHC; standard IHC practice).Inspect the no-primary control and review blocking, washes, reagent handling, and counterstain (standard IHC practice); reassess cell-specific nuclear signal after background is resolved.
Two antibodies give different apparent cell distributions.The HPA tissue profile has medium consistency with RNA despite Enhanced IHC reliability (HPA: reliability), so a discordant distribution needs independent scrutiny.Compare the same tissue regions, nuclear localization, and controls; use the supplied HPA tissue pattern as a reference, without treating either antibody's color alone as proof (HPA: tissue IHC; standard IHC practice).

Sample controls for PAX2 IHC & IF

🧪Run epididymis first: glandular cells should show PAX2 staining (HPA: High in epididymal glandular cells). Use adrenal glandular cells as a negative tissue control (HPA: Not detected in adrenal glandular cells); on the epididymis slide, assess nonglandular cells for background rather than assuming they are PAX2-negative (HPA: positive designation applies to glandular cells).
Positive control tissue: Epididymis (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PAX2 in EFO-21, RPTEC/TERT1, SiHa, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) slide, a rabbit host- and clonality-matched isotype control, and PAX2-knockout material as a biological negative (caption: rabbit primary antibody; standard IHC controls). With the caption’s biotin-based DAB detection, check endogenous peroxidase and biotin background in the positive tissue (caption: biotinylated secondary, SABC and DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected PB9734 tissue-IHC caption does not state the fixative (caption: paraffin section; fixative unreported). Heat retrieval in EDTA at pH 8.0 was used in the selected example, but a requirement for that retrieval condition has not been established (caption: EDTA retrieval, pH 8.0). No supplied evidence shows frozen sections or IF to be easier, or documents an epididymis-specific artefact (supplied HPA and caption evidence); assess nuclear localization when scoring (UniProt Q02962: nucleus).

HPA tissue IHC evidence for PAX2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Epididymis Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced PAX2 IHC Tips

Troubleshoot PAX2 staining by checking retrieval, nuclear localisation, tissue controls and cell specific scoring before interpreting a chromogenic signal.

How should I troubleshoot weak nuclear PAX2 staining after antigen retrieval?
Start with heat mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet PB9734). The selected antibody stained a paraffin embedded human tonsil section after this retrieval, with 1 μg/ml primary antibody incubated overnight at 4°C (caption PB9734). Compare sections retrieved in the same run with a positive tissue control, and check whether the control retains nuclear staining before changing primary antibody concentration (HPA: high nuclear staining in epididymal glandular cells; standard IHC practice). If staining remains weak, adjust heating and cooling within the retrieval equipment’s validated settings, then compare signal with tissue integrity and background on matched sections (standard IHC practice).
Could fixation explain variable PAX2 staining across my paraffin sections?
Target specific sensitivity of PAX2 staining to fixation is unknown from the supplied evidence; the selected paraffin tissue caption does not state a fixative (caption PB9734). Record the fixative, fixation duration, tissue thickness and processing history for each specimen before comparing staining intensity (standard IHC practice). Run similarly processed positive controls alongside study sections so a failed nuclear signal can be distinguished from a specimen level difference (HPA: high nuclear staining in epididymal glandular cells; standard IHC practice). When fixation histories differ, interpret intensity cautiously and compare matched batches, because fixation and processing can alter epitope access in paraffin section IHC (standard IHC practice).
Where should convincing PAX2 signal appear in a chromogenic IHC section?
Expect a predominantly nuclear signal: PAX2 is annotated in the nucleus, and tissue IHC shows distinct nuclear expression in epididymis (UniProt Q02962: nucleus; HPA: tissue IHC profile). Score staining within identifiable nuclei rather than counting diffuse cytoplasmic pigment as positive PAX2 (HPA: nuclear staining; standard IHC practice). Epididymal glandular cells provide a supported high expression comparator, whereas kidney proximal tubules are reported at low expression and may be harder to assess (HPA: epididymis high; HPA: kidney proximal tubules low). Compare nuclear and surrounding cytoplasmic colour on the same section, and inspect a no primary control if pigment obscures compartment assignment (standard IHC practice).
Can this antibody distinguish PAX2 isoforms or a modified epitope in tissue?
PAX2 has 4 annotated isoforms and a reported phosphothreonine at residue 226 (UniProt Q02962: isoforms and modified residues). The supplied antibody caption gives staining conditions but no epitope sequence or isoform reactivity, so tissue staining cannot be assigned to one isoform or phosphorylation state (caption PB9734). For discrepant specimens, request epitope and isoform validation data before claiming selective detection, and keep scoring tied to nuclear staining in the expected cells (UniProt Q02962: isoforms; HPA: tissue IHC profile; standard IHC practice). Compare serial sections with appropriate controls, since retrieval and processing can change epitope accessibility in chromogenic IHC (standard IHC practice).
How should I adapt a PAX2 localisation check for multiplex immunofluorescence?
For a secondary IF check, assess whether PAX2 signal occupies nuclei, consistent with its supported nucleoplasmic localisation (HPA: subcellular localisation). Multiplex with a marker identifying the expected cell population, and confirm that both signals can be assigned to the same cells rather than adjacent structures (HPA: high staining in epididymal glandular cells; standard IF practice). Choose a fluorophore channel after inspecting unstained tissue autofluorescence, and include single stain controls to check channel bleed through (standard IF practice). Because PAX2 is nuclear and has no annotated transmembrane segment, permeabilise sufficiently for nuclear antibody access while preserving morphology; the antibody epitope itself is unspecified (UniProt Q02962: nucleus and topology; standard IF practice).
What should I check when DAB obscures nuclear PAX2 staining?
First compare the stained section with a no primary control to identify signal from detection reagents or tissue pigment (standard IHC practice). The selected protocol uses a biotinylated secondary antibody, a streptavidin biotin complex and DAB, so inspect reagent dependent background when using that detection sequence (caption PB9734; standard IHC practice). Apply the routine peroxidase block, check the effectiveness of protein blocking, and assess whether DAB development has obscured nuclear borders (standard IHC practice). The caption reports 10% goat serum blocking and 1 μg/ml primary antibody; use these as documented starting conditions while comparing background and nuclear signal on matched sections (caption PB9734).
How can I quantify PAX2 staining across sections with different cell composition? ⚠ ANSWER MARKED FOR VERIFICATION
Define the anatomical region and eligible cell population before scoring, then record the percentage of nuclei with convincing chromogenic signal (HPA: nuclear tissue staining; standard IHC practice). If intensity is reproducible across matched batches, calculate a nuclear H-score from the proportions of cells at each staining intensity and report the scoring scale (standard IHC practice). Normalise positive counts to the number of eligible nuclei, or report positive cell density per mm² of assessed tissue with the sampled area stated (standard IHC practice). Keep glandular and other cell populations separate when comparing specimens, because PAX2 tissue expression varies by cell type (HPA: tissue IHC profile; standard IHC practice).
How do I distinguish true PAX2 staining from artefact in paraffin IHC?
Give greatest weight to crisp nuclear staining in an expected cell population, such as epididymal glandular cells, alongside a satisfactory positive control (HPA: high nuclear staining in epididymal glandular cells; standard IHC practice). Treat predominantly cytoplasmic colour cautiously because PAX2 is a nuclear protein and HPA supports nucleoplasmic localisation (UniProt Q02962: nucleus; HPA: subcellular localisation). Examine section edges, necrotic areas and the no primary control for staining that follows tissue damage or persists without primary antibody (standard IHC practice). Check endogenous enzyme background when interpreting DAB colour, and avoid calling a specimen negative solely from weak staining in a tissue reported to have low PAX2 expression (standard IHC practice; HPA: low staining in kidney proximal tubules).
Boster reagents

Best PAX2 / Paired box protein Pax-2 IHC Antibodies

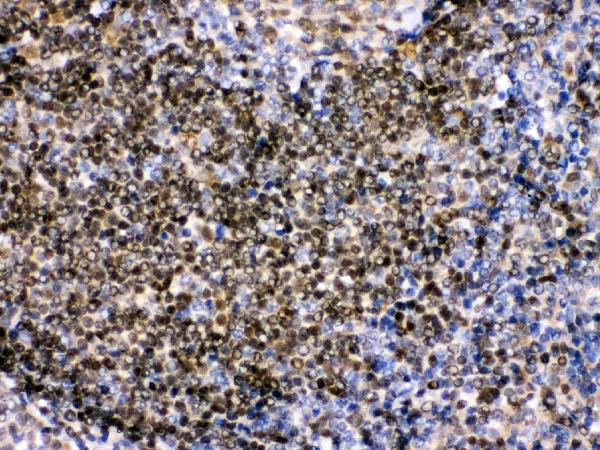
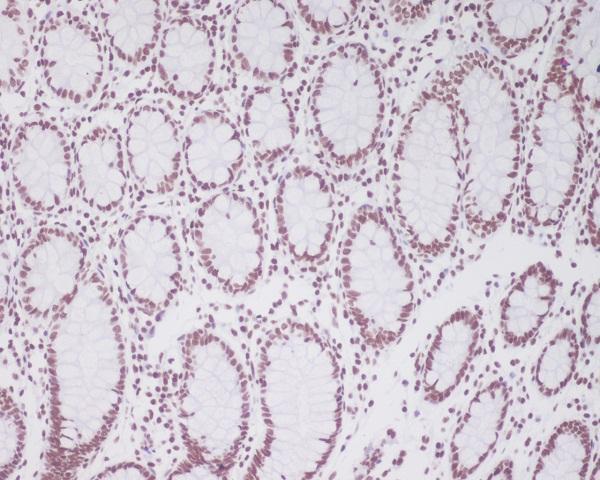
Two anti-PAX2 antibodies have paraffin-section IHC images: PB9734 in human tonsil and M01288-1 in human colon (PB9734 and M01288-1 image captions).

Real IHC data IHC analysis of Pax2 using anti-Pax2 antibody (PB9734). Pax2 was detected in a paraffin-embedded section of human tonsil tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1 μg/ml rabbit anti-Pax2 Antibody (PB9734) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-Pax2 Antibody ®
Cat # PB9734
Real IHC data Immunohistochemical analysis of paraffin-embedded human colon using Pax2 Antibody.
Anti-Pax2 Rabbit Monoclonal Antibody
Cat # M01288-1

PB9734 has an IHC image from a paraffin-embedded human tonsil section and lists human, mouse and rat reactivity (PB9734 image caption; catalog reactivity). M01288-1 has an IHC image from paraffin-embedded human colon and lists human and mouse reactivity (M01288-1 image caption; catalog reactivity).

Which to pick: For tissue IHC, PB9734 provides a documented human tonsil procedure with EDTA retrieval and 1 μg/ml primary antibody, while M01288-1 is a rabbit monoclonal with a human colon IHC image (PB9734 image caption; M01288-1 image caption; catalog clone). Choose PB9734 for broader listed species coverage, including rat; M01288-1 lists human and mouse (catalog reactivity). Neither SKU lists IF/ICC, so there is no IF/ICC pick from these cards; both captions describe paraffin sections, but neither reports the fixative (catalog applications; PB9734 and M01288-1 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q02962 (PAX2_HUMAN, Paired box protein Pax-2).
  2. Human Protein Atlas. PAX2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. PAX2 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. PAX2 antibody validation summary (3 antibodies).
  5. Rapamycin-mediated suppression of renal cyst expansion in del34 Pkd1-/- mutant mouse embryos: an investigation of the feasibility of renal cyst prevention in the foetus. Nephrology (Carlton, Vic.) 2012 — PMC5621736.
  6. PAX2 expression in low malignant potential ovarian tumors and low-grade ovarian serous carcinomas. Modern pathology : an official journal of the United States and Canadian Academy of Pathology, Inc 2009 — PMC2736318.
  7. PAX2 loss by immunohistochemistry occurs early and often in endometrial hyperplasia. International journal of gynecological pathology : official journal of the International Society of Gynecological Pathologists 2012 — PMC4646427.
  8. Reliable Identification of Endometrial Precancers Through Combined Pax2, β-Catenin, and Pten Immunohistochemistry. The American journal of surgical pathology 2022 — PMC8860214.
  9. PubMed PMID:1378753 — UniProt-cited evidence.
  10. PubMed PMID:7819127 — UniProt-cited evidence.
  11. PubMed PMID:8661132 — UniProt-cited evidence.