This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
This paraffin-section IHC guide covers PPP1R14D’s expected cytoplasmic location (UniProt) and reported glandular-cell staining in colon, rectum and small intestine (HPA tissue IHC). It gives the catalog antibody’s IHC dilution of 1:100–1:300 (datasheet A14433) and flags the uncertain specificity of the tissue staining (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue staining; reliability uncertain (HPA tissue IHC) | |
| Staining pattern | Glandular-cell cytoplasm in gastrointestinal tissues (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A14433) | |
| Positive control | Colon+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep paraffin-section fixation consistent. (standard IHC practice; not target-specific) | |
| Caveat | Presumed off-target binding; staining needs verification (HPA tissue IHC) | |
| Regulation | Expression regulation not established (UniProt) | |
| Isoform / epitope | No annotated isoforms; one 1–145 chain (UniProt) |
The catalog antibody’s IHC-P protocol and one published PPP1R14D tissue IHC protocol are available for comparison (datasheet A14433; PMC9635868).
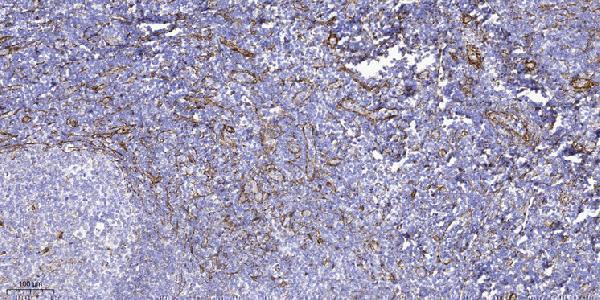
| Sample | Paraffin-embedded human tonsil tissue; fixative not specified (datasheet A14433) |
| Fixation | Image fixative and duration unreported (datasheet A14433); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A14433); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-PPP1R14D, 1:100-1:300 (datasheet A14433) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PPP1R14D-positive staining in glandular cells of colon (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissues, including the gastrointestinal tract. No signal in the no-primary control. |
PPP1R14D is annotated as cytoplasmic and has no transmembrane segment (UniProt Q9NXH3: subcellular location and topology). In paraffin-section IHC, the strongest reported staining is in glandular cells of the colon, rectum and small intestine (HPA: High). Interpret this pattern cautiously: HPA rates tissue IHC reliability as Uncertain because presumed off-target binding was observed and disregarded, pending external verification (HPA: reliability description).
| Cytoplasmic staining in gastrointestinal glandular cells. | This matches the annotated compartment (UniProt Q9NXH3: Cytoplasm) and HPA's reported High staining in colon, rectum and small-intestine glandular cells (HPA: tissue IHC). It is a pattern match, not independent proof of antibody specificity (HPA: Uncertain reliability). |
| Predominantly nuclear or sharply membrane-restricted staining. | This conflicts with the cytoplasmic annotation and lack of a transmembrane segment (UniProt Q9NXH3: location and topology). Check controls and repeatability before calling it PPP1R14D; HPA's uncertain IHC validation increases the need for caution (HPA: reliability). |
| Strong staining in a cell type reported as not detected. | For example, HPA reports adipocytes in adipose tissue and bronchial respiratory epithelial cells as Not detected (HPA: tissue IHC). Unexpected staining may reflect cross-reactivity or endogenous chromogen-generating activity; compare matched controls before assigning a cause. |
| Diffuse staining across cells and extracellular areas. | A widespread haze does not fit HPA's cell-associated cytoplasmic profile (HPA: tissue IHC). In general IHC practice, assess nonspecific reagent binding, incomplete washing and endogenous detection activity with appropriate controls. |
| No stain in an expected positive section. | Colon, rectum and small-intestine glandular cells are reported High (HPA: tissue IHC). A blank section warrants a check of section quality, retrieval, antibody conditions and detection controls; HPA's Uncertain rating means the reported pattern is a provisional benchmark (HPA: reliability). |
| Tissue and cell selection | Colon, rectum and small-intestine glandular cells have High reported staining; appendix, duodenum and gallbladder glandular cells, and kidney tubular cells, have Medium staining (HPA: tissue IHC). Choose comparisons at the cell level. |
| Low and undetected comparators | Stomach glandular cells and smooth-muscle cells are Low, while adipocytes in adipose tissue are Not detected (HPA: tissue IHC). These labels describe observed IHC signal, not an absolute protein absence or a validated specificity test. |
| Antibody evidence | The listed antibody HPA041846 is rated Uncertain for IHC; HPA reports presumed off-target binding and pending external verification (HPA: antibody IHC status and reliability description). Treat even plausible positive staining as provisional. |
| Compartment and topology | A cytoplasmic pattern is consistent with UniProt's location annotation; no transmembrane segment is annotated (UniProt Q9NXH3: location and topology). A crisp membrane-only pattern lacks support from this record. |
| Protein state | PPP1R14D inhibits PPP1CA only when phosphorylated, and Thr58 is annotated as a phosphothreonine site (UniProt Q9NXH3: function and modified residues). The payload gives no antibody epitope or phospho-specificity, so staining cannot establish phosphorylation state. |
| Processing and isoforms | UniProt lists one 1–145 chain, no signal peptide or propeptide, and no annotated isoforms (UniProt Q9NXH3: processing and isoforms). Do not assign a separate staining compartment or cell pattern to an unreported processed form. |
| IF/ICC Q&A | Can IF/ICC confirm the compartment here? HPA provides no main ICC-IF location or cell-line images, and the listed antibody has no ICC validation entry (HPA: subcellular and antibody records). This section therefore offers no IF/ICC protocol or image-based confirmation. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected gastrointestinal glandular cells are blank. | A technical failure is possible; HPA reports these cells as High but rates tissue IHC Uncertain (HPA: tissue IHC and reliability). | In general IHC practice, check tissue integrity, retrieval, primary-antibody setup and detection reagents with a known working control; repeat before interpreting a negative result. |
| Only nuclei stain strongly. | The observed compartment conflicts with UniProt's cytoplasmic annotation (UniProt Q9NXH3: subcellular location). Nonspecific staining or interpretation error is possible. | Compare a primary-omission control and cell morphology, then repeat under adjusted general IHC blocking and washing conditions; avoid scoring nuclei as a supported PPP1R14D pattern. |
| A crisp cell-surface rim dominates. | UniProt annotates no transmembrane segment and places PPP1R14D in the cytoplasm (UniProt Q9NXH3: topology and location). | Recheck the section's compartment boundaries and staining controls. Require independent specificity evidence before assigning a membrane-localized result to PPP1R14D. |
| Unexpected cells stain as strongly as the positive comparator. | Cross-reactivity is plausible because presumed off-target binding was observed (HPA: Uncertain reliability); endogenous chromogenic activity is another general IHC possibility. | Compare a matched primary-omission control and, where applicable, an endogenous-enzyme control; document the precise cell type rather than treating all tissue staining as equivalent. |
| The whole section has a brown haze. | Diffuse background can arise from general IHC issues such as nonspecific binding, insufficient washing or endogenous detection activity; HPA describes a cytoplasmic cellular profile (HPA: tissue IHC). | Use a matched negative control, review blocking and wash steps, and inspect signal at the cell level before scoring intensity. |
| Smooth muscle stains weakly despite the annotated role in contraction. | UniProt describes a phosphorylation-dependent function, while HPA reports Low staining in smooth-muscle cells (UniProt Q9NXH3: function; HPA: tissue IHC). Function does not predict strong IHC signal. | Score the observed cells against the HPA tissue pattern and controls; do not increase exposure or development solely to force a strong smooth-muscle result. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Presumed off target binding observed and disregarded. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Rectum | Glandular cells | High | Protein (IHC) | HPA → |
| Small intestine | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot PPP1R14D staining in paraffin section IHC using the catalog image, protein record, and tissue patterns as distinct lines of evidence.
A14433 has IHC data from paraffin-embedded human tonsil (IHC image caption); its listed reactivity covers human, mouse and rat, and IF is listed without an IF image (catalog).
A14433 will render with an IHC image of paraffin-embedded human tonsil (IHC image caption). Its listed applications include IHC and IF, and its listed reactivity includes human, mouse and rat (catalog).
Which to pick: For tissue IHC, choose A14433: its own image shows paraffin-embedded human tonsil with Tris-EDTA retrieval at pH 9.0 and primary antibody at 1:200 (IHC image caption); the fixative is unreported (IHC image caption). For IF, A14433 is listed at 1:50, but no IF image is supplied, and ICC is not listed (catalog). A14433 is polyclonal and lists mouse and rat reactivity alongside human; the supplied IHC image documents human tissue only (catalog; IHC image caption).