This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan PTK7 chromogenic IHC in paraffin sections using cytoplasmic tissue staining as the reference pattern (HPA tissue IHC). Endometrial stromal cells show high staining, while adipocytes are not detected (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue signal (HPA tissue IHC); membrane and junctional location (UniProt) | |
| Staining pattern | Cytoplasmic staining in several tissues, high in endometrial stroma (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Endometrium+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | A secreted variant may complicate tissue RNA–protein agreement (HPA tissue IHC) | |
| Regulation | Expression varies by tissue (HPA tissue IHC) | |
| Isoform / epitope | 6 isoforms; map the epitope to the extracellular or cytoplasmic region (UniProt) |
The catalog antibody IHC-P protocol is followed by 3 published PTK7 IHC workflows for breast, lung, and pancreatic tissue (PMC11430626; PMC4084668; PMC10323888).
| Sample | Paraffin-embedded tissue sections; fixative not specified (datasheet A02957; sample unspecified) |
| Fixation | Image fixative and duration unreported (datasheet A02957); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Mouse monoclonal (clone 4F9) anti-PTK7, 1:200-1:1000 (datasheet A02957) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PTK7-positive staining in cells in endometrial stroma of endometrium (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissues. No signal in the no-primary control. |
PTK7 is a transmembrane protein with an extracellular region and cytoplasmic tail (UniProt Q13308 topology). Expect staining at cell borders, with possible cytoplasmic staining: HPA reports cytoplasmic expression across several tissues and rates its tissue IHC profile Approved despite low agreement with RNA data (HPA tissue IHC). The strongest listed signal is in endometrial stromal cells; several epithelial and neuronal cell types show medium staining (HPA tissue IHC).
| Cell-border staining in endometrial stromal cells, with possible cytoplasmic signal. | This fits PTK7 membrane localization (UniProt Q13308 subcellular location) and HPA's High endometrial stromal IHC signal and broader cytoplasmic profile (HPA tissue IHC). Assess the stained cells and compartment together; border staining alone does not establish antibody specificity. |
| A strong nuclear-only pattern, without convincing cell-border or cytoplasmic staining. | Nuclear-only staining does not match the reported cell membrane and cell-junction localization (UniProt Q13308 subcellular location) or HPA's cytoplasmic tissue profile (HPA tissue IHC). Treat it as a possible artefact and check controls and detection conditions before scoring it as PTK7. |
| Strong staining in adipocytes or cardiomyocytes. | HPA lists PTK7 as Not detected in adipocytes and cardiomyocytes (HPA tissue IHC). Check whether the signal tracks those cells or tissue edges and whether a no-primary control also stains. Cross-reactivity or endogenous detection activity is plausible, but the slide alone cannot distinguish them. |
| Diffuse color across cells, stroma, and blank areas, obscuring cell borders. | That distribution is difficult to reconcile with a cell-associated PTK7 call (UniProt Q13308 subcellular location; HPA tissue IHC). In chromogenic IHC, background can arise from detection reagents or insufficient blocking or washing (general IHC practice). Compare a no-primary control and judge signal only where cell identity remains clear. |
| No convincing staining in an endometrial stromal positive-control section. | HPA reports High staining in endometrial stromal cells (HPA tissue IHC), so absence warrants a technical check. Confirm that the expected cells are present, then review antibody dilution, retrieval and detection controls (general IHC practice). An HPA tissue pattern does not guarantee every specimen will stain. |
| Membrane topology and observed tissue compartment | PTK7 has an extracellular region at residues 31–704, a transmembrane segment at 705–725, and a cytoplasmic region at 726–1070 (UniProt Q13308 topology). HPA describes tissue IHC staining as cytoplasmic (HPA tissue IHC). Score visible compartment and cell type; do not require a perfect membrane outline in every positive cell. |
| Cell and tissue selection | HPA lists endometrial stromal cells as High; breast glandular, bronchial respiratory epithelial, and kidney tubular cells as Medium (HPA tissue IHC). Use a listed cell population to assess a positive control. HPA reports adipocytes and cardiomyocytes as Not detected, useful context for interpreting unexpected staining (HPA tissue IHC). |
| Variant and validation limits | UniProt lists 6 PTK7 isoforms (UniProt Q13308 isoforms). HPA notes that at least one protein variant is secreted and that RNA and protein locations may differ (HPA tissue IHC reliability description). HPA rates the tissue profile Approved with low RNA–staining consistency and lists HPA003222 IHC as Approved (HPA tissue IHC; HPA antibodies). Interpret discordance cautiously. |
| IF/ICC Q: What localization is expected? | A: HPA reports mainly plasma membrane and cytosol, with additional vesicles; its plasma-membrane assignment is Supported, cytosol Uncertain, and vesicles Approved (HPA subcellular ICC-IF). UniProt also places PTK7 at cell junctions and the leading edge of migrating cells (UniProt Q13308 subcellular location). These IF observations are context, not an IHC staining requirement. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected endometrial stromal signal is absent. | The expected cells may be missing, or the IHC workflow may have failed; HPA lists these cells as High (HPA tissue IHC). | Verify stromal cells on the section. Check the IHC-validated antibody's specified dilution and retrieval procedure, then confirm detection with an appropriate positive control (general IHC practice). |
| Only nuclei appear positive. | This conflicts with PTK7 cell membrane and junction localization and HPA's cytoplasmic tissue profile (UniProt Q13308 subcellular location; HPA tissue IHC). | Review the no-primary control and staining distribution. Reassess antigen retrieval and detection conditions using the antibody's IHC procedure before assigning a PTK7 score (general IHC practice). |
| Adipocytes or cardiomyocytes stain strongly. | HPA lists these cells as Not detected; unexpected signal may reflect cross-reactivity or endogenous detection activity (HPA tissue IHC; general IHC practice). | Compare a no-primary control and inspect the cell identity. If background persists, review blocking and the detection system; if only the primary-stained slide is positive, reconsider antibody specificity (general IHC practice). |
| Diffuse chromogen obscures cell boundaries. | Nonspecific background can obscure a cell-associated pattern (general IHC practice); PTK7 is reported at the membrane and junctions, while HPA also observes cytoplasmic tissue staining (UniProt Q13308 subcellular location; HPA tissue IHC). | Inspect no-primary and positive-control sections. Review blocking, washing, primary dilution and detection development according to the IHC workflow (general IHC practice). |
| Cytoplasmic staining is present, but membrane outlines are faint. | HPA's tissue IHC profile is cytoplasmic, while UniProt assigns PTK7 to the membrane (HPA tissue IHC; UniProt Q13308 subcellular location). | Record the observed compartment and cell type. Compare a listed positive tissue and controls before judging the result; do not reject cytoplasmic staining solely because borders are faint (HPA tissue IHC; general IHC interpretation). |
| Protein staining disagrees with RNA abundance. | HPA reports low staining–RNA consistency and says a secreted protein variant can complicate agreement between RNA and protein location (HPA tissue IHC reliability description). | Score the observed IHC pattern and document the mismatch. Check antibody controls and tissue cell composition; avoid treating RNA abundance alone as proof of a positive or negative IHC result (HPA tissue IHC; general IHC interpretation). |
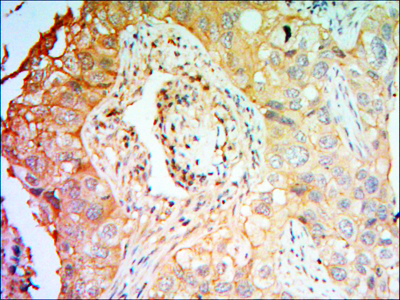
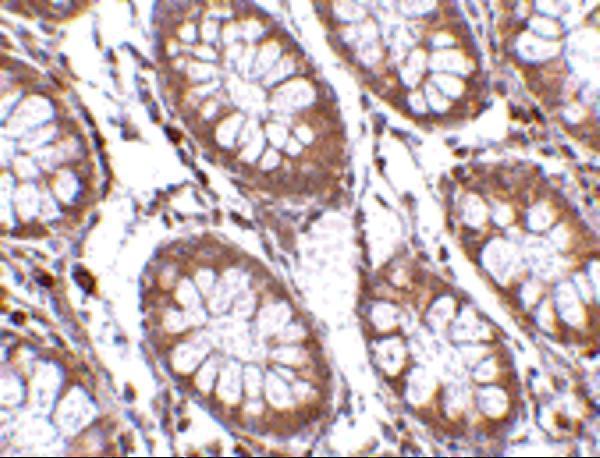
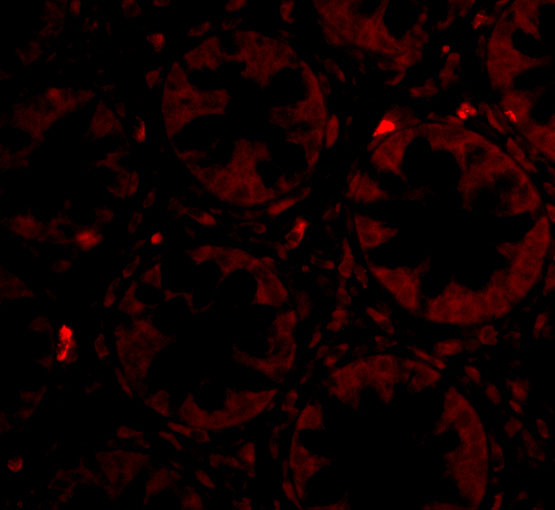

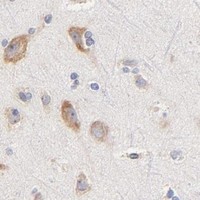
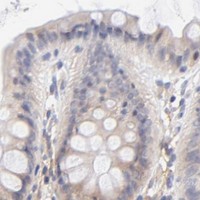
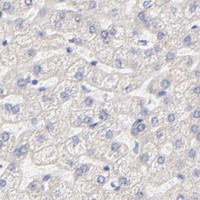


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Endometrium | Cells in endometrial stroma | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Medium | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Not detected | Protein (IHC) | HPA → |
| Parathyroid gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
These questions address PTK7 staining in paraffin sections with chromogenic detection; the IF question covers a separate assay.
The catalog shows PTK7 IHC images from human lung cancer, colon tissue, and cancer tissue, plus an IF image from human colon cells (catalog image captions).
A02957 shows IHC in human lung cancer paraffin sections; IF is listed for human samples, but no IF image is supplied (catalog image caption; catalog applications/reactivity). A02957-1 shows IHC in human colon tissue and IF in human colon cells; A02957-2 shows IHC in formalin-fixed, paraffin-embedded human breast carcinoma and hepatocarcinoma (catalog image captions).
Which to pick: For tissue IHC, choose A02957-2 when documented paraffin-section paraffin-embedded examples matter (catalog image caption); A02957 shows paraffin-section IHC, but its caption does not report the fixative (catalog image caption). For IF/ICC, choose A02957-1 because its catalog includes IF and shows staining in human colon cells (catalog applications and IF image caption). A02957-1 is also the cross-species candidate because its stated reactivity includes human, mouse, and rat, though its supplied IHC image shows human colon tissue only and does not report the fixative (catalog reactivity and IHC image caption). The selected A02957 tissue-IHC caption documents paraffin sections, but does not specify the fixative (selected-SKU IHC image A02957).