This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic RFX1 IHC around nuclear staining and a 2–5 μg/mL antibody starting range (HPA tissue IHC; datasheet A04392-1). Use colon glandular cells as a positive reference and adipocytes as an undetected comparator (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear staining in most tissues (HPA tissue IHC) | |
| Staining pattern | Nuclear signal in most tissues, including glandular cells (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A04392-1) | |
| Positive control | Colon+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Staining and RNA expression show low consistency (HPA tissue IHC) | |
| Regulation | Regulation not annotated (UniProt) | |
| Isoform / epitope | No isoforms or alternate processing annotated (UniProt) |
The catalog antibody IHC-P protocol is accompanied by published RFX1 protocols for esophageal, liver, and colorectal specimens (PMC3174211; PMC11996997; PMC12712669).
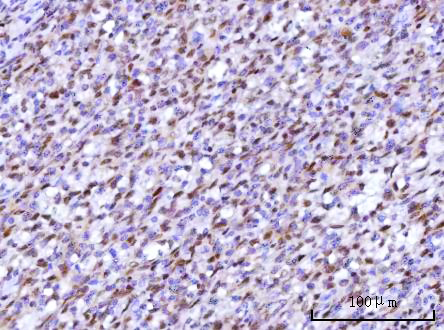
| Sample | Paraffin-embedded Diffuse large B-cell lymphoma of human intestine tissue; fixative not specified (datasheet A04392-1) |
| Fixation | Image fixative and duration unreported (datasheet A04392-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A04392-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A04392-1) |
| Primary antibody | Rabbit anti-RFX1, 2-5 μg/ml (datasheet A04392-1) |
| Primary incubation | Overnight at 4 °C (datasheet A04392-1) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A04392-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
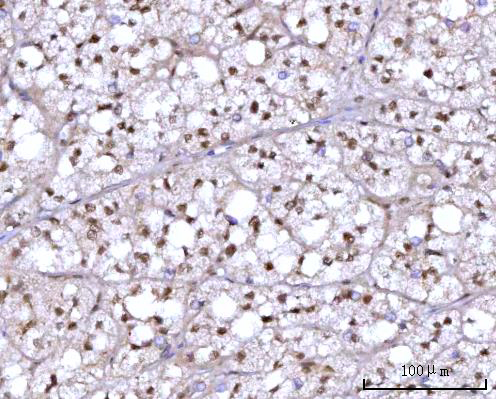
| Expected result | RFX1-positive staining in glandular cells of colon (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in most tissues. No signal in the no-primary control. |
RFX1 is a nuclear, DNA-binding protein with no transmembrane segment (UniProt P22670: subcellular location, function, topology). In paraffin-section IHC, expect nuclear staining in many tissues, especially colon, rectum, and stomach glandular cells and kidney tubular cells (HPA: nuclear expression in most tissues; High in these cells). HPA rates its tissue IHC profile Approved but reports low consistency between antibody staining and RNA expression (HPA: reliability description).
| Distinct nuclear staining in colon, rectum, or stomach glandular cells, or kidney tubular cells. | This matches the reported High cell-specific staining and nuclear tissue profile (HPA: tissue IHC). Assess the named cells against nearby nuclei and background; a positive tissue section establishes that the run can detect the expected pattern, but does not by itself establish antibody specificity (HPA: IHC Approved). |
| Predominantly cytoplasmic, membranous, or broadly extracellular chromogen. | A dominant signal outside nuclei conflicts with RFX1's nuclear location and lack of a transmembrane segment (UniProt P22670: subcellular location, topology). Treat it as suspect until nuclear staining appears in an HPA High cell population and the pattern is checked against a no-primary control (HPA: tissue IHC; general IHC practice). |
| Strong staining in adipocytes, prostate glandular cells, or smooth muscle cells. | These specific cell populations are reported as Not detected in HPA tissue IHC. Unexpected staining raises possible cross-reactivity or endogenous detection activity; compare the cell identity, distribution, and no-primary control before assigning it to RFX1 (HPA: tissue IHC; general IHC practice). |
| Weak haze across nuclei and surrounding tissue, without a clear cell-specific pattern. | Diffuse background cannot be scored as the reported nuclear expression in most tissues (HPA: tissue IHC). Review background in the no-primary control and reassess blocking, washing, antibody concentration, and detection exposure as general chromogenic IHC checks; none establishes an RFX1-specific cause (general IHC practice). |
| No nuclear signal in colon glandular cells or kidney tubular cells. | This misses two HPA High reference populations and makes a negative test section difficult to interpret (HPA: tissue IHC). First confirm the expected cells are present, then check the IHC-P run and controls; absence alone cannot distinguish a technical failure from biological variation (general IHC practice). |
| Reference tissue and cell identity | Use the named cell populations, rather than an entire organ, to judge the pattern: HPA reports High staining in colon, rectum, and stomach glandular cells and kidney tubular cells, but Not detected in several other cell populations (HPA: tissue IHC). |
| Evidence strength | HPA describes nuclear expression in most tissues and rates its IHC profile Approved, while flagging low consistency between antibody staining and RNA expression; interpret a matching image as supporting evidence, with that reliability caveat (HPA: tissue IHC reliability). |
| Cellular location and topology | UniProt places RFX1 in the nucleus and annotates no transmembrane segment or signal peptide. These features support a nuclear interpretation, but do not identify an antibody epitope or predict how paraffin-section processing affects detection (UniProt P22670: subcellular location, topology, processing). |
| Antigen retrieval | Retrieval conditions may be compared during paraffin IHC optimization (general IHC practice). No RFX1-specific retrieval requirement or fixation sensitivity is supplied here, so a change in staining after retrieval must be judged using the slide controls rather than attributed to a documented RFX1 effect. |
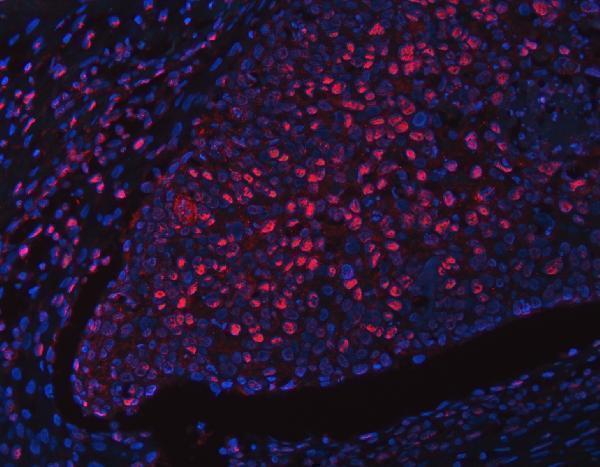
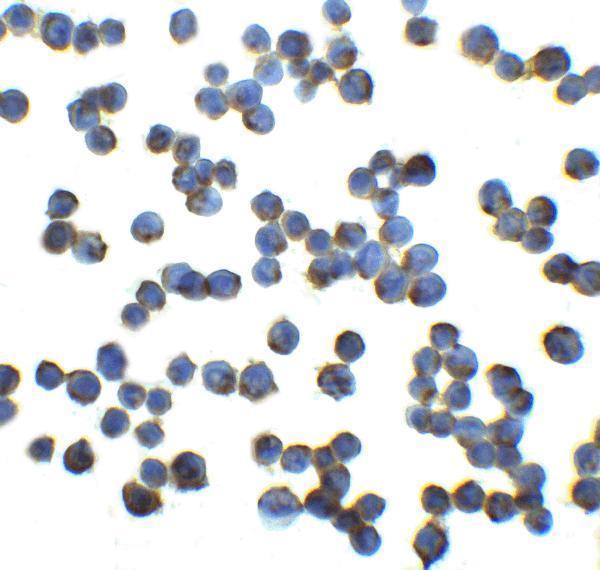
| IF/ICC Q&A: where should signal appear? | Mainly in the nucleoplasm (HPA: ICC-IF, enhanced); HPA also lists vesicles as an uncertain additional location. This IF/ICC observation is a localization cross-check, not a paraffin IHC expectation or an IF protocol (HPA: subcellular summary). |
| Situation | Likely cause | Next action |
|---|---|---|
| Known-positive glandular or tubular cells show no nuclear stain. | The result conflicts with HPA High staining in colon, rectum, and stomach glandular cells or kidney tubular cells; the cause is unresolved (HPA: tissue IHC). | Verify that the expected cells and a working detection control are present; review the IHC-P run's retrieval, antibody application, and detection steps as general IHC checks. Repeat before interpreting a test tissue as negative (general IHC practice). |
| Signal is strongest in cytoplasm or along cell borders. | That distribution conflicts with the reported nuclear location and no-transmembrane topology (UniProt P22670: subcellular location, topology). | Compare nuclear and extranuclear staining in an HPA High reference population and inspect a no-primary control. If the extranuclear pattern persists, withhold a positive RFX1 call pending antibody-specific validation (HPA: tissue IHC; general IHC practice). |
| Adipocytes, prostate glandular cells, or smooth muscle cells stain strongly. | HPA reports these cell populations as Not detected; cross-reactivity or detection background is possible, but the image alone cannot identify which (HPA: tissue IHC). | Confirm cell identity, compare with a nuclear positive reference, and run a no-primary control to assess detection background (HPA: tissue IHC; general IHC practice). |
| The whole section has diffuse brown background. | General IHC possibilities include nonspecific antibody binding, incomplete washing, or endogenous detection activity; no RFX1-specific background mechanism is supplied (general IHC practice). | Inspect a no-primary control, then review blocking, washes, detection conditions, and antibody concentration. Score only a resolved nuclear, cell-specific pattern (general IHC practice; UniProt P22670: nucleus). |
| Staining varies between tissue types or disagrees with RNA data. | HPA explicitly reports low consistency between antibody staining and RNA expression, despite its Approved tissue IHC rating (HPA: reliability description). | Record the exact tissue and cell population, compare with HPA's cell-level staining categories, and retain the discrepancy in the interpretation rather than treating RNA and staining as interchangeable measures (HPA: tissue IHC reliability). |
| Vesicular IF/ICC signal is used to justify cytoplasmic IHC staining. | HPA calls vesicles an uncertain additional ICC-IF location, while its main ICC-IF location is nucleoplasm and its tissue IHC profile is nuclear (HPA: subcellular summary; tissue IHC). | Judge paraffin IHC against the nuclear tissue pattern. Treat vesicular IF/ICC signal as uncertain supporting context, and investigate dominant cytoplasmic IHC staining with controls before assigning it to RFX1 (HPA: subcellular summary; general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Kidney | Cells in tubules | High | Protein (IHC) | HPA → |
| Rectum | Glandular cells | High | Protein (IHC) | HPA → |
| Stomach | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Lymph node | Germinal center cells | Not detected | Protein (IHC) | HPA → |
| Prostate | Glandular cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot RFX1 staining in paraffin section chromogenic IHC by checking nuclear localisation, the documented retrieval condition, and cell type matched controls.
Catalog images show RFX1 IHC in human paraffin sections and IF/ICC in HeLa cells (A04392-1 IHC captions; A04392 IF captions). Both antibodies list human reactivity (catalog reactivity).
A04392-1 lists human IHC and IF and shows staining in a paraffin-embedded section of human intestinal diffuse large B-cell lymphoma (catalog applications/reactivity; A04392-1 IHC caption). A04392 lists human IF and ICC and shows staining in HeLa cells (catalog applications/reactivity; A04392 IF captions).
Which to pick: Choose A04392-1 for tissue IHC: its own image shows paraffin-section staining, with the fixative unreported (A04392-1 IHC caption). Choose A04392 for IF/ICC in cells; its HeLa images support those applications, while clonality is unreported for both SKUs (A04392 IF captions; catalog clone fields). Neither SKU has stated reactivity beyond human, so no cross-species choice is supported (catalog reactivity).