RGN / Regucalcin · IHC design guide

Design Immunohistochemistry for RGN

Use liver hepatocytes and adrenal zona fasciculata as strong positive controls for RGN staining (HPA tissue IHC). This guide covers paraffin-section chromogenic IHC with the catalog antibody and assessment of cytoplasmic and nuclear staining (datasheet A05900-1; HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for RGN (IHC for RGN): expected localisation Cytoplasmic and nuclear staining in selected tissue cells (HPA tissue IHC), antibody A05900-1, validated IHC image, and IHC protocol steps
Printable RGN IHC protocol sheet — expected localisation Cytoplasmic and nuclear staining in selected tissue cells (HPA tissue IHC), antibody A05900-1, controls and protocol steps. Open the full RGN IHC guide →

RGN Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and nuclear staining in selected tissue cells (HPA tissue IHC)
Staining pattern Hepatocytes, exocrine and renal tubule cells, adrenal cortex: cytoplasm/nuclei (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A05900-1)
Positive control ⓘ Adrenal gland+3 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Endogenous peroxidase may raise liver DAB background (standard IHC practice)
Regulation No expression regulator annotated (UniProt)
Isoform / epitope 2 isoforms; epitope differences unspecified (UniProt)
Section 1

Recommended RGN IHC & IF Protocols

The catalog antibody protocol (datasheet: A05900-1) is followed by published RGN IHC protocols from four articles (PMC4240664; PMC10170118; PMC7899017; PMC12898724).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded mouse liver tissue; fixative not specified (datasheet A05900-1)
FixationImage fixative and duration unreported (datasheet A05900-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A05900-1)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A05900-1)
Primary antibodyRabbit anti-RGN, 1μg/ml (datasheet A05900-1)
Primary incubationOvernight at 4 °C (datasheet A05900-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A05900-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultRGN-positive staining in cells in zona fasciculata of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and nuclear expression in hepatocytes, exocrine pancreas, renal tubules and adrenal cortex. No signal in the no-primary control.
💡Decision noteStart with heat-mediated citrate pH 6 retrieval (datasheet: A05900-1); two published protocols also specify citrate pH 6 with heating times (PMC4240664; PMC7899017).
Section 2

What Is the Expected RGN Staining Pattern?

RGN is cytoplasmic and has no transmembrane segment (UniProt Q15493). In tissue IHC, expect cytoplasmic and sometimes nuclear staining in hepatocytes, exocrine pancreatic cells, renal tubules, and adrenal cortex cells (HPA: tissue IHC profile). Staining is high in hepatocytes and zona fasciculata cells (HPA: tissue IHC). The tissue profile has Enhanced reliability, reflecting agreement between staining and RNA expression (HPA: reliability).

What am I looking at on my slide?
Strong cytoplasmic staining in hepatocytes or adrenal zona fasciculata cells, with possible nuclear staining.This matches the high staining reported in those cells and the cytoplasmic and nuclear tissue profile (HPA: tissue IHC). Judge the pattern in identifiable cells, alongside the counterstain (general IHC practice).
Predominantly membranous or extracellular staining, without the expected cellular pattern.RGN is cytoplasmic and has no transmembrane segment (UniProt Q15493); HPA describes cytoplasmic and nuclear tissue staining (HPA: tissue IHC). Review whether detection or background is producing the misplaced signal (general IHC practice). Nuclear staining alone is not grounds for rejection in tissue IHC (HPA: tissue IHC).
Strong staining in adipocytes or respiratory epithelial cells while expected positive cells are weak.Those cell populations were not detected in the sampled HPA tissues (HPA: tissue IHC). Consider cross-reactivity or endogenous detection activity (general IHC practice). An HPA negative observation does not prove every specimen of that tissue must be negative.
Diffuse chromogen covers tissue and obscures cell boundaries.An unreadable background cannot establish RGN localisation (general IHC practice). Compare a control lacking primary antibody and inspect washing, blocking, and detection steps (general IHC practice); do not score diffuse colour as expression.
No staining in hepatocytes or zona fasciculata cells in a putative positive section.Both are high-staining reference populations (HPA: tissue IHC). Check tissue identity and preservation, then review the IHC-validated antibody, retrieval, dilution, and detection against its instructions (general IHC practice). Absence alone cannot distinguish low antigen from an assay failure.
💡Expected RGN appearanceA convincing positive is strong cellular staining in hepatocytes or adrenal zona fasciculata cells, chiefly cytoplasmic with possible nuclear signal (HPA: tissue IHC); diffuse background or isolated membranous colour is suspect (UniProt Q15493 topology; general IHC practice).
How each factor affects the staining
Tissue and cell populationHPA reports high staining in hepatocytes and zona fasciculata cells, medium staining in pancreatic exocrine cells and duodenal Brunner glands, and low staining in kidney proximal tubules (HPA: tissue IHC). Compare like cells when judging intensity; a low reference population gives a less decisive negative result (general IHC practice).
Compartment and assay contextTissue IHC includes cytoplasmic and nuclear staining, whereas approved ICC-IF localisation is cytosolic (HPA: tissue IHC; HPA: subcellular ICC-IF). Interpret nuclear signal in the context of the assay and cell type; neither record establishes that every nucleus should stain.
Antibody validationHPA029102 and HPA029103 have Enhanced IHC status; HPA029104 has Approved ICC status (HPA: antibodies). These statuses support their respective applications, but do not establish identical staining with a different catalog antibody or specify its dilution.
Isoforms and molecular formUniProt lists two isoforms, no signal peptide or propeptide, and a 1–299 regucalcin chain (UniProt Q15493). Without an epitope map, the record cannot show whether the IHC-validated antibody recognizes both isoforms or whether they differ in tissue staining.
IF/ICC Q: What should fluorescence look like?A: Expect cytosolic localisation under the approved ICC-IF record (HPA: subcellular ICC-IF). Tissue IHC also reports nuclear expression (HPA: tissue IHC); use the assay-specific observation when interpreting images. This section supplies no IF/ICC protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive tissue is blank.A missed assay step or insufficient signal is possible (general IHC practice); high hepatocyte and zona fasciculata staining is the HPA reference (HPA: tissue IHC).Confirm the sampled cells, primary antibody identity, retrieval and detection steps; compare with a valid positive control (general IHC practice). No RGN-specific retrieval condition is supplied.
Only kidney proximal tubules look faint.HPA reports low staining in proximal tubule cell bodies (HPA: tissue IHC), so faint signal there may fit the reference pattern.Assess high-staining hepatocytes or zona fasciculata cells in parallel before treating the kidney result as assay failure (HPA: tissue IHC; general IHC practice).
Colour appears on membranes or outside cells.That distribution conflicts with cytoplasmic RGN and its lack of a transmembrane segment (UniProt Q15493).Inspect a control lacking primary antibody, examine background and reassess the stained cells (general IHC practice). Do not assign the colour to RGN solely because it is intense.
Many unrelated cells show uniform colour.Nonspecific staining or endogenous detection activity is possible (general IHC practice); selected adipocytes and respiratory epithelial cells were not detected by HPA (HPA: tissue IHC).Compare those cell types with an appropriate control and review blocking and detection controls (general IHC practice). Treat HPA negatives as sampled observations, not universal exclusions.
Nuclear staining appears alongside cytoplasmic staining.This can match the tissue IHC profile (HPA: tissue IHC), even though ICC-IF localisation is approved for cytosol (HPA: subcellular ICC-IF).Check whether signal occurs in the expected tissue cell population and whether background obscures localisation (HPA: tissue IHC; general IHC practice). Do not reject it solely for being nuclear.
Background prevents confident scoring.Diffuse chromogen may reflect assay background rather than a resolvable cellular pattern (general IHC practice).Compare a control lacking primary antibody; review blocking, washing, and detection conditions under the IHC-validated antibody's instructions (general IHC practice). Score only interpretable cells.

Sample controls for RGN IHC & IF

🧪Run liver first: hepatocytes should stain strongly (HPA: High in hepatocytes); use adipose tissue as a negative, with adipocytes expected at background (HPA: Not detected in adipocytes). On the liver slide, compare hepatocyte staining with adjacent nonhepatocyte areas, interpreting any apparent negative cells against the control slides rather than assuming they lack RGN.
Positive control tissue: Adrenal gland (Cells in zona fasciculata, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show RGN in CACO-2, Hep-G2, U2OS, with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only), species- and isotype-matched rabbit control IgG, and RGN-knockout tissue or a validated peptide-block control (caption: rabbit primary antibody). In liver, control endogenous peroxidase and endogenous biotin when using the reported biotin-based chromogenic detection (selected-SKU caption: biotinylated secondary, avidin-biotin complex and DAB).
⚠️Feasibility: The selected-SKU caption reports paraffin-section mouse liver staining after citrate retrieval at pH 6 for 20 minutes, but its fixative is unreported; no target-specific fixation window or fixation effect is supplied (selected-SKU caption). Retrieval was used in that example, but a requirement for retrieval across preparations is unreported; the evidence also does not establish whether frozen sections or IF are easier (selected-SKU caption; HPA: ICC-IF images and approved cytosolic localization). Liver's endogenous peroxidase and biotin can complicate interpretation of this chromogenic method, so assess background with the controls above (selected-SKU caption: biotin-based DAB detection; standard IHC practice).

HPA tissue IHC evidence for RGN

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Cells in zona fasciculata High Protein (IHC) HPA →
Liver Hepatocytes High Protein (IHC) HPA →
Duodenum Glands of Brunner Medium Protein (IHC) HPA →
Pancreas Exocrine glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Appendix Endocrine cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced RGN IHC Tips

Troubleshoot RGN staining in paraffin sections by checking retrieval, controls, cell identity and compartment before interpreting chromogenic signal.

How should I retrieve RGN in paraffin sections when staining is weak?
Start with heat-mediated citrate retrieval at pH 6 for 20 minutes (datasheet A05900-1). The selected paraffin-section image used those conditions in mouse liver, followed by an overnight primary incubation at 4°C (datasheet A05900-1). If hepatocyte staining is weak, compare a fresh section with the documented run while holding antibody concentration, detection and development time constant. Check that sections remained covered by buffer during heating and cooled consistently before blocking; uneven treatment can create patchy staining (standard IHC practice). Compare the resulting hepatocyte pattern with the reported high liver signal before changing retrieval conditions (HPA: high in hepatocytes).
Could fixation explain absent or uneven RGN staining?
Target-specific sensitivity of RGN staining to fixation is unknown from the supplied evidence: the selected paraffin-section caption does not state a fixative (datasheet A05900-1). Record the actual fixative, fixation duration and tissue thickness for each specimen, then compare matched sections processed together (standard IHC practice). If staining varies across specimens, review those records alongside section age, retrieval and detection conditions before attributing the difference to RGN abundance. Include a well-preserved liver control with each run because hepatocytes have reported high staining (HPA: high in hepatocytes). The tissue staining pattern and protein annotations do not establish an RGN-specific fixation effect (HPA: tissue IHC; UniProt Q15493).
Should RGN appear in nuclei or only in cytoplasm?
Expect substantial cytoplasmic staining: RGN is annotated as cytoplasmic, and its approved subcellular location is cytosol (UniProt Q15493; HPA: cytosol). Nuclear staining is also reported in hepatocytes, exocrine pancreas, renal tubules and adrenal cortex in tissue IHC (HPA: tissue profile). Judge nuclear signal against the accompanying cytoplasmic pattern, cell identity and a clean negative control rather than discarding it automatically. A crisp membrane-only outline would be discordant with the absence of a transmembrane segment (UniProt Q15493 topology). Compare serial sections at the same chromogen development time so apparent compartment differences are not driven by signal saturation (standard IHC practice).
Could RGN isoforms or epitope accessibility change the staining pattern?
RGN has 2 annotated isoforms, but the supplied evidence does not map this antibody’s epitope to either one (UniProt Q15493; datasheet A05900-1). Interpret differences between specimens as staining differences until isoform coverage and specificity have been established independently. The protein has 3 listed N6-succinyllysine sites at residues 144, 244 and 253; their effect on antibody binding is unknown (UniProt Q15493). If staining is unexpected, compare matched positive and negative tissues under the documented citrate retrieval conditions before invoking epitope masking (datasheet A05900-1; HPA: tissue IHC). Record the antibody lot and processing conditions to make later comparisons interpretable (standard IHC practice).
How should I assess RGN when adding an IF channel?
Treat IF as a separate application and assess its controls independently of the paraffin-section chromogenic result (datasheet A05900-1). Multiplex RGN with a marker identifying the expected cell population, such as hepatocytes in liver, and check that both signals occupy the intended cells (HPA: high in hepatocytes). Choose a fluorophore channel after inspecting unstained tissue for autofluorescence, then include single-channel controls to assess bleed-through (standard IF practice). For an intracellular epitope, optimise permeabilisation for access to the cytosolic side; RGN is cytosolic and has no transmembrane segment (HPA: cytosol; UniProt Q15493 topology). Compare compartment patterns with the cytosolic IF annotation while assessing any tissue nuclear signal separately (HPA: subcellular and tissue profiles).
What causes diffuse brown background in RGN IHC?
First inspect a section without primary antibody to separate detection-system background from primary-dependent staining (standard IHC practice). The documented image used a biotinylated secondary, avidin–biotin detection and DAB, so evaluate endogenous peroxidase and endogenous biotin controls when that workflow is used (datasheet A05900-1; standard IHC practice). Review serum blocking, washing and DAB development time across sections before increasing the primary concentration; the image used 10% goat serum and 1 μg/ml primary (datasheet A05900-1). Compare background in cell populations reported as undetected, such as adipocytes, with hepatocyte staining (HPA: adipocytes not detected; HPA: high in hepatocytes). Exclude pigment and tissue folds during review (standard IHC practice).
How can I quantify RGN staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the anatomical region and cell population before scoring, then keep retrieval, imaging and DAB development consistent across the comparison (standard IHC practice). For hepatocytes, record the percentage of positive cells and intensity categories 0–3; their weighted sum gives an H-score from 0–300 (standard IHC practice; HPA: high in hepatocytes). If counting discrete positive cells, report cells per mm² of viable tissue rather than per whole slide (standard IHC practice). Normalise scores to the number of eligible cells or viable tissue area, as appropriate, and report cytoplasmic and nuclear scores separately because both patterns occur in tissue IHC (standard IHC practice; HPA: tissue profile). Include the same control section across batches (standard IHC practice).
How do I distinguish genuine RGN signal from artefact?
A convincing result places signal in the expected cells and compartments: hepatocytes have reported high staining, while RGN is cytosolic and tissue IHC can also show nuclear signal (HPA: tissue and subcellular profiles). Treat membrane-only staining cautiously because RGN lacks a transmembrane segment (UniProt Q15493 topology). Check unexpected positivity in adipocytes against controls, since adipocyte staining was reported as undetected (HPA: adipocytes not detected). Discount staining confined to section edges, folds or necrotic areas, and compare with the no-primary section for endogenous enzyme or detection background (standard IHC practice). When conclusions depend on unexpected cells, seek an independent specificity check before assigning that signal to RGN (standard IHC practice).
Boster reagents

Best RGN / Regucalcin IHC Antibodies

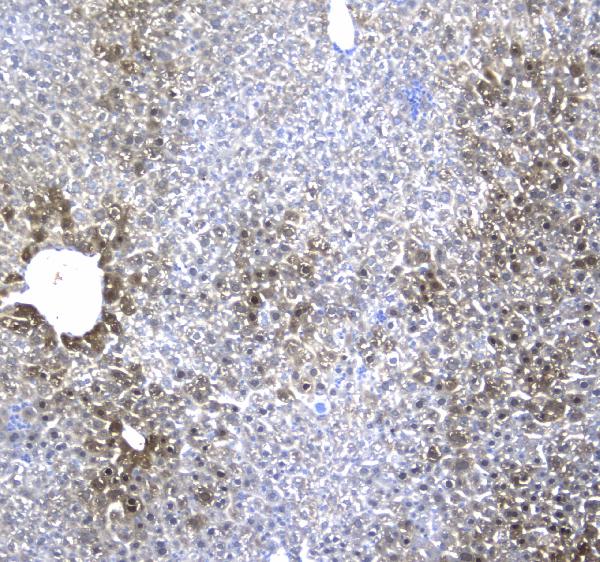
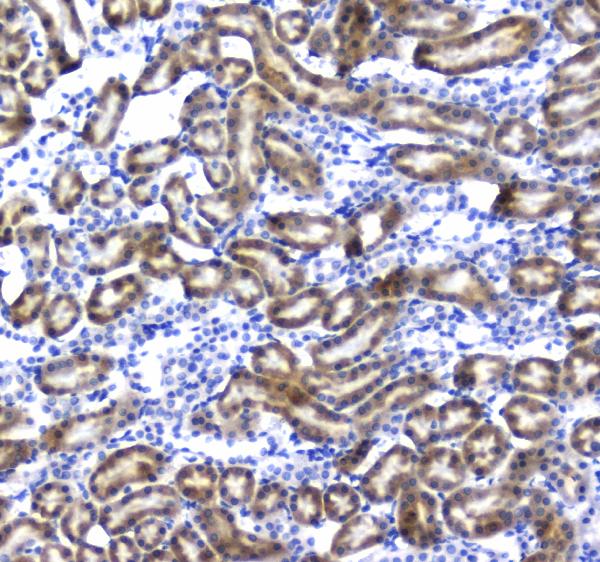
A05900-1 has IHC images from paraffin sections of mouse liver, rat liver and rat kidney (A05900-1 image captions); human reactivity is listed (A05900-1 catalog).

Real IHC data IHC analysis of Regucalcin using anti-Regucalcin antibody (A05900-1). Regucalcin was detected in paraffin-embedded section of mouse liver tissue . Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-Regucalcin Antibody (A05900-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-Regucalcin/RGN Antibody ®
Cat # A05900-1

A05900-1 is listed for IHC and for human, mouse and rat reactivity (A05900-1 catalog). Its IHC images show paraffin sections of mouse liver, rat liver and rat kidney; the fixative is unreported (A05900-1 image captions).

Which to pick: Choose A05900-1 for paraffin-section tissue IHC: it is a rabbit polyclonal antibody listed for IHC, with images from mouse liver and rat liver and kidney (A05900-1 catalog; A05900-1 image captions). For cross-species work, A05900-1 lists human, mouse and rat reactivity, although its pictured IHC evidence covers mouse and rat only (A05900-1 catalog; A05900-1 image captions). There is no payload-supported IF/ICC pick because A05900-1 has no listed IF/ICC application or IF image (A05900-1 catalog); its paraffin-section captions do not report the fixative (A05900-1 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q15493 (RGN_HUMAN, Regucalcin).
  2. Human Protein Atlas. RGN tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. RGN subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. RGN antibody validation summary (3 antibodies).
  5. Regucalcin expression in bovine tissues and its regulation by sex steroid hormones in accessory sex glands. PloS one 2014 — PMC4240664.
  6. RGN as a prognostic biomarker with immune infiltration and ceRNA in lung squamous cell carcinoma. Scientific reports 2023 — PMC10170118.
  7. Regucalcin expression profiles in veal calf testis: validation of histological and molecular tests to detect sex steroids illicit administration. PeerJ 2021 — PMC7899017.
  8. High Glucose-Induced Alterations in Regucalcin Expression in Podocytes and Their Potential Consequences. International journal of molecular sciences 2026 — PMC12898724.
  9. PubMed PMID:7548213 — UniProt-cited evidence.
  10. PubMed PMID:10677570 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.