This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan RIPK1 chromogenic IHC in paraffin sections using the cytoplasmic tissue pattern and cell type differences reported by HPA (HPA tissue IHC). Compare staining within defined cell populations and keep fixation consistent across samples (HPA tissue IHC; standard IHC practice).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining (HPA tissue IHC); cell membrane location (UniProt) | |
| Staining pattern | Ubiquitous cytoplasmic staining; high in selected glandular cells (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A00141-1) | |
| Caveat | Staining intensity varies by tissue cell type (HPA tissue IHC) | |
| Regulation | No expression regulator annotated (UniProt) | |
| Isoform / epitope | 2 isoforms; check epitope coverage (UniProt) |
The catalog antibody’s IHC-P protocol is followed by published RIPK1 staining protocols for rat cerebellum (PMC13582310) and mouse spleen (PMC11071064).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A00141-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-RIPK1, 2.5 μg/mL (datasheet A00141-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | RIPK1-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control. |
RIPK1 should appear predominantly in the cytoplasm, with possible membrane-associated signal (UniProt Q13546 subcellular location; HPA: cytoplasmic tissue profile; HPA: plasma membrane and cytosol approved in ICC-IF). In paraffin sections, expect especially strong staining in glandular cells of several digestive tissues and type I alveolar cells in lung (HPA: High). HPA rates the tissue IHC evidence Supported, with medium consistency between staining and RNA data (HPA: reliability).
| Cytoplasmic staining is clear in colon or stomach glandular cells, or lung type I alveolar cells; some cells show membrane accentuation. | This fits the reported high-staining cell populations (HPA: High in these cells) and RIPK1 localisation (UniProt Q13546: cytoplasm and cell membrane). Score the relevant cells and compartment separately from surrounding tissue (general IHC practice). |
| Strong nuclear-only staining dominates while the expected cytoplasmic pattern is absent. | Treat this as a localisation mismatch, not evidence for nuclear RIPK1: the supplied localisation records specify cytoplasm and cell membrane (UniProt Q13546; HPA: approved cytosol and plasma membrane in ICC-IF). Check whether the nuclear colour belongs to counterstain or nonspecific detection (general IHC practice). |
| An unexpected cell population stains more strongly than the documented positive cells on the same section. | Review cell identity before calling this cross-reactivity: HPA describes ubiquitous cytoplasmic expression and low tissue specificity, so staining outside its High examples can be genuine (HPA: tissue profile; RNA specificity). If staining lacks the expected compartment, assess nonspecific primary binding or endogenous detection activity (general IHC practice). |
| Colour spreads across stroma, lumina, or most of the section without distinct cellular boundaries. | That distribution is difficult to reconcile with the reported cytoplasmic cellular profile (HPA: tissue IHC). Evaluate background from detection reagents, incomplete blocking, or inadequate washing using appropriate controls (general IHC practice). Background alone cannot establish RIPK1 abundance. |
| A known-positive glandular or alveolar population has no convincing signal. | First confirm the sampled cell population: HPA reports High staining in appendix, colon, duodenum, gallbladder, rectum, small intestine, and stomach glandular cells, and lung type I alveolar cells (HPA: tissue IHC). A blank result warrants review of the antibody and detection workflow; HPA's Supported rating does not guarantee every specimen will stain (HPA: reliability; general IHC practice). |
| Tissue and cell selection | Use the named High populations as positive references (HPA: tissue IHC). HPA lists low staining in cerebral-cortex endothelial cells, hippocampal and caudate glial cells, adrenal and salivary glandular cells, and liver cholangiocytes; low is not an absence control (HPA: Low; negative list empty). |
| Subcellular interpretation | RIPK1 has no transmembrane segment, although UniProt lists cell-membrane localisation (UniProt Q13546: topology and subcellular location). Do not require a continuous membrane rim in paraffin sections; HPA describes the tissue pattern as ubiquitous cytoplasmic expression (HPA: tissue profile). |
| Antibody evidence | HPA lists HPA015257 and CAB010302 as IHC Supported and ICC Approved (HPA: antibody validation). Supported is the supplied status; it does not establish that a different catalog antibody has the same tissue pattern or that either antibody resolves RIPK1 isoforms (HPA: antibody records; UniProt Q13546: two isoforms). |
| IF/ICC Q&A: Where should signal appear? | Cytosol and plasma membrane are the approved ICC-IF locations, with images listed for A-431, U-251MG, U2OS, and KOLF2.1J (HPA: subcellular). This localisation helps interpret IF images; the tissue-intensity examples come from IHC and should not be assigned to those cell lines (HPA: tissue IHC; HPA: ICC-IF record). |
| Processing and molecular forms | UniProt reports a single chain spanning residues 1–671, no signal peptide or propeptide, and two isoforms (UniProt Q13546: processing and isoforms). These annotations provide no basis to expect staining of a shed fragment or to predict which isoform an antibody detects without its epitope information. |
| Situation | Likely cause | Next action |
|---|---|---|
| The intended positive field looks blank. | The section may lack the specific glandular or type I alveolar cells reported as High, or the staining run may have failed (HPA: High cell populations; general IHC practice). | Verify cell identity and run a documented High tissue alongside the test section; inspect the detection controls and the antibody's IHC-P instructions (HPA: tissue IHC; general IHC practice). |
| Signal is weak in a cell population listed as Low. | Low staining is already reported for several cell populations and does not imply a true negative (HPA: Low; negative list empty). | Compare with a documented High population in the same run before changing the assay; record intensity by cell type (HPA: High and Low; general IHC practice). |
| Nuclei appear positive but cytoplasm does not. | The distribution conflicts with the supplied RIPK1 localisation; counterstain or nonspecific colour may be mistaken for target signal (UniProt Q13546; HPA: cytoplasmic profile; general IHC practice). | Review the single-stain and no-primary controls, then assess staining in the expected cytoplasmic compartment (general IHC practice; HPA: tissue profile). |
| Diffuse brown deposit obscures cell boundaries. | Background from endogenous detection activity, reagent binding, or washing can obscure a cellular pattern (general IHC practice). | Compare no-primary and detection-only controls; check blocking, washing, and detection conditions before assigning a RIPK1 score (general IHC practice). |
| Membrane accentuation is absent despite clear cytoplasmic staining. | A complete membrane rim is not required by the tissue IHC profile, which reports ubiquitous cytoplasmic expression (HPA: tissue profile). | Score the cytoplasmic signal in the correct cells; use the HPA ICC-IF localisation only as supporting compartment context (HPA: tissue IHC; HPA: approved ICC-IF locations). |
| Results change after retrieval conditions are adjusted. | The supplied sources do not report RIPK1-specific retrieval or fixation sensitivity (UniProt Q13546; HPA: supplied tissue and subcellular records). | Use the IHC-validated antibody's stated IHC-P conditions as the starting point and compare controls across runs; interpret any condition effect as assay-specific until validated (general IHC practice). |



Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | High | Protein (IHC) | HPA → |
| Lung | Alveolar cells type I | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: RIPK1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot RIPK1 staining in paraffin sections by checking retrieval, compartment, controls, and scoring before interpreting pathway activity.
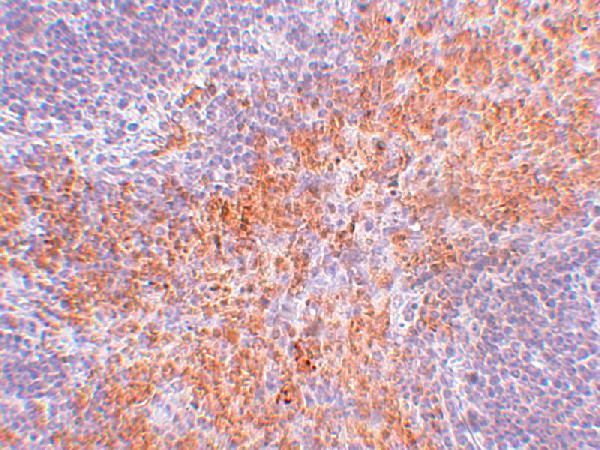
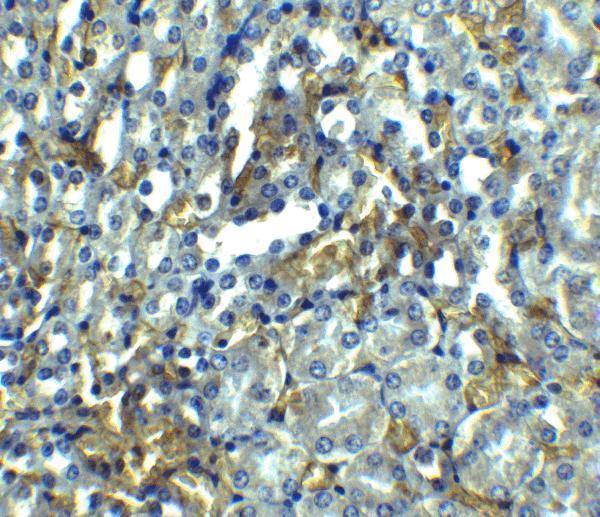
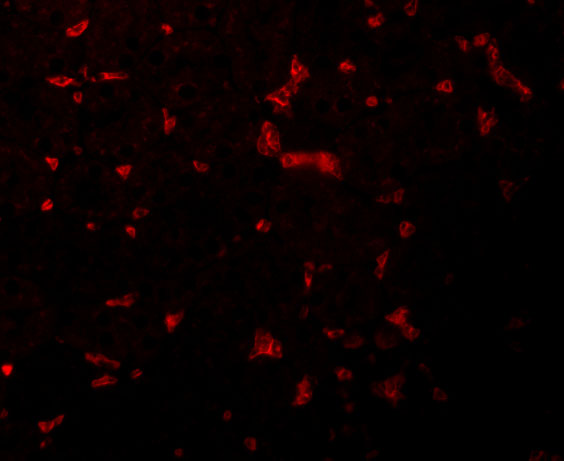
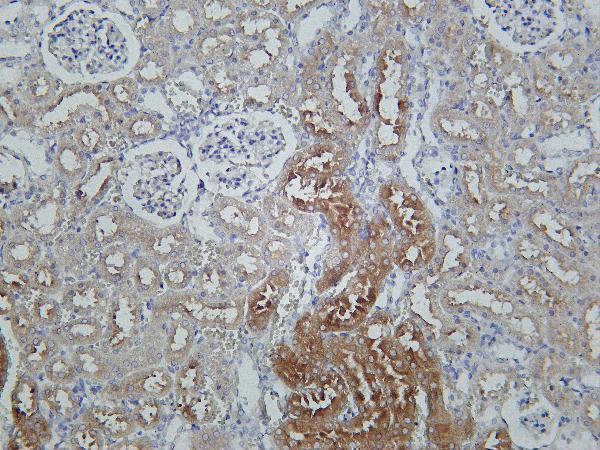
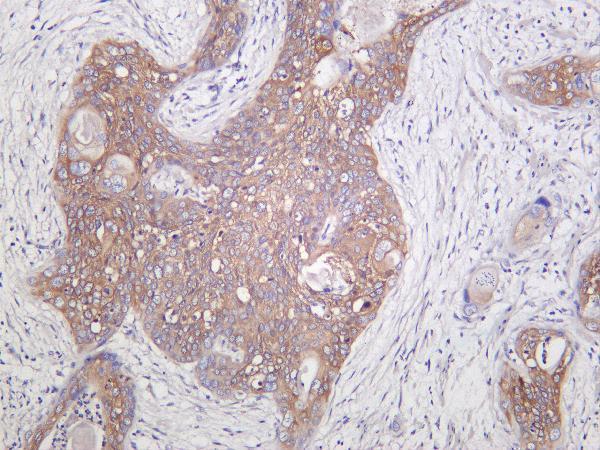
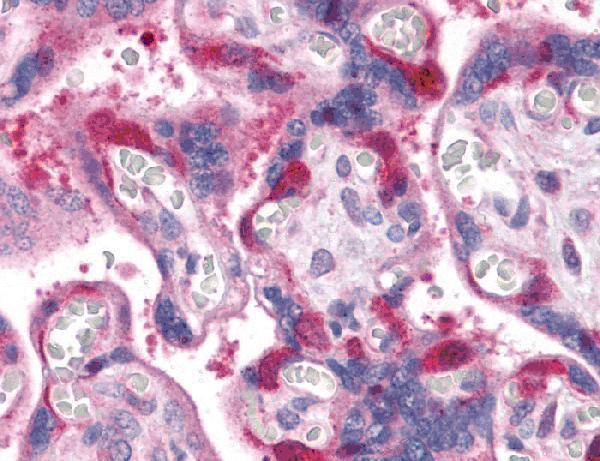
Three catalog antibodies have RIPK1 IHC images in human placenta, mouse kidney, or human cervical carcinoma; one also has a mouse kidney cell IF image (catalog image captions).
A00141 shows human placenta IHC at 10 μg/mL (A00141 IHC image caption); A00141-1 shows mouse kidney IHC at 2.5 μg/mL and mouse kidney cell IF at 20 μg/mL (A00141-1 image captions). M00141-3 has IHC captions for rat kidney and human cervical carcinoma, while its listed reactivity is Human only (M00141-3 IHC image captions; catalog reactivity).
Which to pick: For human tissue IHC-P, A00141 has a human placenta image and a listed 5–10 μg/mL range (A00141 IHC image caption; datasheet: IHC-P, 5–10 μg/mL); its fixative is unreported (A00141 IHC image caption). For IF, start with A00141-1 at 20 μg/mL, supported by its mouse kidney cell IF image (A00141-1 IF image caption; datasheet: 20 μg/mL). For work across human, mouse, and rat, A00141-1 lists all three species and IHC-P and IF applications, with mouse kidney IHC evidence; its fixative is unreported (A00141-1 catalog reactivity and applications; IHC image caption).