RPA2 / Replication protein A 32 kDa subunit · IHC design guide

Design Immunohistochemistry for RPA2

Plan chromogenic RPA2 IHC on paraffin sections using the catalog antibody at 2–5 μg/mL (datasheet: M02067-2). Assess nuclear staining by cell type (HPA tissue IHC) and consider damage-associated nuclear foci when interpreting the pattern (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for RPA2 (IHC for RPA2): expected localisation Nuclear tissue staining (HPA tissue IHC), antibody M02067-2, validated IHC image, and IHC protocol steps
Printable RPA2 IHC protocol sheet — expected localisation Nuclear tissue staining (HPA tissue IHC), antibody M02067-2, controls and protocol steps. Open the full RPA2 IHC guide →

RPA2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear tissue staining (HPA tissue IHC)
Staining pattern Widespread nuclear staining across tissue cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M02067-2)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep formalin fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat DNA damage may shift nuclear signal into foci (UniProt)
Regulation DNA damage redistributes RPA2 into foci (UniProt)
Isoform / epitope 3 isoforms; check antibody epitope coverage (UniProt)
Section 1

Recommended RPA2 IHC & IF Protocols

The catalog antibody has an IHC-P protocol (datasheet: M02067-2). The four published options below describe RPA2 staining in breast carcinoma, oral carcinoma, and carotid plaque (PMC9743555; PMC5354728; PMC4344740; PMC10063624).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human spleen tissue; fixative not specified (datasheet M02067-2)
FixationImage fixative and duration unreported (datasheet M02067-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M02067-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M02067-2)
Primary antibodyMouse monoclonal (clone 3B2E9) anti-RPA2, 2 μg/ml (datasheet M02067-2)
Primary incubationOvernight at 4 °C (datasheet M02067-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet M02067-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultRPA2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: M02067-2); use each article’s retrieval conditions when reproducing its protocol (PMC9743555; PMC5354728; PMC4344740; PMC10063624).
Section 2

What Is the Expected RPA2 Staining Pattern?

RPA2 should stain nuclei across many cell types in paraffin sections: HPA describes ubiquitous nuclear expression with supported tissue IHC reliability and high staining in several listed cell populations (HPA: tissue IHC). Nuclear localization agrees with its replication and DNA repair role; the protein has no transmembrane segment (UniProt P15927: subcellular location and topology).

What am I looking at on my slide?
Clear nuclear chromogen in glandular cells of breast or adrenal gland.This matches HPA high staining in those cells and its ubiquitous nuclear profile (HPA: tissue IHC). Judge the result against nuclear counterstain and background in the same section (general IHC practice).
Predominantly cytoplasmic or membranous staining, with little nuclear signal.The compartment conflicts with the reported nuclear location and lack of a transmembrane segment (UniProt P15927). Treat it as possible nonspecific staining or detection artefact; verify with an appropriate control (general IHC practice).
Signal concentrates in a cell population while expected positive cells are unstained.For example, assess whether bone marrow hematopoietic cells show the reported high staining (HPA: High in hematopoietic cells). An unexpected distribution can reflect cross-reactivity or endogenous detection activity; HPA provides no negative-cell list here (HPA: tissue IHC; general IHC practice).
Weak, diffuse chromogen obscures nuclear boundaries throughout the section.This cannot be scored confidently as nuclear RPA2, even though broad nuclear expression is expected (HPA: ubiquitous nuclear expression). Compare with a detection-only control and assess blocking, antibody concentration and wash conditions (general IHC practice).
No nuclear staining in a known-positive tissue.Absence in the HPA-listed high-staining cells, such as bronchial respiratory epithelium, warrants a technical check before a biological interpretation (HPA: High in respiratory epithelial cells). Examine tissue preservation, retrieval and detection controls without assuming a target-specific fixation effect (general IHC practice).
💡Expected RPA2 appearanceCall a result positive when chromogen is predominantly nuclear in the relevant cells, with readily visible signal in an HPA-listed high-staining population; isolated cytoplasmic or membranous color is suspect (HPA: tissue IHC; UniProt P15927: nuclear location and topology).
How each factor affects the staining
Tissue and cell contextHPA reports high staining in adrenal and breast glandular cells, appendix endocrine cells, marrow hematopoietic cells, bronchial respiratory epithelium and listed neural populations (HPA: tissue IHC). Its empty negative list does not define a negative tissue.
Compartment and damage responseThe baseline expectation is nuclear staining; UniProt also places RPA2 in PML bodies and reports redistribution to discrete nuclear foci after DNA damage (UniProt P15927). Do not require damage-associated foci in routine IHC sections.
Antibody validationHPA026306, HPA026309 and CAB016538 have Supported IHC status (HPA: antibodies). This supports comparing nuclear patterns, but does not establish identical intensity, epitope recognition or performance for an unlisted catalog antibody.
Molecular variationThree isoforms and several modified residues, including phosphorylation sites, are annotated (UniProt P15927). The supplied record gives no IHC epitope or modification-specific staining effect, so use these annotations as interpretive limits.
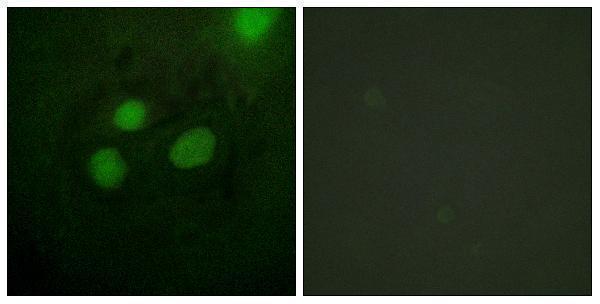
IF/ICC: where should signal appear?In nucleoplasm and nuclear bodies; HPA marks both locations enhanced in ICC-IF (HPA: subcellular). This answers localization only; it provides no IF/ICC protocol option.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive tissue has no nuclear signal.The slide may have failed at retrieval, primary-antibody binding or detection (general IHC practice); HPA reports high staining in the specified positive cells (HPA: tissue IHC).Run a known-positive section with the same detection run, confirm reagent and control performance, then assess retrieval using the antibody's validated IHC instructions (general IHC practice).
Staining is mainly cytoplasmic or membranous.That location conflicts with RPA2's nuclear annotation and lack of a transmembrane segment (UniProt P15927); nonspecific binding or detection artefact is possible (general IHC practice).Compare nuclear counterstain, inspect a detection-only control and reassess antibody concentration and washes before scoring the section (general IHC practice).
Diffuse background makes nuclei hard to distinguish.Background can arise from nonspecific binding, inadequate blocking or incomplete washes (general IHC practice). HPA's ubiquitous nuclear profile alone cannot validate diffuse color (HPA: tissue IHC).Check a detection-only control and optimize blocking, antibody concentration and washes within the validated IHC workflow (general IHC practice).
Strong color appears only in unexpected cells.Cross-reactivity or endogenous detection activity is possible (general IHC practice). HPA lists high-staining populations but supplies no negative-cell examples for this record (HPA: tissue IHC).Confirm the expected cells and compartment on the same section; use appropriate primary-omission and endogenous-activity controls for the detection chemistry (general IHC practice).
Nuclear puncta are interpreted as a failed diffuse pattern.RPA2 may redistribute to discrete nuclear foci after DNA damage, while its annotated locations include the nucleus and PML bodies (UniProt P15927). Routine tissue context alone does not establish damage.Score nuclear localization separately from puncta; seek independent damage-context evidence before assigning a damage-response interpretation (UniProt P15927; general IHC practice).
Results differ between antibody preparations.The three listed antibodies have Supported IHC validation, but the supplied HPA statuses do not prove matched epitope coverage or staining strength (HPA: antibodies).Compare each preparation against the same HPA-listed positive cells and nuclear criterion; follow its own validated IHC instructions for dilution and detection (HPA: tissue IHC; general IHC practice).

Sample controls for RPA2 IHC & IF

🧪Run bone marrow first and assess nuclear staining in hematopoietic cells (HPA: High in bone marrow hematopoietic cells; UniProt P15927: nuclear localization). HPA detects RPA2 in all 45 scored tissues, so use no-primary and isotype controls instead of a negative tissue; nuclei without chromogen on the positive slide show local background but are not validated RPA2-negative cells (HPA: no negative tissue rows).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: RPA2 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show RPA2 in A-431, U-251MG, U2OS, U2OS, siRNA 2 (10x), U2OS, siRNA 2 (40x), U2OS, scrambled (10x), U2OS, scrambled (40x), with annotated localisation: Nucleoplasm (enhanced), Nuclear bodies (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a concentration- and subclass-matched mouse IgG isotype control, and RPA2 knockout material as a biological specificity control if available (caption: mouse primary antibody; standard IHC practice). In bone marrow, quench endogenous peroxidase and check for endogenous biotin before interpreting chromogenic staining (caption: SABC/DAB detection; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected M02067-2 paraffin-section caption does not state the fixative (caption: fixative unreported). The caption uses heat retrieval in EDTA at pH 8.0 for spleen, which provides a starting condition but does not establish that retrieval is required for bone marrow (caption: EDTA pH 8.0 retrieval in spleen). HPA shows ICC-IF images with nucleoplasmic and nuclear-body localization, but the supplied evidence does not establish whether frozen sections or IF are easier than paraffin IHC; endogenous peroxidase and biotin warrant control in bone marrow (HPA: subcellular ICC-IF images; standard IHC practice).

HPA tissue IHC evidence for RPA2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Endocrine cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: RPA2 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced RPA2 IHC Tips

Troubleshoot nuclear RPA2 staining in paraffin sections by checking retrieval, controls, compartment, and scoring before interpreting DNA damage responses (UniProt P15927; HPA tissue IHC).

Which retrieval conditions should I try when nuclear RPA2 staining is weak?
Start with heat mediated antigen retrieval in EDTA at pH 8.0 for the catalog antibody in paraffin sections (datasheet M02067-2). Compare a consistent heating and cooling cycle across sections, then check whether nuclei remain intact before increasing retrieval intensity (standard IHC practice). The pictured human spleen section used 2 μg/ml primary antibody overnight at 4°C, so match that tested concentration and incubation when assessing retrieval (caption M02067-2). If staining remains weak, evaluate an alternative retrieval buffer on matched control sections as a fallback, recording nuclear signal and tissue damage separately (standard IHC practice).
Could fixation explain weak or uneven RPA2 staining?
The selected paraffin section caption does not state a fixative, so target specific fixation sensitivity cannot be established from this evidence (caption M02067-2). Record the actual fixative and fixation duration for each specimen, and compare sections processed together before changing antibody concentration (standard IHC practice). Check nuclear preservation and staining near tissue edges; uneven processing can mimic a change in antigen detection (standard IHC practice). If fixation histories differ, optimize retrieval and primary incubation on representative sections from each processing group, using the same detection reagents and a control section in every run (standard IHC practice).
Where should a convincing RPA2 signal appear in tissue?
Score signal primarily within nuclei: RPA2 is nuclear, and HPA reports ubiquitous nuclear tissue expression (UniProt P15927 subcellular; HPA tissue IHC). Nucleoplasm and nuclear bodies are reported locations, while discrete nuclear foci can appear after DNA damage in an ATR dependent manner (HPA subcellular; UniProt P15927 subcellular). Use a nuclear counterstain to distinguish nuclear chromogen from pigment or material overlying cells, and inspect several fields away from section edges (standard IHC practice). Predominantly membranous staining warrants a specificity check because the record lists no transmembrane segment and places RPA2 in the nucleus (UniProt P15927 topology and subcellular).
How do isoforms and phosphorylation affect antibody interpretation?
RPA2 has 3 recorded isoforms and several annotated modified residues, including phosphorylation near its amino terminus (UniProt P15927 isoforms and modified residues). The supplied caption gives no epitope map or isoform coverage for M02067-2, so staining cannot identify a specific isoform or phosphorylation state (caption M02067-2; UniProt P15927 isoforms). Ask for the antibody's epitope information before assigning a mechanistic meaning to a loss of signal, then compare matched sections under identical retrieval conditions (standard IHC practice). Interpret changes in nuclear staining alongside independent evidence of expression or DNA damage, since RPA2 participates in replication and damage responses (UniProt P15927 function).
How should I plan an IF follow-up to the tissue IHC result?
For IF/ICC follow-up, multiplex RPA2 with an independently validated marker for the expected cell population; HPA reports high tissue IHC signal in bone marrow hematopoietic cells and several other cell types (HPA tissue IHC). Choose fluorophores after checking the specimen's autofluorescence in each channel, and include single stain controls when separating overlapping signals (standard IF practice). RPA2 is nuclear and has no transmembrane segment, so use permeabilisation that admits antibody to the nuclear epitope and check nuclear morphology (UniProt P15927 subcellular and topology; standard IF practice). Compare nucleoplasmic and nuclear body patterns with nuclear counterstaining; DNA damage associated foci require appropriate controls before interpretation (HPA subcellular; UniProt P15927 subcellular).
How can I reduce diffuse chromogen without losing nuclear signal?
Start with a no primary control and inspect whether diffuse chromogen persists, especially in areas with endogenous enzyme activity or tissue damage (standard IHC practice). The pictured section used 10% goat serum blocking, biotinylated goat anti mouse secondary for 30 minutes at 37°C, and a streptavidin biotin complex with DAB (caption M02067-2). Check peroxidase blocking and wash stringency as general chromogenic IHC controls, then titrate primary concentration around the pictured 2 μg/ml condition on matched sections (standard IHC practice; caption M02067-2). Retain settings that preserve nuclear detail while reducing signal in the no primary control (standard IHC practice).
What should I measure when comparing RPA2 across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because the reported tissue pattern is broadly nuclear (HPA tissue IHC; UniProt P15927 subcellular). For chromogenic sections, report nuclear H-score or the percentage of positive nuclei, with thresholds and intensity bins fixed before comparing groups (standard IHC practice). Normalize counts to evaluable nuclei within the same annotated region, or report positive nuclear density per mm² when cell density itself matters (standard IHC practice). Exclude folds, necrotic areas, and damaged edges consistently, and keep retrieval, detection, imaging, and scoring settings matched across comparison sections (standard IHC practice).
When does RPA2 staining indicate a real biological change?
A convincing result is reproducible nuclear staining in preserved cells with appropriate control behavior, consistent with reported nuclear RPA2 localisation (UniProt P15927 subcellular; HPA tissue IHC; standard IHC practice). Compare the same cell population across groups, since HPA reports high staining in multiple distinct tissue cell types and broadly nuclear expression (HPA tissue IHC). Treat predominantly membranous signal, edge restricted staining, necrotic chromogen, or color remaining in a no primary control as possible artefact (UniProt P15927 topology and subcellular; standard IHC practice). Increased nuclear signal alone does not prove DNA damage: RPA2 also functions in replication, while damage can redistribute it into nuclear foci (UniProt P15927 function and subcellular).
Boster reagents

Best RPA2 / Replication protein A 32 kDa subunit IHC Antibodies

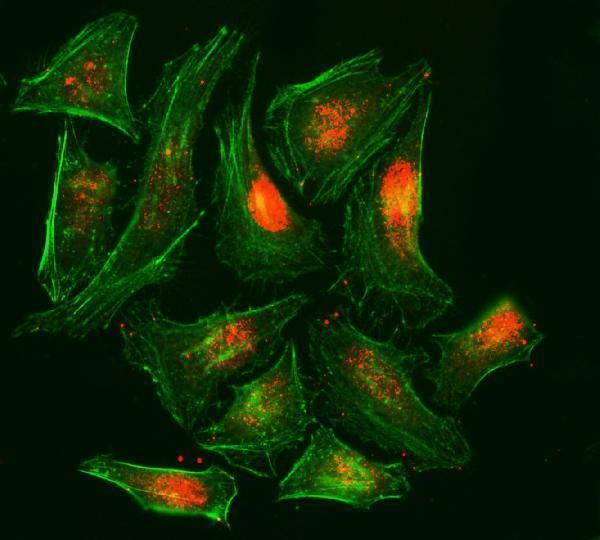
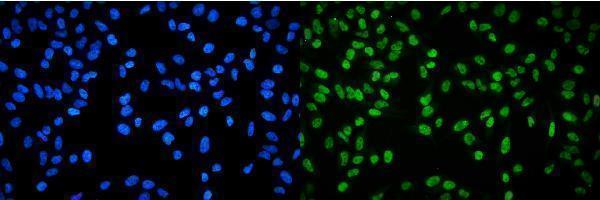
Anti-RPA2 antibodies have IHC images from human paraffin sections and human, mouse, and rat tissues; IF images show human HeLa cells (catalog IHC and IF captions).

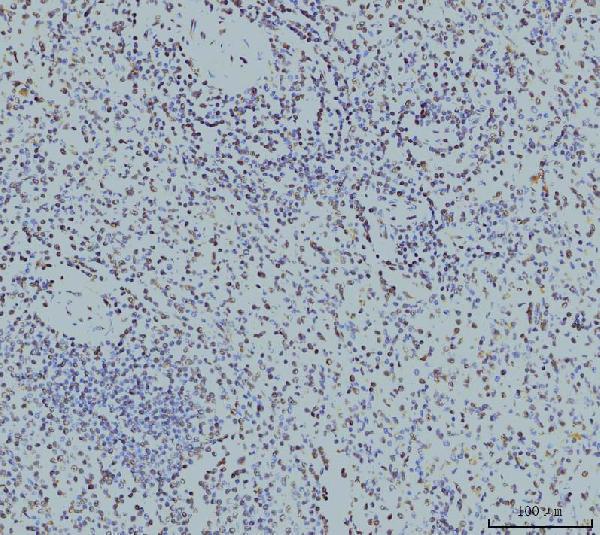
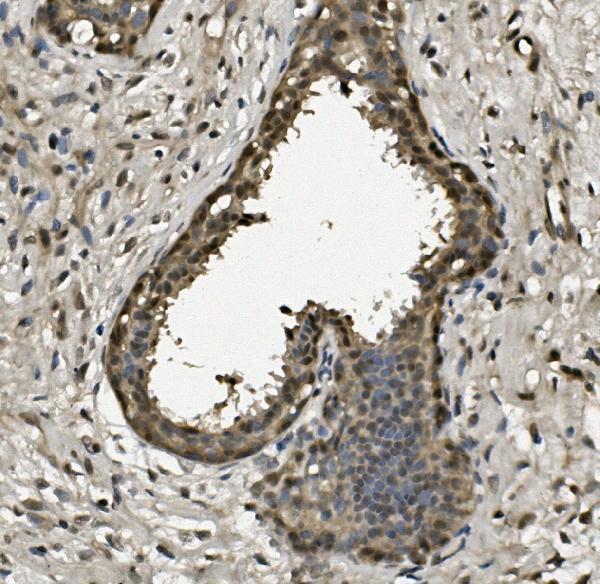
Real IHC data IHC analysis of RPA32/RPA2 using anti-RPA32/RPA2 antibody (M02067-2). RPA32/RPA2 was detected in a paraffin-embedded section of human spleen tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml mouse anti-RPA32/RPA2 Antibody (M02067-2) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-RPA32/RPA2 Antibody ® (monoclonal, 3B2E9)
Cat # M02067-2
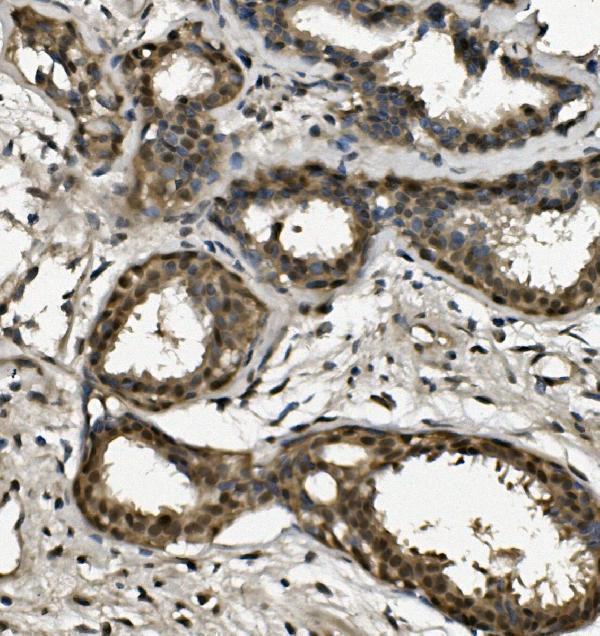
Real IHC data IHC analysis of RPA32/RPA2 using anti-RPA32/RPA2 antibody (A02067-1). RPA32/RPA2 was detected in paraffin-embedded section of human mammary cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-RPA32/RPA2 Antibody (A02067-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-RPA32/RPA2 Antibody ®
Cat # A02067-1
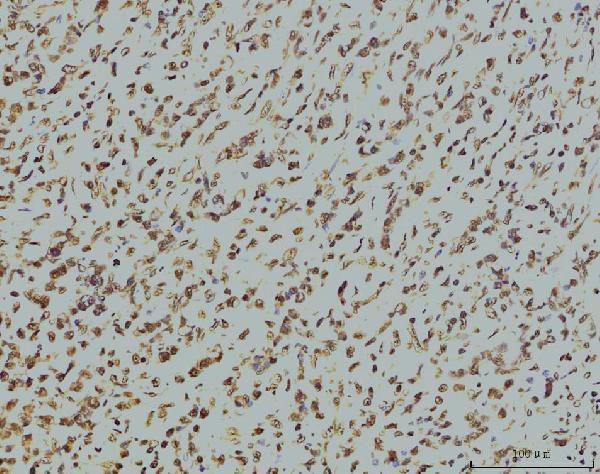
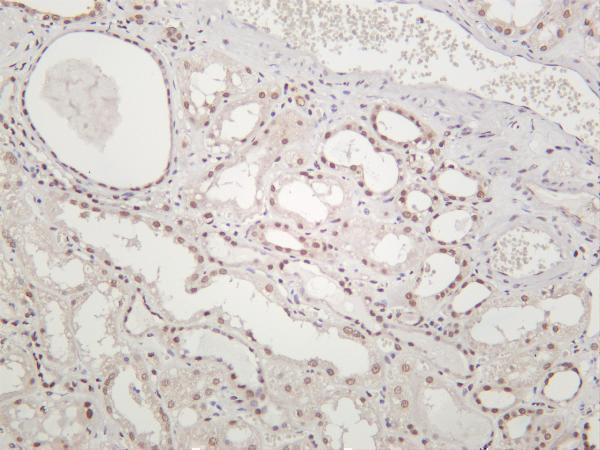
Real IHC data Human kidney was stained with anti-RPA32/RPA2 rabbit antibody
Anti-RPA32/RPA2 Rabbit Monoclonal Antibody
Cat # M02067-5
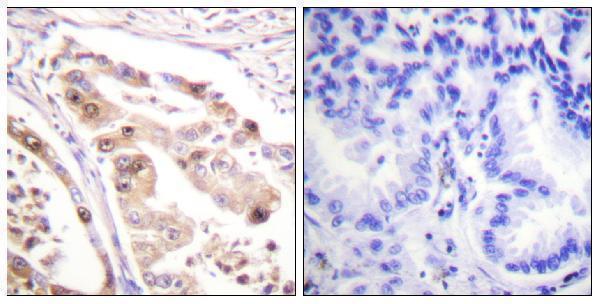
Real IHC data Immunohistochemistry analysis of paraffin-embedded human lung carcinoma tissue, using RFA2 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-RFA2 Antibody
Cat # A30447

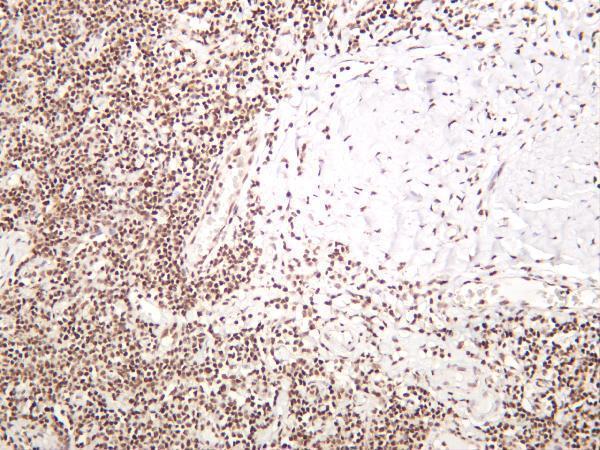
M02067-2 shows human spleen paraffin sections, while A02067-1 shows human mammary cancer paraffin sections (catalog IHC captions). M02067-5 shows human kidney, tonsil, mouse liver, and rat liver; A30447 shows human lung carcinoma paraffin sections (catalog IHC captions).

Which to pick: For human paraffin-section IHC, M02067-2 is a mouse monoclonal with an EDTA pH 8.0 retrieval and DAB example; the caption does not report the fixative (catalog host and IHC caption). For IF/ICC, A02067-1 has both applications listed and a HeLa cell IF image (catalog applications and IF caption). For human, mouse, or rat tissue IHC, choose M02067-5 for its listed reactivity and tissue images across all three species; its captions do not report fixation or processing (catalog reactivity and IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P15927 (RFA2_HUMAN, Replication protein A 32 kDa subunit).
  2. Human Protein Atlas. RPA2 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. RPA2 subcellular location (ICC-IF): Localized to the nucleoplasm and nuclear bodies..
  4. Human Protein Atlas. RPA2 antibody validation summary (3 antibodies).
  5. Markers associated with genomic instability, immunogenicity and immune therapy responsiveness in Metaplastic carcinoma of the breast: Expression of γH2AX, pRPA2, P53, PD-L1 and tumor infiltrating lymphocytes in 76 cases. BMC cancer 2022 — PMC9743555.
  6. S4S8-RPA phosphorylation as an indicator of cancer progression in oral squamous cell carcinomas. Oncotarget 2017 — PMC5354728.
  7. Identification of stroke-associated-antigens via screening of recombinant proteins from the human expression cDNA library (SEREX). Journal of translational medicine 2015 — PMC4344740.
  8. Unravelling the clinicopathological and functional significance of replication protein A (RPA) heterotrimeric complex in breast cancers. NPJ breast cancer 2023 — PMC10063624.
  9. PubMed PMID:2406247 — UniProt-cited evidence.
  10. PubMed PMID:16710414 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.