This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic SATB2 IHC in paraffin sections using nuclear staining as the readout (HPA tissue IHC). Colon or rectum endocrine cells and cortical neurons provide positive tissue references; adipocytes provide a negative cell reference (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Selective nuclear staining in intestine and brain (HPA tissue IHC) | |
| Staining pattern | Nuclear staining in intestinal endocrine cells and neuronal subsets (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | Intestinal staining is selective for endocrine cells (HPA tissue IHC) | |
| Regulation | Expression varies across brain regions (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope coverage is unspecified (UniProt) |
The catalog antibody protocol is paired with two published chromogenic IHC protocols for SATB2 in odontogenic tumors and sarcomas (PMC13535953; PMC5106294).
| Sample | Paraffin-embedded human stomach cancer tissue; fixative not specified (datasheet M02588) |
| Fixation | Image fixative and duration unreported (datasheet M02588); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit monoclonal (clone ADI-19) anti-SATB2, 1:50 (datasheet M02588) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | SATB2-positive staining in endocrine cells of appendix (HPA tissue IHC: High). HPA tissue profile: Selective nuclear expression in large intestine and subsets of neuronal cells in brain. No signal in the no-primary control. |
SATB2 is a nuclear matrix protein with no transmembrane segment (UniProt Q9UPW6 topology and subcellular location). In paraffin-section IHC, expect selective nuclear staining in large-intestine endocrine cells and subsets of brain neurons (HPA: tissue IHC profile). HPA rates the tissue pattern Enhanced, citing high consistency between antibody staining and RNA expression (HPA: tissue IHC reliability). Interpret signal by both its compartment and the identity of stained cells.
| Distinct nuclear staining in colon or rectum endocrine cells, or cerebral-cortex neuronal cells. | This matches HPA's High staining annotations for those cell and tissue pairs (HPA: tissue IHC). A positive result need not label every cell: the reported pattern is selective (HPA: tissue IHC profile). |
| Predominantly cytoplasmic staining with little or no nuclear signal in an expected positive population. | Treat this as a compartment mismatch requiring investigation: SATB2 is assigned to the nuclear matrix (UniProt Q9UPW6), while HPA reports selective nuclear tissue staining (HPA: tissue IHC). Cytoplasmic color alone does not establish a true SATB2-positive cell. |
| Strong staining across cell types outside the annotated positive population in colon or cerebral cortex. | Check for antibody cross-reactivity or endogenous chromogenic detection activity (general IHC practice). HPA assigns High staining specifically to colon endocrine cells and cerebral-cortex neuronal cells (HPA: tissue IHC); its annotations are a comparison, not an exhaustive cell atlas. |
| Diffuse color across nuclei, cytoplasm, and surrounding tissue, with poor cell boundaries. | The distribution is difficult to score against HPA's selective nuclear pattern (HPA: tissue IHC profile). Review blocking, wash conditions, chromogen development, and detection controls as general IHC troubleshooting steps. |
| No nuclear staining in a run that includes colon endocrine cells or cerebral-cortex neuronal cells. | Both are annotated High by HPA (HPA: tissue IHC), so an entirely negative known-positive control raises concern about assay performance. Check tissue preservation, primary-antibody handling, retrieval, and detection using general IHC practice; HPA supplies no SATB2-specific fixation effect. |
| Compartment | SATB2 is assigned to the nuclear matrix and has no transmembrane segment (UniProt Q9UPW6). Score nuclear staining first; broad membrane staining conflicts with that topology and with HPA's selective nuclear IHC profile (HPA: tissue IHC). |
| Tissue and cell selection | Appendix, colon, and rectum endocrine cells and cerebral-cortex neurons are High; small-intestine endocrine cells and testis pachytene spermatocytes are Medium (HPA: tissue IHC). Compare like cell types when judging intensity, because a whole-section average can obscure selective staining. |
| Low and undetected comparators | HPA reports Low neuronal staining in hippocampus and caudate, Low signal in kidney proximal tubules, and Not detected staining in adipocytes of adipose tissue (HPA: tissue IHC). A low-signal tissue is a weaker run control than an annotated High population. |
| Evidence strength | HPA labels tissue IHC reliability Enhanced and lists multiple antibodies with Enhanced IHC validation (HPA: tissue IHC; HPA: antibody validation). This supports the reported pattern but does not validate every new antibody, retrieval condition, or interpretation of an atypical cell. |
| Protein forms and retrieval | UniProt lists two isoforms, a 1–733 SATB2 chain, and phosphorylation sites (UniProt Q9UPW6). These records do not specify the catalog antibody's epitope or isoform coverage. Antigen retrieval may be optimized as general paraffin-IHC practice; no SATB2-specific fixation or retrieval effect is supplied. |
| IF/ICC Q&A: where should signal appear? | Mainly in the nucleoplasm (HPA: ICC-IF, supported). HPA also lists cytosol, centrosome, and basal body as uncertain additional locations (HPA: ICC-IF). Those uncertain observations do not override the nuclear expectation for tissue IHC (HPA: tissue IHC profile). |
| Situation | Likely cause | Next action |
|---|---|---|
| Known-positive tissue is entirely blank. | A failed staining step is possible when annotated High cells show no signal (HPA: colon endocrine cells; HPA: cerebral-cortex neuronal cells). The supplied sources do not identify a SATB2-specific fixation cause. | Confirm that the expected cells are present, then review the primary antibody, retrieval setup, detection reagents, and a run control in that order (general IHC practice). Do not infer target absence from a failed positive control. |
| Signal appears weak in hippocampus or caudate. | HPA records Low staining in neuronal cells at both sites (HPA: tissue IHC). Weak signal there can fit the reference pattern and is less decisive than absence from a High reference population. | Assess nuclear localization and compare with a High annotated population, such as cerebral-cortex neuronal cells, on a suitable control (HPA: tissue IHC; general IHC practice). |
| A chromogenic slide shows mainly cytoplasmic or membranous color. | That distribution disagrees with SATB2's nuclear matrix assignment and HPA's selective nuclear tissue pattern (UniProt Q9UPW6; HPA: tissue IHC). Background or nonspecific detection is possible (general IHC practice). | Check nuclear counterstain alignment, examine a negative reagent control, and review primary-antibody dilution and washes (general IHC practice). Base the SATB2 call on convincing nuclear signal. |
| Many unexpected cells stain strongly within an otherwise plausible tissue. | HPA's High calls specify particular endocrine or neuronal cells (HPA: tissue IHC). Cross-reactivity or endogenous detection activity can create extra signal (general IHC practice); an HPA annotation alone cannot identify its cause. | Map stained cells against morphology, run an appropriate primary-antibody omission control, and assess the detection system's endogenous activity controls (general IHC practice). |
| Diffuse background obscures selective nuclear staining. | Excess background can mask the expected cell-restricted pattern (HPA: tissue IHC profile). Inadequate blocking or washing, excessive antibody concentration, and prolonged chromogen development are general IHC possibilities. | Inspect controls and adjust blocking, washes, primary-antibody concentration, or chromogen development one variable at a time (general IHC practice). Reassess whether signal resolves to nuclei in the annotated cells. |
| An HPA Not detected comparator appears strongly positive. | Strong staining in adipose-tissue adipocytes or bone-marrow hematopoietic cells conflicts with their HPA Not detected annotations (HPA: tissue IHC). HPA annotations are reference observations, not proof that every sample must be negative. | Verify cell identity and control performance, then investigate nonspecific staining and endogenous detection activity (general IHC practice). Report the discrepancy instead of converting it into a new expected SATB2 pattern. |
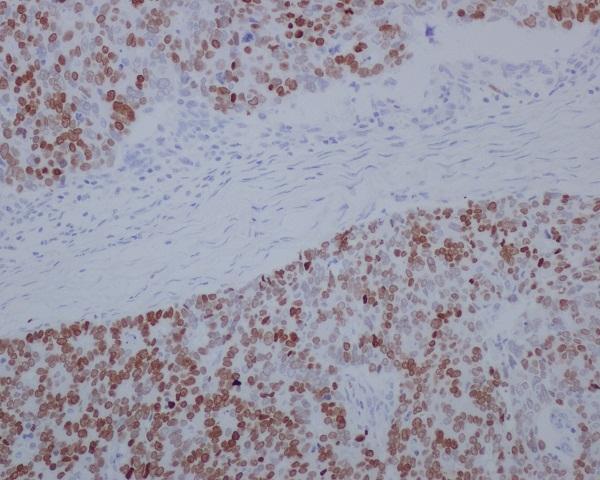
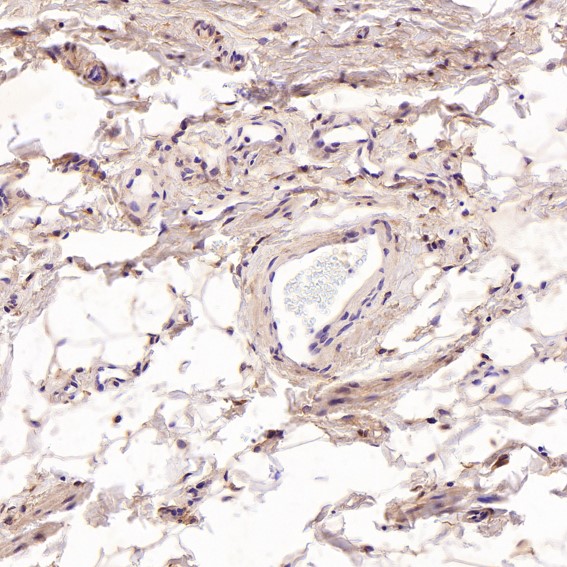
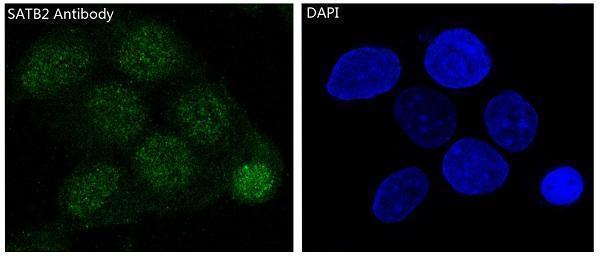
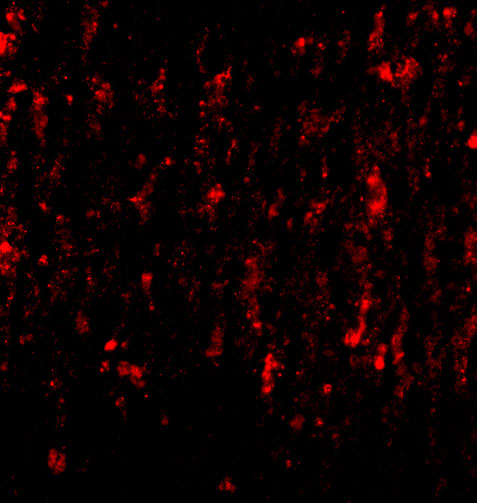


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Endocrine cells | High | Protein (IHC) | HPA → |
| Cerebral cortex | Neuronal cells | High | Protein (IHC) | HPA → |
| Colon | Endocrine cells | High | Protein (IHC) | HPA → |
| Rectum | Endocrine cells | High | Protein (IHC) | HPA → |
| Small intestine | Endocrine cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot SATB2 staining by checking nuclear localisation, cell type and matched controls before changing the chromogenic IHC workflow (UniProt: nuclear matrix; HPA: selective nuclear expression).
The catalog lists SATB2 antibodies reactive with human, mouse and rat samples (catalog: M02588, A02588). The figures show paraffin-section IHC and human brain cell IF, respectively (image captions: M02588, A02588).
M02588 lists IHC and ICC/IF, with an IHC image of paraffin-embedded human stomach cancer (catalog: applications; image caption: M02588). A02588 lists IHC-P and IF, with an IF image of human brain cells (catalog: applications; image caption: A02588).
Which to pick: For tissue IHC, choose M02588: its own image shows staining in a paraffin-embedded human stomach cancer section; the fixative is unreported (image caption: M02588). For IF/ICC, choose M02588 when ICC is required, or A02588 for the pictured human brain cell IF experiment (catalog: applications; image caption: A02588). Both list human, mouse and rat reactivity; M02588 is a rabbit monoclonal, while A02588 has no clone designation in the catalog (catalog: reactivity, host, clone).