This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic SCARB2 IHC on paraffin sections using the IHC-validated antibody at 2 μg/mL (datasheet: A05090-1 IHC-P). Use high staining in colon glandular cells as a positive reference (HPA tissue IHC), then assess cytoplasmic staining intensity and distribution (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining (HPA tissue IHC); lysosome membrane (UniProt) | |
| Staining pattern | Cytoplasmic staining across tissue cell types (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Breast+1 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet A05090); verify before use. | |
| Caveat | Staining–RNA consistency is medium (HPA tissue IHC) | |
| Regulation | Intensity regulation is unreported (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope conservation and position are unknown (UniProt) |
The catalog antibody’s IHC-P protocol accompanies this published SCARB2 protocol for tree shrew tissue sections (PMC12241082).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A05090); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-SCARB2, 2.5 μg/mL (datasheet A05090) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | SCARB2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control. |
SCARB2 is a lysosomal membrane protein with two transmembrane segments and a large lumenal region (UniProt Q14108 topology). In paraffin-section IHC, expect cytoplasmic staining in cells shown as positive by HPA, including glandular, respiratory epithelial, and glial cells (HPA tissue IHC). HPA describes the tissue profile as ubiquitous cytoplasmic expression, with Supported reliability and medium consistency between antibody staining and RNA data (HPA tissue IHC).
| Cytoplasmic staining in colon or duodenum glandular cells, bronchus respiratory epithelial cells, or cerebral cortex glial cells. | These cell and tissue combinations are reported as High by HPA (HPA tissue IHC). Record intensity in the named cell population rather than assigning one score to the whole section. A cytoplasmic result fits HPA's tissue profile; the stain alone does not identify individual lysosomes (HPA tissue IHC; UniProt Q14108 subcellular location). |
| Predominantly nuclear staining, or a sharp cell-surface rim without a cytoplasmic component. | That distribution does not fit HPA's reported cytoplasmic tissue pattern or UniProt's lysosomal membrane assignment (HPA tissue IHC; UniProt Q14108 subcellular location). Treat it as an interpretation concern; check the staining run and antibody validation before calling it SCARB2. |
| Strong signal in breast glandular cells or vaginal squamous epithelial cells. | HPA reports SCARB2 as Not detected in those particular cell populations (HPA tissue IHC). Unexpected staining warrants a check for cross-reactivity or endogenous detection activity (general IHC practice). It does not, by itself, disprove HPA's broader description of ubiquitous cytoplasmic expression (HPA tissue IHC). |
| Diffuse color across cells, extracellular areas, and the section background, obscuring cell boundaries. | A widespread deposit cannot be scored confidently as the cell-associated cytoplasmic pattern reported by HPA (HPA tissue IHC). Review background controls, blocking, wash steps, and chromogen development as general IHC checks; do not assign the diffuse deposit to SCARB2 without a distinct cellular pattern. |
| No staining in the expected positive cells of colon, duodenum, or bronchus. | HPA reports High staining in the specified glandular or respiratory epithelial cells (HPA tissue IHC). A blank result calls for run-level checks of the antibody, detection reagents, and section handling (general IHC practice). It is not enough evidence to conclude that the specimen lacks SCARB2. |
| Tissue and cell population | HPA reports High staining in selected glandular, respiratory epithelial, glial, and cerebellar molecular-layer cells, but Not detected in the listed breast glandular and vaginal squamous epithelial cells (HPA tissue IHC). Select and score controls by the specified cell population, since tissue-wide labels can hide differences between cell types. |
| Location and membrane topology | UniProt places SCARB2 in the lysosomal membrane and annotates transmembrane segments at residues 5–27 and 434–459, with a lumenal region at 28–433 (UniProt Q14108 topology). HPA's paraffin-section readout is cytoplasmic; organelle identity cannot be established from chromogenic localization alone (HPA tissue IHC). |
| Antibody evidence | HPA lists IHC as Supported for HPA018014 and CAB015415, while its tissue profile has Supported reliability with medium staining–RNA consistency (HPA antibodies; HPA tissue IHC). These assessments support using the reported pattern as a reference, but an unexpected result still needs controls and specimen-specific interpretation. |
| Glycosylation and isoforms | UniProt annotates 10 glycosylation sites and 2 isoforms (UniProt Q14108). The supplied record does not identify the catalog antibody's epitope or show an isoform-specific staining difference. Do not infer that glycosylation, retrieval, or isoform choice explains a particular IHC intensity from these annotations alone. |
| IF/ICC Q&A: should IF show the IHC pattern? | HPA calls cytosol the approved ICC-IF location and lists A-431 images; its tissue IHC profile is cytoplasmic (HPA subcellular; HPA tissue IHC). UniProt assigns SCARB2 to the lysosomal membrane (UniProt Q14108 subcellular location). Interpret each assay in its own context; this IHC section does not establish an IF protocol or lysosome-level colocalization. |
| Situation | Likely cause | Next action |
|---|---|---|
| Known positive cells are blank. | A failed staining or detection run is possible; the specified colon, duodenum, and bronchus cell populations are High in HPA (HPA tissue IHC). | Check a positive control section, antibody preparation, detection reagents, and development conditions (general IHC practice). Record which expected cell population was actually present before calling the tissue negative. |
| The whole section has weak, diffuse color. | Background deposition or incomplete washing can obscure cell-associated staining (general IHC practice). | Review the no-primary control, blocking and wash steps, and chromogen development (general IHC practice). Score SCARB2 only where a distinct cytoplasmic pattern is visible in an interpretable cell population (HPA tissue IHC). |
| Signal is mainly nuclear or outlines the plasma membrane. | The location conflicts with the reported cytoplasmic tissue pattern and lysosomal membrane assignment (HPA tissue IHC; UniProt Q14108 subcellular location). | Review section morphology and detection controls, then compare with a positive reference section (general IHC practice). Do not count the discordant compartment alone as confirmed SCARB2. |
| Unexpected strong staining appears in an HPA-listed negative cell population. | Cross-reactivity or endogenous detection activity is possible (general IHC practice); HPA reports breast glandular and vaginal squamous epithelial cells as Not detected (HPA tissue IHC). | Check a no-primary control and compare staining with the surrounding cell populations (general IHC practice). Report the discrepancy by tissue and cell type rather than treating the whole organ as uniformly positive. |
| Positive and negative areas coexist in one section. | Cell populations can differ: HPA assigns levels to named cells within tissues, and reports low tissue RNA specificity overall (HPA tissue IHC). | Score the relevant cell types separately and document whether the signal is cytoplasmic (HPA tissue IHC). Avoid using a single section-wide intensity to explain a cell-specific discrepancy. |
| An IF/ICC image seems more diffuse than the IHC reference. | HPA reports an approved cytosol location for ICC-IF and a cytoplasmic tissue IHC profile; UniProt identifies the protein as lysosomal membrane-associated (HPA subcellular; HPA tissue IHC; UniProt Q14108 subcellular location). | Keep the assay readouts separate. Use the IHC cell and compartment pattern to interpret this paraffin-section result; evaluate IF/ICC localization in its own guide and controls. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Caudate | Glial cells | High | Protein (IHC) | HPA → |
| Cerebellum | Cells in molecular layer | High | Protein (IHC) | HPA → |
Troubleshoot SCARB2 staining in paraffin sections by checking retrieval, compartment, cellular context and controls before comparing signal intensity.
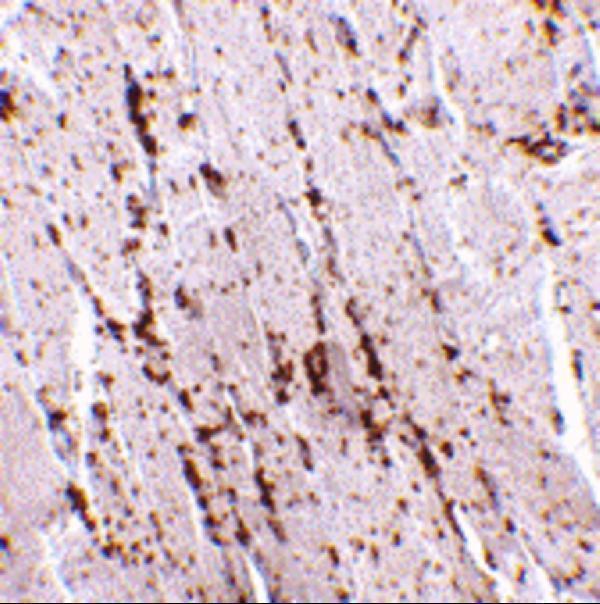
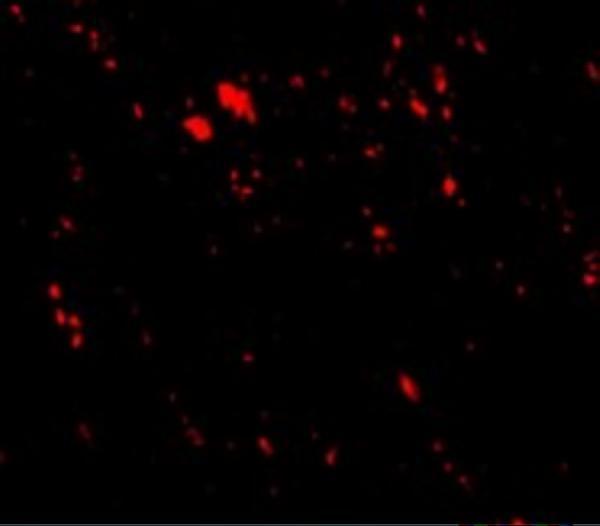
SCARB2 IHC and IF images show human skeletal muscle (A05090 image captions); the antibody lists human, mouse and rat reactivity (catalog: A05090 reactivity).
A05090 is the sole SKU that will render, with IHC-P and IF listed as applications (catalog: A05090 applications). Its images show human skeletal muscle IHC at 2.5 μg/mL and IF at 20 μg/mL (A05090 image captions).
Which to pick: For tissue IHC, choose A05090 based on its human skeletal muscle IHC image (A05090 IHC caption); the caption does not report section processing or fixative (A05090 IHC caption). For IF, choose A05090 based on its human skeletal muscle IF image (A05090 IF caption); ICC validation is unreported (catalog: A05090 applications). For cross-species studies, A05090 lists human, mouse and rat reactivity (catalog: A05090 reactivity), while the supplied IHC and IF images document human tissue only (A05090 image captions).