SDHA / Succinate dehydrogenase [ubiquinone] flavoprotein subunit, mitochondrial · IHC design guide

Design Immunohistochemistry for SDHA

Plan paraffin-section IHC around the granular cytoplasmic pattern seen in tissue (HPA tissue IHC) and SDHA’s inner mitochondrial membrane location (UniProt). Use high-staining cardiomyocytes as a reference (HPA tissue IHC) while optimizing the catalog antibody’s IHC conditions (datasheet: PA1717).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SDHA (IHC for SDHA): expected localisation Granular cytoplasm (HPA tissue IHC); inner mitochondrial membrane (UniProt), antibody PA1717, validated IHC image, and IHC protocol steps
Printable SDHA IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); inner mitochondrial membrane (UniProt), antibody PA1717, controls and protocol steps. Open the full SDHA IHC guide →

SDHA Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); inner mitochondrial membrane (UniProt)
Staining pattern Granular cytoplasm in cardiomyocytes and many other cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PA1717)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Ubiquitous staining limits negative-cell comparisons (HPA tissue IHC)
Regulation No specific regulator annotated (UniProt)
Isoform / epitope Three isoforms; epitope differences unspecified (UniProt)
Section 1

Recommended SDHA IHC & IF Protocols

The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet: PA1717). The published SDHA IHC protocols below cover gastrointestinal stromal tumors and renal tumors (PMC3545041; PMC7528421; PMC8353944).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissue; fixative not specified (datasheet PA1717)
FixationImage fixative and duration unreported (datasheet PA1717); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PA1717); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PA1717)
Primary antibodyRabbit anti-SDHA, 2-5 μg/ml (datasheet PA1717)
Primary incubationOvernight at 4 °C (datasheet PA1717)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet PA1717)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSDHA-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression with a granular pattern. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: PA1717); the gastric GIST protocol used a high-pH retrieval buffer (PMC3545041).
Section 2

What Is the Expected SDHA Staining Pattern?

SDHA is an inner mitochondrial membrane protein with no transmembrane segment (UniProt P31040 topology). In paraffin-section IHC, expect granular cytoplasmic staining across many cell types (HPA: ubiquitous cytoplasmic expression with a granular pattern). Cardiomyocytes, hepatocytes and kidney collecting ducts are among the cells scored High (HPA: tissue IHC). The tissue IHC profile has Enhanced reliability, with medium consistency between antibody staining and RNA expression (HPA: tissue IHC reliability).

What am I looking at on my slide?
Granular cytoplasmic staining in cardiomyocytes, hepatocytes or kidney collecting ducts.This fits SDHA's mitochondrial location (UniProt P31040 subcellular location) and the High staining recorded for these cells (HPA: tissue IHC). Compare granularity and distribution with a validated positive control on the same run (general IHC practice).
Dominant nuclear staining, or a smooth outline around cells instead of cytoplasmic granules.This does not fit the expected IHC pattern (HPA: ubiquitous granular cytoplasmic expression). Review antibody specificity and detection background (general IHC practice). A plasma-membrane signal is reported only as an uncertain additional ICC-IF location (HPA: subcellular).
Strong staining confined to an unexpected cell population while adjacent expected cells show little signal.Check the cell identity and local HPA reference before calling it cross-reactivity: SDHA staining is widespread, and HPA lists no negative tissue (HPA: tissue IHC). If the pattern remains discordant, assess nonspecific antibody binding or endogenous detection activity (general IHC practice).
Uniform haze, precipitate-like deposits or similar color across cells and empty regions.These features do not establish mitochondrial SDHA staining (UniProt P31040 subcellular location; HPA: granular cytoplasmic pattern). Examine no-primary and detection-only controls for background, endogenous enzyme activity or chromogen deposits (general IHC practice).
No granular signal in heart cardiomyocytes or liver hepatocytes.Both are High in the HPA tissue IHC record, so a blank result calls for a run and specimen review (HPA: High in cardiomyocytes and hepatocytes). Check control performance, antibody dilution and detection before interpreting SDHA as absent (general IHC practice).
💡Expected SDHA appearanceCall a positive result when cytoplasmic granules are clearly visible in expected cells, including High-scoring cardiomyocytes or hepatocytes (HPA: tissue IHC); dominant nuclear color or uniform haze does not match the supported mitochondrial pattern (UniProt P31040 subcellular location; HPA: tissue IHC).
How each factor affects the staining
Compartment and topologySDHA is assigned to the mitochondrial inner membrane but has no transmembrane segment (UniProt P31040 topology). Judge IHC by granular cytoplasmic distribution, not a continuous cell-boundary outline (HPA: tissue IHC pattern).
Tissue choice and intensityHPA scores cardiomyocytes and hepatocytes High, but adipocytes and bone-marrow hematopoietic cells Low (HPA: tissue IHC). Use a High-scoring cell population as the positive reference; Low is not a validated negative (HPA: tissue IHC).
Antibody evidenceThe supplied antibodies have different IHC validation statuses: HPA041981 is Supported and CAB034929 is Enhanced (HPA: antibodies). These labels support pattern assessment but do not provide a dilution, retrieval condition or guarantee for another antibody (HPA: antibodies).
Isoforms and processingUniProt lists three SDHA isoforms and a mature chain spanning residues 43–664 (UniProt P31040 isoforms and processing). The supplied evidence gives no antibody epitope, so it cannot establish which isoforms a particular stain detects.
IF/ICC: what location is expected?Mainly mitochondrial staining is supported; an additional plasma-membrane location is uncertain (HPA: subcellular ICC-IF). This ICC-IF observation is context for interpretation, not an IHC-P protocol or proof that membrane staining is the dominant paraffin-section pattern (HPA: subcellular; HPA: tissue IHC).
Fixation sensitivityTarget-specific effects of fixation on SDHA staining are unreported in the supplied UniProt and HPA records. Record the preparation and compare controls when optimizing an IHC run (general IHC practice); do not infer SDHA fixation sensitivity from its topology or HPA intensity.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A known High-scoring control is blank.A failed staining run or unsuitable assay conditions are possible; HPA reports High staining in cardiomyocytes and hepatocytes (HPA: tissue IHC).Confirm that the positive-control section contains the expected cells, then review antibody dilution, retrieval and detection against the validated IHC-P procedure (general IHC practice). No SDHA-specific retrieval setting is supplied here.
The slide shows widespread brown haze without distinct granules.Nonspecific binding or detection background may obscure the granular pattern recorded by HPA (HPA: tissue IHC; general IHC practice).Inspect no-primary controls and review blocking, washes, antibody concentration and chromogen development (general IHC practice). Score SDHA only where a cell-associated granular pattern remains interpretable (HPA: tissue IHC).
Blood-rich or other unexpected areas stain strongly with chromogenic detection.Endogenous detection activity can contribute color independent of the primary antibody (general IHC practice). The HPA record provides no negative tissue against which to assume those areas must be blank (HPA: tissue IHC).Compare a no-primary or detection-only section and apply the detection system's appropriate endogenous-activity control (general IHC practice). Reassess whether staining follows the HPA granular cytoplasmic pattern (HPA: tissue IHC).
Nuclei are the dominant stained structure.Dominant nuclear localization conflicts with the mitochondrial assignment and HPA granular cytoplasmic profile (UniProt P31040 subcellular location; HPA: tissue IHC).Check counterstain and detection-only controls, then compare with a High-scoring tissue control and the antibody's validation record (general IHC practice; HPA: tissue IHC and antibodies).
An unexpected cell type appears positive while nearby cells are faint.Cell composition and intensity vary: HPA reports ubiquitous expression alongside High and Low cell-specific scores (HPA: tissue IHC). Cross-reactivity is possible but cannot be diagnosed from that contrast alone.Identify the stained cells, compare their compartment and granularity with the HPA profile, and use controls to investigate nonspecific color (HPA: tissue IHC; general IHC practice).
A smooth cell-boundary signal is interpreted as SDHA.The supported IHC profile is granular cytoplasmic, while plasma-membrane localization is uncertain in ICC-IF data (HPA: tissue IHC; HPA: subcellular ICC-IF).Review a High-scoring IHC control and antibody validation, and avoid scoring boundary-only color as a clear positive without corroborating granular cytoplasmic staining (HPA: tissue IHC and antibodies).

Sample controls for SDHA IHC & IF

🧪Run heart muscle first; cardiomyocytes should stain (HPA: High in heart muscle cardiomyocytes). HPA detects SDHA in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and expect nuclei within positive cells to lack the mitochondrial staining pattern rather than treating any cell type as a validated negative (HPA: detected in all 45 scored tissues; UniProt P31040 subcellular location).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: SDHA is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SDHA in HeLa, MCF-7, U2OS, KOLF2.1J, with annotated localisation: Mitochondria (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide and a concentration-matched rabbit isotype control for the rabbit catalog antibody; confirm specificity with SDHA knockout material or a validated immunizing-peptide block where available (selected PA1717 tissue-IHC caption: rabbit antibody; standard IHC practice). Quench endogenous peroxidase and distinguish cardiac pigment from DAB signal in heart muscle (standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected PA1717 paraffin-section caption does not state a fixative (selected PA1717 tissue-IHC caption). That caption reports heat-mediated retrieval in EDTA at pH 8.0, but does not establish that retrieval is required under every condition (selected PA1717 tissue-IHC caption). The supplied evidence does not establish whether frozen sections or IF are easier; cardiac pigment can complicate interpretation of chromogenic heart sections (standard IHC practice).

HPA tissue IHC evidence for SDHA

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →
Heart muscle Cardiomyocytes High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: SDHA is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced SDHA IHC Tips

Troubleshoot SDHA staining in paraffin sections by checking retrieval, mitochondrial pattern and controls before comparing signal across cells (UniProt P31040; HPA tissue IHC).

How should I retrieve SDHA when paraffin sections stain weakly?
Start with heat-mediated retrieval in EDTA, pH 8.0 (datasheet PA1717). That condition was used for SDHA staining in a paraffin-embedded human lung cancer section, followed by 2 μg/ml primary antibody overnight at 4°C (datasheet PA1717). If signal is weak, compare retrieved and unretrieved sections from the same block while holding antibody concentration and detection constant (standard IHC practice). Check a tissue with high expected staining, such as heart muscle cardiomyocytes, before increasing retrieval intensity (HPA tissue IHC: High in cardiomyocytes; standard IHC practice). Overretrieval can damage morphology, so judge both granular cytoplasmic staining and tissue preservation (HPA tissue IHC: granular pattern; standard IHC practice).
Could fixation explain inconsistent SDHA staining between paraffin blocks?
Target-specific fixation sensitivity is unknown: the selected PA1717 image describes a paraffin-embedded section but does not state its fixative (datasheet PA1717). Record each block’s fixative and fixation duration, then compare sections processed with the same retrieval and detection conditions (standard IHC practice). Begin with heat-mediated EDTA, pH 8.0 retrieval and 2 μg/ml primary antibody overnight at 4°C, matching the reported staining conditions (datasheet PA1717). Include an internal positive cell population when available, and evaluate morphology alongside signal before attributing a difference to fixation (standard IHC practice). Neither the observed tissue pattern nor SDHA’s membrane association establishes a fixation effect (HPA tissue IHC; UniProt P31040 topology).
What SDHA staining pattern should I accept as mitochondrial in tissue?
Expect a granular cytoplasmic pattern in positive cells (HPA tissue IHC: ubiquitous cytoplasmic expression with a granular pattern). SDHA belongs to mitochondrial complex II and is assigned to the inner membrane despite having no transmembrane segment (UniProt P31040 subunit and topology). In chromogenic sections, compare signal within intact cells to their cytoplasm and nuclei; diffuse nuclear staining alone does not match the expected pattern (HPA tissue IHC; standard IHC practice). Cardiomyocytes and kidney collecting ducts offer examples of cells with high reported staining for pattern comparison (HPA tissue IHC: High). Treat apparent surface staining cautiously because the additional plasma membrane location has uncertain support (HPA subcellular: plasma membrane uncertain).
Can SDHA isoforms or modifications change what this antibody detects?
SDHA has 3 annotated isoforms, but the supplied antibody evidence does not identify which epitopes PA1717 recognizes (UniProt P31040 isoforms; datasheet PA1717). The annotated mature chain spans residues 43–664, and reported modifications include FAD attachment at histidine 99 and alternative modifications at lysine 179 (UniProt P31040 processing and modified residues). Those annotations alone cannot establish that an isoform or modification changes staining, because epitope position and binding effects are unreported (UniProt P31040; datasheet PA1717). If a staining discrepancy matters, obtain epitope information and compare an independently validated SDHA reagent on adjacent sections (standard IHC practice). Keep retrieval and scoring identical during that comparison (standard IHC practice).
How can I check an SDHA pattern by multiplex immunofluorescence?
Use IF as a separate assay and first establish conditions for the IHC-validated antibody; the supplied PA1717 tissue example documents chromogenic staining, not an IF protocol (datasheet PA1717). Pair SDHA with a marker identifying the expected cell type, such as a cardiomyocyte marker in heart muscle, where staining is reported high (HPA tissue IHC: High in cardiomyocytes; standard IF practice). Choose spectrally separated fluorophores and assess an unstained section for autofluorescence before assigning a weak signal (standard IF practice). Because SDHA is associated with the mitochondrial inner membrane and has no transmembrane segment, optimise permeabilisation for access to the antibody’s epitope once its location is known (UniProt P31040 topology; standard IF practice).
How do I reduce diffuse brown background without losing SDHA signal?
First inspect a no-primary control to separate primary-antibody staining from detection background (standard IHC practice). The PA1717 example used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and DAB chromogen; these are reported conditions, not evidence that every block needs them (datasheet PA1717). Apply a peroxidase block and check for endogenous pigment or residual peroxidase signal before increasing primary antibody concentration (standard chromogenic IHC practice). If background remains, compare carefully titrated primary concentrations and wash conditions against a positive control while preserving the granular cytoplasmic pattern (HPA tissue IHC: granular pattern; standard IHC practice). Score cells away from folds and damaged edges (standard IHC practice).
How should I quantify SDHA across sections with different cell mixtures? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and analysis area before scoring, because reported SDHA staining varies among cell types (HPA tissue IHC). For chromogenic staining, record the percentage of positive cells and intensity, then calculate an H-score if intensity grades are reproducible across the batch (standard IHC practice). If counting discrete positive cells, report density per mm² of viable tissue and state the threshold used (standard IHC practice). Normalise to the number or area of the relevant cells, rather than total section area when cell composition differs (standard IHC practice). Compare sections stained and imaged together, excluding folds, necrosis and tissue edges from the measured area (standard IHC practice).
When does apparent SDHA loss reflect biology rather than an IHC artefact?
Interpret loss only when intact cells of the intended type show reduced granular cytoplasmic staining while suitable internal positive cells retain signal (HPA tissue IHC: granular pattern; standard IHC practice). Compare like cell populations: cardiomyocytes have high reported staining, whereas adipocytes are listed as low (HPA tissue IHC). Nuclear-only or sharp edge-restricted staining conflicts with the expected mitochondrial pattern and warrants review for artefact (UniProt P31040 subcellular location; standard IHC practice). Exclude necrotic regions and review the no-primary control for pigment or endogenous peroxidase before assigning a negative result (standard IHC practice). SDHA staining measures detectable protein; it does not by itself establish complex II activity (UniProt P31040 function; standard IHC interpretation).
Boster reagents

Best SDHA / Succinate dehydrogenase [ubiquinone] flavoprotein subunit, mitochondrial IHC Antibodies

IHC images cover human lung and breast cancer sections, mouse heart, and human, mouse, and rat kidney (catalog IHC captions); IF images cover HeLa and U2OS cells (catalog IF captions).

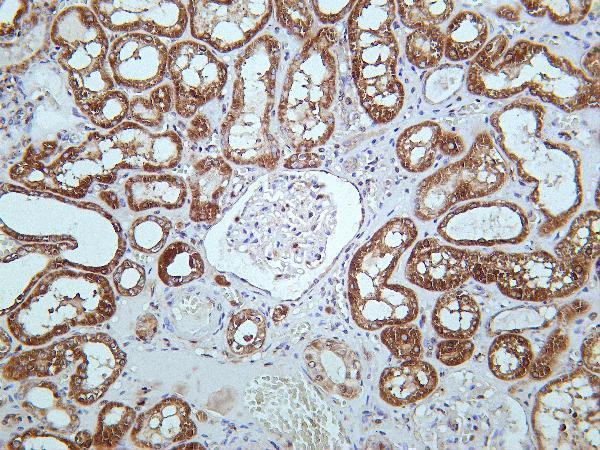
Real IHC data IHC analysis of SDHA using anti-SDHA antibody (PA1717). SDHA was detected in a paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-SDHA Antibody (PA1717) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-SDHA Antibody ®
Cat # PA1717
Real IHC data IHC analysis of SDHA using anti-SDHA antibody (PB9433). SDHA was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-SDHA Antibody (PB9433) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-SDHA Antibody ®
Cat # PB9433
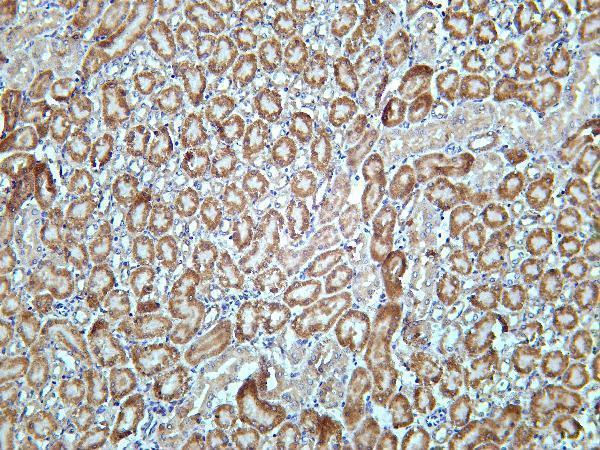
Real IHC data Human kidney was stained with Anti-SDHA rabbit antibody
Anti-SDHA Rabbit Monoclonal Antibody
Cat # M01753-2
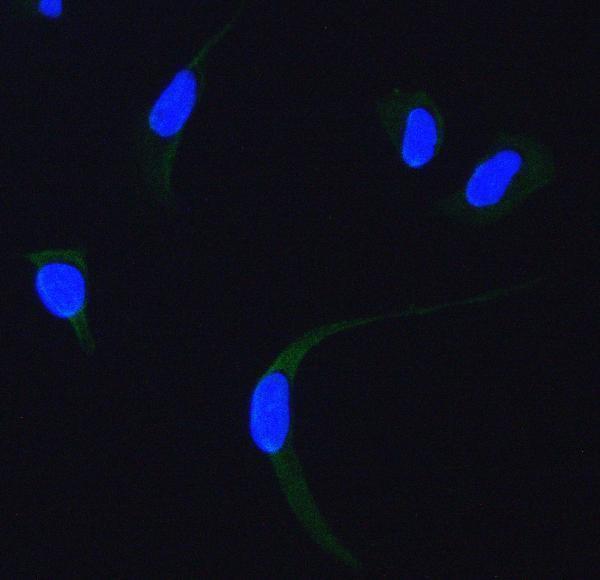
Real IF data IF analysis of SDHA using anti-SDHA antibody (A01753). SDHA was detected in immunocytochemical section of Hela cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 2μg/mL rabbit anti-SDHA Antibody (A01753) overnight at 4°C. DyLight®488 Conjugated Goat Anti-Rabbit IgG (BA1127) was used as secondary antibody at 1:100 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-SDHA Antibody ®
Cat # A01753

PA1717 has a paraffin-section IHC image of human lung cancer (PA1717 IHC caption), and PB9433 has one of human breast cancer (PB9433 IHC caption). M01753-2 has IHC images of human, mouse, and rat kidney (M01753-2 IHC captions); A01753 has an IF image of HeLa cells (A01753 IF caption).

Which to pick: Choose PA1717 or PB9433 for paraffin-section IHC with heat retrieval in EDTA at pH 8.0 (PA1717 and PB9433 IHC captions); the captions do not report the fixative. For IF/ICC, choose A01753 for its HeLa cell IF image (A01753 IF caption), or PB9433 when one antibody is needed for both IHC and IF/ICC (PB9433 applications and image captions). For IHC across human, mouse, and rat samples, M01753-2 is a rabbit monoclonal with kidney images from all three species (M01753-2 catalog and IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P31040 (SDHA_HUMAN, Succinate dehydrogenase [ubiquinone] flavoprotein subunit, mitochondrial).
  2. Human Protein Atlas. SDHA tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. SDHA subcellular location (ICC-IF): Mainly localized to the mitochondria. In addition localized to the plasma membrane..
  4. Human Protein Atlas. SDHA antibody validation summary (2 antibodies).
  5. Immunohistochemical loss of succinate dehydrogenase subunit A (SDHA) in gastrointestinal stromal tumors (GISTs) signals SDHA germline mutation. The American journal of surgical pathology 2013 — PMC3545041.
  6. Molecular Alterations in Dog Pheochromocytomas and Paragangliomas. Cancers 2019 — PMC6563419.
  7. Incidence of succinate dehydrogenase and fumarate hydratase-deficient renal cell carcinoma based on immunohistochemical screening with SDHA/SDHB and FH/2SC. Human pathology 2019 — PMC7528421.
  8. Single nucleotide variants of succinate dehydrogenase A gene in renal cell carcinoma. Cancer science 2021 — PMC8353944.
  9. PubMed PMID:7798181 — UniProt-cited evidence.
  10. PubMed PMID:8142412 — UniProt-cited evidence.
  11. PubMed PMID:10746566 — UniProt-cited evidence.