SLC5A2 / Sodium/glucose cotransporter 2 · IHC design guide

Design Immunohistochemistry for SLC5A2

Use membranous staining of kidney proximal-tubule microvilli as the tissue IHC reference (HPA tissue IHC). For paraffin sections, this guide uses a catalog antibody dilution of 0.5–1 μg/ml with chromogenic detection (datasheet A03748-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SLC5A2 (IHC for SLC5A2): expected localisation Apical cell membrane (UniProt), antibody A03748-1, validated IHC image, and IHC protocol steps
Printable SLC5A2 IHC protocol sheet — expected localisation Apical cell membrane (UniProt), antibody A03748-1, controls and protocol steps. Open the full SLC5A2 IHC guide →

SLC5A2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Apical cell membrane (UniProt)
Staining pattern Membranous staining of kidney proximal-tubule microvilli (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A03748-1)
Positive control ⓘ Kidney
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A03748-1)
Caveat Kidney endogenous biotin may mimic avidin–biotin signal (standard IHC practice; datasheet A03748-1)
Regulation No specific expression regulator reported (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended SLC5A2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A03748-1) appears alongside one published paraffin-section protocol for human and mouse tissues (PMC7587001).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human renal cancer tissues; fixative not specified (datasheet A03748-1)
FixationImage fixative and duration unreported (datasheet A03748-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A03748-1)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03748-1)
Primary antibodyRabbit anti-SLC5A2, 0.5-1μg/ml (datasheet A03748-1)
Primary incubationOvernight at 4 °C (datasheet A03748-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A03748-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSLC5A2-positive staining in proximal tubules (microvilli) of kidney (HPA tissue IHC: High). HPA tissue profile: Membranous expression in proximal tubules in kidney. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6 heat retrieval for the catalog antibody (datasheet A03748-1). The published protocol used no retrieval with its own antibody (PMC7587001).
Section 2

What Is the Expected SLC5A2 Staining Pattern?

SLC5A2 should appear at the apical membrane of kidney proximal tubule cells, particularly their microvilli (UniProt P31639: apical cell membrane; HPA tissue IHC: high in proximal tubule microvilli). This fits a transporter with 14 transmembrane segments (UniProt P31639 topology). HPA rates its tissue IHC pattern Enhanced, citing high consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Strong, sharply outlined staining along the luminal edge of kidney proximal tubules.This is the expected positive pattern: HPA reports high membranous expression in proximal tubule microvilli, and UniProt places SLC5A2 at the apical cell membrane (HPA tissue IHC; UniProt P31639 localisation). Judge the edge against identifiable tubule architecture; color filling the entire cell is less persuasive than a luminal membrane pattern (general IHC interpretation).
Predominantly nuclear, diffuse cytoplasmic, or basolateral staining in proximal tubules.Those compartments do not match the reported apical localisation (UniProt P31639 localisation; HPA tissue IHC). Treat the result as suspect rather than assigning it to SLC5A2; inspect morphology, background, and controls for staining artefacts (general IHC practice). The supplied sources do not establish a separate nuclear or cytoplasmic tissue pattern.
Prominent staining in cells outside kidney proximal tubules, especially an HPA-negative comparison tissue.HPA reports SLC5A2 as kidney enriched and lists adipocytes in adipose tissue and glandular cells in adrenal gland as not detected (HPA tissue IHC). Unexpected color may reflect antibody cross-reactivity or endogenous detection activity; a stain alone cannot distinguish those causes (general IHC practice). Evaluate the relevant negative control before calling expression.
A broad haze covers tubules, interstitium, and tissue-free areas without a clear luminal edge.A nonanatomic distribution is less consistent with HPA's proximal tubule membrane pattern (HPA tissue IHC). Check the detection and background controls, blocking, washing, and section cleanliness as general chromogenic IHC troubleshooting steps (general IHC practice). Background intensity alone does not establish where SLC5A2 resides.
No staining appears in an adequately preserved kidney section with recognizable proximal tubules.This conflicts with HPA's high proximal tubule staining, but one blank slide does not establish biological absence (HPA tissue IHC; general IHC interpretation). Review tissue identification, antibody and detection controls, and the assay's documented conditions before interpreting a negative result (general IHC practice).
💡Expected SLC5A2 appearanceCall a section positive when high staining follows the apical microvillar edge of kidney proximal tubule cells; widespread nonapical or nonanatomic color is suspect (HPA tissue IHC; UniProt P31639 localisation; general IHC interpretation).
How each factor affects the staining
Tissue and cell selectionKidney proximal tubules provide the documented high-signal reference; HPA reports low staining in cells of testis seminiferous ducts and not-detected staining in several listed tissues (HPA tissue IHC). A weak signal outside kidney should therefore be interpreted with its cell type and controls, not treated as equivalent to the kidney pattern (HPA tissue IHC; general IHC interpretation).
Membrane topology and epitopeSLC5A2 has 14 transmembrane segments and both extracellular and cytoplasmic regions (UniProt P31639 topology). The antibody epitope is not identified in the supplied record, so topology alone cannot specify a retrieval method or predict how a particular section treatment will affect staining.
Antibody validationHPA assigns IHC status Enhanced to antibody HPA041603 and reports high agreement between tissue staining and RNA expression (HPA antibody record; HPA tissue IHC). That supports the reported tissue pattern; it does not validate every unexpected compartment or every staining result obtained with another antibody (general IHC interpretation).
Isoforms and processingUniProt lists 2 isoforms and describes a chain spanning residues 1–672, with no signal peptide or propeptide annotated (UniProt P31639). The supplied evidence does not map the IHC antibody's epitope to either isoform, so an observed stain cannot establish isoform identity.
GlycosylationUniProt annotates one glycosylation site at residue 250 (UniProt P31639). The supplied sources give no IHC comparison by glycosylation state; do not use this annotation to explain a weak section or to choose antigen retrieval.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Kidney proximal tubules are blank.The observed result conflicts with the reported high kidney pattern; the slide alone cannot identify whether tissue, primary antibody, or detection failed (HPA tissue IHC; general IHC practice).Confirm proximal tubules are present and interpretable, then review positive and detection controls and the antibody's documented IHC-P conditions (general IHC practice). Do not infer target-specific fixation sensitivity from the supplied sources.
Most color is nuclear, cytoplasmic, or basolateral.That distribution differs from the apical membrane pattern (UniProt P31639 localisation; HPA tissue IHC). Nonspecific staining or interpretation of overlapping structures is possible (general IHC practice).Recheck the luminal boundary at higher magnification and compare with control sections; score only convincing apical membrane staining as the expected result (general IHC interpretation).
An HPA-negative cell population stains strongly.Cross-reactivity or endogenous detection activity is possible; HPA's not-detected entries describe observed cell populations, not a guarantee for every specimen (HPA tissue IHC; general IHC practice).Identify the stained cell type and inspect a primary-omission detection control and an appropriate comparison tissue before assigning SLC5A2 expression (general IHC practice).
Diffuse chromogen obscures the tubule brush border.The background does not follow the reported proximal tubule microvillar pattern (HPA tissue IHC). Detection background, insufficient blocking, or residual reagent can cause broad color (general IHC practice).Compare background controls and review blocking, washing, and detection conditions using standard chromogenic IHC quality checks (general IHC practice).
Only testis seminiferous duct cells show weak color.HPA reports low staining there, whereas kidney proximal tubule microvilli stain high (HPA tissue IHC). Weak testis color is therefore a limited reference for judging assay sensitivity.Use a kidney section with identifiable proximal tubules to assess the expected positive pattern and interpret testis staining against its low HPA level (HPA tissue IHC; general IHC interpretation).
Can an IF/ICC membrane signal substitute for the kidney IHC pattern?HPA summarizes subcellular localisation as membrane but supplies no ICC-IF images or ICC validation status for the listed antibody (HPA subcellular record; HPA antibody record).Use the separate IF/ICC guide for that application; assess this paraffin IHC result against HPA's kidney proximal tubule pattern (HPA tissue IHC).

Sample controls for SLC5A2 IHC & IF

🧪Run kidney first: proximal tubule microvilli should show strong staining (HPA: High in proximal tubules [microvilli]). Run adipose tissue as a negative, with adipocytes expected to be unstained (HPA: Not detected in adipocytes); on the kidney slide, use areas outside proximal tubule microvilli as an internal background reference, without treating them as a validated negative cell population (HPA: High in proximal tubules [microvilli]).
Positive control tissue: Kidney (Proximal tubules (microvilli), HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for SLC5A2; derive a cell-line control from the positive tissue's cell type (Proximal tubules (microvilli)) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control, a matched rabbit IgG control, and SLC5A2 knockout material or a matching immunizing-peptide block if available (selected-SKU caption: rabbit primary antibody; standard IHC practice). For chromogenic detection in kidney, check endogenous peroxidase and biotin background alongside the controls (selected-SKU caption: biotinylated secondary, avidin–biotin complex and DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported, and the selected-SKU paraffin-section caption does not state a fixative (selected-SKU caption: fixative not stated). The caption uses citrate retrieval at pH 6 for 20 minutes, but does not establish that retrieval is required (selected-SKU caption: citrate retrieval, pH 6, 20 minutes); kidney background from the biotin-based detection system warrants checking (selected-SKU caption: avidin–biotin detection; standard IHC practice). Frozen-section or IF ease cannot be ranked from the supplied evidence; no ICC-IF cell-line images are listed (HPA subcellular: no cell lines with ICC-IF images).

HPA tissue IHC evidence for SLC5A2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Kidney Proximal tubules (microvilli) High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced SLC5A2 IHC Tips

Use the expected apical pattern in kidney proximal tubules to guide SLC5A2 staining, controls, and scoring (HPA tissue IHC; UniProt P31639 localisation).

How should I retrieve SLC5A2 in paraffin sections when staining is weak?
Start with heat-mediated retrieval in citrate buffer at pH 6 for 20 minutes (A03748-1 tissue-IHC caption). Run a known positive kidney section alongside the sample, because proximal-tubule microvilli show high SLC5A2 staining (HPA tissue IHC). If signal remains weak, check heating consistency and primary-antibody incubation before changing retrieval conditions; the documented incubation is 1 μg/ml overnight at 4°C (A03748-1 tissue-IHC caption; standard IHC practice). Compare any retrieval adjustment against the same kidney control and preserve a distinct apical pattern when judging improvement (HPA tissue IHC; standard IHC practice).
Could fixation explain loss of apical SLC5A2 staining?
Target-specific sensitivity of SLC5A2 to fixation is unknown from the supplied evidence; the selected paraffin-section caption does not report its fixative (A03748-1 tissue-IHC caption). Record the fixative, fixation duration, and processing history for each specimen before comparing staining intensity across sections (standard IHC practice). Keep those conditions consistent while testing the documented citrate pH 6, 20-minute retrieval on a known positive kidney section (A03748-1 tissue-IHC caption; HPA tissue IHC; standard IHC practice). If staining differs between preparations, repeat them with matched processing and controls before attributing the difference to SLC5A2 abundance (standard IHC practice).
Where should convincing SLC5A2 staining appear in kidney?
Look for membrane staining at the microvillar, apical aspect of kidney proximal tubules, where expression is reported as high (HPA tissue IHC; UniProt P31639 localisation). SLC5A2 is a 14-pass membrane transporter, so a crisp luminal border is more persuasive than diffuse staining throughout a tubule (UniProt P31639 topology; HPA tissue IHC). Evaluate orientation and preserved tubule morphology on the counterstained section before calling a border apical (standard IHC practice). Use a known positive kidney section in the same run to judge whether the chromogenic pattern reproduces the expected compartment (HPA tissue IHC; standard IHC practice).
How do isoforms and membrane topology affect antibody interpretation?
SLC5A2 has 2 annotated isoforms and 14 transmembrane segments, so establish which sequence the antibody recognizes before assigning staining to an isoform (UniProt P31639 isoforms and topology; standard IHC practice). The supplied caption documents tissue staining but does not identify the antibody epitope or demonstrate isoform discrimination (A03748-1 tissue-IHC caption). If epitope information becomes available, map it against extracellular, cytoplasmic, and transmembrane regions, including the annotated glycosylation site at residue 250 (UniProt P31639 topology and glycosylation). Until then, report staining as SLC5A2 immunoreactivity and assess specificity using the expected apical kidney pattern and appropriate controls (HPA tissue IHC; standard IHC practice).
How can IF help assess a questionable IHC localisation pattern?
For a separate IF assessment, pair SLC5A2 with a marker that identifies proximal tubules and inspect whether its signal occupies the expected apical membrane (HPA tissue IHC; UniProt P31639 localisation; standard IF practice). Choose fluorophores after checking kidney autofluorescence, and consider a far-red channel when shorter wavelengths obscure the border (standard IF practice). Match permeabilisation to the antibody epitope: assess an extracellular epitope without permeabilisation first, or use controlled permeabilisation for a cytoplasmic epitope (UniProt P31639 topology; standard IF practice). The supplied tissue caption establishes a chromogenic paraffin-section workflow, while epitope identity and IF performance remain unreported (A03748-1 tissue-IHC caption).
What should I check when DAB obscures the tubule border?
First compare the specimen with a no-primary control to locate background from detection reagents or endogenous tissue activity (standard IHC practice). Include an appropriate peroxidase block before DAB development and inspect whether brown deposit also appears in compartments lacking the expected apical pattern (standard IHC practice; HPA tissue IHC). The documented assay used 10% goat serum, 1 μg/ml primary antibody overnight at 4°C, and a biotin-based DAB detection system (A03748-1 tissue-IHC caption). If background persists, assess blocking, washing, and detection-system contributions on matched sections before interpreting faint tubule staining as SLC5A2 (standard IHC practice).
How should I score SLC5A2 staining across kidney sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scoring compartment as the apical border of proximal tubules before comparing sections, because that is the reported high-expression site (HPA tissue IHC). Record the percentage of positive proximal tubules and an intensity score, or calculate an H-score from the percentage of cells at each intensity (standard IHC practice). Normalise counts to evaluable proximal tubules or apical-border length rather than total tissue area, and exclude poorly preserved regions using the same rule for every specimen (standard IHC practice). Keep exposure to citrate pH 6 retrieval and DAB development consistent across the scored batch (A03748-1 tissue-IHC caption; standard IHC practice).
How can I distinguish true SLC5A2 staining from artefact?
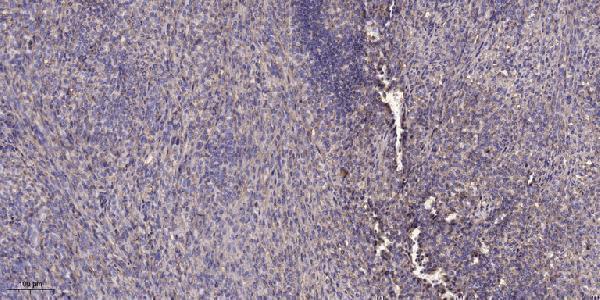
Give greatest weight to a continuous apical signal in morphologically intact proximal tubules, the compartment supported by the kidney staining profile (HPA tissue IHC; UniProt P31639 localisation). Treat diffuse cytoplasmic signal, staining in unrelated cells, and signal concentrated at section edges or necrotic areas as findings requiring control-based review (HPA tissue IHC; standard IHC practice). Compare a known positive kidney section and a no-primary control, and assess endogenous peroxidase activity before accepting weak DAB deposits (HPA tissue IHC; standard IHC practice). A human renal cancer paraffin-section image documents staining with A03748-1, but its caption does not establish the fixative or make every tumour signal specific (A03748-1 tissue-IHC caption).
Boster reagents

Best SLC5A2 / Sodium/glucose cotransporter 2 IHC Antibodies

The catalog shows paraffin-section IHC images for human renal and colon cancer and mouse and rat kidney (catalog: IHC captions). ICC is listed for A03748-1, but no IF image is supplied (catalog: applications/images).

Real IHC data IHC analysis of SLC5A2 using anti-SLC5A2 antibody (A03748-1). SLC5A2 was detected in paraffin-embedded section of human renal cancer tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-SLC5A2 Antibody (A03748-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-SGLT2/SLC5A2 Antibody ®
Cat # A03748-1
Real IHC data Immunohistochemical analysis of paraffin-embedded human Colon cancer. 1, Antibody was diluted at 1:200(4° overnight). 2, Tris-EDTA,pH9.0 was used for antigen retrieval. 3,Secondary antibody was diluted at 1:200(room temperature, 45min).
Anti-SLC5A2/Sglt2 Antibody
Cat # A03748

A03748-1 has paraffin-section IHC images from human renal cancer and mouse and rat kidney (A03748-1 IHC captions). A03748 has a paraffin-section IHC image from human colon cancer (A03748 IHC caption).

Which to pick: For tissue IHC, choose A03748-1 for the depicted renal samples or A03748 for the depicted colon sample; neither caption reports the fixative (catalog: IHC captions). For ICC, A03748-1 is the listed option, although it has no IF image; A03748 lists IHC but not ICC (catalog: applications/images). For work across human, mouse and rat samples, A03748-1 has IHC images in all three species, while both antibodies list reactivity with all three and A03748 is identified as polyclonal (catalog: IHC captions/reactivity/dilution data).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P31639 (SC5A2_HUMAN, Sodium/glucose cotransporter 2).
  2. Human Protein Atlas. SLC5A2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. SLC5A2 subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. SLC5A2 antibody validation summary (1 antibodies).
  5. High-Salt Attenuates the Efficacy of Dapagliflozin in Tubular Protection by Impairing Fatty Acid Metabolism in Diabetic Kidney Disease. Frontiers in pharmacology 2021 — PMC8720966.
  6. Sodium/glucose cotransporter 2 is expressed in choroid plexus epithelial cells and ependymal cells in human and mouse brains. Neuropathology : official journal of the Japanese Society of Neuropathology 2020 — PMC7587001.
  7. Analysis of potential biomarkers for diabetic kidney disease based on single-cell RNA-sequencing integrated with a single-cell sequencing assay for transposase-accessible chromatin. Aging 2023 — PMC10599739.
  8. Bone from Healthy Individuals and Patients with CKD Expresses the Sodium-Glucose Co-transporter-2 (SGLT2). Calcified tissue international 2026 — PMC12982296.
  9. PubMed PMID:1415574 — UniProt-cited evidence.
  10. PubMed PMID:15616553 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.